Acute respiratory distress syndrome (ARDS) is an acute, diffuse, inflammatory injury of the alveolar–capillary membrane that causes protein-rich non-cardiogenic pulmonary oedema, a stiff and heterogeneously aerated lung, and shunt-mediated hypoxaemia. Described by Ashbaugh and colleagues in 1967, it complicates roughly 10% of intensive care admissions and about 23% of invasively ventilated patients.
Its central paradox is that no drug reliably reduces mortality, whereas the way the lung is ventilated does. The ventilated ARDS lung behaves as a small "baby lung": only a fraction of the parenchyma is recruitable, so a tidal volume trivial for healthy tissue becomes injurious. This chapter covers the Berlin definition, the exclusion of cardiogenic oedema, the ventilator mechanics that determine outcome, the adjunctive evidence, and VV-ECMO referral.
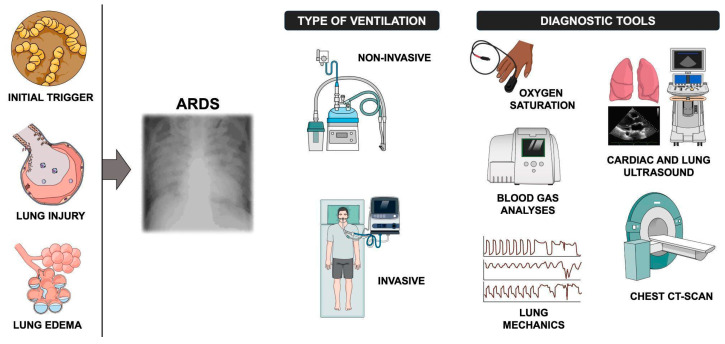 Figure 1: The pathogenesis of ARDS, its representative chest radiograph, the spectrum of non-invasive and invasive ventilatory support, and the bedside tools used to grade severity. (Source: Biuzzi C, et al. Diagnostics (Basel) 2025. DOI: 10.3390/diagnostics15151930).
The Berlin Definition (2012)
Berlin replaced the 1994 criteria, which were criticised for arbitrary timing and unreliable radiography, and was validated against 4,188 patients. It requires all four of the following:
- Timing — onset within 1 week of a known insult, or new or worsening respiratory symptoms.
- Chest imaging — bilateral opacities on radiograph or CT not fully explained by effusion, lobar collapse, lung collapse or nodules.
- Origin of oedema — respiratory failure not fully explained by cardiac failure or fluid overload; echocardiography is required when no ARDS risk factor is present.
- Oxygenation — the arterial-to-inspired oxygen ratio, measured on PEEP of at least 5 cmH₂O.
The $P_aO_2/F_iO_2$ ratio, always measured on PEEP ≥ 5 cmH₂O, defines severity with graded mortality.
| Severity | $P_aO_2/F_iO_2$ on PEEP ≥ 5 cmH₂O | Approximate mortality |
|---|---|---|
| Mild | 201–300 mmHg | ~27% |
| Moderate | 101–200 mmHg | ~32% |
| Severe | ≤ 100 mmHg | ~45% |
where $P_aO_2$ is arterial oxygen tension in mmHg and $F_iO_2$ the inspired fraction as a decimal. It is a marker of severity rather than of injury, because it ignores PEEP, distending pressure and the work required to achieve that oxygenation.
Radiograph reliability is poor (CT is more sensitive but not required), and Berlin deliberately abandoned the pulmonary artery occlusion pressure threshold because the wedge is often uninterpretable on PEEP. A 2023–2024 global consensus later extended the framework to non-intubated patients on high-flow nasal oxygen, but the Berlin strata remain the reference standard for the intubated adult with an arterial line.
Differential Diagnosis and the Cardiogenic Exclusion
ARDS is a syndrome without a pathognomonic test. Inflammatory injury is direct — pneumonia, aspiration, inhalation, contusion, fat embolism — or indirect, mediated by circulating cytokines in sepsis, trauma, pancreatitis, transfusion and burns. Indirect injury produces a more recruitable lung that responds better to PEEP; direct injury is more consolidated.
Hydrostatic oedema is the critical mimic, and Berlin requires it to be excluded rather than assumed absent.
- Echocardiography is decisive: left ventricular systolic or diastolic dysfunction, left atrial enlargement, a restrictive inflow pattern (raised $E/e'$), valvular disease or global hypokinesis favour a cardiogenic mechanism.
- Natriuretic peptides are supportive only: a BNP below 100 pg/mL or NT-proBNP below 500 pg/mL makes cardiogenic oedema unlikely, but sepsis and renal failure raise both, so a high value cannot exclude ARDS.
- Pulmonary artery occlusion pressure below about 18 mmHg was historically confirmatory but is no longer required.
The two conditions frequently coexist, which is why fluid strategy matters. Histologically, most cases show diffuse alveolar damage (DAD): endothelial and epithelial injury, protein-rich oedema, neutrophil infiltration and hyaline membranes.
DAD is present in only about half of patients fulfilling the clinical Berlin criteria at autopsy. ARDS is defined clinically because the histology is neither sensitive nor timely; do not equate the definition with a tissue diagnosis.
Lung-Protective Ventilation: The Only Consistent Mortality Benefit
ARDSNet ARMA (2000) randomised 861 patients to 6 mL/kg predicted body weight (PBW) with plateau pressure ≤ 30 cmH₂O, or to 12 mL/kg. It stopped early: mortality fell from 39.8% to 31.0%, a benefit no drug has reproduced. Its principles are to limit tidal volume, limit plateau pressure, and accept permissive hypercapnia.
Tidal volume is scaled to predicted body weight, never actual weight — using actual weight in obesity or fluid overload systematically overdoses the lung.
A 175 cm man has a PBW of $50 + 0.91 \times 22.6 \approx 70.6$ kg, so a 6 mL/kg tidal volume is about 420 mL.
The plateau pressure ($P_{plat}$), measured by end-inspiratory occlusion at zero flow, reflects elastic recoil. If it exceeds 30 cmH₂O, tidal volume is reduced in 1 mL/kg steps towards 4 mL/kg. Hypercapnia is tolerated to a pH of roughly 7.20–7.25, with intracranial hypertension and severe right ventricular failure as relative contraindications. A square inspiratory flow waveform lowers peak pressure and makes plateau measurement reliable.
- Treat the cause — drainage, antibiotics, fluid balance.
- Recheck tidal volume against PBW; confirm $P_{plat} \le 30$ cmH₂O.
- Optimise PEEP against driving pressure, not oxygenation alone.
- Prone-position if the P/F ratio stays below 150.
- Consider neuromuscular blockade for refractory dyssynchrony or high driving pressure.
- Refer for VV-ECMO if hypoxaemia remains refractory.
Driving Pressure, Plateau Pressure and Mechanical Power
Tidal volume is injurious in proportion to the strain it imposes on the aerated compartment, and that strain is captured by the pressure change from end-expiration to end-inspiration.
where $\Delta P$, $P_{plat}$ and PEEP are in cmH₂O. Because $\Delta P = V_T / C_{rs}$, it integrates breath size and respiratory-system stiffness. Values below about 15 cmH₂O are associated with survival; each 1 cmH₂O increment above that is linked to higher mortality.
This identity explains why driving pressure outperforms its components: a recruiting PEEP lowers compliance-normalised strain even if $P_{plat}$ rises, while a low tidal volume still too large for a very small baby lung yields a high $\Delta P$ despite an acceptable $P_{plat}$. In Amato's 2015 analysis, $\Delta P$ mediated essentially all of the survival benefit attributed to low tidal volume and higher PEEP, making it the better correlate of harm. Mechanical power generalises the same idea to the total energy delivered per minute.
where $MP$ is in joules per minute, $RR$ in breaths per minute, $V_T$ in litres, and $P_{peak}$ and $\Delta P$ in cmH₂O; the constant 0.098 converts cmH₂O·L to joules.
A ventilator can be protective by tidal volume and injurious by mechanical power: tachypnoea, high peak flow and a high respiratory rate all raise delivered power even at 6 mL/kg. Power above roughly 17–20 J/min is associated with increased mortality, and the 30 cmH₂O plateau and 15 cmH₂O driving-pressure targets are ceilings, not comfortable goals.
Adjunctive and Rescue Strategies
Oxygenation is an unreliable surrogate: some therapies raise $P_aO_2$ without altering outcome, and one widely used manoeuvre improved oxygenation while increasing mortality.
Fluid management (FACTT)
FACTT (2006) randomised 1,000 patients to conservative or liberal fluid. Mortality at 60 days was unchanged, but the conservative arm improved oxygenation and shortened ventilation (about 14.6 versus 18.1 days) and intensive care stay, without more dialysis or vasopressors. After shock resolves, aim for a neutral-to-negative cumulative balance.
Prone positioning (PROSEVA)
PROSEVA (2013) prone-positioned patients with a P/F ratio below 150 on $F_iO_2 \ge 0.6$ and PEEP ≥ 5 cmH₂O for at least 16 hours per session. Twenty-eight-day mortality fell from 32.8% to 16.0% (hazard ratio 0.39). It is the only adjunct with a large, reproducible mortality benefit, indicated in moderate-to-severe ARDS and ideally started within 12–24 hours; the mechanism is homogenisation of the vertical pleural pressure gradient, which recruits dorsal lung.
Target 12 and preferably 16–20 hours per session; benefit is dose-dependent. Protect the eyes, face and pressure points, secure the airway before turning, and allow hours rather than minutes for the response.
Neuromuscular blockade (ACURASYS versus ROSE)
ACURASYS (2010) found a 48-hour cisatracurium infusion in severe ARDS (P/F < 150) improved 90-day survival (hazard ratio 0.68) without increasing weakness. The larger ROSE trial (2019) found no mortality difference. Routine paralysis is therefore unjustified; reserve blockade for refractory dyssynchrony, very high driving pressures, or facilitation of prone positioning and ECMO.
PEEP strategy, recruitment and its harm signal
Higher-versus-lower PEEP trials (ALVEOLI, LOVS) found no overall mortality benefit, although meta-analyses favour higher PEEP in moderate-to-severe ARDS; titrate PEEP to driving pressure and oxygenation rather than to a fixed number. Aggressive recruitment is different: ART (2017) combined a staircase recruitment manoeuvre with decremental PEEP titration and was stopped for excess mortality, 65.3% versus 59.9% (relative risk 1.09).
Aggressive staircase recruitment plus decremental PEEP titration increased six-month mortality in moderate-to-severe ARDS. Recruitment is a monitored rescue consideration, never a default.
Corticosteroids, inhaled vasodilators and VV-ECMO
DEXA-ARDS (2020) gave dexamethasone 20 mg daily for five days, then 10 mg daily for five days, shortening ventilation and improving survival; the case is strongest in COVID-19 ARDS, so reserve a course for moderate-to-severe disease. Inhaled nitric oxide and prostacyclin improve oxygenation transiently but have not reduced mortality and are not routine; they are rescue therapy for refractory hypoxaemia or right ventricular failure. EOLIA (2018) reported 60-day mortality of 35% with ECMO versus 46% with control — not statistically significant (risk ratio 0.76, p = 0.09) — but a quarter of controls crossed over and post-hoc Bayesian analyses suggested benefit.
Refer when, despite optimised protective ventilation and prone positioning, the P/F ratio remains below 80 mmHg for more than 6 hours or below 50 mmHg for more than 3 hours; or when pH stays near 7.25 with $P_aCO_2 \ge 60$ mmHg for more than 6 hours. Refer early rather than as a last resort.
Initial Ventilator Settings and Targets
Every value below is a starting point for titration, not a destination.
| Parameter | Initial setting | Target / safety threshold |
|---|---|---|
| Mode | Volume-controlled (preferred) or pressure-controlled | Either acceptable; VCV eases $P_{plat}$ measurement |
| Tidal volume | 6 mL/kg PBW | Reduce in 1 mL/kg steps to 4 mL/kg if $P_{plat} > 30$ cmH₂O |
| Respiratory rate | 12–16/min (maximum 35/min) | Titrate to pH ≥ 7.30; accept permissive hypercapnia |
| PEEP | 5–10 cmH₂O initially | Titrate against driving pressure and oxygenation; higher in moderate-severe ARDS |
| $F_iO_2$ | 1.0 initially, then wean | Target $S_pO_2$ 88–95% and $P_aO_2$ 55–80 mmHg |
| Plateau pressure | End-inspiratory hold | ≤ 30 cmH₂O |
| Driving pressure | Calculated as $P_{plat} - PEEP$ | ≤ 15 cmH₂O |
| Inspiratory flow | Square waveform, 40–60 L/min (VCV) | Avoid excessive flow that raises mechanical power |
| I:E ratio | 1:1 to 1:2 | Shorten inspiration if air trapping or auto-PEEP appears |
flowchart TD
    A["Acute hypoxaemic respiratory failure on invasive ventilation"] --> B{"Onset within 7 days of a known insult?"}
    B -->|"No"| Z["Reassess for an alternative diagnosis"]
    B -->|"Yes"| C{"Bilateral opacities not explained by effusion, collapse or nodules?"}
    C -->|"No"| Z
    C -->|"Yes"| D{"Not fully explained by cardiac failure or fluid overload?"}
    D -->|"No"| Z
    D -->|"Yes"| E["Measure P/F ratio on PEEP >= 5 cmH2O"]
    E --> F{"P/F ratio"}
    F -->|"201 to 300"| G["Mild ARDS: VT 6 mL/kg PBW, Pplat <= 30 cmH2O"]
    F -->|"101 to 200"| H["Moderate ARDS: higher PEEP, consider neuromuscular blockade"]
    F -->|"<= 100"| I["Severe ARDS: prone >= 16 h/day, neuromuscular blockade"]
    H --> J{"P/F still < 150 after optimisation?"}
    I --> J
    J -->|"Yes"| K["Prone positioning, then consider VV-ECMO referral"]
    J -->|"No"| L["Continue protective ventilation and wean FiO2 and PEEP"]
    K --> M{"Refractory hypoxaemia?"}
    M -->|"Yes"| N["Refer for VV-ECMO"]
    M -->|"No"| L
Tidal volume 6 mL/kg PBW; $P_{plat} \le 30$ cmH₂O; $\Delta P \le 15$ cmH₂O; pH ≥ 7.30 with tolerated hypercapnia; PEEP titrated to driving pressure; $S_pO_2$ 88–95%. Prone at P/F < 150; reserve neuromuscular blockade, recruitment, corticosteroids, inhaled vasodilators and ECMO for defined rescue indications.
Key Takeaways
- Berlin (2012) is the adult diagnostic standard: onset within 1 week of an insult, bilateral opacities not otherwise explained, respiratory failure not fully explained by cardiac failure or fluid overload, and a P/F ratio measured on PEEP ≥ 5 cmH₂O.
- Severity is graded by the P/F ratio — mild 201–300, moderate 101–200, severe ≤ 100 mmHg — with mortality rising from about 27% to 45% across the strata.
- Cardiogenic oedema must be actively excluded, chiefly by echocardiography; natriuretic peptides are supportive only, and the two conditions commonly coexist. The pathological correlate in about half of cases is diffuse alveolar damage with hyaline membranes.
- Tidal volume is scaled to predicted body weight, not actual weight: 6 mL/kg PBW, reduced to 4 mL/kg if $P_{plat}$ exceeds 30 cmH₂O, with permissive hypercapnia accepted.
- Driving pressure ($\Delta P = P_{plat} - PEEP$) is the better correlate of harm than its components, and mechanical power integrates volume, pressure and rate into one measure of delivered energy; target $\Delta P \le 15$ cmH₂O and avoid power above roughly 17–20 J/min.
- Only protective ventilation and prone positioning have a robust mortality benefit. Conservative fluids (FACTT) shorten ventilation without altering mortality; routine neuromuscular blockade failed to reproduce ACURASYS in ROSE; corticosteroids and inhaled vasodilators have narrower roles; and aggressive recruitment (ART) increased mortality.
- VV-ECMO is a rescue for refractory hypoxaemia (EOLIA), and referral should be early, with triggers including a P/F ratio below 80 for more than 6 hours or below 50 for more than 3 hours.