An acute exacerbation of chronic obstructive pulmonary disease (AECOPD) is the commonest cause of acute hypercapnic respiratory failure, and the patient who arrives tachypnoeic, sweating, and drowsy is running out of time. The threat is not simply hypoxaemia. Years of emphysema and small-airway inflammation have produced expiratory flow limitation, a long respiratory time constant, and a lung that cannot empty before the next breath begins. Positive-pressure ventilation — the very treatment that rests the respiratory muscles and corrects gas exchange — can accelerate that failure if it is applied with ordinary settings.
The clinician therefore faces a counter-intuitive task. The instinct to normalise the arterial carbon dioxide tension by increasing minute ventilation is precisely the instinct that shortens expiratory time, worsens air trapping, raises intrathoracic pressure, and can precipitate cardiovascular collapse. Good ventilatory care of the obstructed patient is measured hypoventilation, deliberate tolerance of hypercapnia, and an obsession with the expiratory limb of the flow–time waveform.
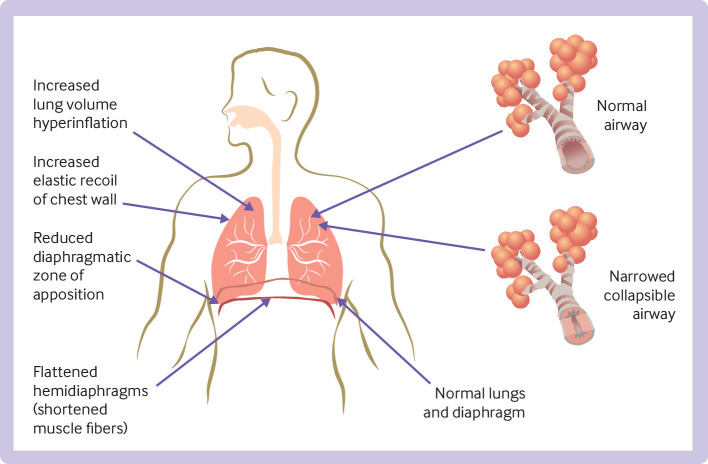 Figure 1: Hyperinflation shortens the respiratory muscles and loads the chest wall, and positive-pressure support offsets that load while splinting collapsible airways to improve expiratory emptying. (Source: Hatipoğlu U, Aboussouan LS. BMJ Medicine 2022. DOI: 10.1136/bmjmed-2022-000146).
Pathophysiology of the Exacerbation
Expiratory Flow Limitation and Airway Collapse
An exacerbation — most often infection, occasionally air pollution or failure of maintenance therapy — adds mucosal inflammation, bronchospasm, and mucus to airways that were already narrowed. Luminal resistance rises. The decisive mechanism of expiratory flow limitation in emphysema, however, is dynamic collapse. Loss of elastic recoil lowers the pressure that tethers the airways open while raising compliance, so during expiration pleural pressure exceeds the pressure within the collapsible intrathoracic airways downstream of the flow-limiting segment. Flow becomes independent of effort — the lung behaves as a Starling resistor — and a greater expiratory effort produces no greater flow, and may produce less: the harder such a patient exhales, the more gas is trapped.
Both determinants of the expiratory time constant are deranged:
$$\tau = R \times C$$where $\tau$ is the expiratory time constant ($\text{s}$), $R$ is airway and respiratory-system resistance ($\text{cmH}_2\text{O}\cdot\text{L}^{-1}\cdot\text{s}$), and $C$ is respiratory-system compliance ($\text{L}/\text{cmH}_2\text{O}$). A healthy adult has $\tau \approx 0.5\ \text{s}$; a patient with severe COPD may have $\tau \geq 1.5$–$2.0\ \text{s}$.
Dynamic Hyperinflation and Intrinsic PEEP
Exhalation is exponential:
$$V(t) = V_0 \times e^{-t/\tau}$$where $V_0$ is the end-inspiratory volume above the relaxation volume ($\text{mL}$) and $t$ is time ($\text{s}$). Complete emptying is asymptotic, so about three time constants are needed to exhale 95% of the tidal volume and four to reach 98%. With $\tau = 2\ \text{s}$ that demands 6–8 seconds of expiration, which a patient breathing at 25 breaths/min does not have. Each breath therefore begins before the previous one has finished emptying.
When expiratory time is shorter than the time needed for the lung to return to its relaxation volume, end-expiratory lung volume climbs breath by breath — dynamic hyperinflation. The alveoli then remain positively pressurised at end-expiration relative to the airway opening, and this elastic recoil pressure is intrinsic PEEP (auto-PEEP, $PEEP_i$). It is a real pressure, not an artefact of the ventilator.
The volume still trapped at end-expiration follows directly:
$$V_{trapped} = V_0 \times e^{-T_E/\tau}$$so trapping grows with every increment in respiratory rate, tidal volume, or inspiratory time, and with every second that expiratory time is shortened. Because $\tau$ is fixed by disease, the ventilator can only manipulate time.
The Work of Breathing and the Threshold Load
Intrinsic PEEP is a threshold load. Before inspiratory flow can begin, the inspiratory muscles must lower alveolar pressure below the airway opening pressure — overcoming $PEEP_i$ and then the ventilator's trigger threshold. If the patient cannot generate that sum, the effort is wasted: an ineffective triggering effort that neither opens the inspiratory valve nor delivers a breath.
Total work of breathing rises through three simultaneous routes: a resistive load from narrowed airways, an elastic load from breathing at high lung volume, and the threshold load of $PEEP_i$. Hyperinflation compounds the problem mechanically. At high lung volume the diaphragm is flattened, its zone of apposition is reduced, and its fibres are shortened, so each fibre generates less force for the same neural drive — a length–tension disadvantage that converts a load problem into pump failure. The clinical signature is tachypnoea, accessory muscle recruitment, intercostal indrawing, paradoxical abdominal motion, and finally respiratory alternans and fatigue.
Mechanisms of Hypercapnia
Hypercapnia is never a single defect. Alveolar ventilation falls relative to carbon dioxide production:
$$P_{a\text{CO}_2} \approx \frac{\dot{V}_{\text{CO}_2} \times 0.863}{\dot{V}_A}$$where $P_{a\text{CO}_2}$ is the arterial carbon dioxide tension ($\text{mmHg}$), $\dot{V}_{\text{CO}_2}$ is carbon dioxide production ($\text{mL}/\text{min}$, STPD), $\dot{V}_A$ is alveolar ventilation ($\text{L}/\text{min}$, BTPS), and $0.863$ is a conversion constant. Alveolar ventilation is $\dot{V}_A = (V_T - V_D) \times f$, where $V_T$ is tidal volume, $V_D$ is dead-space volume, and $f$ is respiratory rate.
Every term moves the wrong way. Dead space rises as overdistended alveoli compress their capillaries and $V/Q$ mismatch is exaggerated. Carbon dioxide production rises with fever, sepsis, corticosteroids, and the work of breathing that hyperinflation inflates. Muscles fatigue, and drive is blunted in chronic retainers. Crucially, raising $f$ to lower $P_{a\text{CO}_2}$ can be self-defeating: less expiratory time means more trapping, more dead space, and sometimes a higher $P_{a\text{CO}_2}$ than before.
Tachypnoea shortens expiratory time, trapping rises, $PEEP_i$ rises, the work of breathing rises, and the patient breathes faster still. Positive-pressure ventilation must interrupt this loop, not feed it.
Clinical Recognition and Measurement
The Expiratory Flow–Time Waveform
The expiratory flow–time scalar is the single most useful bedside instrument. Normally expiratory flow returns to zero and stays there for a brief pause. In dynamic hyperinflation the expiratory limb is truncated: flow is still positive at the instant the next inspiration begins, and the curve never touches the baseline. The volume–time trace carries the same information, the expiratory volume failing to return to its starting point. In a passively ventilated patient this observation alone justifies lengthening expiratory time before any blood gas returns.
End-Expiratory Hold and the Measurement of Auto-PEEP
In a relaxed, passive patient, an end-expiratory hold for one to two seconds equilibrates alveolar and airway pressure and displays total PEEP, so intrinsic PEEP is their difference:
$$PEEP_i = PEEP_{tot} - PEEP_{ext}$$where $PEEP_i$ is intrinsic (auto-)PEEP, $PEEP_{tot}$ is the total end-expiratory occlusion pressure, and $PEEP_{ext}$ is the extrinsic PEEP set on the ventilator — all in $\text{cmH}_2\text{O}$. The manoeuvre is unreliable in a patient making inspiratory efforts, because end-expiratory muscle activity distorts the occluded pressure; deep sedation, or oesophageal and gastric manometry, is needed for accuracy. End-expiratory occlusion also reports an average and therefore underestimates the highest regional alveolar pressure in a heterogeneous lung.
Pressure Dissociation: Peak versus Plateau
Peak airway pressure contains both resistive and elastic pressure; the plateau pressure obtained by an end-inspiratory hold isolates the elastic component — the end-inspiratory alveolar pressure. Their difference is the resistive drop across the tube and airways:
$$P_{peak} - P_{plat} = R \times \dot{V}$$where $R$ is resistance ($\text{cmH}_2\text{O}\cdot\text{L}^{-1}\cdot\text{s}$) and $\dot{V}$ is inspiratory flow ($\text{L}/\text{s}$). In severe obstruction $P_{peak}$ may exceed 50 $\text{cmH}_2\text{O}$ while $P_{plat}$ remains acceptable, and that dissociation reassures. A high $P_{peak}$ alone is not the injury to fear. What matters is $P_{plat}$, and above all the driving pressure applied from total PEEP, since $P_{plat} = \Delta P_{elastic} + PEEP_{tot}$. A rising $P_{plat}$ in a deteriorating patient means worsening hyperinflation or a new pneumothorax until proven otherwise.
Haemodynamic Consequences of Raised Intrathoracic Pressure
The hyperinflated chest behaves like a closed compartment under pressure. Raised intrathoracic pressure impedes caval inflow, lowering right-ventricular preload and stroke volume, while compressing alveolar vessels and raising pulmonary vascular resistance, right-ventricular afterload, and the risk of acute cor pulmonale; septal shift then impedes left-ventricular filling. Central venous and pulmonary artery occlusion pressures are spuriously raised. Clinically one sees hypotension, narrow pulse pressure, pulsus paradoxus, distended neck veins, and a tachycardia that gives way to bradycardia and pulseless electrical activity as perfusion fails.
Any obstructed patient who becomes hypotensive on positive-pressure ventilation should be assumed to have dynamic hyperinflation until proven otherwise. The blood pressure is a respiratory variable in this disease.
Deliberate Controlled Hypoventilation
Ventilator Settings
The strategy is named for its intent: accept a higher $P_{a\text{CO}_2}$ in exchange for a lower lung volume. Respiratory rate is the dominant lever, because each additional breath steals expiratory time:
$$T_E = \frac{60}{f} - T_I$$where $T_E$ is expiratory time ($\text{s}$), $f$ is respiratory rate (breaths/min), and $T_I$ is inspiratory time ($\text{s}$). At $f = 12$ and $T_I = 0.8\ \text{s}$, $T_E = 4.2\ \text{s}$; at $f = 20$ it collapses to $2.2\ \text{s}$.
| Parameter | Initial setting | Target or safety threshold |
|---|---|---|
| Mode | Volume- or pressure-controlled assist-control, initially passive | Guarantees tidal volume and inspiratory time |
| Tidal volume ($V_T$) | 6–8 $\text{mL}/\text{kg}$ predicted body weight | Use the lower end if $P_{plat}$ or auto-PEEP is high |
| Respiratory rate ($f$) | 8–12 breaths/min | As low as the chosen pH floor allows |
| Inspiratory flow | 60–80 $\text{L}/\text{min}$ (square wave), or the shortest $T_I$ in pressure control | $T_I \leq 1\ \text{s}$ |
| Inspiratory-to-expiratory ratio | 1:3 to 1:5 | The longest expiratory time achievable |
| Extrinsic PEEP | 0–5 $\text{cmH}_2\text{O}$ if passive; 60–80% of measured auto-PEEP if spontaneously breathing | Never exceed the measured auto-PEEP |
| Plateau pressure ($P_{plat}$) | $\leq 30\ \text{cmH}_2\text{O}$ | End-inspiratory alveolar stress |
| Total PEEP (end-expiratory hold) | $\leq 10$–$15\ \text{cmH}_2\text{O}$ | Surrogate for the degree of hyperinflation |
| $P_{a\text{CO}_2}$ | 50–70 $\text{mmHg}$ or the patient's chronic baseline | Deliberate permissive hypercapnia |
| Arterial pH floor | $\geq 7.20$–$7.25$, ideally $\geq 7.25$ | Individualise to the chronic baseline |
A controlled mode is preferred early because it guarantees the tidal volume and inspiratory time set and allows meaningful plateau and total PEEP measurements. High inspiratory flow shortens $T_I$ and buys expiratory time; leave the flow waveform square rather than decelerating.
Permissive Hypercapnia and the pH Floor
The target is not a normal $P_{a\text{CO}_2}$. A $P_{a\text{CO}_2}$ of 50–70 $\text{mmHg}$, or a return to the chronic baseline, is well tolerated provided pH stays at or above roughly 7.20–7.25; chronic retainers with metabolic compensation tolerate hypercapnia better than the naive patient, and the safe floor should be individualised. Rapid correction of chronic hypercapnia is itself harmful, risking post-hypercapnic alkalosis and cerebral vasoconstriction. Apply permissive hypercapnia cautiously, or not at all, with raised intracranial pressure, severe pulmonary hypertension, severe left-ventricular dysfunction, or a severe coexisting metabolic acidosis — there the acidosis, not the carbon dioxide, is the limiting factor.
Monitoring the Strategy
Adequacy is judged by pH, comfort, and synchrony, not by $P_{a\text{CO}_2}$. Watch the flow–time waveform for a clear end-expiratory pause, measure total PEEP after every setting change, and keep $P_{plat}$ below 30 $\text{cmH}_2\text{O}$. Trapped gas can be quantified by the release volume: a 20–30 second disconnection during apnoea releases the trapped volume, measurable with a spirometer. A blood gas at 30–60 minutes confirms that the chosen minute ventilation is compatible with the pH floor.
When hypercapnia forces a decision, reduce the rate before you reduce the tidal volume. Trading volume for rate lengthens expiratory time; trading rate for volume does the opposite.
Extrinsic PEEP and the Threshold Load
Reducing Inspiratory Effort in Spontaneous Patients
In a spontaneously breathing or assisted patient, extrinsic PEEP below the level of intrinsic PEEP does not inflate the lung further. It raises the end-expiratory airway pressure towards the alveolar pressure, so the inspiratory muscles need generate less additional pressure to reach the trigger threshold and start flow. The threshold load falls, and with it the work of breathing, the number of ineffective efforts, and the patient's distress. Extrinsic PEEP of roughly 60–80% of the measured auto-PEEP is the usual starting point, titrated to greatest comfort and lowest inspiratory effort without any rise in total PEEP. A second benefit is mechanical: positive pressure splints the collapsible, flow-limiting airways open during expiration, which can improve emptying and reduce hyperinflation itself.
When Extrinsic PEEP Worsens Hyperinflation
Once extrinsic PEEP approaches or exceeds the intrinsic PEEP, or is applied to a passive patient who is not flow-limited, it simply adds to end-expiratory alveolar pressure. Total PEEP, end-expiratory lung volume, and intrathoracic pressure rise; venous return and blood pressure fall. The signs are a climbing $P_{plat}$, a rising total PEEP on repeat hold, and worsening haemodynamics after an increase in extrinsic PEEP. Titration must be empirical and re-measured, never assumed.
The 60–80% rule applies to the spontaneously breathing patient in whom the aim is to unload a threshold. In a paralysed, passively ventilated patient there is no threshold to unload, and extrinsic PEEP above 5 $\text{cmH}_2\text{O}$ usually adds hyperinflation. Keep passive extrinsic PEEP low.
Non-Invasive Ventilation as First-Line Therapy
Indications and the Evidence Base
Bilevel non-invasive ventilation (NIV) is the default first-line ventilatory support for acute hypercapnic AECOPD. It assists inspiration, rests the respiratory muscles, and may improve expiratory emptying by splinting the airways, while avoiding the sedation, ventilator-associated pneumonia, and barotrauma of intubation. The evidence is strong. The 2017 Cochrane review pooled 17 randomised trials and 1264 patients: adding NIV to usual care reduced mortality (risk ratio 0.54, 95% confidence interval 0.38–0.76; number needed to treat 12) and intubation (risk ratio 0.36, 95% confidence interval 0.28–0.46; number needed to treat 5), and shortened hospital stay by about 3.4 days. Benefit was similar for milder (pH 7.30–7.35) and more severe (pH < 7.30) acidosis and in intensive-care and ward settings alike.
The classic indication is persistent hypercapnic acidosis despite optimal medical therapy — in practice a pH of about 7.25–7.35 with $P_{a\text{CO}_2}$ above 45 $\text{mmHg}$ — with respiratory distress or a rising $P_{a\text{CO}_2}$. NIV also serves as a ceiling of support for patients with a documented decision against intubation and facilitates weaning in hypercapnic patients.
| Feature | Detail |
|---|---|
| First-line indication | Persistent hypercapnic acidosis despite optimal medical therapy, typically pH 7.25–7.35 with $P_{a\text{CO}_2} > 45\ \text{mmHg}$ |
| Typical settings | Inspiratory positive airway pressure 10–14 $\text{cmH}_2\text{O}$ titrated to comfort and tidal volume; expiratory positive airway pressure 4–6 $\text{cmH}_2\text{O}$; backup rate 10–14 breaths/min |
| Interface | Oronasal mask, with a spacer or forehead pad to reduce pressure injury |
| Reassessment | Arterial blood gas, pH, respiratory rate, and conscious level at one to two hours |
| Failure triggers | No improvement or deterioration in pH, $P_{a\text{CO}_2}$, or consciousness; inability to protect the airway; haemodynamic instability |
Contraindications
Absolute contraindications are cardiac or respiratory arrest, inability to protect the airway or clear secretions, and undrained pneumothorax. NIV is also unsafe with facial trauma, burns, or deformity that prevents a seal; upper-airway obstruction; vomiting or bowel obstruction with a high aspiration risk; and haemodynamic instability requiring vasopressors. Hypercapnic drowsiness is only relative, because it often improves once ventilation begins; agitation, however, commonly predicts failure.
When to Proceed to Invasive Ventilation
NIV is a time-limited trial, and its failure carries a high mortality if intubation is delayed. Proceed to invasive ventilation when there is no improvement in pH, $P_{a\text{CO}_2}$, respiratory rate, or conscious level within one to two hours; when acidosis deepens below pH 7.20; or when coma, inability to protect the airway, agitation requiring sedation, respiratory arrest, or progressive haemodynamic instability develops. An absolute contraindication at the outset is itself an indication to intubate rather than persist.
Set an explicit reassessment time when NIV starts. Failure to improve within one to two hours is a decision point, not a reason to continue hoping.
The Dynamic-Hyperinflation Crisis
Recognition
The hyperinflated chest can decompensate abruptly into a tension physiology. A stable patient becomes profoundly hypotensive, often with a falling expiratory flow signal, a rising plateau pressure, distended neck veins, and a bradycardia that heralds pulseless electrical activity. The classic setting is immediately after intubation of a severely obstructed patient, but the same physiology can follow bag-valve-mask ventilation, an inadvertent increase in respiratory rate, or secretions or a tube kink obstructing exhalation. The principal differential is tension pneumothorax, which may coexist.
Immediate Decompression
The immediate manoeuvre is mechanical and takes seconds. Disconnect the endotracheal tube from the ventilator, removing the driving pressure and letting the lungs empty. Compress the chest bilaterally with the force and rhythm of external cardiac compressions to augment expiratory flow. Deliver oxygen by a self-inflating bag without added PEEP, or by open-circuit oxygen, and reassess blood pressure and expiratory flow within half a minute. If the patient is in arrest, treat as pulseless electrical activity per advanced life support, with continuous attention to decompression and strict avoidance of hyperventilation, which recreates the trapping that caused the arrest. Exclude and decompress a pneumothorax if ultrasound demonstrates one.
Ventilator Changes
Once circulation returns, rebuild the settings around expiratory time. Reduce the rate to 6–10 breaths/min, reduce the tidal volume, shorten inspiratory time by raising the inspiratory flow, and lengthen expiration to an inspiratory-to-expiratory ratio of at least 1:4. Reduce extrinsic PEEP to the minimum. Suction secretions, check the circuit and tube for obstruction, and deepen sedation; add neuromuscular blockade if spontaneous effort and asynchrony persist, since patient-triggered breaths defeat any strategy that depends on a long expiratory time. Recheck total PEEP, plateau pressure, and haemodynamics after every change.
flowchart TD
    A["AECOPD with acute hypercapnic respiratory failure"] --> B["Optimise bronchodilators, corticosteroids, controlled oxygen, treat the trigger"]
    B --> C{"Persistent pH 7.25-7.35 with PaCO2 > 45 mmHg and distress?"}
    C -->|"Yes"| D["Start bilevel NIV; reassess at one to two hours"]
    C -->|"No, pH >= 7.35"| E["Continue medical therapy and watch for deterioration"]
    C -->|"No, pH < 7.25"| F["ICU review; consider a trial of NIV only if no contraindication"]
    D --> G{"pH, PaCO2, and conscious level improving?"}
    F --> G
    E --> G
    G -->|"Yes"| H["Continue NIV, then wean as the exacerbation resolves"]
    G -->|"No"| I["Intubate and ventilate with deliberate controlled hypoventilation"]
flowchart TD
    A["Sudden hypotension, bradycardia, or pulseless electrical activity"] --> B["Suspect dynamic hyperinflation crisis or tension pneumothorax"]
    B --> C["Disconnect the endotracheal tube from the circuit"]
    C --> D["Compress the chest bilaterally to augment exhalation"]
    D --> E["Lung ultrasound to exclude pneumothorax"]
    E --> F{"Blood pressure restored?"}
    F -->|"Yes"| G["Reduce rate to 6-10/min, reduce tidal volume, lengthen expiratory time"]
    F -->|"No"| H["Treat as pulseless electrical activity; continue decompression and avoid hyperventilation"]
    G --> I["Recheck total PEEP, plateau pressure, and haemodynamics"]
    I --> J["Deepen sedation and add neuromuscular blockade if asynchrony persists"]
Key Takeaways
- Dynamic hyperinflation, not hypoxaemia, is the lethal mechanism of ventilating a severely obstructed patient; it reflects a prolonged time constant ($\tau = R \times C$) and an expiratory time too short to empty the lung.
- Intrinsic PEEP is a threshold load that raises the work of breathing; in a passive patient it is measured on an end-expiratory hold as $PEEP_i = PEEP_{tot} - PEEP_{ext}$.
- Flow that never returns to zero before the next breath, on the flow–time waveform, is the earliest and most reliable sign of trapping.
- Treatment is deliberate controlled hypoventilation — tidal volume 6–8 $\text{mL}/\text{kg}$ predicted body weight, rate 8–12 breaths/min, high inspiratory flow, I:E 1:3 to 1:5, plateau pressure below 30 $\text{cmH}_2\text{O}$, and permissive hypercapnia to a pH floor of about 7.20–7.25.
- In spontaneously breathing patients, extrinsic PEEP at roughly 60–80% of measured auto-PEEP reduces the threshold load; in passive patients it usually worsens hyperinflation and should be kept low.
- Non-invasive ventilation is first-line for acute hypercapnic AECOPD (pH 7.25–7.35 with hypercapnia) and reduces intubation and mortality; failure to improve within one to two hours, deepening acidosis, or loss of airway protection mandates invasive ventilation.
- A hypotensive, tension patient must be disconnected from the ventilator immediately and the chest compressed manually to decompress it, followed by a lower rate, smaller tidal volume, longer expiratory time, and consideration of sedation and paralysis.