Status asthmaticus is a severe exacerbation of asthma unresponsive to repeated bronchodilator therapy that threatens exhaustion, hypoxaemia and cardiac arrest. It is one of the few conditions where the ventilator can kill a patient whose gas exchange would otherwise be survivable: the conducting airways are almost closed, so each positive-pressure breath cannot be fully exhaled before the next. Every breath stacks on the trapped volume of the last, inflating the thorax until the heart can no longer fill.
Because the danger is mechanical rather than gasometric, the target differs from that of ARDS. The clinician does not chase a normal $PaCO_2$ or pH, but deliberately hypoventilates, accepts a respiratory acidosis, and buys time for corticosteroids and beta-2 agonists to reverse the obstruction. The organising adage is: give the patient more time to breathe out.
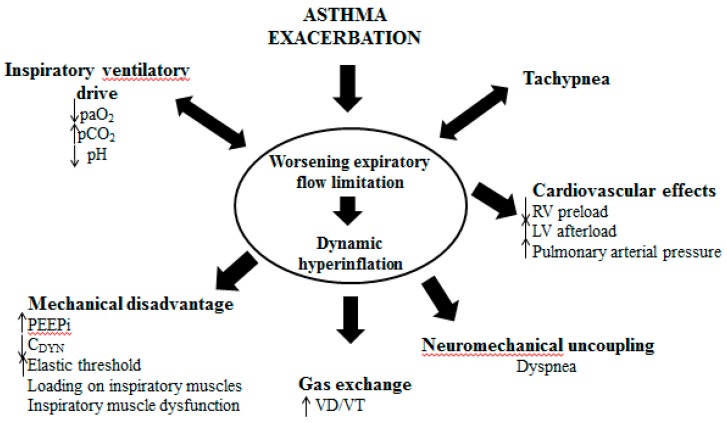 Figure 1: The cascade from dynamic hyperinflation to haemodynamic compromise in acute severe asthma — air trapping raises intrathoracic pressure, impedes venous return, and lowers cardiac output, the mechanism behind post-intubation hypotension and arrest. (Source: Kostakou E, Kaniaris E, Filiou E, et al. J Clin Med 2019. DOI: 10.3390/jcm8091283).
Pathophysiology of the Severe Attack
Bronchospasm, Oedema, and Mucus Plugging
The attack obstructs the airway three ways at once: smooth-muscle contraction narrows the lumen, mucosal oedema thickens the wall, and mucus plugs occlude segments and subsegments. The result is a very high, heterogeneous airway resistance, defined by the pressure–flow relationship
$$R_{aw} = \frac{\Delta P}{\dot V}$$where $R_{aw}$ is airway resistance ($\text{cmH}_2\text{O}\cdot\text{L}^{-1}\cdot\text{s}$), $\Delta P$ the pressure gradient from airway opening to alveolus ($\text{cmH}_2\text{O}$), and $\dot V$ gas flow ($\text{L}\cdot\text{s}^{-1}$). Normal values are $1$–$3\ \text{cmH}_2\text{O}\cdot\text{L}^{-1}\cdot\text{s}$; in severe asthma they rise tenfold or more as flow becomes turbulent.
The Prolonged Expiratory Time Constant
The mechanics of any lung unit are captured by its time constant:
$$\tau = R_{aw} \times C_{rs}$$where $\tau$ is the time constant ($\text{s}$), $R_{aw}$ airway resistance ($\text{cmH}_2\text{O}\cdot\text{L}^{-1}\cdot\text{s}$), and $C_{rs}$ respiratory-system compliance ($\text{L}\cdot\text{cmH}_2\text{O}^{-1}$). A normal lung has $\tau \approx 0.5\ \text{s}$; a severe attack pushes it above $1.0$–$1.5\ \text{s}$ as resistance rises. Emptying is exponential: three time constants exhale 95% of a tidal breath. A patient with $\tau = 1.5\ \text{s}$ therefore needs $4.5$–$7.5\ \text{s}$ of expiratory time per breath — a demand a spontaneous rate of 30 cannot meet.
The volume retained at end-expiration after a tidal volume $V_T$ delivered with expiratory time $T_E$ is
$$V_{trap} = V_T \times e^{-T_E/\tau}$$where volumes are in $\text{mL}$ and times in $\text{s}$. When $T_E \geq 3\tau$, trapped volume falls below about 5% of the tidal volume.
Ventilation–Perfusion Mismatch
Heterogeneous obstruction creates heterogeneous ventilation: poorly ventilated but well-perfused units generate shunt and hypoxaemia, while overinflated units compress their own capillaries and generate dead space. Hypoxaemia is therefore usually modest and corrects with a small increment in inspired oxygen; the dominant abnormality is carbon dioxide retention. Hypercapnia appears late and warns that respiratory arrest is close.
Physiological Consequences: Dynamic Hyperinflation and Its Haemodynamic Cost
Pressure Partitioning: High Peak, Nearly Normal Plateau
Because resistance is high but compliance is comparatively preserved, peak airway pressure ($P_{peak}$) is strikingly elevated while the plateau pressure ($P_{plat}$) after an end-inspiratory hold is only moderately raised. A $P_{peak}$ of $50$–$60\ \text{cmH}_2\text{O}$ generated largely by the resistive load of a narrow endotracheal tube is far less injurious than the same pressure from a stiff, consolidated lung. Plateau pressure and driving pressure, $\Delta P = P_{plat} - PEEP_{tot}$, correlate with alveolar distension and should be held below about $30\ \text{cmH}_2\text{O}$ and $15$–$18\ \text{cmH}_2\text{O}$.
Intrinsic PEEP and the Trapping Relation
Each breath that begins before the previous one has emptied leaves a residual volume and a residual elastic recoil pressure. Measured at the airway after an end-expiratory hold in a passive patient, this is intrinsic PEEP:
$$PEEP_i = PEEP_{tot} - PEEP_{ext}$$where $PEEP_i$ is intrinsic PEEP ($\text{cmH}_2\text{O}$), $PEEP_{tot}$ the total end-expiratory alveolar pressure measured by expiratory occlusion ($\text{cmH}_2\text{O}$), and $PEEP_{ext}$ the applied extrinsic PEEP ($\text{cmH}_2\text{O}$). Values of $10$–$20\ \text{cmH}_2\text{O}$ are common and read out hyperinflation directly; they also impose a threshold load, since the inspiratory muscles must first overcome the whole of $PEEP_i$.
Haemodynamic Collapse and Post-Intubation Hypotension
A spontaneously breathing asthmatic compensates for hyperinflation by generating a very negative pleural pressure on inspiration, preserving venous return. Induction of anaesthesia and positive-pressure ventilation destroy that compensation: sedatives remove vasoconstrictor tone, positive pressure converts the thorax into a pressurised cavity, and the trapped volume already present is compounded by the first ventilated breaths. Right atrial pressure rises and both ventricles become underfilled. The result is post-intubation hypotension, which may progress to pulseless electrical activity and arrest. The safest resuscitation is not fluid or vasopressor but less ventilation: circuit disconnection and manual decompression of the chest.
Hyperinflation raises intrathoracic pressure, abolishing venous return and precipitating PEA arrest. If a ventilated asthmatic becomes hypotensive or loses their pulse, the first action is to disconnect the endotracheal tube, allow the thorax to empty, and begin chest compressions. Escalating vasopressors while leaving the ventilator unchanged is the classic fatal error.
Ventilation Strategy: Controlled Hypoventilation
The strategy is controlled hypoventilation with maximal expiratory time. Every parameter minimises delivered volume relative to available expiratory time and keeps plateau pressure low, accepting hypercapnia to avoid hyperinflation.
Tidal Volume and Respiratory Rate
Tidal volume is set at $6$–$8\ \text{mL}/\text{kg}$ predicted body weight, deliberately lower than the $8\ \text{mL}/\text{kg}$ used routinely. Respiratory rate is kept low, typically $8$–$12\ \text{min}^{-1}$ and as low as $6$–$8\ \text{min}^{-1}$ in the most severe cases. The resulting minute ventilation may be half of normal. Because $T_E$ depends on rate, halving the rate from 20 to 10 doubles expiratory time per breath and is the most powerful single manoeuvre available.
High Inspiratory Flow and Short Inspiratory Time
A high inspiratory flow, of the order of $80$–$100\ \text{L}\cdot\text{min}^{-1}$ in volume-controlled ventilation with a square waveform, shortens inspiratory time for a given tidal volume. Inspiratory time should be the minimum the patient tolerates, with an I:E ratio of approximately $1{:}4$ to $1{:}5$. At a rate of $10\ \text{min}^{-1}$ and a $1{:}4$ ratio, $T_I$ is $1.2\ \text{s}$ and $T_E$ is $4.8\ \text{s}$, comfortably exceeding three time constants; the same rate at $1{:}1$ leaves only $3.0\ \text{s}$ and traps volume.
Permissive Hypercapnia and the pH Floor
Carbon dioxide retention is expected: a $PaCO_2$ of $60$–$80\ \text{mmHg}$ is tolerable provided there is a defined pH floor, conventionally $7.20$, and $PaCO_2$ is normalised gradually during recovery to avoid rebound cerebral vasodilation. A rising $PaCO_2$ on an unchanged deliberate strategy is not a reason to increase the rate. If pH falls below the floor despite optimal mechanics, correct hypovolaemia, abolish dyssynchrony with deeper sedation or neuromuscular blockade, and consider extracorporeal carbon dioxide removal — rather than increasing minute ventilation and worsening trapping.
Initial Settings at a Glance
| Parameter | Initial setting | Target or safety threshold |
|---|---|---|
| Mode | Volume-controlled (square flow) | Guarantees $V_T$ and $T_I$; allows plateau measurement |
| Tidal volume | 6–8 mL/kg PBW | Lowest volume preserving gas exchange |
| Respiratory rate | 8–12/min (as low as 6) | Titrated to $T_E$ and pH, never to $PaCO_2$ alone |
| Inspiratory flow | 80–100 L/min | Shortens $T_I$; higher if tolerated |
| I:E ratio | 1:4 to 1:5 | $T_E \geq 3\tau$; never an I:E < 1:3 |
| Extrinsic PEEP | 0–5 cmH₂O (up to 80% of $PEEP_i$ if triggering is hard) | Reduce threshold load without adding hyperinflation |
| Plateau pressure | < 30 cmH₂O | End-inspiratory hold in a passive patient |
| Driving pressure | < 15–18 cmH₂O | $\Delta P = P_{plat} - PEEP_{tot}$ |
| PaCO₂ / pH | 60–80 mmHg / ≥ 7.20 | Permissive hypercapnia with a defined pH floor; normalise slowly |
Extrinsic PEEP: Rationale and the Risk of Worsening Hyperinflation
The Case for a Low Level of Extrinsic PEEP
The rationale for extrinsic PEEP in severe asthma is not recruitment — the lung is not collapsed — but reduction of the inspiratory threshold load. If $PEEP_i$ is $12\ \text{cmH}_2\text{O}$, the patient must generate a $12\ \text{cmH}_2\text{O}$ drop in alveolar pressure before any flow begins, at high metabolic cost. Applying extrinsic PEEP of about 80% of the measured $PEEP_i$ narrows that gradient and eases triggering without adding to end-expiratory lung volume, because it simply replaces trapped gas pressure.
The Danger of Worsening Hyperinflation
The theory is fragile. Because obstruction is heterogeneous, applied PEEP reaches the least obstructed, often already overinflated, units, while the most obstructed receive little. Above a critical level it therefore increases end-expiratory lung volume, raises $PEEP_i$ further, and aggravates the haemodynamic compromise it was meant to relieve. Measuring $PEEP_i$ requires a passive patient and an end-expiratory occlusion, both unreliable in a fighting asthmatic.
Never apply extrinsic PEEP routinely in status asthmaticus. Start at $0$–$5\ \text{cmH}_2\text{O}$, set it only against a measured $PEEP_i$ in a passive patient, and stop escalating the moment $P_{plat}$ or total PEEP rises. If the patient fights the ventilator, prefer deeper sedation or neuromuscular blockade over raising PEEP.
Pharmacological and Adjunctive Therapy
Mechanical ventilation only temporises; the obstruction itself reverses with sustained pharmacological therapy, so the ventilator is a bridge rather than a treatment.
Bronchodilators and Corticosteroids
Continuous inhaled beta-2 agonists are first-line, given as a nebulised infusion (for example salbutamol $10$–$20\ \text{mg}\cdot\text{h}^{-1}$) rather than boluses, supplemented by inhaled ipratropium. Systemic corticosteroids should be given early and in adequate dose — hydrocortisone $100\ \text{mg}$ every six hours, or methylprednisolone $40$–$60\ \text{mg}$ every six to eight hours — because their anti-inflammatory effect takes hours and underpins recovery; inhaled agents alone are inadequate.
Magnesium, Ketamine, and Volatile Anaesthetics
Intravenous magnesium sulfate ($2\ \text{g}$ over $20\ \text{minutes}$) relaxes smooth muscle and is a reasonable adjunct in the deteriorating patient, though outcome evidence is modest. Ketamine bronchodilates and preserves sympathetic tone, making it a rational induction agent, at the cost of secretions and possible hypertension. Volatile anaesthetics, particularly sevoflurane and isoflurane, are potent, rapidly titratable rescue bronchodilators delivered through an anaesthetic-conserving device; they require anaesthetic expertise and atmospheric scavenging.
Heliox, Non-Invasive Ventilation, and Extracorporeal Support
A helium–oxygen mixture lowers gas density and hence turbulent resistance, reducing work of breathing and trapped volume; evidence is inconsistent, so it is a trial. Non-invasive ventilation has a limited role: it may avert intubation in a responsive patient, but in near-fatal asthma it risks delaying an inevitable intubation and can distend the stomach. Extracorporeal carbon dioxide removal or veno-venous extracorporeal membrane oxygenation is reserved for refractory hypercapnia with pH below the defined floor despite optimal mechanics, or refractory hypoxaemia.
| Adjunct | Mechanism and role | Cautions |
|---|---|---|
| Continuous inhaled beta-2 agonist | Smooth-muscle relaxation; first-line bronchodilation | Tachyarrhythmia, hypokalaemia, tremor |
| Systemic corticosteroids | Suppress airway inflammation; onset over hours | Must be early; inhaled agents insufficient |
| Ipratropium bromide | Anticholinergic; additive bronchodilation | Dry mouth, urinary retention |
| Magnesium sulfate IV | Smooth-muscle relaxation | Hypotension, flushing |
| Ketamine | Bronchodilation with preserved sympathetic tone | Secretions, hypertension, tachycardia |
| Volatile anaesthetic (sevoflurane, isoflurane) | Potent, rapidly titratable rescue bronchodilation | Needs anaesthetic expertise and scavenging |
| Helium–oxygen | Lowers turbulent resistance and work of breathing | Requires high helium fraction; inconsistent evidence |
| Neuromuscular blockade | Abolishes dyssynchrony and breath stacking | Risk of ICU-acquired weakness |
| ECCO₂R or VV-ECMO | Removes carbon dioxide, permitting ultra-low ventilation | Invasive; refractory failure only |
The Crashing Ventilated Asthmatic
Recognition
Deterioration follows a recognisable pattern: rising peak and plateau pressures, falling blood pressure, distended neck veins, and a rising $PaCO_2$ with falling pH despite unchanged settings. A chest that becomes tight and difficult to ventilate, with sudden hypotension and desaturation, should immediately raise tension pneumothorax, commoner here because of overdistension. Classic signs may be absent in the ventilated patient, so the diagnosis is often clinical and must be acted upon immediately.
Immediate Decompression
When hypotension or arrest occurs with a picture of hyperinflation, disconnect the circuit and allow the thorax to empty for $30$–$60\ \text{seconds}$ while compressing the chest manually; this is the fastest way to interrupt the trapping cycle and restore venous return. Simultaneously reduce respiratory rate and tidal volume, deepen sedation, and treat possible pneumothorax with needle decompression or thoracostomy. Vasopressors and fluid come afterwards, as adjuncts rather than substitutes.
- Disconnect the circuit; allow 30–60 seconds of passive expiration.
- Compress the chest manually to expel trapped gas.
- Reduce respiratory rate and tidal volume; lengthen expiratory time.
- Exclude and immediately decompress tension pneumothorax.
- Deepen sedation or paralyse; correct hypovolaemia.
- Reconnect only at settings that guarantee a long $T_E$.
A Status Asthmaticus Management Algorithm
The algorithm escalates from medical therapy, through invasive ventilation with controlled hypoventilation, to rescue adjuncts and extracorporeal support. Each step follows optimisation of the last, and the threshold for disconnecting the ventilator is deliberately low.
flowchart TD
    A["Severe asthma exacerbation: SpO2 < 92%, PEF < 50% predicted, exhaustion"] --> B["Continuous inhaled salbutamol and ipratropium, systemic corticosteroids"]
    B --> C{"Response within 1-2 hours?"}
    C -->|"Yes"| D["Continue medical therapy; consider NIV in a responsive, awake patient"]
    C -->|"No"| E["Exhaustion, silent chest, drowsiness, or rising PaCO2"]
    F["Intubate: ketamine, large-bore tube, volume preload"]
    F --> G["Controlled hypoventilation: VT 6-8 mL/kg PBW, RR 8-12/min, I:E 1:4-1:5"]
    G --> H["Targets: Pplat < 30 cmH2O, PEEP ext 0-5 cmH2O, pH floor 7.20"]
    H --> I{"Hypotension, desaturation, or rising plateau pressure?"}
    I -->|"Yes"| J["Disconnect circuit, manual decompression, exclude pneumothorax, reduce RR and VT"]
    I -->|"No"| K["Escalate adjuncts: magnesium, ketamine, volatile agent, or Heliox"]
    K --> L{"pH < 7.15 with refractory hypercapnia or refractory hypoxaemia?"}
    L -->|"Yes"| M["Consider ECCO2R or VV-ECMO to permit ultra-low ventilation"]
    L -->|"No"| N["Wean as obstruction resolves; extubate when secretion load and strength permit"]
Key Takeaways
- The life-threatening lesion is mechanical: extreme airway resistance prolongs the expiratory time constant ($\tau = R_{aw} \times C_{rs}$), so each breath is delivered before the last has emptied, producing dynamic hyperinflation and intrinsic PEEP.
- Peak airway pressure is high but plateau pressure is comparatively preserved; plateau pressure, driving pressure and trapped volume — not peak pressure — determine alveolar and haemodynamic injury.
- Dynamic hyperinflation raises intrathoracic pressure, impairs venous return, and causes post-intubation hypotension that may progress to PEA arrest.
- Ventilation is deliberate hypoventilation: tidal volume $6$–$8\ \text{mL}/\text{kg}$ predicted body weight, rate $8$–$12\ \text{min}^{-1}$, high inspiratory flow, I:E $1{:}4$ to $1{:}5$, plateau pressure below $30\ \text{cmH}_2\text{O}$, and permissive hypercapnia with a pH floor near $7.20$.
- Extrinsic PEEP is not routine: about 80% of a measured intrinsic PEEP may reduce the threshold trigger load, but excess extrinsic PEEP worsens hyperinflation.
- Pharmacological therapy is definitive — continuous inhaled beta-2 agonists, systemic corticosteroids, and adjuncts such as magnesium, ketamine, volatile anaesthetics or Heliox — with extracorporeal support reserved for refractory hypercapnia or hypoxaemia.
- In the crashing ventilated asthmatic, disconnect the circuit, decompress the thorax manually, reduce rate and tidal volume, and exclude tension pneumothorax before reaching for vasopressors.