Ventilation in acute brain injury is not primarily a treatment for the lung. It is the most rapidly adjustable means of controlling four variables that decide whether an injured brain is further damaged: the arterial carbon dioxide tension ($PaCO_2$), the arterial oxygen tension ($PaO_2$), the intrathoracic pressure that governs cerebral venous return, and the mean arterial pressure ($MAP$) from which cerebral perfusion is derived. The lung is the organ through which these variables are manipulated, but the target organ is the brain.
This reframing matters because the priorities of the two systems diverge. In acute respiratory distress syndrome (ARDS) the ventilator is titrated to tidal volume, plateau pressure and driving pressure to limit ventilator-induced lung injury, and a degree of hypercapnia is accepted. In the patient with a swollen brain, hypercapnia is not benign: it dilates the cerebral resistance vessels, expands cerebral blood volume, and raises intracranial pressure (ICP) at the very moment when intracranial compliance is exhausted. The intensivist therefore manages a coupled system, and every ventilator change must be read twice — once as a lung intervention and once as a neurological one.
The organising principle is the prevention of secondary neurological injury. Hypoxaemia, hypotension, hypercapnia, hyperthermia and seizure activity all extend the initial lesion; the ventilator is used to prevent the first three and to support the treatment of the last two. Targets are consequently written in terms of cerebral perfusion, ICP, oxygenation and carbon dioxide rather than in terms of the lung alone.
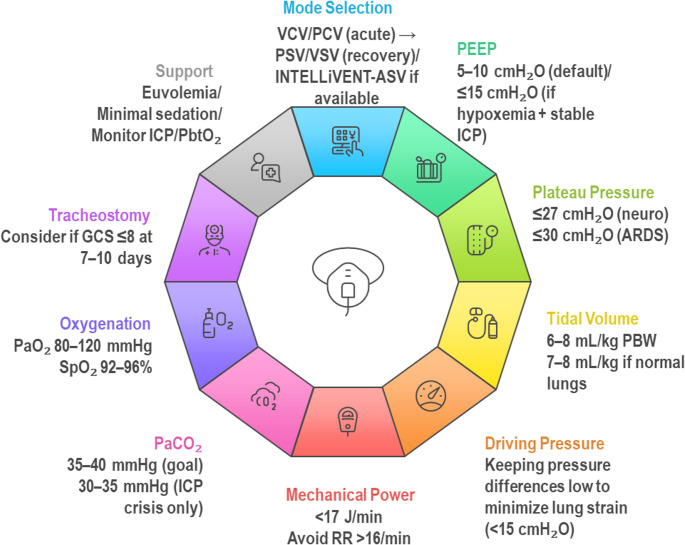 Figure 1: Brain-protective ventilation requires a single set of settings that simultaneously satisfies respiratory and neurophysiological goals — mode selection, moderate PEEP, plateau pressure and driving-pressure limits, normocapnia, and avoidance of both hypoxaemia and hyperoxaemia — because each ventilator change acts on both the lung and the cerebral circulation. (Source: Sharie SA, Almari R, Azzam S, et al. Curr Neurol Neurosci Rep 2025. DOI: 10.1007/s11910-025-01462-2).
The Logic of Neuroprotective Ventilation
Secondary Injury Is the Target
The primary insult — the contusion, the ruptured aneurysm, the occluded vessel — is largely fixed by the time the patient reaches intensive care. What remains modifiable is the secondary cascade: hypoperfusion, cytotoxic and vasogenic oedema, excitotoxicity, inflammation and herniation. Mechanical ventilation lies at the centre of that modifiable space because it determines oxygenation, carbon dioxide clearance and the pressure environment of the thorax at the same time.
The Monro–Kellie Constraint
Inside a rigid cranium the volumes of brain, blood, cerebrospinal fluid and any mass are fixed in sum:
$$V_{brain} + V_{blood} + V_{CSF} + V_{lesion} = \text{constant}$$where each $V$ is a volume ($\text{mL}$). Because the cranium is rigid, an increase in one compartment must be offset by a decrease in another.
The cerebral blood volume is the compartment most rapidly altered by the ventilator — through vasoreactivity to $PaCO_2$ and through cerebral venous drainage. Once the compensation afforded by displacing cerebrospinal fluid and venous blood is exhausted, small additional volume produces steep rises in ICP.
Coupling: One Knob, Many Effects
A single change of respiratory rate alters $PaCO_2$, which alters cerebral blood volume and ICP, which alters cerebral perfusion pressure. The same change alters intrathoracic pressure and systemic venous return, and therefore $MAP$. Positive end-expiratory pressure (PEEP) recruits lung and improves oxygenation, but may impede jugular venous outflow. No ventilator setting has a single consequence, so the bedside rule is to change one variable at a time and to measure the cerebral response — ICP, and where available brain tissue oxygen tension ($PbtO_2$).
Carbon Dioxide: The Most Powerful Control Input
Cerebral Vasoreactivity
Cerebral arterioles respond to changes in $PaCO_2$ across a range extending roughly from 20 to 60 mmHg, and the relationship is approximately linear within it:
$$\frac{\Delta CBF}{CBF} \approx k\,\Delta PaCO_2, \qquad k \approx 0.03\text{–}0.04\ \text{mmHg}^{-1}$$where $CBF$ is cerebral blood flow ($\text{mL}\cdot\text{min}^{-1}$), $\Delta PaCO_2$ is the change in arterial carbon dioxide tension ($\text{mmHg}$), and $k$ is the vasoreactivity slope (fractional change per mmHg). A fall in $PaCO_2$ of 10 mmHg therefore reduces cerebral blood flow by roughly 30–40%. The mechanism is a direct effect of perivascular pH on vascular smooth muscle and is independent of autoregulation, which defends flow against changes in perfusion pressure rather than against changes in $PaCO_2$. The response is fast — seconds to minutes — which is why hyperventilation lowers ICP so reliably, and why the effect is so transient.
Normocapnia Is the Default
For almost every patient with acute brain injury the target is normocapnia, conventionally $PaCO_2$ 35–40 mmHg (4.7–5.3 kPa). Normocapnia preserves the coupling between metabolism and flow and avoids both extremes: hypercapnia, which raises ICP, and hypocapnia, which reduces perfusion and may worsen ischaemia in tissue that is already vulnerable. End-tidal carbon dioxide ($ETCO_2$) is a convenient continuous surrogate, but its gradient from arterial blood varies with dead space, cardiac output and lung disease, so it must be calibrated against arterial blood gases, especially when lung injury coexists.
Therapeutic Hyperventilation: A Narrow, Temporary Rescue
Hyperventilation to $PaCO_2$ 30–35 mmHg remains an accepted temporising measure for imminent cerebral herniation — a unilaterally fixed dilated pupil, a rapidly falling Glasgow Coma Scale, or a precipitous ICP rise — while definitive therapy is arranged. Three caveats define its safe use:
- It is a bridge, not a treatment. Cerebrospinal fluid pH equilibrates over 1–24 hours, after which the vasoconstriction wanes and ICP drifts back toward its previous level.
- It can cause ischaemia. The vasoconstriction that lowers ICP also lowers CBF; in tissue with impaired autoregulation, particularly in the first 24–48 hours after traumatic brain injury, aggressive hypocapnia has been associated with worse neurological outcome.
- It must be reversed gradually. Abrupt restoration of normocapnia after prolonged hyperventilation produces rebound hyperaemia and ICP elevation.
Routine or prophylactic hyperventilation to $PaCO_2$ below 30–35 mmHg in traumatic brain injury is not recommended and may worsen outcome by reducing cerebral perfusion. Reserve it for documented intracranial hypertension or clinical herniation, continue it for the shortest possible time, and monitor perfusion where possible by jugular venous oxygen saturation, $PbtO_2$, or near-infrared spectroscopy.
Oxygenation and Cerebral Oxygen Delivery
Hypoxaemia
Arterial hypoxaemia is directly injurious: it reduces the oxygen content of blood reaching tissue whose extraction is already high. A single episode of $PaO_2$ below 60 mmHg or $SpO_2$ below 90% in a brain-injured patient is associated with worse outcome, and the threshold for concern should be higher than in general intensive care. The pragmatic target is $SpO_2$ 92–96% with $PaO_2$ 80–120 mmHg (10.7–16.0 kPa).
Hyperoxia
A high $PaO_2$ is not a safety margin. Supraphysiological oxygen tension increases reactive oxygen species and promotes reperfusion injury, and it also produces mild cerebral vasoconstriction that reduces CBF. Trials of early hyperoxia in traumatic brain injury and after cardiac arrest have not demonstrated benefit and in some analyses have shown harm. The aim is adequate oxygenation, not maximal oxygenation.
Cerebral Oxygen Delivery
The physiologically relevant variable is not $PaO_2$ alone but cerebral oxygen delivery:
$$CaO_2 = 1.34 \times Hb \times SaO_2 + 0.003 \times PaO_2$$$$DO_2 = 10 \times CBF \times CaO_2$$where $CaO_2$ is the arterial oxygen content ($\text{mL O}_2\cdot\text{dL}^{-1}$), $Hb$ is the haemoglobin concentration ($\text{g}\cdot\text{dL}^{-1}$), $SaO_2$ is the arterial oxygen saturation (fraction), $PaO_2$ is in mmHg, 1.34 is the oxygen-carrying capacity of haemoglobin ($\text{mL O}_2\cdot\text{g}^{-1}$), and 0.003 is the solubility of oxygen in plasma ($\text{mL O}_2\cdot\text{dL}^{-1}\cdot\text{mmHg}^{-1}$); $DO_2$ is whole-brain oxygen delivery ($\text{mL O}_2\cdot\text{min}^{-1}$) and $CBF$ is in $\text{mL}\cdot\text{min}^{-1}$.
Because haemoglobin carries almost all of the oxygen, $DO_2$ is governed far more by haemoglobin and saturation than by $PaO_2$. Raising $PaO_2$ from 100 to 200 mmHg adds only about 0.3 $\text{mL}\cdot\text{dL}^{-1}$ to $CaO_2$ (roughly 1.5%), whereas a fall in haemoglobin from 10 to 8 $\text{g}\cdot\text{dL}^{-1}$ removes about 2.7 $\text{mL}\cdot\text{dL}^{-1}$ (roughly 13%). Transfusion in neurocritical care is therefore a cerebral as well as a systemic decision, and anaemia should not be tolerated merely because the $PaO_2$ is high.
Cerebral oxygen delivery tracks haemoglobin and saturation far more than $PaO_2$. Correct anaemia and desaturation; do not chase a supranormal $PaO_2$.
Positive-Pressure Ventilation, PEEP, and the Cranial Compartment
Intrathoracic Pressure and Cerebral Venous Return
The brain is drained by a low-pressure venous system without valves, so cerebral venous outflow depends on the gradient between cerebral venous pressure and the pressure in the superior vena cava or right atrium. When intrathoracic pressure rises, it can become the effective downstream pressure and impede venous drainage, raising cerebral blood volume and hence ICP. This is the mechanism by which coughing, straining, high airway pressures and patient–ventilator dyssynchrony produce acute ICP surges. The practical corollaries are to keep the head elevated about 30 degrees with neutral alignment, to avoid constricting the neck with tube ties or collars, and to abolish pain, shivering and breath stacking.
PEEP: Usually Tolerated, Occasionally Harmful
The traditional fear that any PEEP raises ICP is not supported by the balance of evidence. Provided systemic arterial pressure is maintained and the lung is recruitable, PEEP up to about 10–15 $\text{cmH}_2\text{O}$ is generally well tolerated and its effect on ICP is small; the improvement in oxygenation and compliance may even lower ICP by reducing $PaCO_2$ and relieving atelectasis. PEEP can nonetheless raise ICP when it is applied at high levels, when it is transmitted to a cranium with exhausted compliance, when it reduces venous return enough to lower $MAP$ and cerebral perfusion pressure, or when it is combined with a head-down or venous-obstructed position.
Do not apply a fixed PEEP rule to a brain-injured patient. Increase it in steps while watching ICP, arterial pressure and, where available, $PbtO_2$; if ICP rises or perfusion falls, step back and address the mechanism rather than simply accepting the change.
Cerebral Perfusion Pressure
$$\text{CPP} = MAP - ICP$$where CPP and $MAP$ are in mmHg and $ICP$ is referenced to the level of the foramen of Monro (the external auditory meatus). In adults the target is generally 60–70 mmHg. Below about 50–60 mmHg ischaemia develops; above about 70 mmHg the vasopressor and fluid load required exposes the injured lung to hydrostatic oedema, and a landmark trial showed that deliberately targeting a CPP above 70 mmHg increased the incidence of ARDS without improving neurological outcome. CPP is supported by raising $MAP$ first and lowering ICP second, since raising $MAP$ in a non-compliant cranium can itself raise ICP.
In a rising ICP with a falling CPP, act in order: (1) secure the airway and confirm oxygenation and normocapnia; (2) sedate and control pain, cough and dyssynchrony; (3) support $MAP$ to preserve CPP; (4) position head-up 30 degrees with a neutral neck; (5) give osmotherapy (hypertonic saline or mannitol) for acute intracranial hypertension; (6) consider brief hyperventilation to $PaCO_2$ 30–35 mmHg only as a bridge; (7) escalate to neuromuscular blockade and neurosurgical decompression.
When Lung Protection Collides With Carbon Dioxide Control
The Conflict
The patient with both ARDS and acute brain injury gives the ventilator two incompatible instructions. Lung-protective ventilation uses low tidal volume and permissive hypercapnia, and its price is carbon dioxide retention; the brain, by contrast, needs tight control of $PaCO_2$ to keep cerebral blood volume and ICP stable. Hypercapnia raises ICP and reduces cerebral perfusion, and the intracranial hypertension it provokes may then be treated with hyperventilation, which in turn increases the risk of lung injury if it demands high volumes or pressures.
Negotiating the Trade-off
Resolution is a hierarchy rather than a single compromise:
- Protect the lung mechanically. Keep tidal volume at 6–8 $\text{mL}/\text{kg}$ predicted body weight and plateau pressure below 27–30 $\text{cmH}_2\text{O}$. Do not increase tidal volume simply to clear carbon dioxide.
- Clear carbon dioxide without adding volume. Raise respiratory rate cautiously, limited by expiratory time and intrinsic PEEP; reduce dead space by treating bronchospasm, secretions and hypovolaemia.
- Set a carbon dioxide ceiling, not a licence for hypercapnia. Permit $PaCO_2$ to rise only to the top of the normal range (40–45 mmHg) under ICP monitoring; if ICP rises, adjust the lung strategy deliberately rather than abandoning it.
- Use extracorporeal carbon dioxide removal when the tension is irreconcilable. ECCO₂R decouples $PaCO_2$ from minute ventilation and permits genuinely protective ventilation while maintaining normocapnia — the cleanest solution in severe ARDS with refractory intracranial hypertension.
- Never trade a fatal ICP for a marginally safer tidal volume, but equally do not create ventilator-induced lung injury in pursuit of a single normal blood gas value.
Agree the limits before changing the ventilator: for example $PaCO_2$ up to 45 mmHg with ICP below 22 mmHg, plateau pressure below 30 $\text{cmH}_2\text{O}$ and driving pressure below 15 $\text{cmH}_2\text{O}$. If any limit is breached, escalate monitoring or move to ECCO₂R rather than loosening the others.
Condition-Specific Goals
Traumatic Brain Injury
TBI sets the template: normocapnia at 35–40 mmHg, $PaO_2$ 80–120 mmHg, ICP below 22 mmHg, CPP 60–70 mmHg, and normothermia. Sedation and analgesia are titrated to control ICP and dyssynchrony. Prophylactic hypothermia is not recommended — a large randomised trial showed worse outcomes with early prophylactic cooling — and fever is treated actively. Hyperventilation is reserved for herniation.
Aneurysmal Subarachnoid Haemorrhage
Early after aneurysmal subarachnoid haemorrhage the priority is prevention of delayed cerebral ischaemia, which is exquisitely sensitive to hypoperfusion and hypocapnia. Hyperventilation is therefore particularly hazardous, because it reduces flow in a territory already prone to vasospasm. Maintain normocapnia and euvolemia, avoid hypotension, and monitor for delayed ischaemia and hydrocephalus; intracranial hypertension from hydrocephalus, oedema or rebleeding is managed as in TBI.
Intracerebral Haemorrhage and Ischaemic Stroke
In spontaneous intracerebral haemorrhage, early intensive blood-pressure lowering to a systolic pressure of about 130–140 mmHg is safe and may limit haematoma expansion; thereafter perfusion should be adequate to maintain CPP. In ischaemic stroke the aim is to preserve flow to the penumbra: avoid hypercapnia, which may worsen oedema, and avoid hypoxia. Routine supplemental oxygen in non-hypoxaemic stroke is not beneficial and hyperoxia may be harmful, so target $SpO_2$ at or above 94%. In both conditions hyperventilation is confined to signs of herniation.
Status Epilepticus
The ventilated patient in status epilepticus needs seizure control first and ventilation second. Seizure activity raises cerebral metabolic demand, and the mismatch between demand and delivery — compounded by hyperthermia, acidosis and rhabdomyolysis — injures the brain. Ventilation protects the airway, treats the metabolic acidosis of prolonged convulsion, and prevents hypercapnia, which lowers the seizure threshold and raises ICP. Hyperventilation has no established role in terminating seizures. Deep sedation with a titratable agent is the mainstay, with vigilance for its hazards, including propofol infusion syndrome.
Temperature, Sedation, and Prone Positioning
Fever is among the most neglected secondary insults, since each degree Celsius raises cerebral metabolic rate by roughly 5–7%; controlled normothermia is therefore an active therapy. Therapeutic hypothermia at 32–35 °C is not routine in TBI, though it remains a legitimate rescue for refractory intracranial hypertension. Sedation is titrated to ICP rather than to a fixed depth, and neuromuscular blockade is a reasonable short-term adjunct for refractory intracranial hypertension and for dyssynchrony that raises ICP. Prone positioning, used for severe ARDS, can be applied to brain-injured patients with meticulous attention to head and neck alignment, line security and ICP monitoring; it often lowers ICP by improving venous drainage and lung mechanics, but must be abandoned if ICP rises.
| Neurological condition | Target $PaCO_2$ | Oxygenation target | Perfusion and ICP target | Key caveats |
|---|---|---|---|---|
| Traumatic brain injury | 35–40 mmHg (brief 30–35 only for herniation) | $PaO_2$ 80–120 mmHg; $SpO_2$ 92–96% | CPP 60–70 mmHg; ICP < 22 mmHg | Avoid prophylactic hyperventilation and prophylactic hypothermia; treat fever |
| Aneurysmal subarachnoid haemorrhage | 35–40 mmHg; avoid sustained hypocapnia | $PaO_2$ 80–120 mmHg | CPP ~70 mmHg; euvolemia | Hypocapnia worsens delayed cerebral ischaemia; watch for hydrocephalus |
| Intracerebral haemorrhage | 35–40 mmHg | $SpO_2$ ≥ 94% | Systolic BP 130–140 mmHg early; CPP 60–70 mmHg | Hyperventilation only for herniation |
| Ischaemic stroke | 35–40 mmHg; avoid hypercapnia | $SpO_2$ ≥ 94% (oxygen only if hypoxaemic) | Perfusion according to reperfusion status | Avoid routine hyperoxia; protect penumbral flow |
| Status epilepticus | 35–40 mmHg; avoid hypercapnia | $SpO_2$ ≥ 94%; $PaO_2$ 80–120 mmHg | $MAP$ to sustain CPP; control fever | Hyperventilation does not terminate seizures; watch propofol infusion syndrome |
| Acute brain injury with ARDS | 35–45 mmHg with ICP monitored | $PaO_2$ 55–80 mmHg; $SpO_2$ 88–95% | CPP 60–70 mmHg; ICP < 22 mmHg | $V_T$ 6–8 mL/kg PBW and $P_{plat}$ < 30 $\text{cmH}_2\text{O}$; consider ECCO₂R |
A Neurocritical-Care Ventilation and ICP Algorithm
The algorithm integrates lung-protective limits with cerebral targets and escalates only when a defined threshold is crossed.
flowchart TD
    A["Acute brain injury requiring invasive ventilation"] --> B["Secure airway; target SpO2 92-96% and PaO2 80-120 mmHg"]
    B --> C["Controlled ventilation: VT 6-8 mL/kg PBW, Pplat < 30 cmH2O"]
    C --> D["Titrate respiratory rate to PaCO2 35-40 mmHg; calibrate ETCO2 with ABG"]
    D --> E["Head up 30 degrees, neutral neck; sedate to control ICP and dyssynchrony"]
    E --> F{"ICP >= 22 mmHg or CPP < 60 mmHg?"}
    F -->|"No"| G["Continue normocapnia; PEEP 5-10 cmH2O titrated against ICP"]
    F -->|"Yes"| H["Support MAP for CPP 60-70 mmHg; exclude pain, cough, seizure, fever, hydrocephalus"]
    H --> I{"Refractory intracranial hypertension?"}
    I -->|"No"| G
    I -->|"Yes"| J["Osmotherapy; deepen sedation; consider neuromuscular blockade"]
    J --> K{"Signs of herniation?"}
    K -->|"No"| M["Reassess Pplat and driving pressure"]
    K -->|"Yes"| L["Brief hyperventilation to PaCO2 30-35 mmHg as a bridge to definitive therapy"]
    L --> M
    M --> N{"ARDS with PaCO2 > 45 mmHg and ICP at ceiling?"}
    N -->|"Yes"| O["Consider ECCO2R to decouple CO2 clearance from minute ventilation"]
    N -->|"No"| P["Daily SBT and airway-protection assessment"]
    O --> P
    P --> Q{"Cough, secretions, consciousness and cuff leak adequate?"}
    Q -->|"Yes"| R["Extubate with close surveillance; assess swallowing before oral intake"]
    Q -->|"No"| S["Continue ventilation; consider tracheostomy if prolonged weaning is anticipated"]
Airway Protection, Weaning, and Tracheostomy
Why Extubation Fails in Brain Injury
Extubation failure is more common in neurocritical care than in general intensive care, because successful extubation depends not only on respiratory muscle strength and gas exchange but also on airway protection, which is a function of consciousness, cough and swallowing. Impaired consciousness reduces both the drive to cough and the ability to protect the airway; bulbar and pseudobulbar involvement impairs swallowing; loss of the cough reflex and of glottic closure permits aspiration of secretions; and delayed gastric emptying increases the risk of regurgitation. A patient who passes a spontaneous breathing trial may still fail extubation through aspiration, so passing the trial is necessary but not sufficient.
Assessing Airway Protection
Readiness is judged on four axes: the neurological trajectory and level of consciousness, since the ability to follow simple commands is reassuring; cough strength, where a peak cough flow below 60 $\text{L}\cdot\text{min}^{-1}$ or a weak cough on suctioning predicts failure; the volume and frequency of secretions; and laryngeal integrity, assessed by a cuff-leak test and, where available, flexible endoscopic evaluation of swallowing before oral intake. Each measure informs but none decides; serial assessment across a day is more reliable than a single threshold.
Tracheostomy
Tracheostomy is considered when prolonged ventilation is anticipated, when sedation must be lightened for neurological assessment, or when airway protection remains inadequate after the underlying process has stabilised. In neurocritical care it facilitates weaning, reduces sedation, lowers the work of breathing, and permits oral care and communication. The evidence does not support a rigid early-versus-late timing rule, so the decision should be individualised to the neurological trajectory, the predicted duration of ventilation and the burden of secretions. Percutaneous dilatational tracheostomy is feasible in brain-injured patients but demands attention to coagulation status, particularly with therapeutic anticoagulation, and to the risk of a transient ICP rise during the procedure.
Key Takeaways
- Ventilation in acute brain injury is a tool for preventing secondary neurological injury; targets are set around cerebral perfusion, ICP, oxygenation and carbon dioxide, not around the lung alone.
- Cerebral vasoreactivity changes CBF by approximately 3–4% per mmHg of $PaCO_2$, so normocapnia at 35–40 mmHg is the default and both hypercapnia and hypocapnia are harmful.
- Therapeutic hyperventilation to $PaCO_2$ 30–35 mmHg is a narrow, temporary bridge for imminent herniation; the effect wanes within hours and the vasoconstriction risks ischaemia.
- Cerebral oxygen delivery depends chiefly on haemoglobin and saturation, so anaemia and desaturation must be corrected; hyperoxia adds little content and may cause harm.
- Cerebral perfusion pressure is $\text{CPP} = MAP - ICP$; a target of 60–70 mmHg is supported by raising $MAP$ first and lowering ICP second, while deliberately exceeding 70 mmHg increases lung injury without neurological benefit.
- PEEP up to about 10–15 $\text{cmH}_2\text{O}$ is usually well tolerated but must be titrated against ICP and perfusion, because raised intrathoracic pressure can impede cerebral venous return.
- In combined ARDS and acute brain injury, keep protective volumes and recruit carbon dioxide clearance by other means, including ECCO₂R, rather than trading intracranial hypertension for lung protection or accepting ventilator-induced lung injury for a normal blood gas.
- Extubation in brain injury is limited by airway protection as much as by respiratory strength; assess consciousness, cough, secretions and swallowing, and consider tracheostomy when prolonged weaning is anticipated.