Tracheostomy creates a stable surgical airway through the anterior wall of the trachea, and its percutaneous dilatational variant (PDT) has become the default elective airway for the patient who cannot be liberated from mechanical ventilation or protect the upper airway. Roughly 10% of patients requiring at least three days of invasive ventilatory support receive a tracheostomy, and intensivists now perform most at the bedside. It changes respiratory mechanics, nursing care, and the patient's trajectory toward rehabilitation or long-term ventilatory dependence.
The physiological case rests on two mechanical advantages. The tube is short and of large calibre, so it adds far less resistive load and dead space than a translaryngeal endotracheal tube, and it frees the mouth and larynx for oral care, swallowing, phonation, and lighter sedation. These benefits must be weighed against procedural risk and against evidence, more nuanced than early enthusiasm suggested, on the timing of placement. One principle runs throughout: a tracheostomy is a means to an end, and that end should be articulated before the procedure, not after it.
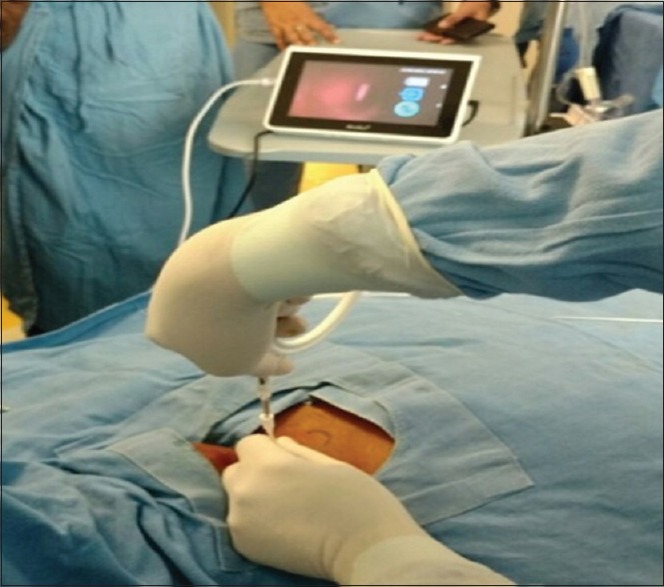 Figure 1: Under continuous fibreoptic bronchoscopic guidance the operator watches the needle and guidewire enter the tracheal lumen in the midline and confirms the correct intercartilaginous level, detecting posterior-wall contact before dilation begins — the most effective safeguard against paratracheal placement and posterior wall injury. (Source: Mehta C, Mehta Y. Annals of Cardiac Anaesthesia 2017;20(Supplement):S19–S25. DOI: 10.4103/0971-9784.197793).
Indications and the Evidence on Timing
Established Indications
Tracheostomy is indicated when the translaryngeal route is failing, unsafe, or unsustainable. The dominant indication is prolonged mechanical ventilation or failure to wean. Upper-airway obstruction — laryngeal tumour, bilateral vocal-cord palsy, subglottic stenosis, maxillofacial trauma, or angio-oedema — is bypassed by a tracheostomy. Airway protection is required by depressed consciousness, bulbar dysfunction, or absent cough, as in severe stroke or high cervical spinal-cord injury. The remaining indications are unmanageable secretions and the need for durable access to long-term ventilation.
Early Versus Late: What the Randomised Trials Show
Rumbak and colleagues reported striking reductions in mortality, pneumonia, and sedation when tracheostomy was performed within 48 hours rather than after day 14, but the trial was small and single-centre and the effect size has never been reproduced. Terragni and colleagues found that tracheostomy at 6–8 days reduced ventilator-associated pneumonia, but not mortality, compared with 13–15 days. The largest trial, TracMan, randomised 909 patients to early tracheostomy (within four days) or a late strategy (after ten days) and found no difference in 30-day mortality, intensive-care or hospital length of stay, or pneumonia; the early strategy simply caused more tracheostomies. A Cochrane review concurs.
The trials do not show that tracheostomy is harmless, nor that timing is irrelevant. They show that routine early tracheostomy, applied before the trajectory is knowable, confers no survival benefit — at day three or four we cannot identify who will still be ventilated at day fourteen. Individualise timing on the anticipated trajectory: consider tracheostomy around day 7–14 when weaning failure is established or the airway is unsafe, and give a patient with a plausible route to extubation that chance first.
Techniques of Percutaneous Dilatational Tracheostomy
The Ciaglia Technique
The Ciaglia method, now usually performed with a single curved dilator as the Ciaglia Blue Rhino, is the most widely used technique. A small midline incision is made between the first and second or second and third tracheal rings. A needle is advanced under bronchoscopic vision until air and then carbon dioxide are aspirated, confirming intratracheal placement; a guidewire is passed; a graded or single curved dilator is advanced over the wire; and the tube is railroaded into position. Everything after the wire follows a confirmed intratracheal path — the guiding principle of the Seldinger method.
The Griggs, Fantoni, and Other Methods
The Griggs technique dilates the tract in one step over the guidewire using the Howard–Kelly forceps, reducing manipulations. The Fantoni translaryngeal technique works retrogradely: the guidewire is advanced out through the mouth, and the dilator and tube are drawn from inside the trachea outward through the anterior wall. Because dilation proceeds outward, it is theoretically less likely to injure the posterior wall, but it requires more equipment and is less familiar. PercuTwist and balloon dilatation are alternatives. No device has shown superiority in mortality or major complications; operator familiarity and disciplined confirmation of position matter more than the kit.
Bronchoscopic and Ultrasound Guidance
Continuous fibreoptic bronchoscopy is the most important safety adjunct, and Figure 1 shows its rationale directly. Passed through the existing endotracheal tube, it confirms midline puncture at an appropriate level, verifies that the guidewire lies within the tracheal lumen rather than a paratracheal plane, and shows the dilator and tube remaining intratracheal, so posterior-wall contact is detected before it becomes perforation. The bronchoscope also occludes part of the tube lumen, however, and can cause hypercapnia, desaturation, and a rise in intracranial pressure; the trade-off must be explicit. Ultrasound complements it by mapping the pretracheal vasculature, midline, cricoid cartilage, and tracheal rings, and is valuable in obesity, short necks, and impalpable landmarks.
Percutaneous Versus Surgical Tracheostomy
Cochrane comparisons show that PDT reduces wound infection and stomal scarring and may reduce cost, with no difference in mortality or major haemorrhage. It is therefore preferred for the elective airway in favourable anatomy, whereas surgical tracheostomy retains advantages in the emergency airway, difficult anatomy, children, and combined procedures under one anaesthetic.
Contraindications and Complications
Absolute and Relative Contraindications
Absolute or situational blockers: an emergency airway, an unidentifiable cricoid cartilage or midline, infection or a malignant mass over the site, and laryngotracheal obstruction that makes a stoma pointless. Correctable relative blockers: coagulopathy (platelets below about 50 × 10⁹/L or INR above roughly 1.5), severe hypoxaemia or a high PEEP requirement, uncontrolled intracranial hypertension when bronchoscopy will be used, and inability to extend the neck. Correct what can be corrected; where risk persists, choose an operating-theatre tracheostomy or defer.
Complications and Their Prevention
Complications divide into intra-operative, early, and late events, and most are preventable with technique and cuff discipline.
| Complication | Timing | Mechanism | Prevention and management |
|---|---|---|---|
| Bleeding | Intra-operative to 48 h | Pretracheal vessel injury; coagulopathy | Correct coagulopathy; ultrasound mapping; pressure or endoscopy |
| Posterior wall injury | Intra-operative | Needle or dilator too deep | Continuous bronchoscopy; shallow needle depth |
| Paratracheal placement | Intra-operative | Guidewire outside the lumen | Confirm an intratracheal wire before dilation |
| Pneumothorax or emphysema | Immediate | Pleural injury or lateral dissection | Stay midline; chest radiograph; drain if symptomatic |
| Stomal infection or granulation | 3–10 days | Colonisation; poor stoma care | Aseptic technique; daily stoma care; antibiotics if cellulitis |
| Tracheo-innominate fistula | 7–14 days or later | Cuff erosion into the innominate artery | Cuff 20–30 $\text{cmH}_2\text{O}$; avoid low placement; tamponade; surgery |
| Tracheal stenosis or tracheomalacia | Weeks to months | Cuff-pressure ischaemia | Keep cuff below 30 $\text{cmH}_2\text{O}$; correct tube size; dilate or resect |
| Aspiration and dysphagia | Post-procedure | Reduced laryngeal excursion; persistent cuff | Speech and language therapy; cuff-deflation trials; FEES |
A sentinel bleed from the stoma or airway must never be dismissed as granulation bleeding: the cuff erodes the anterior wall into the innominate artery, classically at the first to third tracheal rings. Overinflate the cuff to tamponade, apply digital pressure through the stoma, and call for urgent bronchoscopy and vascular support; do not remove the tube blindly.
Ventilation Through a Tracheostomy
Dead Space, Resistance, and Work of Breathing
A tracheostomy shortens the artificial airway and therefore reduces added anatomical dead space, so a larger fraction of each tidal volume reaches the alveoli:
$$V_A = (V_T - V_D) \times f$$where $V_A$ is alveolar ventilation in $\text{L}\cdot\text{min}^{-1}$, $V_T$ is tidal volume in $\text{L}$, $V_D$ is anatomical dead space in $\text{L}$, and $f$ is respiratory rate in $\text{breaths}\cdot\text{min}^{-1}$. The dead-space fraction is estimated at the bedside by the Bohr equation:
$$\frac{V_D}{V_T} = \frac{P_{a\text{CO}_2} - P_{\bar{E}\text{CO}_2}}{P_{a\text{CO}_2}}$$where $P_{a\text{CO}_2}$ and $P_{\bar{E}\text{CO}_2}$ are the arterial and mixed expired carbon dioxide tensions in $\text{mmHg}$. A tracheostomy typically removes roughly 20–50 $\text{mL}$ of added dead space.
Resistance to gas flow through a tube follows the Hagen–Poiseuille relation:
$$R = \frac{8\mu L}{\pi r^4}$$where $R$ is airway resistance in $\text{cmH}_2\text{O}\cdot\text{L}^{-1}\cdot\text{s}$, $\mu$ is the dynamic viscosity of the gas mixture, $L$ is tube length in $\text{cm}$, and $r$ is internal radius in $\text{cm}$. Because resistance is proportional to length and inversely proportional to the fourth power of radius, the shorter tracheostomy tube offers far lower resistance than an endotracheal tube of comparable calibre:
$$R_{\text{trach}} \ll R_{\text{ETT}}$$Lower dead space and resistance reduce the elastic and resistive work of breathing, which is why sedation can often be lightened. A tracheostomy does not reverse the underlying lung disease, and its clearest benefits are comfort, safety, oral care, and rest for the larynx.
Suctioning, Humidification, and Cuff Management
The tracheostomy bypasses the nose, so humidification is obligatory — a heated humidifier or heat-and-moisture exchanger. Suctioning should be on clinical indication rather than schedule, with a catheter sized to about half the tube's internal diameter; routine saline instillation is not recommended. Cuff pressure should be measured every shift and kept at 20–30 $\text{cmH}_2\text{O}$, because higher pressures cause mucosal ischaemia, stenosis, and fistula, while lower pressures permit aspiration. Subglottic drainage, semi-recumbent positioning, daily sedation interruption, and oral care complete the ventilator-associated pneumonia bundle. A one-way speaking valve on a deflated cuff restores airflow over the vocal cords and uses subglottic pressure to improve cough, laryngeal excursion, and swallowing.
Weaning and Decannulation
Weaning Through the Tracheostomy
Weaning follows the same principles as with an endotracheal tube: daily readiness assessment, spontaneous breathing trials on T-piece or low-level pressure support, and treatment of reversible causes. The tracheostomy lowers the resistive load and allows sedation to be minimised, but a patient who cannot wean through it generally has unresolved respiratory, cardiac, or neuromuscular disease.
Assessment for Decannulation
Decannulation answers four questions: is the reason for the tracheostomy resolved; can the patient breathe without support; can secretions be cleared; and is the upper airway patent? A capping trial — occluding the tube for at least 24 hours with monitoring — tests patency and the ability to breathe around the tube. Where patency is doubtful, endoscopy assesses granulation, stenosis, or vocal-cord dysfunction, and the tube may be downsized first. Weak cough, heavy secretions, impaired swallow, or depressed consciousness warrant deferral.
flowchart TD
    A["Tracheostomy in the ICU"] --> B{"Cause of respiratory failure resolved?"}
    B -- "No" --> C["Continue support; reassess weekly"]
    B -- "Yes" --> D{"Breathing without support?"}
    D -- "No" --> C
    D -- "Yes" --> E{"Effective cough and manageable secretions?"}
    E -- "No" --> F["Optimise secretions and cough; reassess in 48-72 h"]
    F --> E
    E -- "Yes" --> G["Cuff deflation trial; capping for 24 h"]
    G --> H{"Tolerates cuff deflation and capping, airway patent?"}
    H -- "No" --> I["Downsize tube; endoscopy; reassess"]
    I --> G
    H -- "Yes" --> J["Decannulate; monitor 24-48 h for stridor"]
Before the tract matures, blind reinsertion can create a fatal paratracheal false passage. Occlude the stoma, ventilate from above with an orotracheal tube under direct laryngoscopy, then re-site the tracheostomy under controlled conditions.
Long-Term Ventilation and the Chronically Critically Ill
Definitions
Prolonged mechanical ventilation is conventionally defined as ventilation for at least twenty-one consecutive days, a threshold used to describe the ventilator-dependent population; the more clinically useful prolonged weaning category is failure of at least three spontaneous breathing trials or ventilation beyond seven days after the first. The chronically critically ill patient is a distinct phenotype: typically eight or more days in intensive care with persistent organ support, prolonged ventilation, delirium and brain dysfunction, critical illness neuromyopathy, malnutrition, and chronic inflammation. They occupy a small fraction of admissions but a large share of intensive-care bed-days, and their outcome depends on the accumulation of these chronic features rather than the original diagnosis.
Settings for Home and Long-Term Ventilation
Long-term ventilation may be invasive through the tracheostomy or non-invasive through a mask; the choice depends on airway protection, secretion burden, and tolerance. Non-invasive ventilation is preferred wherever tolerated, particularly in restrictive and neuromuscular disease and obesity hypoventilation, because it avoids an indwelling tube. Where invasive ventilation is required, the modes used are volume-targeted assist-control (a set tidal volume of roughly 8–10 $\text{mL/kg}$ of ideal body weight with a backup rate), pressure-targeted ventilation with a guaranteed volume, or pressure support with a backup rate; the backup rate covers apnoea and nocturnal hypoventilation. Settings are titrated to comfort, sleep quality, morning headache, and where available nocturnal carbon dioxide and oximetry. Humidification, a reliable power source, alarms, trained caregivers, and a documented emergency plan are essential.
The Multidisciplinary Team and Goals of Care
Outcome depends on the team around the tube. Weaning units and specialised respiratory-care centres improve liberation rates and reduce mortality compared with continued care in an acute bed, largely through expertise and a rehabilitative focus. Speech and language therapy assesses swallowing, manages cuff deflation and speaking valves, and performs videofluoroscopy or endoscopic evaluation of swallowing, preventing aspiration and unnecessary nil-by-mouth status. Nutrition should deliver 1.2–2.0 $\text{g}\cdot\text{kg}^{-1}\cdot\text{day}^{-1}$ of protein enterally where possible, supporting respiratory-muscle and immune function. Rehabilitation — early mobilisation and limb and respiratory-muscle training — attenuates critical illness neuromyopathy and improves the likelihood of decannulation. Prevention of ventilator-associated pneumonia and pressure injury completes the bundle: subglottic drainage, oral care, cuff-pressure monitoring, and regular repositioning.
Before tracheostomy in a patient whose trajectory is uncertain, hold an explicit goals-of-care discussion. State the likely time course and the probability of eventual liberation, distinguish treatment that prolongs life from treatment that prolongs dying, and define the circumstances in which the tracheostomy would be withdrawn in favour of comfort-focused care. Documenting and revisiting that discussion is the ethical scaffolding of the decision.
Key Takeaways
- Document which problem the tracheostomy solves — prolonged ventilation, obstruction, airway protection, secretions, or long-term access — because that defines the decannulation criteria.
- The trials, especially TracMan, show no mortality or length-of-stay benefit from routine early tracheostomy; individualise timing, usually around day 7–14.
- Ciaglia, Griggs, and Fantoni are all acceptable; operator familiarity and confirmation of guidewire placement matter more than the device.
- Continuous bronchoscopy confirms midline placement and correct level and prevents posterior-wall injury and paratracheal false passage (Figure 1), balanced against its effects on carbon dioxide and intracranial pressure.
- Correct coagulopathy, hypoxaemia, and high PEEP before a bedside PDT; site infection, unidentifiable landmarks, and emergency need mandate another strategy.
- Keep cuff pressure at 20–30 $\text{cmH}_2\text{O}$, humidify gas, suction on indication, and use a speaking valve early to prevent late morbidity.
- A tracheostomy raises $V_A$ for a given $V_T$ and $f$ by lowering dead space, and lowers airway resistance because $R \propto L/r^4$, without reversing the underlying disease.
- Decannulate only when the cause is resolved, breathing is sustained, secretions are manageable, and the airway is patent; recognise the chronically critically ill phenotype and plan long-term ventilation and goals of care accordingly.