Closed-loop ventilation moves a repetitive decision from the bedside to the ventilator's algorithm: a variable is measured continuously, its error against a target computed, and an output adjusted by a defined control law.
The algorithm owns the moment-to-moment titration; the clinician owns the target, the bounds, the signal and the decision to wean.
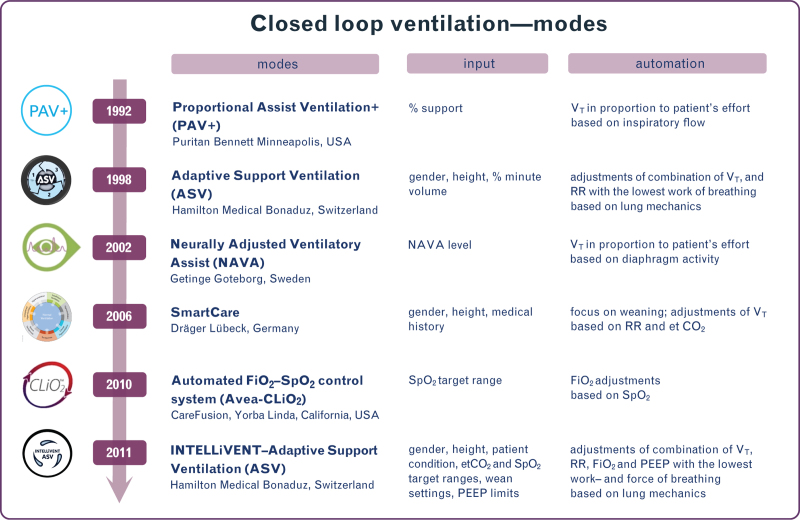 Figure 1: The commercial closed-loop modes differ less in their hardware than in which feedback variable they read and which output they automate — from patient effort (PAV+), lung mechanics (ASV), diaphragm electrical activity (NAVA) and respiratory pattern (SmartCare) to the fully integrated carbon dioxide, oxygen and mechanical control of INTELLiVENT-ASV. (Source: Goossen RL, Schultz MJ, Tschernko E, Chew MS, Robba C, Paulus F, van der Heiden PLJ, Buiteman-Kruizinga LA. European Journal of Anaesthesiology 2024. DOI: 10.1097/EJA.0000000000001972).
The Taxonomy of Closed-Loop Ventilation
Open Loop, Fixed Target, and Adaptive Targets
Open-loop modes set output from the clinician's settings alone, never modifying it from a measurement: volume-controlled ventilation delivers a set tidal volume at a set rate regardless of pressure, and pressure-controlled ventilation holds a set pressure. They guarantee a minimum minute ventilation but leave changes in mechanics or demand unaddressed.
Closed loop with a fixed target adds one measured variable and one controller: the clinician chooses the variable and its target, and the ventilator reduces the discrepancy. Closed-loop oxygen control and modes that servo tidal volume or rate to a setpoint belong here.
The most advanced tier adapts the targets themselves. INTELLiVENT-ASV selects a tidal volume and respiratory rate pair so that end-tidal carbon dioxide stays within a range, saturation stays within a range, and the work and force of breathing are minimised, all within clinician-set limits.
The Controller, the Target, and the Feedback Variable
Every loop has three irreducible elements.
Controller — the algorithm that computes the adjustment: a proportional–integral–derivative law or a set of knowledge-based rules. Target (setpoint) — the value or range to be maintained, such as an end-tidal carbon dioxide of $35\text{–}45\ \text{mmHg}$ or a saturation of $92\text{–}97\%$. Feedback variable — the measured signal compared with the target: end-tidal carbon dioxide, tidal volume, respiratory rate, oxygen saturation, or a derived mechanical quantity.
The simplest controller is proportional: the change in the manipulated variable is proportional to the current error.
$$\Delta u = K_p \left( x_{\text{set}} - x_{\text{meas}} \right)$$Here $\Delta u$ is a pressure-support increment in $\text{cmH}_2\text{O}$, $x_{\text{set}}$ the target, $x_{\text{meas}}$ the measured value and $K_p$ the gain: $2\ \text{cmH}_2\text{O}$ per $1\ \text{mL}$ shortfall gives $K_p = 2\ \text{cmH}_2\text{O}\cdot\text{mL}^{-1}$. A proportional controller leaves a persistent offset, which integral action removes; excessive gain oscillates.
The Governing Equations of Ventilation Control
All controllers manipulate minute ventilation, the product of tidal volume and respiratory rate:
$$\dot V_E = V_T \times f$$where $\dot V_E$ is in $\text{L}\cdot\text{min}^{-1}$, $V_T$ in litres and $f$ in $\text{breaths}\cdot\text{min}^{-1}$. Only the fraction reaching alveoli clears carbon dioxide, so alveolar ventilation subtracts dead space:
$$\dot V_A = (V_T - V_D) \times f$$and arterial carbon dioxide follows the ratio of production to alveolar ventilation:
$$P_{a\text{CO}_2} \approx \frac{0.863 \times \dot V_{\text{CO}_2}}{\dot V_A}$$with $P_{a\text{CO}_2}$ in $\text{mmHg}$ and $\dot V_{\text{CO}_2}$ in $\text{mL}\cdot\text{min}^{-1}$.
The resulting control topology is shown below: clinician-owned targets and bounds feed the controllers, which drive the ventilator, whose effect on the patient is measured by the sensors and returned.
flowchart LR
    subgraph Clinician["Clinician-owned"]
        T1["etCO2 target range"]
        T2["SpO2 target range"]
        L1["Safety bounds: PEEP min/max, PS max, VT max, alarm limits"]
    end
    subgraph Controller["Ventilator controller"]
        C1["CO2 controller"]
        C2["Oxygen controller"]
        C3["Demand and mechanics controller"]
    end
    V["Ventilator"]
    P["Patient"]
    M["Sensors: capnography, pulse oximetry, flow and pressure"]
    T1 --> C1
    T2 --> C2
    L1 --> C1
    L1 --> C2
    L1 --> C3
    C1 --> V
    C2 --> V
    C3 --> V
    V --> P
    P --> M
    M -->|"etCO2, VT, RR"| C1
    M -->|"SpO2"| C2
    M -->|"Compliance and resistance"| C3
INTELLiVENT-ASV: Dual Control of Ventilation and Oxygenation
Inputs and the Ventilation Controller
INTELLiVENT-ASV integrates three controllers. Its inputs are predicted body weight; end-tidal carbon dioxide, or arterial carbon dioxide when a blood gas is entered; tidal volume and respiratory rate; and oxygen saturation. A carbon-dioxide controller and an oxygen controller sit alongside a demand controller.
The demand controller selects the tidal volume and rate minimising the work and force of breathing — the Otis optimum, which trades the elastic cost of large breaths against the resistive cost of frequent ones:
$$f_{\text{opt}} = \frac{-1 + \sqrt{1 + 4\pi^2\tau\,(\dot V_A / V_D)}}{2\pi^2\tau}$$where $\tau$ is the inspiratory time constant and $\dot V_A / V_D$ the ratio of alveolar ventilation to dead space. The clinician anchors support with a target minute volume as a percentage of predicted normal.
Dual Control of Oxygenation
Oxygenation is regulated in parallel. The controller adjusts PEEP and inspired oxygen fraction to keep saturation in the target range, moving first on oxygen and then on PEEP up to the permitted ceiling.
Automatic Weaning
Weaning is an emergent property of the carbon-dioxide controller. As the pattern matures, it reduces support toward the least required to keep end-tidal carbon dioxide in target; at minimal support with an adequate pattern, the ventilator signals readiness for a spontaneous breathing trial and can conduct one automatically.
Pressure support is weaned by the loop's search for the least support that satisfies the target; the clinician confirms genuine recovery, not a compensated, tiring patient.
SmartCare and Knowledge-Based Weaning
Pressure-Support Titration Against the Respiratory Pattern
SmartCare is knowledge-based rather than mathematical: it encodes clinical rules in a decision table. Every few minutes it samples tidal volume, respiratory rate and end-tidal carbon dioxide on pressure support and classifies the patient: comfortable (an acceptable rate, tidal volume and carbon dioxide), insufficient ventilation (hypoventilation with hypercapnia), excessive ventilation (hyperventilation with hypocapnia) or respiratory distress (a rapid, shallow pattern). It then changes pressure support by a fixed step, typically $2\text{–}4\ \text{cmH}_2\text{O}$, and waits before reassessing.
From Comfort to the Spontaneous Breathing Trial
While the patient is over-supported the system steps support downward; if distress emerges it steps support back up. When support reaches a low threshold — conventionally around $7\ \text{cmH}_2\text{O}$ — with stable carbon dioxide and no distress, the system declares readiness to wean and can conduct a spontaneous breathing trial.
Because SmartCare's rules are explicit, the ventilator can display why it changed support — but those rules are only as good as the thresholds encoded in them.
Other Servo-Controlled Systems for Comparison
Proportional-Assist and Neurally Adjusted Ventilation
Proportional-assist ventilation (PAV+) amplifies the patient's own effort: it derives instantaneous muscular pressure from flow and volume using estimated elastance and resistance, and delivers a clinician-selected percentage of it. Neurally adjusted ventilatory assist (NAVA) reads diaphragm electrical activity (EAdi) through an oesophageal catheter and applies a pressure proportional to that signal, preserving effort–assist coupling; its weaknesses are the specialised catheter and signal drift.
Adaptive Support Ventilation and Automated Protocols
Adaptive support ventilation (ASV) shares the mechanical core of INTELLiVENT-ASV: the clinician enters predicted body weight and percentage minute volume, and the ventilator uses breath-by-breath compliance and resistance to choose a tidal volume and rate near the Otis optimum. ASV closes the loop on mechanics but not on carbon dioxide or oxygen, which INTELLiVENT-ASV adds. Automated weaning protocols conduct trials at fixed intervals.
| System | Feedback variables | Variables controlled | Clinician-set limits |
|---|---|---|---|
| PAV+ | Flow and volume, from which effort is estimated | Applied pressure as a percentage of effort | Percentage assist, alarm limits |
| NAVA | Diaphragm electrical activity (EAdi) | Applied pressure proportional to EAdi | NAVA level, trigger and alarm limits |
| ASV | Compliance, resistance, spontaneous rate | Tidal volume and respiratory rate to a minute-volume target | Predicted body weight, $\%$MinVol, maximal pressure and rate |
| INTELLiVENT-ASV | etCO2, $V_T$, respiratory rate, SpO2, mechanics | $V_T$, respiratory rate, PEEP and FiO2 to CO2 and SpO2 targets | $\%$MinVol, etCO2 and SpO2 ranges, PEEP min/max, maximal pressure and $V_T$, alarms |
| SmartCare | $V_T$, respiratory rate, etCO2, distress signs | Pressure support during weaning | Target etCO2 range, maximal support, weaning thresholds |
| Closed-loop oxygen | SpO2 | FiO2 to a saturation target | SpO2 target range, FiO2 min/max, alarms |
The Evidence Base
Automated Weaning Versus Protocolised Weaning
The 2025 Cochrane update by Rose and colleagues pooled 62 randomised trials enrolling 5,052 critically ill adults and children. Automated weaning reduced the duration of mechanical ventilation (mean difference $-0.28$ log hours, a relative reduction of $24\%$; 95% CI 18–30%) and shortened intensive-care stay by $14\%$ and hospital stay by $10\%$. Mortality was unchanged (risk ratio 0.94, 95% CI 0.82–1.07).
The safety signal is more persuasive than the mortality signal. Automated systems reduced reintubation (risk ratio 0.73, 95% CI 0.59–0.89), post-extubation non-invasive ventilation (0.74, 95% CI 0.62–0.88), prolonged ventilation (0.54, 95% CI 0.34–0.87) and tracheostomy (0.75, 95% CI 0.62–0.91), with no demonstrated harm.
Duration, Time to First Spontaneous Breathing Trial, and Workload
Protocolised weaning waits for a clinician to recognise readiness; automated systems screen continuously and initiate the trial as soon as thresholds are crossed, shortening the interval to the first spontaneous breathing trial. The 2024 systematic review by Goossen and colleagues, covering 51 randomised trials, found closed-loop ventilation at least as effective as clinician management at choosing lung-protective settings, with reduced workload.
In a randomised crossover study of moderate-to-severe ARDS, INTELLiVENT-ASV lowered transpulmonary driving pressure versus conventional pressure-controlled ventilation (median $7.0$ versus $10.0\ \text{cmH}_2\text{O}$), and in a COVID-19 ARDS cohort it achieved lung-protective targets for $65\%$ of the first seven days versus $38\%$.
Safety Signals and the Limits of the Evidence
Many trials are single-centre and small; the comparator ranges from usual care to rigorous protocol, so benefit shrinks when the control arm is already protocolised. Targets, thresholds and step sizes differ between vendors, so pooling narrows the confidence interval while masking heterogeneity. The ACTiVE multicentre trial of INTELLiVENT-ASV was designed to test duration and quality of ventilation at scale; its completion is awaited.
A randomised comparison of sidestream and mainstream capnography during closed-loop ventilation could not confirm the non-inferiority of sidestream sampling for the quality of breathing.
Safety Framework, Set-Up, and Troubleshooting
What Remains Physician-Controlled
The clinician hands over the titration but never the objectives. Before activating a closed-loop mode, the operator must confirm predicted body weight and sex; select the target ranges for end-tidal carbon dioxide and saturation; set the percentage minute volume or level of support; and define the bounds — maximal airway and driving pressures, maximal tidal volume, PEEP minimum and maximum, maximal pressure support, and alarm limits for apnoea, disconnection and carbon dioxide. Bounds convert an open-ended servo into a therapy.
An automated system takes the target literally. Set the target or bounds incorrectly, and it will pursue the wrong physiological state faster and more consistently than a distracted human.
Verifying the Feedback Signals
Capnography is the primary input of the carbon-dioxide loop. Confirm a normal waveform with a stable plateau; a sloping or truncated plateau suggests obstruction, leak or rebreathing, and a low amplitude with a normal arterial carbon dioxide suggests dilution from dead space. Corroborate a value that drives therapy with interval arterial blood gases.
Pulse oximetry is the more treacherous signal. It is unreliable in poor perfusion, shock and motion, and is confounded by dyshaemoglobins. Because the oxygen controller acts on saturation, any of these can produce a loop satisfied with a dangerously low arterial oxygen tension. Treat the arterial blood gas as the arbiter whenever the oximeter and the clinical picture disagree.
In a cold, vasoconstricted or shocked patient the oximeter may report a saturation that is untrustworthy or absent. Closed-loop oxygen control cannot detect this, so verify with an arterial blood gas or suspend the loop.
Interpreting Messages, Dislodgement, and Artefact
An automated ventilator narrates its reasoning: carbon dioxide out of range, a sensor needing attention, support being stepped down, readiness for a spontaneous breathing trial. Interpret any message by verifying the patient, not the screen — examine chest movement, auscultate, check the airway and circuit, and assess the work of breathing. A sudden change in the controlled variables may be a genuine change in mechanics, a leak or partial dislodgement of the tube, or an artefact in the feedback signal.
If the tube has migrated, the leak and altered mechanics corrupt every derived measurement; reposition the tube and confirm its position. If the capnograph is disconnected, occluded, or sampling from a leak, the value is invalid and the loop must be suspended. When signal validity is in doubt, switch to a conventional clinician-directed mode, correct the signal, and only then restore the closed loop.
- Assess the patient first — oxygenation, ventilation, airway and haemodynamics.
- Disconnect the loop: revert to a conventional mode or a manual safe baseline.
- Check the feedback chain: sensor, sampling line, filter, circuit, and airway for leak or dislodgement.
- Verify against an arterial blood gas.
- Correct the cause, re-check the bounds, then re-engage.
Key Takeaways
- Closed-loop ventilation formalises an ordinary clinical loop: a controller adjusts an output to reduce the error between a measured feedback variable and a target.
- Classify any mode by its tier — open loop, fixed target, or adaptive control of physiological targets — and by its controller, target and feedback variable.
- Minute ventilation is the product of tidal volume and respiratory rate ($\dot V_E = V_T \times f$); because the two factors carry opposite mechanical consequences, their combined selection is key.
- INTELLiVENT-ASV adjusts tidal volume, respiratory rate, PEEP and FiO2 together within clinician-set limits, and its automatic weaning is the loop reducing support to the least that satisfies the target.
- SmartCare classifies the respiratory pattern, steps pressure support accordingly, and reduces support to a threshold at which it signals readiness for a spontaneous breathing trial.
- The 2025 Cochrane review of 62 trials found that automated weaning probably shortens ventilation and intensive-care and hospital stay and reduces reintubation and tracheostomy.
- The evidence is limited by single-centre, underpowered and unblinded studies, so benefit is smallest where conventional care is already protocolised.
- Safety rests on clinician-set bounds, verified signals and vigilance; capnography and especially pulse oximetry fail silently in poor perfusion.
- When a signal is suspect, suspend the automation, verify the patient and the signal, and re-engage only after the cause is corrected.