Real-time scalar waveforms—plotting airway pressure ($P_{aw}$), gas flow ($\dot{V}$), or tidal volume ($V$) against time ($t$) on the horizontal axis—constitute the fundamental continuous bedside monitoring interface during invasive mechanical ventilation. Scalar analysis allows the clinician to continuously interrogate patient effort, respiratory system mechanics (airway resistance, static compliance, viscoelastic stress relaxation), gas trapping (intrinsic positive end-expiratory pressure, or auto-PEEP), and patient-ventilator asynchrony non-invasively at the bedside without interrupting ventilatory support.
+-------------------------------------------------------------------------+
|                  TRIAD OF VENTILATOR SCALAR WAVEFORMS                   |
+--------------------+----------------------------+-----------------------+
| Pressure-Time (P-t)| Airway pressure vs time    | PIP, Pplat, PEEP,     |
|                    | [cmH2O vs seconds]         | Driving Pressure      |
+--------------------+----------------------------+-----------------------+
| Flow-Time (V'-t)   | Gas velocity vs time       | Flow profile, auto-   |
|                    | [L/min vs seconds]         | PEEP, cycling timing  |
+--------------------+----------------------------+-----------------------+
| Volume-Time (V-t)  | Integrated volume vs time  | VT delivery, circuit  |
|                    | [mL vs seconds]            | or cuff gas leaks     |
+--------------------+----------------------------+-----------------------+
Physical Principles and the Equation of Motion
All scalar morphology is governed by the single-compartment Equation of Motion of the Respiratory System, which states that the total pressure applied across the respiratory system ($P_{tot}$) at any instant in time ($t$) equals the sum of the resistive pressure required to drive airflow through conductive airways and the elastic pressure required to expand the lungs and chest wall above end-expiratory equilibrium:
$$P_{vent}(t) + P_{mus}(t) = P_{res}(t) + P_{el}(t) + PEEP_{tot}$$Expanded in terms of instantaneous flow $\dot{V}(t)$, delivered volume $V(t)$, airway resistance ($R_{aw}$), static respiratory compliance ($C_{rs}$), and respiratory elastance ($E_{rs} = 1 / C_{rs}$):
$$P_{aw}(t) = \left(\dot{V}(t) \times R_{aw}\right) + \left(\frac{V(t)}{C_{rs}}\right) + PEEP_{tot} - P_{mus}(t)$$Where:
- $P_{aw}(t)$ is the airway opening pressure measured at the proximal endotracheal tube or ventilator Y-piece ($\text{cmH}_2\text{O}$).
- $P_{mus}(t)$ is the pressure generated by patient respiratory muscle contraction ($\text{cmH}_2\text{O}$). In fully passive, sedated, or paralyzed patients, $P_{mus} = 0$.
- $\dot{V}(t) \times R_{aw}$ is the resistive pressure drop ($\Delta P_{res}$) overcoming the frictional resistance of the endotracheal tube, ventilator circuit, and tracheobronchial tree.
- $V(t) / C_{rs} = V(t) \times E_{rs}$ is the elastic recoil pressure ($\Delta P_{el}$) generated by alveolar distension and chest wall displacement.
- $PEEP_{tot}$ is the total end-expiratory pressure, representing the sum of extrinsic applied PEEP ($PEEP_{set}$) and intrinsic PEEP ($PEEP_{auto}$).
Pressure (Paw)
  ^
  |        /| <--- Peak Inspiratory Pressure (Ppeak)
  |       / |
  |      /  +--- Resistive Pressure Drop: ΔPres = Ppeak - Pplat = Flow × Raw
  |     /   |
  |    /----+ <--- Plateau Pressure (Pplat)
  |   /     |
  |  /      +--- Elastic Pressure Component: Pel = VT / Crs = ΔP (Driving Pressure)
  | /       |
  |/________| <--- Total PEEP (PEEPset + PEEPauto)
  +----------------------------------------------------> Time (t)
Three Primary Scalar Waveforms
1. Pressure-Time ($P$-$t$) Scalar
The $P$-$t$ scalar plots airway opening pressure ($P_{aw}$, $\text{cmH}_2\text{O}$) continuously on the vertical axis against time ($s$) on the horizontal axis:
- Baseline Pressure: Represents extrinsic positive end-expiratory pressure ($PEEP_{set}$). A downward deflection below PEEP prior to breath delivery marks patient triggering effort in pressure-triggering systems.
- Inspiratory Rise: In Volume-Controlled Continuous Mandatory Ventilation (VC-CMV) with constant square flow, $P_{aw}$ exhibits an instantaneous initial vertical step representing the resistive pressure component ($\dot{V} \times R_{aw}$), followed by a linear upward slope representing progressive elastic alveolar filling ($V(t) / C_{rs}$).
- Peak Inspiratory Pressure ($P_{peak}$ or PIP): The maximum dynamic pressure achieved at the exact termination of inspiratory flow.
- Expiratory Decay: When the exhalation valve opens, airway pressure drops rapidly back to the set PEEP baseline.
2. Flow-Time ($\dot{V}$-$t$) Scalar
The $\dot{V}$-$t$ scalar plots gas flow rate ($\text{L/min}$ or $\text{L/s}$) against time. By international convention:
- Inspiratory Flow: Plotted above the zero baseline (positive values).
- Expiratory Flow: Plotted below the zero baseline (negative values).
- Zero Flow Line: Denotes complete cessation of gas movement. The transition from positive to negative flow marks the end of inspiration and the onset of passive exhalation.
3. Volume-Time ($V$-$t$) Scalar
The $V$-$t$ scalar represents the mathematical integral of the flow scalar over time ($V(t) = \int \dot{V}(t) \, dt$):
- Inspiratory Limb: Rises smoothly from zero to the peak delivered tidal volume ($V_T$).
- Expiratory Limb: Decreases smoothly as gas is evacuated through the exhalation valve back to the zero baseline.
- Zero Return: In a closed, intact patient-circuit system without gas leaks, the expiratory limb must return exactly to the zero volume baseline before the initiation of the next breath ($V_{TI} = V_{TE}$).
Waveform Anatomy in Volume-Control vs Pressure-Control
+-------------------------------------------------------------------------+
|                  VC-CMV vs PC-CMV SCALAR COMPARISON                     |
+----------------------+--------------------------+-----------------------+
| Feature              | VC-CMV (Volume Control)  | PC-CMV (Pressure Ctrl)|
+----------------------+--------------------------+-----------------------+
| Control Variable     | Flow / Volume (Preset)   | Pressure (Preset)     |
| Dependent Variable   | Airway Pressure (Paw)    | Flow & Delivered VT   |
| Flow Waveform Shape  | Square (constant) / Ramp | Exponential decay     |
| Pressure Waveform    | Linear upward ramp       | Rectangular (flat)    |
| Peak Flow Behavior   | Fixed at set value       | Dependent on ΔP & Raw |
| Effect of Low Crs    | Increases Ppeak & Pplat  | Decreases delivered VT|
| Effect of High Raw   | Increases Ppeak only     | Decreases initial flow|
+----------------------+--------------------------+-----------------------+
Waveform Anatomy in VC-CMV
In VC-CMV, the ventilator's internal microprocessor regulates a piston or proportional solenoid valve to deliver a strictly invariant flow pattern and tidal volume regardless of changes in respiratory system mechanics.
VC-CMV (Constant Square Flow):
  Paw (cmH2O)          Flow (L/min)          Volume (mL)
    ^                    ^                     ^
 PIP|    /|            Set|--------+         VT|     /\
    |   / |               |        |           |    /  \
Pplat  /--|               |        |           |   /    \
    | /   |               |        |           |  /      \
PEEP|/____|__          0  |________|____       0 |/________\____
    +--------> t          +--------> t         +--------> t
                          |   /
                          |  /
                      Peak|_/ (Passive Decay)
Constant (Square) Flow Profile:
- Flow immediately steps up to the set peak flow (e.g., $60\text{ L/min} = 1.0\text{ L/s}$) and remains perfectly flat throughout the preset inspiratory time ($T_I$).
- Pressure waveform shows an immediate initial jump ($\Delta P_{res} = \dot{V} \times R_{aw}$), followed by a linear rise to $P_{peak}$: $$P_{peak} = (\dot{V} \times R_{aw}) + \left(\frac{V_T}{C_{rs}}\right) + PEEP$$
- The slope of the linear pressure ascent ($dP/dt$) is inversely proportional to static compliance: $$\frac{dP}{dt} = \frac{\dot{V}}{C_{rs}}$$
Decelerating (Ramp) Flow Profile in VC-CMV:
- Flow immediately peaks at the beginning of inspiration and decreases linearly to zero or a set fraction (e.g., 5 L/min) at the end of $T_I$.
- Because flow is highest when alveolar volume is lowest, resistive pressure is maximal early in the breath and tapers off as elastic pressure accumulates.
- Consequently, the pressure-time scalar exhibits a rounded, dome-shaped contour with a lower $P_{peak}$ for an identical tidal volume and $T_I$ compared to square flow.
Waveform Anatomy in PC-CMV
In PC-CMV, the ventilator rapidly pressurizes the proximal airway to a preset target pressure ($P_{insp} = PEEP + \Delta P_{insp}$) and maintains this pressure constant throughout the entire inspiratory time ($T_I$).
PC-CMV (Exponential Flow Decay):
  Paw (cmH2O)          Flow (L/min)          Volume (mL)
    ^                    ^                     ^
 Pin|------+           Pk | \                VT|    _--_
    |      |              |  \                 |  /      \
    |      |              |   \                | /        \
    |      |              |    \               |/          \
PEEP|______|__         0  |_____\_______       0|____________\__
    +--------> t          +--------> t         +--------> t
                          |   /
                          |  /
                      Peak|_/
- Pressure-Time Morphology: Rapid vertical rise (governed by the adjustable Rise Time / Slope setting) to the preset pressure limit, followed by a flat rectangular plateau that persists until the end of $T_I$.
- Flow-Time Morphology (Exponential Flow Decay):
- At $t=0$, the alveolar pressure ($P_{alv}$) equals PEEP, producing the maximum driving pressure gradient ($\Delta P = P_{insp} - PEEP$) across the airway resistance ($R_{aw}$). Peak inspiratory flow occurs instantaneously: $$\dot{V}_{peak} = \frac{P_{insp} - PEEP}{R_{aw}}$$
- As gas fills the alveoli, $P_{alv}$ rises toward $P_{insp}$, diminishing the driving pressure gradient. Flow decays exponentially according to the inspiratory time constant ($\tau = R_{aw} \times C_{rs}$): $$\dot{V}(t) = \dot{V}_{peak} \cdot e^{-t / \tau}$$
- If $T_I \ge 3\tau$ to $5\tau$, inspiratory flow reaches zero before cycling, indicating complete alveolar equilibration ($P_{alv} = P_{insp}$).
Inspiratory Hold Maneuver and Airway Pressure Decomposition
An end-inspiratory hold (inflation hold / pause) is performed during passive mechanical ventilation by closing both the inspiratory and expiratory valves for 0.5 to 2.0 seconds at the end of tidal volume delivery.
       INSPIRATORY HOLD DECOMPOSITION
Paw (cmH2O)
 ^
 |             Ppeak (Dynamic Peak Pressure)
 |               /\
 |              /  \
 |             /    +--- ΔPres = Ppeak - Pplat (Resistive Drop = Flow × Raw)
 |            /     |
 |           /      +--------------------+ Pplat (Static Plateau Pressure)
 |          /                            |
 |         /                             +--- Driving Pressure: ΔP = Pplat - PEEPtot
 |        /                              |    (Elastic Recoil = VT / Crs)
 |       /                               |
 |______/                                +--- PEEPtot (PEEPset + PEEPauto)
 |      |                                |
 +------+--------------------------------+---------> Time (t)
   Inspiration     Inspiratory Hold Pause    Passive Expiration
   (Flow > 0)           (Flow = 0)              (Flow < 0)
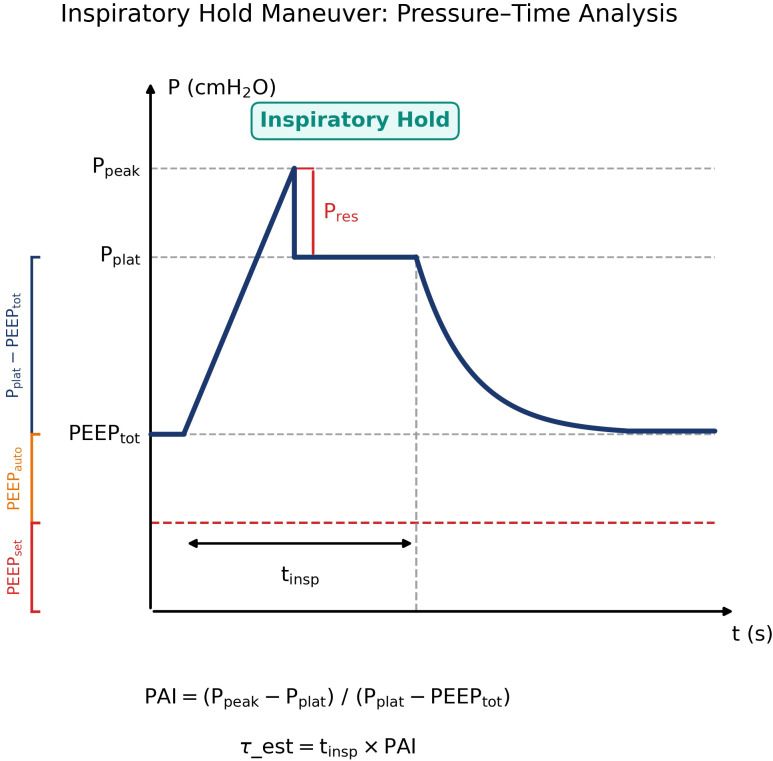 Figure 1: Graphic analysis of the inspiratory hold maneuver and airway pressure decomposition in volume-controlled mechanical ventilation. Closure of the inspiratory and expiratory valves halts airflow ($\dot{V} = 0$), eliminating resistive pressure dissipations ($P_{res} = \dot{V} \times R_{aw}$) and revealing the true static plateau pressure ($P_{plat}$). The transairway pressure gradient ($\Delta P_{res} = P_{peak} - P_{plat}$) directly reflects endotracheal tube and conductive airway resistance. The driving pressure ($\Delta P = P_{plat} - PEEP_{tot}$) represents the true elastic distending pressure across the respiratory system, where $C_{rs} = V_T / \Delta P$. Provenance: Frontiers in Physiology 2026; 17:1846417; DOI: 10.3389/fphys.2026.1846417 (CC-BY 4.0).
Mathematical Derivations from the Hold Maneuver
Peak Inspiratory Pressure ($P_{peak}$):
- Measured during dynamic flow delivery; reflects total combined resistive, elastic, and inertial impedance: $$P_{peak} = (\dot{V} \times R_{aw}) + \left(\frac{V_T}{C_{rs}}\right) + PEEP_{tot}$$
Plateau Pressure ($P_{plat}$):
- Measured during zero airflow ($\dot{V} = 0$). With zero flow, resistive pressure drops to zero ($\dot{V} \times R_{aw} = 0$), leaving only the static elastic recoil pressure of the alveoli and chest wall: $$P_{plat} = \left(\frac{V_T}{C_{rs}}\right) + PEEP_{tot}$$
- Safety Target: $P_{plat} \le 30\text{ cmH}_2\text{O}$ in ARDS to prevent diffuse alveolar overdistension (barotrauma/volutrauma).
Transairway Resistive Pressure Drop ($\Delta P_{res}$):
- The instantaneous vertical drop from $P_{peak}$ to $P_{plat}$: $$\Delta P_{res} = P_{peak} - P_{plat} = \dot{V} \times R_{aw}$$
- Airway Resistance Calculation: $$R_{aw} = \frac{P_{peak} - P_{plat}}{\dot{V}_{insp}\ (\text{L/s})}$$
- Normal in intubated adults: $5\text{--}10\text{ cmH}_2\text{O}/(\text{L/s})$. Values $> 15\text{--}20\text{ cmH}_2\text{O}/(\text{L/s})$ signify severe airway obstruction (bronchospasm, secretions, kinking).
Respiratory System Driving Pressure ($\Delta P$):
- The static pressure difference required to distend the lung parenchyma: $$\Delta P = P_{plat} - PEEP_{tot} = \frac{V_T}{C_{rs}}$$
- Static Respiratory Compliance ($C_{rs}$): $$C_{rs} = \frac{V_T}{P_{plat} - PEEP_{tot}}$$
- Normal compliance in non-intubated lungs: $50\text{--}100\text{ mL/cmH}_2\text{O}$. In ARDS: frequently $< 30\text{ mL/cmH}_2\text{O}$.
- Evidence-Based Target: Amato et al. (NEJM 2015) demonstrated that driving pressure $\Delta P \le 14\text{--}15\text{ cmH}_2\text{O}$ is the single physiological variable most strongly associated with survival in ARDS.
Expiratory Flow Decay and Auto-PEEP Recognition
Passive exhalation is driven exclusively by the potential energy stored in the elastic recoil of the lungs and chest wall during inspiration ($P_{el} = V_T / C_{rs}$).
EXPIRATORY FLOW DECAY PROFILES
Flow (L/min)
 ^
 0 |---------------------------------------------+ Baseline (0 L/min)
   |           /                         /
   |          /                         /| <--- Truncated Expiratory Flow (Auto-PEEP)
   |         / (Complete Return)       / |
   |        /                         /  |
   |_______/                         /   |______ Next breath initiated prematurely
   |      /                         /
-Pk|_____/                         /
   +---------------------------------------------> Time (t)
      Normal (Zero Baseline Met)      Gas Trapping (Auto-PEEP Present)
The Expiratory Time Constant ($\tau_E$)
Expiratory flow decay follows a first-order exponential decay function:
$$\dot{V}_E(t) = \dot{V}_{peak,E} \cdot e^{-t / \tau_E}$$Where the expiratory time constant $\tau_E$ is defined as:
$$\tau_E = R_{aw,E} \times C_{rs}$$- 1 Time Constant ($1\tau_E$): $63.2\%$ of tidal volume is exhaled.
- 2 Time Constants ($2\tau_E$): $86.5\%$ of tidal volume is exhaled.
- 3 Time Constants ($3\tau_E$): $95.0\%$ of tidal volume is exhaled.
- 4 to 5 Time Constants ($4\text{--}5\tau_E$): $> 98.2\text{--}99.3\%$ of tidal volume is evacuated, returning flow to true zero baseline.
Recognizing Dynamic Hyperinflation and Auto-PEEP
- Failure to Reach Zero Flow:
- In obstructive airways disease (COPD, severe asthma), $R_{aw,E}$ is massively elevated, lengthening $\tau_E$ from normal ($0.4\text{--}0.6\text{ s}$) to $> 1.2\text{--}2.0\text{ s}$.
- If expiratory time ($T_E$) is shorter than $3\text{--}4\tau_E$, expiratory flow is abruptly truncated by the subsequent breath above the zero line.
- This truncated non-zero end-expiratory flow confirms dynamic hyperinflation and auto-PEEP (intrinsic PEEP).
- Expiratory Hold Maneuver:
- To quantify auto-PEEP, an end-expiratory hold (0.5 to 2.0 s) is applied. With the airway occluded at end-expiration, trapped alveolar gas equilibrates across the circuit: $$PEEP_{auto} = PEEP_{tot} - PEEP_{set}$$
- Expiratory Flow Limitation (EFL):
- Dynamic compression of small airways during exhalation causes a scooped, non-linear decay pattern on the flow-time scalar with an initial rapid drop followed by a prolonged, flattened tail.
Volume Scalar Analysis and Circuit Leak Detection
The volume-time ($V$-$t$) scalar provides instant verification of delivered vs returned gas volumes.
VOLUME-TIME SCALAR: NORMAL VS AIR LEAK
Volume (mL)
 ^
VT |      /\                          /\
   |     /  \                        /  \
   |    /    \                      /    \
   |   /      \                    /      \_____ <--- Plateau above baseline: Leak Volume
 0 |__/________\_______          _/_____________\___
   +------------------> t        +------------------> t
     Intact Closed System          Circuit / Endotracheal Tube Cuff Leak
Pathognomonic Patterns on the Volume Scalar
- Intact Circuit (Normal Profile):
- Volume ascends smoothly to the set $V_T$ and descends symmetrically back to zero. Expiratory volume equals inspiratory volume ($V_{TE} = V_{TI}$).
- Circuit or Endotracheal Tube Cuff Leak:
- The expiratory tracing fails to return to the zero baseline, creating an abrupt horizontal step or plateau above zero.
- The vertical distance between the plateau and the zero axis corresponds exactly to the leaked volume ($\Delta V_{leak} = V_{TI} - V_{TE}$).
- Differential Diagnosis:
- Ruptured or deflated endotracheal tube pilot balloon / cuff.
- Circuit disconnection or water trap misconnection.
- Bronchopleural fistula or chest tube gas leak.
- Active Patient Exhalation:
- If the expiratory volume tracing dips below the zero baseline, it indicates active abdominal muscle contraction and forced exhalation below functional residual capacity (FRC).
Bedside Troubleshooting Matrix and Clinical Decision Protocol
+----------------------------------------------------------------------------------------------------+
|                         BEDSIDE SCALAR TROUBLESHOOTING ALGORITHM                                   |
+------------------------+---------------------------------+-----------------------------------------+
| Graphic Abnormality    | Pathophysiological Etiology     | Targeted Bedside Action                 |
+------------------------+---------------------------------+-----------------------------------------+
| High Ppeak, Normal     | Increased airway resistance     | Suction airway, clear secretions;       |
| Pplat (ΔPres > 10)     | (bronchospasm, secretions,      | administer bronchodilator; un-kink ETT; |
|                        | biting ETT, small ETT lumen)    | check ETT position with capnography.    |
+------------------------+---------------------------------+-----------------------------------------+
| High Ppeak AND High    | Decreased compliance / elastance| Rule out tension pneumothorax (STAT!);  |
| Pplat (ΔP > 15 cmH2O)  | (ARDS, pulmonary edema,         | treat atelectasis/edema; optimize PEEP; |
|                        | pneumothorax, abdominal comp.)  | lower VT to 4-6 mL/kg PBW for lung prot.|
+------------------------+---------------------------------+-----------------------------------------+
| Non-zero End-          | Dynamic hyperinflation,         | Prolong TE (decrease respiratory rate,  |
| Expiratory Flow        | auto-PEEP (COPD, asthma)        | increase peak flow to 70-80 L/min);     |
|                        |                                 | treat bronchospasm; titrate PEEPset.    |
+------------------------+---------------------------------+-----------------------------------------+
| Pressure-Time          | Patient flow starvation         | Increase set peak inspiratory flow rate;|
| "Scalloping" / Concave | (inspiratory demand > set flow) | switch from square to decelerating flow;|
|                        |                                 | consider switching from VC to PC/PRVC.  |
+------------------------+---------------------------------+-----------------------------------------+
| Expiratory Volume Fails| Airway / circuit leak or        | Check ETT cuff pressure (target 20-30   |
| to Return to Zero      | bronchopleural fistula          | cmH2O); check circuit connections;      |
|                        |                                 | inspect chest tube for air bubbling.    |
+------------------------+---------------------------------+-----------------------------------------+
| Expiratory Flow        | Water condensation in circuit   | Drain water condensation from circuit   |
| Waveform "Chatter"     | tubing / tubing resonance       | tubing water traps; replace filter.     |
+------------------------+---------------------------------+-----------------------------------------+
Practical Clinical Pearls
The Two-Step Diagnostic Rule for High Airway Pressures: Whenever a high peak pressure alarm triggers, immediately perform a 1-second inspiratory hold:
- If $P_{plat}$ is normal ($\le 25\text{--}30\text{ cmH}_2\text{O}$) and $\Delta P_{res} > 10\text{--}15\text{ cmH}_2\text{O}$, the problem is purely resistive (ETT kink, sputum plug, severe bronchospasm). Do not lower tidal volume; treat the airway resistance.
- If $P_{plat}$ is elevated ($> 30\text{ cmH}_2\text{O}$) and driving pressure $\Delta P > 15\text{ cmH}_2\text{O}$, the problem is elastic/parenchymal (pneumothorax, ARDS progression, right mainstem intubation, abdominal compartment syndrome). Immediately auscultate to rule out tension pneumothorax.
Matching PEEP in Auto-PEEP: In spontaneous breathing modes (e.g., Pressure Support Ventilation) with dynamic airway collapse (flow limitation), applying extrinsic $PEEP_{set}$ equal to approximately $70\text{--}80\%$ of measured $PEEP_{auto}$ splints open dynamic airway collapse and reduces the patient's inspiratory work of breathing to trigger the ventilator, eliminating ineffective triggering efforts.
Validity of the Inspiratory Hold: An inspiratory hold maneuver is valid only in fully passive patients. Any active patient inspiratory or expiratory effort during the hold produces negative or positive fluctuations in $P_{aw}$, yielding false $P_{plat}$ and driving pressure measurements. Ensure patient-ventilator harmony or observe a completely flat pressure plateau before recording values.
Key Takeaways
- Scalars are the bedrock of mechanical ventilation monitoring: Real-time examination of $P$-$t$, $\dot{V}$-$t$, and $V$-$t$ waveforms detects resistive obstruction, loss of compliance, gas trapping, and leaks before clinical deterioration occurs.
- The Equation of Motion governs waveform morphology: Airway pressure is the sum of resistive dissipation ($\dot{V} \times R_{aw}$) and elastic alveolar recoil ($V_T / C_{rs}$) above total PEEP.
- The Inspiratory Hold separates resistance from compliance: $P_{peak} - P_{plat}$ isolates airway resistance, while $P_{plat} - PEEP_{tot}$ isolates parenchymal driving pressure ($\Delta P$), the prime determinant of lung injury and mortality in ARDS.
- Expiratory flow decay detects auto-PEEP: Failure of expiratory flow to return to zero baseline before subsequent breath delivery is the diagnostic hallmark of dynamic hyperinflation.
- Volume scalar non-return signals leaks: A persistent plateau above the zero line on the volume-time scalar quantifies the lost volume from an endotracheal tube cuff leak, circuit disconnection, or bronchopleural fistula.