Synchronized Intermittent Mandatory Ventilation (SIMV) and Pressure Support Ventilation (PSV) represent pivotal modes in mechanical ventilation, designed to support spontaneous breathing while preserving a baseline level of alveolar minute ventilation. SIMV combines preset mandatory breaths—delivered at a fixed backup rate with either volume or pressure targets—with unrestricted spontaneous breaths between mandatory cycles. Pressure Support Ventilation provides pressure-assisted, flow-cycled augmentation to every spontaneous inspiratory effort, reducing the imposed work of breathing ($WOB_{\text{imp}}$) incurred by the endotracheal tube (ETT), breathing circuit, and demand valves.
Fundamental Mechanics of SIMV
The SIMV Timing Cycle and Windows
The SIMV respiratory cycle is partitioned into distinct temporal phases determined by the preset mandatory frequency ($f_{\text{SIMV}}$), which establishes the total cycle duration ($T_{\text{cycle}} = 60 / f_{\text{SIMV}}$):
Mandatory Synchronization Trigger Window:
- At the beginning of each SIMV cycle, the ventilator opens a trigger synchronization window (typically lasting $0.5 \text{ to } 1.5\text{ seconds}$, or up to $20\text{--}25\%$ of $T_{\text{cycle}}$).
- If the patient initiates a spontaneous effort that satisfies the trigger threshold (flow trigger $\dot{V}_{\text{trig}}$ or pressure trigger $P_{\text{trig}}$) during this window, the ventilator synchronizes delivery and immediately provides an assisted mandatory breath (volume-controlled or pressure-controlled).
- If no spontaneous effort occurs within this trigger window, the ventilator automatically delivers a time-triggered mandatory breath at the expiration of the window.
Spontaneous Window:
- Following delivery and exhalation of the mandatory breath, the remainder of the $T_{\text{cycle}}$ constitutes the spontaneous breathing window.
- Any patient effort initiated during this period does not trigger a mandatory breath; instead, it opens the demand valve to deliver a purely spontaneous breath or a pressure-supported breath (PSV) if Pressure Support is programmed.
- The tidal volume ($V_T$) and inspiratory time ($T_i$) during this window are dictated entirely by patient neuro-ventilatory drive, patient effort ($P_{\text{mus}}$), respiratory mechanics (compliance $C_{\text{rs}}$ and resistance $R_{\text{aw}}$), and the level of applied Pressure Support ($\Delta P_{\text{supp}}$).
|<----------------------------- Total Cycle Time (Tcycle = 60 / f) ----------------------------->|
|-- Synchronization Window --|----------------------- Spontaneous Window -----------------------|
   [Patient Effort Present]  --> Delivers Synchronized Mandatory Breath (VCV or PCV)
   [No Effort Detected]      --> Delivers Time-Triggered Mandatory Breath
                             --> Patient Efforts Trigger Pressure-Supported Breaths (PSV)
Prevention of Breath Stacking
Historical non-synchronized Intermittent Mandatory Ventilation (IMV) delivered mandatory breaths at rigid clock intervals regardless of patient phase. If a mandatory machine cycle triggered during spontaneous peak inspiration or early exhalation, massive alveolar overdistension (breath stacking) and dangerously elevated transpulmonary pressures occurred. SIMV eliminated this by delaying or synchronizing mandatory delivery to the onset of the patient's spontaneous inspiratory effort.
Comparative Modalities: SIMV-VC vs. SIMV-PC vs. Standalone PSV
| Operational Feature | SIMV-VC (Volume-Controlled) | SIMV-PC (Pressure-Controlled) | Pressure Support Ventilation (PSV) |
|---|---|---|---|
| Control Variable | Volume (constant/decelerating flow) for mandatory breaths | Pressure (decelerating flow) for mandatory breaths | Pressure (decelerating flow) for all breaths |
| Mandatory Breaths | Set $V_T$, flow rate, flow waveform, and backup frequency | Set $P_{\text{insp}}$, $T_i$, and backup frequency | None (purely spontaneous; backup apnea ventilation only) |
| Spontaneous Breaths | Pressure-supported ($\Delta P_{\text{supp}}$) or unassisted | Pressure-supported ($\Delta P_{\text{supp}}$) or unassisted | All breaths supported by preset $\Delta P_{\text{supp}}$ |
| Mandatory Cycling | Volume-cycled / Time-cycled | Time-cycled ($T_i$) | Flow-cycled ($E_{\text{sens}}$ / cycle-off %) |
| Spontaneous Cycling | Flow-cycled (or unassisted spontaneous) | Flow-cycled (or unassisted spontaneous) | Flow-cycled ($E_{\text{sens}}$ threshold) |
| Tidal Volume Guarantee | Guaranteed on mandatory cycles only | Variable (dependent on $C_{\text{rs}}$, $R_{\text{aw}}$, $P_{\text{mus}}$) | Variable on all breaths |
| Peak Pressure Control | Variable on mandatory cycles | Capped ($P_{\text{insp}} + \text{PEEP}$) | Capped ($P_{\text{supp}} + \text{PEEP}$) |
Overcoming Imposed Work of Breathing ($WOB_{\text{imp}}$)
During unassisted spontaneous breathing through an artificial airway, the patient must generate significant negative intrapleural pressure to pull gas through the endotracheal tube (ETT) and trigger mechanical demand valves.
The Physics of ETT Resistance: Rohrer's Equation
Gas flow through an endotracheal tube exhibits turbulent and transitional flow characteristics, modeled by Rohrer's equation:
$$\Delta P_{\text{ETT}} = K_1 \cdot \dot{V} + K_2 \cdot \dot{V}^2$$Where:
- $K_1$ represents the laminar resistive coefficient (dependent on gas viscosity and internal diameter, $r^4$).
- $K_2$ represents the turbulent resistive coefficient (dependent on gas density and tube geometry, $r^5$).
Because resistance scales inversely with the 4th to 5th power of the internal diameter, smaller tubes ($6.5\text{--}7.5\text{ mm}$) substantially increase resistive load during high peak inspiratory flows ($\dot{V} > 60\text{ L/min}$).
Total Work of Breathing Partitioning
Total inspiratory work of breathing ($WOB_{\text{tot}}$) comprises physiological work ($WOB_{\text{phys}}$) and imposed work ($WOB_{\text{imp}}$):
$$WOB_{\text{tot}} = WOB_{\text{phys}} + WOB_{\text{imp}} = \int P_{\text{mus}} \, dV + \int \Delta P_{\text{apparatus}} \, dV$$Without Pressure Support, $WOB_{\text{imp}}$ can account for up to $40\text{--}60\%$ of total patient work, precipitating diaphragmatic fatigue. Applying a baseline Pressure Support ($\Delta P_{\text{supp}}$ of $5\text{--}8\text{ cmH}_2\text{O}$) specifically neutralizes $WOB_{\text{imp}}$, restoring the net load to that of natural un-intubated breathing.
Pressure Support Ventilation: Flow-Cycling and Pressurization Mechanics
In Pressure Support Ventilation, the ventilator targets and maintains a preset pressure above PEEP ($\Delta P_{\text{supp}}$) throughout the patient's spontaneous inspiratory effort. Delivery is governed by two crucial mechanical adjustments: the Pressurization Slope (Rise Time) and the Expiratory Trigger Sensitivity ($E_{\text{sens}}$ / Cycle-Off %).
Pressure (Paw)
  ^
  |        /-------------------\ (Psupp + PEEP)
  |       /  ^                  \
  |      /   | Rise Time         \
  |     /                         \
  |----+---------------------------\-------- PEEP
  +---------------------------------------------> Time
Flow (V')
  ^
  |    |\ (Peak Flow)
  |    | \
  |    |  \
  |    |   \
  |    |    \  <- Expiratory Trigger Threshold (e.g., 25% of Peak Flow)
  |----+-----\---------------------------------- 0 Flow
  |           \        /
  |            \______/ (Expiratory Flow)
  +---------------------------------------------> Time
1. Pressurization Slope / Rise Time Titration
- Definition: The time required for airway pressure to rise from baseline PEEP to the target pressure ($P_{\text{supp}} + \text{PEEP}$), adjustable from $0.05\text{ to } 0.4\text{ seconds}$ (or expressed as a percentage/scale depending on manufacturer).
- High Ventilatory Drive / Air Hunger (e.g., severe sepsis, metabolic acidosis, early ARDS):
- Setting: Fast rise time ($0.05\text{--}0.10\text{ s}$).
- Rationale: Delivers immediate high initial flow matches vigorous patient inspiratory demand, preventing trigger delay and patient-ventilator flow starvation.
- Obstructive Airway Disease (e.g., COPD, severe asthma):
- Setting: Moderate rise time ($0.15\text{--}0.25\text{ s}$).
- Rationale: Excessively fast rise times in high-resistance airways cause pressure overshoot, triggering early flow termination before adequate volume is delivered.
- Low Ventilatory Drive / Comfort Optimization:
- Setting: Gentle slope ($0.20\text{--}0.30\text{ s}$) to prevent abrupt pressure shocks.
2. Expiratory Trigger Sensitivity ($E_{\text{sens}}$ / Cycle-Off Percentage)
Inspiration in PSV terminates when the decelerating inspiratory flow drops to a preset fraction of peak inspiratory flow:
$$\dot{V}_{\text{term}} = E_{\text{sens}} \cdot \dot{V}_{\text{peak}}$$- Default Threshold: Typically set at $25\%$ of peak flow.
- Obstructive Lung Mechanics (COPD / Asthma):
- Pathophysiology: Markedly elevated airway resistance and dynamic hyperinflation result in a prolonged respiratory time constant ($\tau = R_{\text{aw}} \cdot C_{\text{rs}}$). Inspiratory flow decays slowly.
- Consequence of Default $25\%$: Delayed cycling occurs; mechanical insufflation continues after the patient has initiated active neural exhalation, forcing the patient to exhale against an open inspiratory valve.
- Titration: Increase $E_{\text{sens}}$ to $40\text{--}70\%$ of peak flow. This terminates mechanical inspiration early, granting ample time for exhalation and minimizing dynamic intrinsic PEEP ($\text{PEEP}_i$).
- Restrictive Lung Mechanics (ARDS / Pulmonary Fibrosis / Chest Wall Stiffness):
- Pathophysiology: Reduced compliance results in very short respiratory time constants ($\tau$). Inspiratory flow drops abruptly.
- Consequence of Default $25\%$: Premature cycling occurs; the ventilator terminates the breath while the patient's neural inspiration continues, leading to double-triggering or flow starvation.
- Titration: Decrease $E_{\text{sens}}$ to $5\text{--}15\%$ of peak flow. This prolongs mechanical inspiratory time, improving alveolar recruitment and physiological tidal volume delivery.
Patient-Ventilator Asynchrony in Spontaneous and Supported Ventilation
The interaction between patient neural breathing rhythms and ventilator cycling criteria directly impacts clinical outcomes, diaphragmatic integrity, and weaning success.
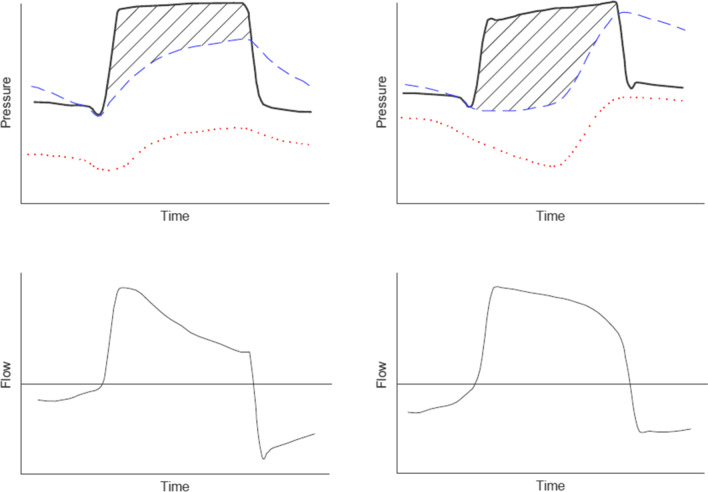 Figure 1: Airway pressure ($P_{aw}$), oesophageal pressure ($P_{es}$), alveolar pressure and inspiratory airflow recorded during pressure support ventilation. The descending inspiratory flow curve is generated by the interaction between the patient's own inspiratory effort and the applied support: the greater the effort, the further the flow curve departs from exponential decay towards downward concavity. This is the physiological basis of the Flow Index and of bedside recognition of over- and under-assistance. (Source: Albani F, et al. Critical Care 2021. DOI:
10.1186/s13054-021-03624-3
, PMCID: PMC8182360).
Major Forms of Asynchrony
- Ineffective Triggering:
- Patient generates an inspiratory effort, but dynamic intrinsic PEEP ($\text{PEEP}_i$) prevents the airway pressure or flow from crossing the trigger threshold.
- Waveform Sign: Negative deflection on $P_{\text{AW}}$ and positive transient blip on expiratory flow during exhalation without subsequent mechanical delivery.
- Premature (Early) Cycling:
- Ventilator cycles to expiration while the diaphragm is still contracting.
- Waveform Sign: Abrupt drop in airway pressure and early expiratory flow spike while diaphragm electromyography or esophageal manometry shows ongoing inspiration.
- Delayed (Late) Cycling:
- Ventilator continues pressurization after neural inspiration ends and neural exhalation begins.
- Waveform Sign: End-inspiratory spike in $P_{\text{AW}}$ ("pressure spike" or camel-back profile) as the patient actively exhales against positive inspiratory pressure.
- Double Triggering:
- High neural drive or premature cycling triggers two consecutive mechanical breaths within $<0.5\text{ s}$, doubling the delivered tidal volume and elevating dynamic driving pressure.
Why SIMV Fails as a Weaning Mode: Pathophysiological and Clinical Evidence
Historically, SIMV was championed as a primary weaning modality: clinicians gradually reduced the mandatory rate ($f_{\text{SIMV}}$ from $12 \rightarrow 8 \rightarrow 4 \rightarrow 2\text{ bpm}$), expecting the respiratory musculature to progressively assume the workload. However, large landmark randomized clinical trials unequivocally proved that SIMV is the slowest, least effective, and most failure-prone weaning strategy.
Physiological Mechanisms of Failure
- Unstable Work of Breathing ($WOB$) and Muscle Fatigue:
- In SIMV, the patient experiences two radically different mechanical environments within the same minute: high-volume, fully unloaded mandatory breaths interspersed with low-volume, high-workload spontaneous breaths.
- Respiratory center neural output fails to adapt rapidly to alternating breath types. The patient exhibits persistent high neuromuscular drive during spontaneous cycles, resulting in rapid shallow breathing, diaphragmatic glycogen depletion, and lactic acidosis.
- Dynamic Asynchrony and Ventilatory Instability:
- The constant transition between mandatory and spontaneous cycles fosters profound patient-ventilator dyssynchrony, anxiety, and sympathetic overdrive.
- Disuse Atrophy vs. Exhaustion Paradox:
- High SIMV backup rates promote ventilator-induced diaphragmatic dysfunction (VIDD), while low SIMV rates cause respiratory muscle fatigue due to uncompensated ETT resistance on spontaneous breaths.
Clinical Trial Evidence: SIMV vs. Daily SBT vs. PSV Weaning
                    Comparison of Weaning Success Rates
Weaning Modality        Median Time to Extubation      Weaning Failure Rate
-----------------------------------------------------------------------------
Daily SBT (T-piece/PSV)       3 to 4 Days (Fastest)            Lowest
Gradual PSV Weaning           4 to 5 Days                      Intermediate
SIMV Rate Weaning             5 to 7 Days (Slowest)            Highest
-----------------------------------------------------------------------------
Evidence: Esteban A, et al. N Engl J Med. 1995; 332(6):345-350.
          Brochard L, et al. Am J Respir Crit Care Med. 1994; 150(4):896-903.
- Esteban et al. (NEJM 1995): Landmark trial comparing once-daily Spontaneous Breathing Trials (SBT), multiple daily SBTs, PSV titration, and gradual SIMV weaning. Daily SBT achieved successful extubation nearly twice as fast as SIMV rate reduction ($p < 0.001$).
- Brochard et al. (AJRCCM 1994): Demonstrated that weaning with SIMV required significantly more days of mechanical ventilation and exhibited the highest rate of weaning failure compared to PSV and T-piece trials.
- Current Guideline Consensus: The ATS/CHEST guidelines recommend against using SIMV as a weaning method. Weaning should be conducted via structured daily Spontaneous Breathing Trials (SBT) using low-level PSV ($5\text{--}8\text{ cmH}_2\text{O}$) or T-piece trials.
Bedside Titration Protocols and Numerical Parameters
1. Initial SIMV Settings Protocol (Full Ventilatory Support Phase)
| Ventilator Parameter | Recommended Initial Target | Clinical Rationale / Safety Threshold |
|---|---|---|
| Mandatory Mode | SIMV-VC or SIMV-PC | Match clinician familiarity and lung mechanics |
| Mandatory Rate ($f_{\text{SIMV}}$) | $10\text{--}14\text{ bpm}$ | Provides $70\text{--}80\%$ of baseline minute ventilation |
| Mandatory $V_T$ (if VC) | $6\text{--}8\text{ mL/kg}$ PBW | $4\text{--}6\text{ mL/kg}$ PBW in ARDS; keep $P_{\text{plat}} \le 30\text{ cmH}_2\text{O}$ |
| Mandatory $P_{\text{insp}}$ (if PC) | Titrate for $V_T \approx 6\text{--}8\text{ mL/kg}$ | Keep driving pressure $\Delta P \le 14\text{--}15\text{ cmH}_2\text{O}$ |
| Pressure Support ($\Delta P_{\text{supp}}$) | $8\text{--}14\text{ cmH}_2\text{O}$ above PEEP | Unload ETT resistance; target spontaneous $V_T \ge 5\text{--}7\text{ mL/kg}$ |
| Trigger Sensitivity | Flow: $1.5\text{--}2.0\text{ L/min}$; Press: $-1.0\text{ to } -1.5\text{ cmH}_2\text{O}$ | Avoid auto-triggering while minimizing trigger delay |
| PEEP | $5\text{--}12\text{ cmH}_2\text{O}$ | Prevent alveolar collapse; titrate per $\text{FiO}_2$ table |
| Rise Time (Slope) | $0.10\text{--}0.20\text{ s}$ | Adjust for patient inspiratory comfort and flow demand |
| $E_{\text{sens}}$ (Cycle-off) | $25\%$ default ($40\text{--}50\%$ in COPD; $10\text{--}15\%$ in ARDS) | Optimize expiratory synchrony |
2. Standalone Pressure Support Ventilation (PSV) Titration Algorithm
                           [ Patient on Standalone PSV ]
                                        |
        +-------------------------------+-------------------------------+
        |                               |                               |
[ Hypoventilation / High WOB ]   [ Target Synchrony ]           [ Over-Assistance ]
  - Spont RR > 30 bpm              - Spont RR: 16-25 bpm          - Spont RR < 12 bpm
  - Spont VT < 5 mL/kg PBW         - Spont VT: 6-8 mL/kg PBW      - Spont VT > 9-10 mL/kg PBW
  - Accessory muscle use           - Patient comfortable          - Ineffective triggers present
  - Rapid Shallow Breath Index     - RSBI < 80                    - Low patient Pmus
    (RSBI) > 105                        |                              |
        |                               v                              v
        v                        [ Maintain Settings ]          [ Reduce PS Level ]
[ Increase PS by 2-3 cmH2O ]                                    - Decrease PS by 2 cmH2O
- Ensure ETT not obstructed                                     - Re-evaluate RSBI & drive
- Optimize Rise Time / Esens
3. Step-by-Step Liberation (SBT) Protocol
- Screening Criteria for Liberation Readiness:
- Resolution/improvement of underlying acute respiratory failure.
- Oxygenation: $\text{PaO}_2/\text{FiO}_2 \ge 150\text{--}200$ with $\text{PEEP} \le 8\text{ cmH}_2\text{O}$ and $\text{FiO}_2 \le 0.40\text{--}0.50$.
- Hemodynamic stability: Minimal vasopressor support (e.g., Norepinephrine $\le 0.05\text{ mcg/kg/min}$ pressure equivalent), no active myocardial ischemia.
- Neurological: Intact cough reflex, purposeful response, adequate mental status.
- Conducting the Spontaneous Breathing Trial (SBT):
- Transition patient directly from full assist mode to PSV $5\text{--}8\text{ cmH}_2\text{O}$ with PEEP $\le 5\text{ cmH}_2\text{O}$ (or T-piece) for $30\text{--}120\text{ minutes}$.
- Do NOT wean SIMV rates stepwise.
- Assessment of SBT Success:
- Rapid Shallow Breathing Index (RSBI): $$\text{RSBI} = \frac{f \text{ (breaths/min)}}{V_T \text{ (Liters)}} < 105$$
- Hemodynamics: Heart rate $< 130\text{ bpm}$ (or $<20\%$ change), systolic BP $90\text{--}160\text{ mmHg}$.
- Gas Exchange: $\text{SpO}_2 \ge 90\%$, $\text{pH} \ge 7.32$, change in $\text{PaCO}_2 \le 8\text{--}10\text{ mmHg}$.
- Clinical: Absence of diaphoresis, thoracoabdominal paradox, severe agitation, or sternocleidomastoid use.
Bedside Troubleshooting & Red Flags
SIMV-Induced Tachypnea & Fatigue Paradox: When a patient on SIMV develops tachypnea, never reflexively reduce the mandatory rate. If the spontaneous breaths have inadequate Pressure Support, the patient will hyperventilate due to severe imposed resistive load ($WOB_{\text{imp}}$). Either increase the spontaneous Pressure Support ($\Delta P_{\text{supp}} \ge 10\text{--}12\text{ cmH}_2\text{O}$) or transition back to full assist-control (A/C).
Dynamic Hyperinflation & Late Cycling in COPD: In obstructive airway disease, setting $E_{\text{sens}}$ too low ($10\text{--}25\%$) leads to late cycling. The patient attempts active exhalation while the ventilator is still insufflating, producing marked dynamic hyperinflation, auto-PEEP, and ineffective trigger efforts. Always increase $E_{\text{sens}}$ to $40\text{--}60\%$ in COPD patients.
Over-Assistance & Ventilator-Induced Diaphragmatic Dysfunction (VIDD): Setting excessively high Pressure Support ($\Delta P_{\text{supp}} > 16\text{--}18\text{ cmH}_2\text{O}$) produces excessive tidal volumes ($>10\text{ mL/kg}$), suppresses patient central respiratory drive ($P_{0.1} < 1.0\text{ cmH}_2\text{O}$), causes ineffective triggering, and induces rapid myofibrillar proteolysis of the diaphragm. Maintain physiological spontaneous tidal volumes of $6\text{--}8\text{ mL/kg}$ PBW.
Key Clinical Takeaways & Pearls
- SIMV Architecture: Mandatory cycles occur in a synchronized trigger window; all intermediate cycles are spontaneous.
- Pressure Support is Mandatory in SIMV: Spontaneous breaths within SIMV must receive adequate Pressure Support ($\Delta P_{\text{supp}} \ge 5\text{--}10\text{ cmH}_2\text{O}$) to overcome the imposed resistance of the endotracheal tube and demand valves.
- Flow Cycling Customization:
- COPD / Obstruction: Increase $E_{\text{sens}}$ ($40\text{--}70\%$) to cut inspiration early and maximize expiratory time.
- ARDS / Restriction: Decrease $E_{\text{sens}}$ ($5\text{--}15\%$) to prevent premature cycling and flow starvation.
- Abandon SIMV for Weaning: Progressive SIMV rate weaning prolongs mechanical ventilation and increases weaning failure. Practice structured daily Spontaneous Breathing Trials (SBT) using low-level PSV ($5\text{--}8\text{ cmH}_2\text{O}$) or T-piece trials.
- Monitor Asynchrony: Regularly inspect scalar waveforms for ineffective triggers, premature cycling, delayed cycling, and double triggering to prevent diaphragmatic fatigue and lung injury.