Patient-ventilator asynchrony (PVA) refers to a mismatch between the patient’s neural respiratory drive (timing, duration, and magnitude of muscular effort) and the mechanical assistance delivered by the positive pressure ventilator. PVA occurs in $25\%$ to $80\%$ of mechanically ventilated intensive care unit (ICU) patients across various phases of mechanical ventilation.
Rather than benign waveform perturbations, persistent asynchronies cause substantial pathophysiological derangements: elevated work of breathing (WOB), respiratory muscle fatigue, diaphragm fiber microtrauma, patient distress, excessive sedation and neuromuscular blockade exposure, worsening gas exchange, dynamic hyperinflation, occult breath-stacking volutrauma, prolonged duration of mechanical ventilation, tracheostomy, weaning failure, and increased ICU and hospital mortality.
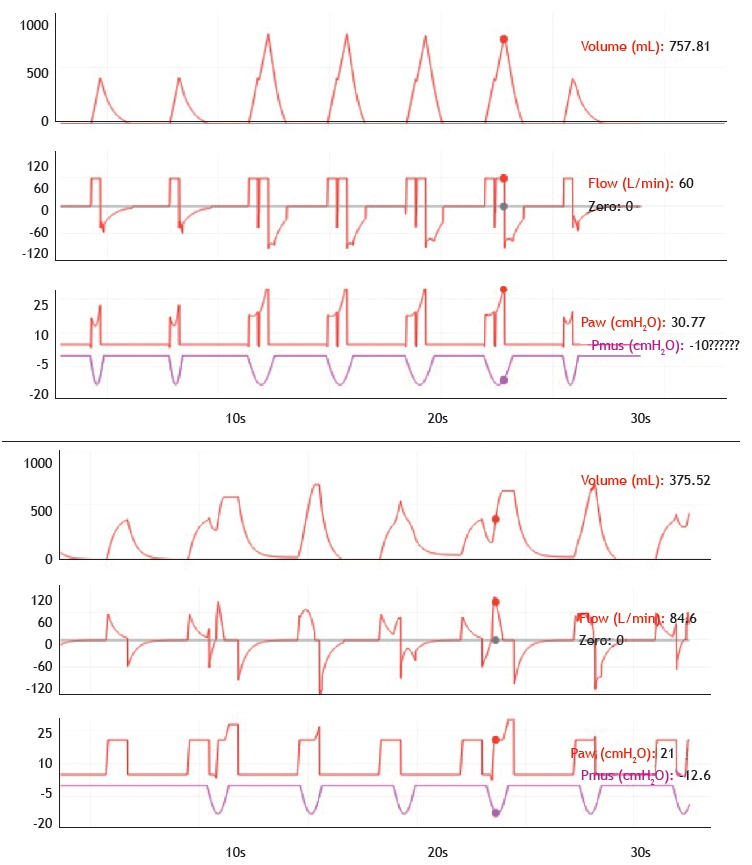 Figure 1: Diagnostic ventilator scalar waveforms demonstrating complex patient-ventilator asynchronies with simultaneous esophageal pressure ($P_{mus}$) recordings. Top panel: Patient-triggered double triggering during Volume-Controlled Ventilation (VC-CMV) where persistent patient inspiratory effort ($P_{mus} \approx -10\text{ to }-15\text{ cmH}_2\text{O}$) outlasts the mechanical inspiratory time ($T_i$), re-triggering a second consecutive breath before complete exhalation and stacking delivered tidal volume to $>750\text{ mL}$. Bottom panel: Reverse triggering in a deeply sedated patient during Pressure-Controlled Ventilation (PC-CMV), where machine-delivered breaths reflexively entrain a delayed diaphragmatic contraction ($P_{mus}$ deflection occurring during or at the end of the mechanical breath), triggering a stacked second pressure cycle. Sourced from Holanda et al., J Bras Pneumol 2018;44(4):321-333. DOI: 10.1590/s1806-37562017000000185 (Open Access / CC BY 4.0).
Neuro-Ventilatory Coupling and The Equation of Motion
Synchronous mechanical ventilation requires harmony across four sequential phases of every respiratory cycle:
- Triggering Phase: Transition from expiration to inspiration.
- Delivery (Flow/Targeting) Phase: Gas delivery matching instantaneous flow and volume demands.
- Cycling Phase: Transition from inspiration to expiration.
- Expiratory Phase: Unimpeded lung emptying back to end-expiratory equilibrium (FRC).
The physical relationship governing patient-ventilator interaction is described by the dynamic equation of motion of the respiratory system:
$$P_{vent}(t) + P_{mus}(t) = \text{Flow}(t) \times R_{aw} + \frac{V(t)}{C_{rs}} + PEEP_{tot}$$Where:
- $P_{vent}(t)$ is the airway pressure delivered by the ventilator relative to atmospheric pressure ($\text{cmH}_2\text{O}$).
- $P_{mus}(t)$ is the pressure generated by the patient's inspiratory muscles ($\text{cmH}_2\text{O}$). During active contraction, $P_{mus}(t)$ becomes negative relative to baseline, reducing intrathoracic and pleural pressure ($P_{pl}$).
- $\text{Flow}(t)$ is the instantaneous gas flow ($\text{L/s}$).
- $R_{aw}$ is the airway and endotracheal tube resistance ($\text{cmH}_2\text{O}\cdot\text{s/L}$).
- $V(t)$ is the lung volume above end-expiratory lung volume ($\text{L}$).
- $C_{rs}$ is the static compliance of the total respiratory system ($\text{L/cmH}_2\text{O}$).
- $PEEP_{tot} = PEEP_{extrinsic} + PEEP_{intrinsic}$ is total positive end-expiratory pressure ($\text{cmH}_2\text{O}$).
When $P_{vent}(t)$ fails to synchronize in timing, flow amplitude, or duration with $P_{mus}(t)$, asynchrony ensues.
Neural Output (Brainstem) ──> Phrenic Nerve ──> Diaphragm (Edi / Pmus) ──> Pneumatic Signal (Paw / Flow) ──> Ventilator Valve
     │                                                                                                                │
     └──────────────────────────────── NEURO-VENTILATORY COUPLING ────────────────────────────────────────────────────┘
Complete Clinical Taxonomy of Patient-Ventilator Asynchrony
Patient-ventilator asynchronies are classified into three primary operational domains based on the phase of the mechanical cycle in which the mismatch occurs: Trigger Asynchronies, Flow (Targeting) Asynchronies, and Cycling (Off-Switching) Asynchronies.
                           PATIENT-VENTILATOR ASYNCHRONIES
                                         │
     ┌───────────────────────────────────┼───────────────────────────────────┐
     │                                   │                                   │
     ▼                                   ▼                                   ▼
TRIGGER ASYNCHRONIES             FLOW ASYNCHRONIES                  CYCLING ASYNCHRONIES
- Ineffective / Wasted Trigger   - Flow Starvation (Inadequate)     - Premature Cycling (Short Ti)
- Auto-Triggering (Leaks/Oscill) - Excessive Flow (Overshoot)       - Delayed / Prolonged Cycling
- Double Triggering (High Drive)                                    - Expiratory Muscle Braking
- Reverse Triggering (Entrained)
1. Trigger Asynchronies
The triggering phase initiates mechanical gas delivery when the ventilator senses a drop in airway pressure ($\Delta P$) or a divergence in continuous circuit bias flow ($\Delta \dot{V}$) produced by patient effort.
A. Ineffective (Wasted / Missed) Triggering
- Definition & Pathophysiology: The patient generates a neural and muscular inspiratory effort ($P_{mus} > 0$), but the resulting pneumatic signal fails to reach the preset trigger threshold; consequently, no ventilator assistance is delivered. Ineffective triggering represents the single most frequent asynchrony in ICU patients (accounting for $>50\%$ of all recorded asynchronous events), especially in severe obstructive lung disease (COPD, asthma) and during high levels of Pressure Support Ventilation (PSV).
- Underlying Mechanisms:
- Dynamic Hyperinflation & Intrinsic PEEP ($PEEP_i$): In airflow obstruction, prolonged expiratory time constants ($\tau = R_{aw} \times C_{rs}$) prevent complete lung emptying before the next breath. Alveolar pressure remains positive at end-expiration ($PEEP_i$). To trigger the ventilator, the patient's respiratory muscles must first contract with sufficient force to pull alveolar pressure below the extrinsic PEEP level ($PEEP_e$) plus the trigger threshold: $$\Delta P_{mus,\text{threshold}} = PEEP_i - PEEP_e + \Delta P_{trigger}$$ If patient strength is insufficient to overcome this threshold load (e.g., $PEEP_i = 10\text{ cmH}_2\text{O}$, $PEEP_e = 5\text{ cmH}_2\text{O}$, Trigger $= 2\text{ cmH}_2\text{O} \implies \Delta P_{mus} \ge 7\text{ cmH}_2\text{O}$ required), the effort is wasted.
- Diaphragmatic Weakness & ICU-Acquired Neuromyopathy: Severe muscle atrophy, sepsis-induced diaphragm dysfunction, steroid/paralytic myopathy, or severe malnutrition reduce maximum inspiratory pressure generation ($P_{imax}$).
- Over-Assistance / Excessive Ventilator Support: High pressure support levels or excessive tidal volumes drive $PaCO_2$ down toward or below the apneic threshold. The brainstem responds by reducing neural drive, causing low-amplitude, abortive muscular efforts.
- Blunted Trigger Sensitivity Settings: Insensitive trigger settings (e.g., pressure trigger $-4\text{ cmH}_2\text{O}$ or flow trigger $5\text{ L/min}$).
- Waveform Recognition:
- Flow-Time Scalar: A transient positive upward deflection (notch) in the expiratory flow curve during exhalation that does not transition into an inspiratory delivery.
- Airway Pressure ($P_{aw}$) Scalar: A subtle negative dip in baseline pressure during the expiratory phase without a subsequent pressure delivery.
- Esophageal Pressure ($P_{es}$) / Electrical Diaphragm Activity ($Edi$): A clear negative dip in $P_{es}$ or burst in $Edi$ without an accompanying mechanical breath.
Flow (L/min)
  ^        +---------------+
  |       /|               |
0 +------+ |               +-------------------------------+
  |        |               |      \       / \       /
  |                        |       \_____/   \_____/  <-- Ineffective Effort (expiratory flow blip)
  v                        +--------\-------/
                           Inspiration     Expiration
B. Auto-Triggering (False / Self-Triggering)
- Definition & Pathophysiology: The ventilator delivers a mechanical breath that was not initiated by patient effort. The machine falsely interprets non-respiratory pressure or flow perturbations as patient demand.
- Underlying Mechanisms:
- Circuit Leaks: In invasive ventilation with unsealed endotracheal/tracheostomy cuffs or in non-invasive ventilation (NIV) mask leaks, gas escaping continuously from the circuit creates a persistent drop in returned flow. Once this leak exceeds the flow-trigger threshold ($\Delta \dot{V}$), the ventilator fires autonomously in a continuous runaway cycle.
- Cardiogenic Oscillations: Mechanical systole and diastole transmit pressure pulses from the beating heart and aorta to the adjacent pulmonary parenchyma and major airways. In patients with large stroke volumes, dilated cardiomyopathy, or hyperdynamic circulation combined with compliant lungs, these oscillations produce periodic pressure fluctuations ($\pm 0.5\text{ to }1.5\text{ cmH}_2\text{O}$) and flow oscillations ($\pm 2\text{ to }4\text{ L/min}$) sufficient to breach sensitive triggers.
- Circuit Condensation / Water Accumulation: Water condensation pooling in corrugated ventilator tubing sloshes rhythmically with gas flow, generating rapid cyclic flow spikes that trip flow triggers.
- Overly Sensitive Trigger Thresholds: Setting trigger thresholds near zero (e.g., flow trigger $\le 0.5\text{ L/min}$ or pressure trigger $\ge -0.5\text{ cmH}_2\text{O}$).
- Waveform Recognition:
- Ventilator cycling at elevated, steady respiratory rates in deeply sedated or paralyzed patients without corresponding negative deflections on the $P_{aw}$ or $P_{es}$ scalars.
- Small, regular sinusoidal fluctuations on the flow-time and pressure-time curves coinciding with ECG R-waves.
C. Double Triggering
- Definition & Pathophysiology: Two consecutive ventilator-delivered breaths separated by an expiratory time ($T_e$) shorter than half the mean inspiratory time ($T_e < 0.5 \times T_i$), where the second breath is triggered by the continuation of the patient's initial inspiratory effort.
- Underlying Mechanisms:
- High Neural Respiratory Drive vs Short Mechanical $T_i$: The patient's neural inspiratory time ($T_{i,neural}$) significantly outlasts the ventilator's preset mechanical inspiratory time ($T_{i,vent}$). When the ventilator cycles off into expiration, the patient's diaphragm is still actively contracting ($P_{mus}$ remains strongly negative). This ongoing effort immediately pulls airway pressure/flow below the trigger threshold at the start of exhalation, triggering a second breath.
- Clinical Context: Common in severe ARDS (high drive driven by metabolic acidosis, hypoxemia, or lung inflammation) ventilated with strict lung-protective low tidal volumes ($6\text{ mL/kg}$ PBW) and short inspiratory times in VC-CMV.
- Consequences: Occult Breath Stacking. The second tidal volume is delivered before the first volume has been exhaled, resulting in a combined delivered volume up to $1.5\times \text{ to } 2.0\times$ the target ($10\text{ to }15\text{ mL/kg}$ PBW), dramatically increasing alveolar peak and plateau pressures and driving transpulmonary pressure ($P_L = P_{aw} - P_{pl}$) into dangerous VILI ranges (volutrauma and barotrauma).
- Waveform Recognition:
- Two consecutive pressure/flow deliveries with virtually zero intervening expiratory flow.
- The volume-time curve steps up to a stacked summit before returning to baseline.
D. Reverse Triggering (Respiratory Entrainment)
- Definition & Pathophysiology: A phenomenon wherein a mandatory, machine-delivered breath triggers a reflex neural inspiratory effort from the patient's respiratory center. Unlike classic triggering (where neural effort precedes machine delivery), in reverse triggering the mechanical inflation occurs first, entraining a delayed diaphragmatic contraction via the Hering-Breuer lung inflation reflex or brainstem pattern generator entrainment.
- Underlying Mechanisms:
- Occurs predominantly in deeply sedated, heavily tranquilized, or early ARDS patients on continuous mandatory modes (VC-CMV or PC-CMV).
- The mechanical stretch of pulmonary mechanoreceptors during early insufflation sends afferent vagal signals to the pontomedullary respiratory groups, inducing phase-locked neuromuscular discharges (1:1, 1:2, or 1:3 entrainment ratios).
- Consequences:
- If the entrained diaphragmatic contraction occurs late in mechanical inspiration and persists into the cycling phase, it triggers a second mechanical breath, producing reverse-triggered double triggering with breath stacking.
- Even without a second breath, active diaphragmatic contraction during mid-to-late inspiration increases transpulmonary pressure ($P_L$) and causes pendelluft (gas shifting from non-dependent to dependent lung zones), aggravating regional lung injury.
- Waveform Recognition:
- The initial breath starts with a smooth, machine-triggered profile (no pre-trigger negative $P_{aw}$ dip).
- Mid-way through or at the end of the mechanical breath, a distinct downward distortion appears in the $P_{aw}$ scalar (in VC-CMV) or an upward flow surge (in PC-CMV), accompanied by an abrupt negative deflection on $P_{es}$ or sharp rise on $Edi$.
2. Flow (Targeting / Delivery) Asynchronies
Flow asynchrony occurs when the rate, profile, or volume of gas delivered during mechanical inspiration fails to meet the instantaneous flow demands dictated by the patient's metabolic state and neural drive.
       FLOW STARVATION (VC-CMV)                    EXCESSIVE FLOW (PC-CMV)
Pressure (cmH2O)                            Pressure (cmH2O)
  ^         /|                                ^    +---/\---+ (Overshoot)
  |        / |                                |    |  /  \  |
  |  +----+  | (Normal)                       |    | /    \ |
  |  |    |  |                                |    |/      \|
  |  | \__/  | (Dished-out / Scalloped)       |    +--------+
  +--+-------+------------------> Time        +----+--------+------------------> Time
A. Flow Starvation (Inadequate Inspiratory Flow)
- Definition & Pathophysiology: The ventilator delivers gas at a fixed, insufficient flow rate or profile relative to the patient's high inspiratory demand ($V'_{mus} > V'_{vent}$).
- Underlying Mechanisms:
- Exclusively seen in Volume-Controlled Ventilation (VC-CMV) with fixed rectangular (constant) or low ramp flow settings (e.g., set flow of $40\text{ to }50\text{ L/min}$ in a tachypneic, distressed patient demanding $>80\text{ L/min}$).
- Because flow is strictly clamped by the ventilator's inspiratory valve, the patient's vigorous muscular effort ($P_{mus}$) decompresses the circuit, attempting to pull gas faster than the ventilator delivers.
- Pathophysiological Consequences: Markedly increases patient work of breathing (WOB), induces diaphragmatic exhaustion, dyspnea, sympathetic surge, and patient agitation.
- Waveform Recognition:
- Airway Pressure ($P_{aw}$) Scalar: The normal linear ascending pressure slope in VC-CMV becomes visibly scalloped, dished-out, or convex downward. In extreme cases, $P_{aw}$ plummets below the baseline PEEP level during active mechanical inspiration.
- Esophageal Pressure ($P_{es}$): Deep, sustained negative deflection throughout the entire delivery phase.
B. Excessive Flow / Pressure Overshoot
- Definition & Pathophysiology: The initial flow delivery is excessively rapid, delivering gas faster than the respiratory system can distribute it into peripheral airways.
- Underlying Mechanisms:
- Seen in Pressure-Controlled Ventilation (PC-CMV) and Pressure Support (PSV) with an ultra-short pressure rise time (inspiratory rise time / slope set to $0\text{ ms}$ or $100\%$).
- High initial peak flow strikes high airway resistance or stiff proximal airways, generating an early transient pressure spike exceeding the target inspiratory pressure before the valve throttles back.
- Waveform Recognition:
- Airway Pressure ($P_{aw}$) Scalar: A sharp, transient pressure spike ("pressure overshoot" or "spike and dome" profile) at the leading edge of the square pressure waveform, exceeding the set pressure target by $\ge 2\text{ to }3\text{ cmH}_2\text{O}$.
- Patient Effect: Early high peak flow can trigger premature vagal termination of breath or patient coughing.
3. Cycling (Off-Switching) Asynchronies
Cycling defines the criterion used by the ventilator to terminate inspiratory flow and open the exhalation valve. Cycling asynchrony occurs when the ventilator's mechanical inspiratory duration ($T_{i,vent}$) does not match the patient's neural inspiratory duration ($T_{i,neural}$).
                             CYCLING ASYNCHRONIES
                                      │
           ┌──────────────────────────┴──────────────────────────┐
           ▼                                                     ▼
   PREMATURE CYCLING                                     DELAYED CYCLING
   (Ti,vent < Ti,neural)                                 (Ti,vent > Ti,neural)
   - Ventilator cuts off early                           - Ventilator continues pressurizing
   - Ongoing Pmus triggers second breath                 - Patient actively exhales against closed valve
   - Leads to Double Triggering                          - Expiratory pressure spike, high work
A. Premature (Early) Cycling
- Definition & Pathophysiology: The ventilator terminates inspiration prematurely while the patient's inspiratory muscles are still actively contracting ($T_{i,vent} < T_{i,neural}$).
- Underlying Mechanisms:
- In Pressure Support Ventilation (PSV): The flow-cycling percentage (expiratory trigger sensitivity, $E_{sens}$) is set too high (e.g., $40\%\text{ to }50\%$ of peak flow) in a patient with high resistance or prolonged neural time.
- In Time-Cycled Modes (VC-CMV, PC-CMV): Mechanical $T_i$ is set arbitrarily short (e.g., $0.6\text{ seconds}$ in a patient with a neural $T_i$ of $1.0\text{ second}$).
- Consequences:
- Because $P_{mus}$ remains negative after the exhalation valve opens, the continued diaphragmatic descent pulls circuit pressure downward or inverts expiratory flow, frequently tripping the trigger threshold and precipitating Double Triggering.
- Waveform Recognition:
- An immediate, sharp downward spike in $P_{aw}$ at the onset of exhalation, accompanied by an abrupt cessation of inspiratory flow and truncated tidal volume.
B. Delayed (Prolonged / Late) Cycling
- Definition & Pathophysiology: The ventilator continues inspiratory gas delivery and maintains high airway pressure after the patient's neural inspiration has ended and active neural expiration has commenced ($T_{i,vent} > T_{i,neural}$).
- Underlying Mechanisms:
- In PSV in Obstructive Disease (COPD / Asthma): Severe airway resistance and high compliance yield long time constants ($\tau = R_{aw} \times C_{rs}$). Inspiratory flow decelerates very slowly. If the flow-cycle threshold is low (e.g., default $25\%$ of peak flow), it takes an excessively long time for flow to decay to that threshold, prolonging $T_{i,vent}$ well past neural inspiration.
- In Circuit Leaks in PSV: If an air leak (e.g., $20\text{ L/min}$) exceeds the cycling flow threshold, the circuit flow never falls below the threshold, causing the ventilator to hang at peak pressure until the absolute secondary safety time-cycling backup (usually $2.5\text{ to }3.0\text{ s}$) terminates the breath.
- In Mandatory Modes: Setting a fixed mechanical $T_i$ excessively long ($T_i > 1.2\text{ to }1.5\text{ s}$).
- Consequences:
- Expiratory Muscle Braking / Active Expiration: The patient activates rectus abdominis and internal intercostal muscles to force exhalation against the pressurized, closed inspiratory valve, markedly increasing dynamic hyperinflation, cardiac afterload, and patient distress.
- Waveform Recognition:
- Airway Pressure ($P_{aw}$) Scalar: A distinct, sharp upward pressure hump ("dog ear" or late-inspiratory pressure spike) exceeding the plateau/support pressure target at the tail end of the inspiratory pressure waveform.
- Flow-Time Scalar: Inspiratory flow decelerates to an abnormally low plateau or remains flat before abruptly plunging straight into deep negative expiratory flow.
The Asynchrony Index (AI)
Mathematical Definition & Calculation
The Asynchrony Index (AI) quantifies the overall burden of patient-ventilator dyssynchrony over a defined monitoring window (ideally $\ge 30\text{ minutes}$ to continuous multi-hour polysomnographic/waveform analysis).
$$\text{Asynchrony Index (AI)} = \frac{\text{Total Asynchronous Events}}{\text{Total Respiratory Efforts}} \times 100\%$$Where:
$$\text{Total Respiratory Efforts} = \text{Total Ventilator Cycles (Delivered Breaths)} + \text{Ineffective Efforts (Missed Triggers)} - \text{Auto-Triggered Cycles}$$Asynchronous events included in the numerator comprise:
- Ineffective triggering efforts.
- Auto-triggered breaths.
- Double-triggered breath events.
- Reverse-triggered cycles (with or without breath stacking).
- Severe premature or delayed cycling events ($|T_{i,vent} - T_{i,neural}| > 0.2\text{ s}$).
                     ASYNCHRONY INDEX FORMULA BREAKDOWN

      Numerator:   [ Ineffective Triggers + Auto-Triggers + Double Triggers + Reverse Triggers + Cycling Errors ]
 AI = ──────────────────────────────────────────────────────────────────────────────────────────────────────────── × 100%
      Denominator: [ Ventilator-Delivered Cycles + Ineffective Triggers - Auto-Triggered Cycles ]
Evidence-Based Clinical Thresholds & Prognostic Significance
Seminal prospective clinical trials (Chao et al., 1997; Epstein et al., 2000; Thille et al., 2006; Blanch et al., 2015) established the definitive prognostic threshold for the Asynchrony Index:
$$\mathbf{AI \ge 10\% \implies \text{Severe, Clinically Significant Asynchrony}}$$| Parameter / Outcome Metric | Low Asynchrony ($AI < 10\%$) | High Asynchrony ($AI \ge 10\%$) | Relative Risk / Odds Ratio ($95\%$ CI) |
|---|---|---|---|
| Prevalence in Mechanically Ventilated ICU Cohorts | $70\% - 75\%$ | $25\% - 30\%$ | — |
| Duration of Mechanical Ventilation (Median Days) | $6\text{ days}$ | $16\text{ days}$ | $p < 0.001$ |
| ICU Length of Stay (Median Days) | $9\text{ days}$ | $21\text{ days}$ | $p < 0.001$ |
| Tracheostomy Rate | $14\%$ | $43\%$ | $\text{OR } 4.2\text{ }(1.8 - 9.8)$ |
| Weaning Failure / Extubation Failure | $16\%$ | $52\%$ | $\text{OR } 3.8\text{ }(1.6 - 8.9)$ |
| ICU Mortality | $18\%$ | $36\%$ | $\text{RR } 2.0\text{ }(1.2 - 3.4)$ |
| Hospital Mortality (Blanch et al., 2015) | $23\%$ | $44\%$ | $p = 0.012$ |
Mechanisms linking elevated AI to adverse outcomes:
- Diaphragmatic Myotrauma: Cyclic eccentric contractions (contraction during lengthening, as in premature cycling and reverse triggering) induce severe sarcomeric disruption, microvascular inflammation, and rapid atrophy.
- Volutrauma from Breath Stacking: Double triggering delivers tidal volumes $>12\text{ to }16\text{ mL/kg}$ PBW, causing localized alveolar stress failure.
- Sedation Escalation: Bedside clinicians often misinterpret patient asynchrony as agitation or pain, administering escalating boluses of sedatives and paralytics, which prolongs delirium, critical illness weakness, and coma.
Comprehensive Differential Diagnostic Taxonomy
The following comparative taxonomy outlines the mechanical features, physiological causes, waveform patterns, and corrective interventions across all major forms of PVA:
| Asynchrony Type | Mechanical Phase | Primary Pathophysiology | Key Scalar Signatures | First-Line Corrective Interventions |
|---|---|---|---|---|
| Ineffective Triggering | Triggering | Elevated $PEEP_i$, severe muscle weakness, or over-assistance ($PaCO_2 < \text{apneic threshold}$). | Transient upward blip in expiratory flow; small negative $P_{aw}$ dip without delivery. | 1. Match extrinsic PEEP to $80\% \text{ of } PEEP_i$. 2. Reduce Pressure Support / $V_t$ to restore neural drive. 3. Increase trigger sensitivity. |
| Auto-Triggering | Triggering | Circuit air leak, cardiogenic flow pulses, or condensed water in circuit. | Machine cycles at fixed high RR with no prior negative $P_{aw}$ dip; visible small oscillations on flow scalar. | 1. Drain tubing water traps. 2. Seal cuff / fix mask leak. 3. Decrease trigger sensitivity or switch from flow to pressure trigger. |
| Double Triggering | Triggering / Cycling | High neural drive with $T_{i,neural} > T_{i,vent}$; low set $V_t$ in stiff lungs. | Two back-to-back inspiratory cycles with near-zero $T_e$; step-up doubled volume scalar. | 1. Increase $T_i$ or match flow demand. 2. Moderate sedation / correct acidosis. 3. Switch to proportional mode (PAV+, NAVA). |
| Reverse Triggering | Triggering | Entrainment of central pattern generator by mandatory machine insufflation (Hering-Breuer reflex). | Mechanical breath starts smoothly; late negative dip in $P_{aw}$ or late inspiratory flow surge; accompanied by delayed $Edi$/$P_{es}$ drop. | 1. Lighten deep sedation to restore spontaneous drive. 2. Alter mandatory respiratory rate (increase or decrease) to break entrainment ratio. 3. Transition to spontaneous/assisted mode. |
| Flow Starvation | Flow Delivery | Fixed insufficient flow rate in VC-CMV ($V'_{vent} < V'_{mus}$). | Dished-out, concave downward "scooped" $P_{aw}$ scalar; $P_{aw}$ drops below PEEP during inspiration. | 1. Increase peak flow rate ($>70\text{ to }80\text{ L/min}$). 2. Change flow profile from square to decelerating ramp. 3. Switch to PC-CMV or PSV. |
| Excessive Flow | Flow Delivery | Ultra-fast inspiratory rise time hitting high resistance or non-compliant airways. | Initial pressure spike exceeding target ("pressure overshoot" or "spike and dome" on $P_{aw}$). | 1. Increase inspiratory rise time (lengthen slope). 2. Decrease initial flow acceleration. |
| Premature Cycling | Cycling | Flow-cycle threshold ($E_{sens}$) too high; mechanical $T_i$ set shorter than patient $T_{i,neural}$. | Sharp downward $P_{aw}$ drop at start of exhalation; truncated flow; secondary double trigger. | 1. Decrease $E_{sens}$ (e.g., from $50\%$ down to $15\%-25\%$). 2. Increase set $T_i$ on mandatory modes. |
| Delayed Cycling | Cycling | Long time constant ($\tau$) in COPD causing slow flow decay; air leaks in PSV; $T_{i,vent} > T_{i,neural}$. | Late-inspiratory upward pressure spike ("dog ear" on $P_{aw}$); prolonged flat flow before steep expiratory drop. | 1. Increase $E_{sens}$ (e.g., from $25\%$ up to $40\%-50\%$). 2. Shorten set $T_i$ or set maximum inspiratory time limit ($T_{i,max}$). 3. Fix circuit air leaks. |
Stepwise Bedside Algorithm for Detecting and Resolving Asynchrony
To systematically identify and eliminate patient-ventilator asynchronies at the bedside, clinicians should apply the following six-step diagnostic and therapeutic sequence:
                          BEDSIDE ASYNCHRONY RESOLUTION ALGORITHM
                                             │
             ┌───────────────────────────────▼───────────────────────────────┐
             │ STEP 1: CLINICAL & WAVEFORM RECOGNITION                       │
             │ - Assess patient comfort, accessory muscle use, abdominal paradox│
             │ - Freeze scalar screens: inspect Paw(t), Flow(t), Vol(t)      │
             └───────────────────────────────┬───────────────────────────────┘
                                             │
             ┌───────────────────────────────▼───────────────────────────────┐
             │ STEP 2: CLASSIFY THE ASYNCHRONY DOMAIN                        │
             │ - Triggering Phase? (Ineffective, Auto, Double, Reverse)      │
             │ - Flow Delivery Phase? (Starvation vs Overshoot)              │
             │ - Cycling Off Phase? (Premature vs Delayed)                   │
             └───────────────────────────────┬───────────────────────────────┘
                                             │
             ┌───────────────────────────────▼───────────────────────────────┐
             │ STEP 3: ASSESS VENTILATORY MECHANICS & DRIVING FORCES         │
             │ - Perform expiratory hold: measure intrinsic PEEP (PEEPi)     │
             │ - Check Raw and Crs; calculate time constant (Tau = Raw x Crs)│
             │ - Evaluate sedation level (RASS score) and blood gas/drive    │
             └───────────────────────────────┬───────────────────────────────┘
                                             │
             ┌───────────────────────────────▼───────────────────────────────┐
             │ STEP 4: IMPLEMENT TARGETED VENTILATOR ADJUSTMENTS             │
             │ - Trigger: set PEEPe = 80% PEEPi; titrate delta-flow / delta-P│
             │ - Flow: switch to decelerating / raise peak flow > 70 L/min   │
             │ - Cycling: adjust Esens (15-25% ARDS, 40-50% COPD); adjust Ti │
             └───────────────────────────────┬───────────────────────────────┘
                                             │
             ┌───────────────────────────────▼───────────────────────────────┐
             │ STEP 5: RE-EVALUATE SEDATION & CLINICAL METABOLIC DRIVERS     │
             │ - If deep sedation induces reverse triggering -> Lighten RASS │
             │ - If severe metabolic acidosis / agitation -> Treat etiology  │
             │ - Avoid reflex paralytic/sedative escalations for machine flaws│
             └───────────────────────────────┬───────────────────────────────┘
                                             │
             ┌───────────────────────────────▼───────────────────────────────┐
             │ STEP 6: ADVANCED SENSING & PROPORTIONAL MODES (REFRACTORY)    │
             │ - Place Esophageal Manometry (Pes) or Diaphragm EMG (Edi)     │
             │ - Transition to NAVA or PAV+ to restore neuro-ventilatory link│
             └───────────────────────────────────────────────────────────────┘
Detailed Operational Steps
Step 1: Clinical & Waveform Inspection
- Observe patient posture, sternocleidomastoid retractions, and thoracoabdominal synchronization.
- Freeze the ventilator screen ($10\text{-second}$ sweep). Systematically review from left to right: baseline stability, triggering deflection, inspiratory flow profile, pressure contour, cycling transition point, and expiratory decay.
Step 2: Classify the Asynchrony Domain
- Is there an effort without a breath? $\implies$ Ineffective Triggering.
- Is there a breath without an effort? $\implies$ Auto-Triggering.
- Are there two breaths back-to-back? $\implies$ Double Triggering (Patient-initiated) vs Reverse Triggering (Machine-initiated).
- Is the pressure scalar scalloped during inspiration? $\implies$ Flow Starvation.
- Is there an end-inspiratory pressure spike or delayed exhalation? $\implies$ Delayed Cycling.
- Is there an end-inspiratory pressure drop or immediate double breath? $\implies$ Premature Cycling.
Step 3: Measure Respiratory Mechanics
- Perform an end-expiratory hold maneuver to quantify $PEEP_i$.
- Perform an end-inspiratory hold maneuver in passive patients to calculate static compliance ($C_{rs} = \frac{V_t}{P_{plat} - PEEP_{tot}}$) and airway resistance ($R_{aw} = \frac{P_{peak} - P_{plat}}{\text{Flow}}$).
- Calculate the expiratory time constant ($\tau = R_{aw} \times C_{rs}$). High $\tau$ ($>0.8\text{ s}$) indicates obstructive disease prone to delayed cycling and auto-PEEP; low $\tau$ ($<0.4\text{ s}$) indicates restrictive disease prone to premature cycling.
Step 4: Execute Targeted Ventilator Titrations
- For Ineffective Triggering from Auto-PEEP: Apply extrinsic PEEP equal to $70\% - 80\%$ of measured static $PEEP_i$. This narrows the pressure differential the patient must overcome to trigger the valve without increasing total alveolar pressure or hyperinflation (the "waterfall effect").
- For Flow Starvation: In VC-CMV, increase peak inspiratory flow from $40-60\text{ L/min}$ to $70-90\text{ L/min}$ or switch to a decelerating ramp. If demand remains variable, convert to Pressure-Controlled Ventilation (PC-CMV) or Pressure Support Ventilation (PSV), where flow is variable and patient-driven.
- For Premature Cycling / Double Triggering: In PSV, lower the expiratory cycle sensitivity ($E_{sens}$) from $30-40\%$ down to $10-20\%$, prolonging $T_i$. In mandatory modes, lengthen set $T_i$.
- For Delayed Cycling in Obstructive Disease: Increase $E_{sens}$ up to $40\%-50\%$ of peak flow, forcing the ventilator to cycle off earlier at higher residual flow rates, allowing adequate time for exhalation ($T_e$).
Step 5: Adjust Sedation and Treat Systemic Reversible Drivers
- For Reverse Triggering: Reverse triggering is exacerbated by deep sedative states (e.g., continuous infusions of propofol or midazolam with RASS $-4$ to $-5$). Systematically lighten sedation to a RASS target of $-1$ to $0$. If neuromuscular blockade is indicated for severe refractory ARDS, complete paralysis will eliminate reverse-triggered muscular contractions; however, sedation weaning is the preferred definitive therapy.
- For Central Over-Drive: Treat high physiological respiratory drives (fever, pain, severe metabolic acidosis, acute hypoxemia) directly rather than merely adjusting the ventilator.
Step 6: Deploy Advanced Physiological Monitoring and Proportional Modes
- In refractory, complex asynchronies (where pneumatically triggered modes continue to fail), place an Esophageal Balloon Catheter ($P_{es}$) or a Neurally Adjusted Ventilatory Assist ($Edi$) Catheter.
- Transition the patient to Proportional Assist Ventilation (PAV+) or Neurally Adjusted Ventilatory Assist (NAVA):
- NAVA utilizes the electrical activity of the diaphragm ($Edi$) to trigger, target, and cycle the breath, bypassing pneumatic delays, leaks, and auto-PEEP completely, reducing the Asynchrony Index below the critical $10\%$ threshold in $>90\%$ of difficult-to-synchronize patients.
- PAV+ continuously estimates instantaneous $R_{aw}$ and $C_{rs}$ via rapid micro-occlusions, delivering proportional pressure assist that tracks patient effort breath-by-breath.
Key Takeaways & Summary
- High Prevalence & Clinical Impact: Patient-ventilator asynchrony occurs in $>25\%$ of mechanically ventilated patients; an Asynchrony Index ($AI$) $\ge 10\%$ is an independent predictor of prolonged mechanical ventilation, weaning failure, tracheostomy, and elevated ICU and hospital mortality.
- Three Functional Domains:
- Trigger Asynchronies: Ineffective triggering (most common, driven by $PEEP_i$ and over-assistance), auto-triggering (leaks, cardiogenic oscillations), double triggering (high neural drive outlasting short $T_i$), and reverse triggering (machine-entrained reflex diaphragmatic contraction).
- Flow Asynchronies: Flow starvation (dished-out $P_{aw}$ in VC-CMV) and excessive flow/overshoot (pressure spike in PC-CMV with fast rise times).
- Cycling Asynchronies: Premature cycling ($T_{i,vent} < T_{i,neural}$, precipitating double triggering) and delayed cycling ($T_{i,vent} > T_{i,neural}$, causing active expiratory muscle braking).
- Double Triggering vs. Reverse Triggering Distinction: Double triggering is patient-initiated (effort precedes first breath) and reflects high neural drive; reverse triggering is machine-initiated (machine breath entrains a delayed diaphragmatic twitch) and occurs in deeply sedated patients. Both can cause severe breath-stacking volutrauma.
- Physiological Correction Hierarchy: Match extrinsic PEEP to $80\%$ of $PEEP_i$ for wasted efforts, adjust $E_{sens}$ based on time constants ($15-20\%$ for restrictive lungs, $45-50\%$ for obstructive lungs), lighten sedation to abolish reverse triggering, and consider proportional neural modes (NAVA / PAV+) for refractory asynchrony.