Ventilator-Induced Lung Injury (VILI) represents an iatrogenic form of acute parenchymal disruption and systemic biological injury caused or propagated by the unphysiological mechanical stresses and energy loads imposed during positive-pressure invasive mechanical ventilation. Originally conceptualized in terms of macro-barotrauma (e.g., tension pneumothorax), the pathophysiological paradigm of VILI has evolved through micro-mechanical models (volutrauma, atelectrauma, and biotrauma) to the contemporary thermodynamic framework of ergotrauma and mechanical power ($MP$).
In acute respiratory distress syndrome (ARDS), the lung parenchyma is profoundly heterogeneous. The "baby lung" model described by Luciano Gattinoni demonstrates that the volume of aerated, functionally compliant lung tissue available for tidal ventilation is drastically diminished—often reduced to dimensions comparable to that of a 5-to-6-year-old child ($300\text{--}500\text{ mL}$). Consequently, even standard physiological tidal volumes delivered into this markedly contracted functional compartment generate excessive physical deformation, dynamic shear stresses, and high energy dissipation, escalating local cellular trauma into systemic multi-organ dysfunction syndrome (MODS).
The Four Classic Mechanisms of VILI
The classic mechanical forces and biological cascades responsible for ventilator-induced parenchymal injury are categorized into four interconnected mechanisms:
+----------------------------------------------------------------------------------------------------+
|                                    MECHANICAL DRIVERS OF VILI                                      |
+------------------------------------+---------------------------------------------------------------+
| Volutrauma                         | Barotrauma                                                    |
| Excessive end-inspiratory strain   | High transalveolar pressure gradient (Palv - Ppl)             |
| Alveolar overdistension & rupture  | Alveolar rupture into bronchovascular sheath (Macklin effect) |
| Basement membrane disruption       | Pneumothorax, PIE, Pneumomediastinum, Subcutaneous emphysema   |
+------------------------------------+---------------------------------------------------------------+
| Atelectrauma                       | Biotrauma                                                     |
| Cyclic recruitment/derecruitment   | Mechanotransduction -> Cytokine cascade (IL-6, IL-8, TNF-a)   |
| Interfacial fluid & shear stress   | Alveolar-capillary barrier breakdown -> Systemic spillover    |
| Stress concentration at interfaces | Systemic inflammatory response -> Distant organ injury (MODS) |
+------------------------------------+---------------------------------------------------------------+
1. Volutrauma (Excessive End-Inspiratory Strain and Alveolar Overdistension)
Volutrauma designates the structural damage inflicted by excessive end-inspiratory lung expansion and alveolar overdistension. Early seminal investigations (Dreyfuss et al., 1988) decoupled volume from airway pressure by demonstrating that high tidal volume ventilation with low airway pressures (achieved with negative-pressure body iron lungs) produced severe alveolar-capillary permeability pulmonary edema, whereas high airway pressures without excessive lung expansion (iron lung with thoracoabdominal strapping) prevented parenchymal injury. Thus, tissue strain (deformation relative to resting volume), rather than airway pressure per se, is the primary mechanical trigger of overdistension injury.
At the microscopic level, excessive volume stretches alveolar epithelial cells (Type I and Type II pneumocytes) and capillary endothelial cells beyond their physiological yield limits. This hyper-strain produces:
- Mechanical micro-fractures in the alveolar epithelial and capillary endothelial plasma membranes.
- Uncoupling of intercellular tight junctions (zonula occludens and claudins).
- Denudation of the alveolar basement membrane, enabling the massive exuded extravasation of proteinaceous fluid, erythrocytes, and macromolecules into the airspaces, obliterating surfactant function.
2. Barotrauma (Transalveolar Pressure Gradients and Air Leaks)
Barotrauma denotes the macroscopic air-leak phenomena secondary to excessive transalveolar pressure ($\Delta P_{alv} = P_{alv} - P_{pl}$). When the pressure differential across the alveolar wall exceeds the structural tensile strength of the lung skeleton, alveolar disruption occurs at the junctions between alveoli and the perivascular adventitial sheaths.
Air dissects centripetally along the bronchovascular sheaths toward the pulmonary hilum and mediastinum—a physiological sequence termed the Macklin effect. The escaped gas manifests as:
- Pulmonary Interstitial Emphysema (PIE): Micro-bubbles tracking along peribronchovascular connective tissue.
- Pneumomediastinum: Accumulation of gas in the mediastinal compartment.
- Subcutaneous Emphysema: Dissection of mediastinal air superiorly into the fascial planes of the neck, face, and chest wall.
- Pneumothorax / Tension Pneumothorax: Rupture of the mediastinal pleura or visceral subpleural blebs into the pleural cavity, leading to lung collapse, acute elevation of intrathoracic pressure, compression of the great veins, compromised venous return, and immediate cardiovascular collapse.
- Systemic Air Embolism: Intravasation of alveolar gas into damaged pulmonary venules under severe pressure gradients.
3. Atelectrauma (Cyclic Recruitment, Derecruitment, and Shear Stress)
Atelectrauma results from the cyclic opening and collapse (recruitment and derecruitment) of unstable, fluid-filled, or surfactant-deficient alveoli and terminal bronchioles with each positive-pressure respiratory cycle. In inhomogeneous ARDS lungs, non-aerated dependent units border normally aerated or overdistended lung zones.
During tidal ventilation without adequate positive end-expiratory pressure (PEEP):
- Interfacial Fluid Dynamics: The fluid menisci present within narrow, collapsed terminal airways generate high surface tension forces. Reopening these collapsed units requires critical opening pressures; as the gas bubble advances through the liquid-filled lumen, it exerts severe interfacial shear stress on the lining epithelial cells, stripping them from their basolateral anchorage.
- Stress Multipliers at Interface Boundaries: As demonstrated by Mead and colleagues, at the physical interface between an atelectatic, non-compliant lung unit and an adjacent inflated, compliant alveolus, the applied transpulmonary pressure is amplified locally by a factor of up to 4-to-5-fold. A global transpulmonary pressure of $20\text{ cmH}_2\text{O}$ can generate local mechanical stresses approaching $80\text{--}100\text{ cmH}_2\text{O}$ at the margin of the collapsed unit, tearing adjacent alveolar septa.
4. Biotrauma (Mechanotransduction and Systemic Inflammatory Propagation)
Biotrauma is the biological and biochemical amplification of mechanical tissue injury into a destructive inflammatory cascade. Alveolar epithelial and capillary endothelial cells function as mechanosensors. Mechanical deformation (strain) and shear stress activate stretch-activated ion channels (e.g., Piezo1, TRPV4), integrin-cytoskeleton complexes, and cell membrane stress receptors.
This mechanotransductive signaling stimulates intracellular pathways (NF-$\kappa$B, AP-1, MAP kinase cascades), inducing rapid transcription and synthesis of pro-inflammatory cytokines, chemokines, and danger-associated molecular patterns (DAMPs):
- Cytokines and Chemokines: Marked upregulation of Interleukin-6 ($\text{IL-6}$), Interleukin-8 ($\text{IL-8}$ / $\text{CXCL8}$), Interleukin-1$\beta$ ($\text{IL-1}\beta$), and Tumor Necrosis Factor-$\alpha$ ($\text{TNF-}\alpha$).
- DAMP Release: Extracellular expulsion of high-mobility group box 1 (HMGB1), heat shock proteins (Hsp70), ATP, and mitochondrial DNA.
- Neutrophil Recruitment and Activation: Release of matrix metalloproteinases (MMP-8, MMP-9) and neutrophil elastase, which enzymatically degrade the extracellular matrix (collagen and elastin network).
- Systemic Spillover and MODS: The breakdown of the alveolar-capillary endothelial barrier allows high concentrations of pulmonary cytokines, endotoxins, and DAMPs to translocate across the compromised microvasculature into the systemic circulation. This systemic spillover drives secondary end-organ dysfunction—inducing acute tubular necrosis in the kidneys, myocardial depression, hepatic ischemia, and gut hypoperfusion, ultimately culminating in Multi-Organ Dysfunction Syndrome (MODS).
Transalveolar Strain and the Physical Limits of Lung Deformation
To understand why tidal volumes must be calibrated to functional lung size rather than total body weight, the physical mechanics of tissue deformation must be defined mathematically:
+----------------------------------------------------------------------------------------------------+
|                                    LUNG STRESS AND STRAIN METRICS                                  |
+------------------------------------+---------------------------------------------------------------+
| Volumetric Strain ($\epsilon$)     | Ratio of volume change to resting end-expiratory volume:       |
|                                    | $\epsilon = \frac{\Delta V}{V_0} = \frac{V_T}{\text{FRC}}$    |
+------------------------------------+---------------------------------------------------------------+
| Global Transpulmonary Stress       | Tension generated across the alveolar wall:                   |
| ($\sigma_L = P_L$)                 | $P_L = P_{alv} - P_{pl} = \epsilon \cdot E_{spec}$            |
+------------------------------------+---------------------------------------------------------------+
| Specific Lung Elastance            | Intrinsic stiffness of healthy lung tissue:                   |
| ($E_{spec}$)                       | $E_{spec} \approx 12\text{--}13.5\text{ cmH}_2\text{O}$       |
+------------------------------------+---------------------------------------------------------------+
1. Volumetric Strain ($\epsilon$)
Lung strain represents the ratio of the cyclic volume change ($\Delta V$, the tidal volume $V_T$) to the resting end-expiratory lung volume (the functional residual capacity, $\text{FRC}$):
$$\epsilon = \frac{V_T}{\text{FRC}}$$When static end-expiratory strain from positive end-expiratory pressure ($\text{PEEP}$) is incorporated:
$$\epsilon_{total} = \frac{V_T + \Delta V_{\text{PEEP}}}{\text{FRC}_0}$$where $\text{FRC}_0$ is the relaxation volume at zero end-expiratory pressure (ZEEP).
2. Transpulmonary Stress ($\sigma_L$) and Specific Lung Elastance ($E_{spec}$)
Stress ($\sigma_L$) is the internal restoring force per unit area generated within the lung skeleton in response to strain, equivalent to transpulmonary pressure ($P_L = P_{alv} - P_{pl}$). Stress and strain are linked by the lung's intrinsic mechanical property, specific lung elastance ($E_{spec}$):
$$P_L = \epsilon \cdot E_{spec} = \left(\frac{V_T}{\text{FRC}}\right) \cdot E_{spec}$$In both normal and ARDS lungs, $E_{spec}$ remains remarkably constant at approximately $12\text{--}13.5\text{ cmH}_2\text{O}$. This fundamental physiological constancy demonstrates that the structural material properties of aerated lung tissue in ARDS are not inherently altered; rather, the absolute quantity of aerated lung tissue ($\text{FRC}$) is drastically contracted.
3. Critical Strain Thresholds
Extensive physiological and experimental animal models (Gattinoni, Caironi, Protti et al.) demonstrate that lung tissue behaves as a linear elastic material up to a critical threshold:
- Physiological Strain: Resting tidal breathing in healthy humans corresponds to $\epsilon \approx 0.1\text{--}0.2$.
- Safe Limit: $\epsilon < 1.0\text{--}1.2$.
- Critical Failure Threshold: When volumetric strain exceeds $\epsilon > 1.5\text{--}2.0$ (corresponding to dynamic lung inflation beyond total lung capacity, where transpulmonary pressure exceeds $20\text{--}25\text{ cmH}_2\text{O}$), progressive alveolar rupture, capillary hemorrhage, severe endothelial detachment, and fatal permeability edema develop rapidly, even in previously healthy lungs.
In severe ARDS where $\text{FRC}$ is reduced from normal ($2500\text{ mL}$) down to $400\text{ mL}$, delivering a standard $500\text{ mL}$ tidal volume imposes a strain of $\epsilon = 500 / 400 = 1.25$ (reaching hazardous deformation), whereas the same volume in a normal lung yields a benign strain of $\epsilon = 500 / 2500 = 0.20$.
Driving Pressure ($\Delta P$): The Master Bedside Normalizer
In 2015, Marcelo Amato and colleagues published a landmark multi-level mediation analysis in The New England Journal of Medicine that transformed bedside ventilator management. Analyzing 3,562 ARDS patients across 9 randomized trials, the investigators evaluated which respiratory variable had the strongest independent epidemiological and causal link to hospital survival.
+----------------------------------------------------------------------------------------------------+
|                                    DRIVING PRESSURE FORMULATION                                    |
|                                                                                                    |
|          $$\Delta P = P_{plat} - \text{PEEP} = \frac{V_T}{C_{rs}} = \frac{V_T}{\text{FRC}} \cdot E_{spec}$$           |
+----------------------------------------------------------------------------------------------------+
1. Physiological Basis
Driving pressure ($\Delta P$) is defined under static zero-flow conditions as the difference between end-inspiratory plateau pressure ($P_{plat}$) and total end-expiratory pressure ($\text{PEEP}$):
$$\Delta P = P_{plat} - \text{PEEP}$$By dividing both numerator and denominator of compliance:
$$C_{rs} = \frac{V_T}{\Delta P} \implies \Delta P = \frac{V_T}{C_{rs}}$$Because respiratory system compliance ($C_{rs}$) in ARDS correlates directly with the volume of functionally aerated lung tissue (the "baby lung" $\text{FRC}$), the ratio $\frac{V_T}{C_{rs}}$ serves as an immediate, non-invasive clinical surrogate for volumetric lung strain ($\frac{V_T}{\text{FRC}}$).
2. Clinical Findings and Danger Thresholds
Amato et al. demonstrated that:
- Neither $V_T$ normalized to predicted body weight (PBW) alone nor PEEP alone predicted mortality across heterogeneous cohorts.
- Reductions in $V_T$ or increases in PEEP were beneficial only if they resulted in a concurrent reduction in $\Delta P$.
- If increasing PEEP caused overdistension (decreasing $C_{rs}$ and increasing $\Delta P$), mortality increased. Conversely, if increasing PEEP recruited collapsed lung tissue (increasing $C_{rs}$ and decreasing $\Delta P$), mortality declined.
- Safe Threshold: Driving pressure must be maintained strictly at:
Increases in $\Delta P$ above $15\text{ cmH}_2\text{O}$ are associated with an exponential increase in mortality risk.
Ergotrauma and Mechanical Power ($MP$)
While tidal volume ($V_T$), driving pressure ($\Delta P$), plateau pressure ($P_{plat}$), and PEEP reflect static or quasi-static mechanical variables per breath, they omit the crucial dimension of time, respiratory frequency ($RR$), inspiratory flow ($\dot{V}$), and cumulative energy dissipation.
In 2016, Luciano Gattinoni and colleagues introduced the unified thermodynamic concept of Mechanical Power ($MP$)—quantifying the continuous mechanical energy transferred from the ventilator to the respiratory system per unit of time (expressed in Joules per minute, $\text{J/min}$).
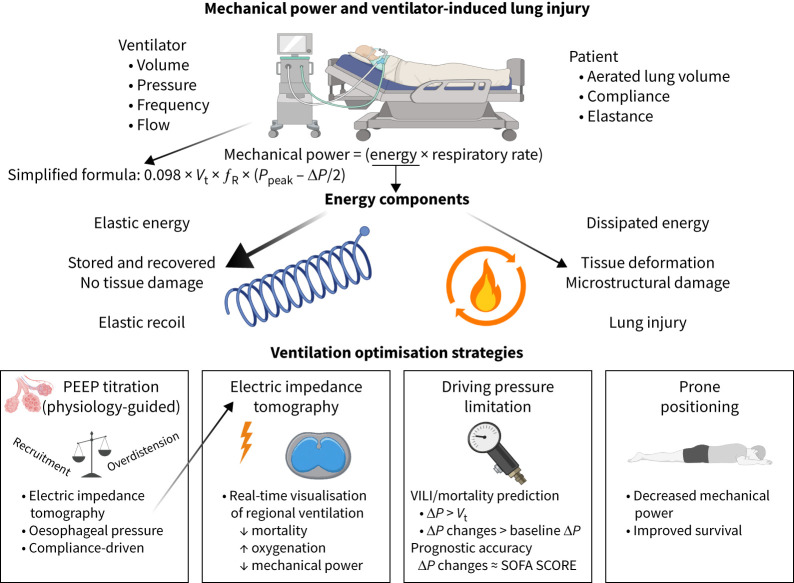 Figure 1: Mechanical power ($MP$) as an integrative physiological framework for ventilator-induced lung injury (VILI) and lung-protective ventilation strategies. Mechanical power unifies tidal volume ($V_T$), airway pressures ($P_{peak}$, $\Delta P$, $\text{PEEP}$), flow rate, and respiratory frequency ($RR$ or $f_R$) into a single energy transfer metric ($\text{J/min}$). Total energy partitions into elastic energy (conserved and recovered during passive expiration without structural injury) and dissipated resistive/viscoelastic energy (driving non-elastic tissue deformation, stress concentration, and microstructural damage). Modern protective interventions (physiologic PEEP titration, driving pressure limitation, prone positioning, and electrical impedance tomography) directly lower or redistribute injurious dissipated energy. Image adapted from Urbankowski et al., European Respiratory Review 2026; DOI:
10.1183/16000617.0283-2025
, distributed under CC BY-NC 4.0.
1. Energy Partitioning: Elastic vs. Dissipated Energy
The energy delivered during each mechanical inflation is represented geometrically by the area under the inspiratory airway pressure-volume ($P\text{--}V$) loop:
Pressure
  ^
  |        /| <- Peak Pressure (Ppeak)
  |       / |
  |      /  | <- Plateau Pressure (Pplat)
  |     /|  |
  |    / |  |    [Resistive / Dissipated Energy Area] (Gas flow & airway resistance)
  |   /  |  |    [Viscoelastic Hysteresis Area] (Tissue friction & plastic deformation)
  |  /   |  |    -----------------------------------------------------------------
  | /    |  |    [Elastic Energy Area] (Stored in chest wall/lung collagen-elastin)
  |/_____|__|____________________________________________________________________> Volume
 PEEP   PEEP+VT
During inspiration, the total work of breathing performed on the respiratory system consists of:
- Resistive Energy ($W_{res}$): Overcomes gas-flow resistance in the endotracheal tube and tracheobronchial tree. Dissipated as thermal energy.
- Viscoelastic / Hysteretic Energy ($W_{visc}$): Overcomes tissue frictional resistance and plastic structural remodeling. This dissipated energy acts directly on parenchymal fibers.
- Elastic Energy ($W_{el}$): Stored in the elastic collagen and elastin matrix of the lung and chest wall during inflation.
- Static Elastic Energy: Maintained by $\text{PEEP} \cdot V_T$.
- Dynamic Elastic Energy: Accumulated by inflating the lung from PEEP to end-inspiration ($\frac{1}{2} E_{rs} \cdot V_T^2$).
During passive exhalation, the elastic potential energy is released to drive expiratory flow. However, in heterogeneous or injured lungs, viscoelastic hysteresis and non-elastic energy dissipation fracture alveolar membranes, propagate shear injury, and trigger inflammatory biotrauma.
2. The Comprehensive Mechanical Power Equation
Derived from the single-compartment Equation of Motion ($P(t) = E_{rs} \cdot V(t) + R_{aw} \cdot \dot{V}(t) + \text{PEEP}$), integrating pressure with respect to volume over time and multiplying by the respiratory rate ($RR$) yields the full physical equation for volume-controlled ventilation with constant inspiratory flow:
$$MP = 0.098 \cdot RR \cdot \left[ V_T^2 \cdot \left( \frac{1}{2} E_{rs} + RR \cdot \frac{1 + I:E}{60 \cdot I:E} \cdot R_{aw} \right) + V_T \cdot \text{PEEP} \right]$$Where:
- $0.098$ converts units from $\text{cmH}_2\text{O} \cdot \text{L}$ to Joules ($\text{J}$).
- $RR$ is respiratory rate ($\text{breaths/min}$).
- $V_T$ is tidal volume ($\text{L}$).
- $E_{rs}$ is respiratory system elastance ($\text{cmH}_2\text{O/L} = 1 / C_{rs}$).
- $R_{aw}$ is airway resistance ($\text{cmH}_2\text{O} / (\text{L/s})$).
- $I:E$ is the inspiratory-to-expiratory ratio.
- $\text{PEEP}$ is positive end-expiratory pressure ($\text{cmH}_2\text{O}$).
3. Simplified Bedside Surrogates
Because calculating the full equation at the bedside is cumbersome, validated simplified algebraic surrogates are utilized in clinical practice.
Gattinoni / Costa Simplified Formula (Volume Control, Constant Flow)
By substituting static plateau pressure ($P_{plat}$) and peak airway pressure ($P_{peak}$), the elastic and resistive components condense into:
$$MP \approx 0.098 \cdot RR \cdot V_T \cdot \left( P_{peak} - \frac{1}{2} \Delta P \right)$$Where:
- $\Delta P = P_{plat} - \text{PEEP}$
- $V_T$ is entered in Liters ($\text{L}$)
- $P_{peak}$ and $\Delta P$ are in $\text{cmH}_2\text{O}$
Pressure-Controlled Ventilation (PCV) Formula
In decelerating flow modes (PCV), where peak pressure approximates plateau pressure ($P_{peak} \approx P_{plat} = \Delta P_{insp} + \text{PEEP}$), the equation simplifies to:
$$MP_{\text{PCV}} \approx 0.098 \cdot RR \cdot V_T \cdot \left( \Delta P_{insp} + \text{PEEP} \right)$$or more precisely (Becher et al.):
$$MP_{\text{PCV}} = 0.098 \cdot RR \cdot V_T \cdot \left( \Delta P + \text{PEEP} - \frac{\Delta P}{1 - e^{-t_i / \tau}} \right)$$4. Exponential Contribution of Ventilator Components
Crucially, the variables within the mechanical power equation do not contribute linearly to tissue injury. As established in experimental animal preparations by Gattinoni, Cressoni, and colleagues:
- Tidal Volume ($V_T$): Contributes to energy quadratically/exponentially ($V_T^2$ or $V_T^{\approx 1.7}$). Doubling $V_T$ quadruples dynamic power.
- Driving Pressure ($\Delta P$): Contributes quadratically ($\Delta P^2$).
- Respiratory Rate ($RR$): Contributes with an exponent of approximately $RR^{1.4}$. Increasing frequency significantly increases power per minute.
- Flow Rate ($\dot{V}$): Contributes to resistive dissipation ($R_{aw} \cdot \dot{V}$).
- PEEP: Contributes linearly to static baseline energy ($V_T \cdot \text{PEEP}$); however, by preventing cyclic recruitment/derecruitment and stabilizing functional compliance ($C_{rs}$), appropriate PEEP can paradoxically decrease total driving pressure and net dissipated power.
+----------------------------------------------------------------------------------------------------+
|                             RELATIVE EXPONENTIAL IMPACT ON MECHANICAL POWER                        |
|                                                                                                    |
|            Variable                Mathematical Weight             Pathophysiological Impact       |
|    ---------------------------    ---------------------    --------------------------------------- |
|    Tidal Volume ($V_T$)                 $V_T^2$            Highest impact (Severe hyper-strain)    |
|    Driving Pressure ($\Delta P$)        $\Delta P^2$       Dominant static stress determinant      |
|    Respiratory Rate ($RR$)              $RR^{1.4}$         Major kinetic energy accelerator        |
|    PEEP (Static baseline)               $\text{Linear}$    Dual role (Recruitment vs Overdistension)|
+----------------------------------------------------------------------------------------------------+
Clinical Danger Thresholds and Outcome Evidence
Multiple international observational cohorts (Serpa Neto et al., PRoVENT, LUNG SAFE sub-studies, Costa et al.) have established the prognostic significance of mechanical power in mechanically ventilated patients with and without ARDS:
+----------------------------------------------------------------------------------------------------+
|                                  MECHANICAL POWER THRESHOLDS                                       |
+------------------------------------+---------------------------------------------------------------+
| Absolute Mechanical Power ($MP$)   | - Safe / Low Risk: $< 12\text{ J/min}$                         |
|                                    | - Intermediate Risk: $12\text{--}17\text{ J/min}$             |
|                                    | - High Risk / Danger Threshold: $> 17\text{ J/min}$            |
|                                    |   (Associated with steep increase in ICU mortality)           |
+------------------------------------+---------------------------------------------------------------+
| Normalized Power to Compliance     | $MP / C_{rs} > 0.35\text{--}0.50\text{ J/min} / (\text{mL/cmH}_2\text{O})$|
| ($MP / C_{rs}$)                    | Highly specific for baby-lung overexertion                    |
+------------------------------------+---------------------------------------------------------------+
| Normalized Power to Lung Volume    | $MP / \text{FRC} > 4.0\text{--}6.0\text{ J/min per Liter of aerated lung}$|
| ($MP / \text{FRC}$)                | Gold-standard physiological index of regional energy density  |
+------------------------------------+---------------------------------------------------------------+
| Normalized Power to Body Weight    | $MP / \text{PBW} > 0.25\text{--}0.30\text{ J/min/kg}$          |
+------------------------------------+---------------------------------------------------------------+
In an analysis of 8,207 ARDS and non-ARDS ICU patients by Serpa Neto et al., mechanical power exceeding $17\text{ J/min}$ was independently associated with:
- Significant increase in 28-day in-hospital mortality (adjusted Hazard Ratio $1.35\text{--}1.60$).
- Decreased ventilator-free days.
- Higher incidence of newly developed ARDS in previously non-injured mechanically ventilated patients.
Bedside Optimization Protocol: The Ergotrauma Minimization Ladder
When caring for the mechanically ventilated patient, clinicians must employ a systematic step-by-step titration ladder to suppress driving pressure and mechanical power while maintaining adequate gas exchange:
+----------------------------------------------------------------------------------------------------+
|                               THE ERGOTRAUMA MINIMIZATION LADDER                                   |
+----------------------------------------------------------------------------------------------------+
| Step 1: Strict Tidal Volume Restriction (4-6 mL/kg PBW)                                            |
|   -> Immediately reduces the quadratic energy driver (VT^2).                                       |
|                                                                                                    |
| Step 2: Driving Pressure Limitation (Target dP < 14 cmH2O)                                         |
|   -> Re-evaluate Pplat at zero flow; titrate VT down to 5 or 4 mL/kg if dP >= 15 cmH2O.            |
|                                                                                                    |
| Step 3: Physiology-Guided PEEP Optimization                                                        |
|   -> Find the "sweet spot" on the compliance curve where Crs is maximized and dP is minimized.     |
|                                                                                                    |
| Step 4: Conservative Respiratory Rate Titration & Tolerant Permissive Hypercapnia                  |
|   -> Avoid tachypneic targets (RR > 28-30/min) that drive RR^1.4 power; tolerate pH >= 7.20.       |
|                                                                                                    |
| Step 5: Early Prone Positioning (>= 16 hours/day)                                                  |
|   -> Homogenizes transpulmonary pressure distribution, unloads dorsal units, lowers net power.     |
|                                                                                                    |
| Step 6: Deep Sedation & Neuromuscular Blockade (Early 48h in severe ARDS)                          |
|   -> Eliminates patient-ventilator dyssynchrony, double triggering, and occult P-SILI.             |
|                                                                                                    |
| Step 7: Extracorporeal Support (ECCO2R / V-V ECMO)                                                 |
|   -> Decouples gas exchange from lung mechanics, enabling "ultra-protective" ventilation           |
|      (VT 1-3 mL/kg, RR 4-10/min, dP < 10 cmH2O, MP < 5-8 J/min).                                  |
+----------------------------------------------------------------------------------------------------+
Bedside Monitoring and Parameter Targets Summary
| Parameter | Clinical Target | Physiological Rationale | Action If Exceeded |
|---|---|---|---|
| Tidal Volume ($V_T$) | $4\text{--}6\text{ mL/kg PBW}$ | Minimizes volumetric strain ($\epsilon = V_T / \text{FRC}$) and quadratic energy ($V_T^2$). | Reduce $V_T$ by $1\text{ mL/kg}$ steps down to $4\text{ mL/kg}$; allow permissive hypercapnia ($pH \ge 7.20$). |
| Driving Pressure ($\Delta P$) | $< 14\text{ cmH}_2\text{O}$ | Direct surrogate for dynamic lung strain; predicts mortality. | Decrease $V_T$; titrate PEEP for maximum compliance; verify absence of auto-PEEP. |
| Plateau Pressure ($P_{plat}$) | $\le 28\text{--}30\text{ cmH}_2\text{O}$ | Upper threshold for static transalveolar rupture and barotrauma. | Reduce $V_T$, treat chest wall stiffness, check abdominal compartment pressure. |
| Mechanical Power ($MP$) | $< 12\text{--}17\text{ J/min}$ | Total energy delivered per minute; prevents cumulative ergotrauma. | Reduce $RR$ (first-line for high power with modest $V_T$), reduce $V_T$, reduce excessive PEEP causing overdistension. |
| Normalized Power ($MP/C_{rs}$) | $< 0.35\text{ J/min}/(\text{mL/cmH}_2\text{O})$ | Calibrates mechanical energy to functional baby lung capacity. | Implement prone positioning; initiate early paralytics; evaluate for ECMO. |
| Respiratory Rate ($RR$) | $14\text{--}24\text{ breaths/min}$ | Suppresses kinetic frequency multiplier ($RR^{1.4}$). | Remove mechanical deadspace (HME $\to$ heated humidifier); accept mild acidosis. |
Bedside Troubleshooting & Red Flag Scenarios
High Mechanical Power with Low Tidal Volume (The Tachypnea Paradox): In patients ventilated with $V_T = 6\text{ mL/kg PBW}$ but a high respiratory rate ($RR = 32\text{--}35\text{ breaths/min}$) to clear severe hypercapnia, the mechanical power frequently exceeds $20\text{--}25\text{ J/min}$. Because $MP$ scales exponentially with frequency ($RR^{1.4}$), high-frequency ventilation in severe ARDS causes silent, unremitting ergotrauma.
Intervention: Decrease dead space (switch from passive HME filters to active heated humidifiers, trim excess tubing), lower the set $RR$ to $20\text{--}24\text{ breaths/min}$, tolerate respiratory acidosis down to $pH \approx 7.20\text{--}7.25$, and use intravenous sodium bicarbonate or tris-hydroxymethyl aminomethane (THAM) infusions if needed to maintain systemic buffer capacity.
Occult Patient Self-Inflicted Lung Injury (P-SILI) in Spontaneous Modes: Transitioning a severely injured ARDS patient to assisted spontaneous breathing modes (e.g., Pressure Support Ventilation) prematurely can drastically amplify mechanical power. Vigorous spontaneous inspiratory efforts generate large negative pleural pressure swings ($\Delta P_{pl}$ up to $-20\text{ cmH}_2\text{O}$), creating massive localized transpulmonary driving pressure ($P_L = P_{ao} - P_{pl} > 30\text{ cmH}_2\text{O}$), occult pendelluft gas shifts from nondependent to dependent units, and intense capillary transmural vascular shear stress.
Intervention: Measure esophageal pressure swings ($\Delta P_{es}$) or airway occlusion pressure ($P_{0.1}$). If $P_{0.1} > 3.5\text{--}4.0\text{ cmH}_2\text{O}$ or $\Delta P_{es} > 10\text{--}12\text{ cmH}_2\text{O}$, increase sedation depth, resume controlled mandatory ventilation, and administer short-course neuromuscular blockade.
Key Clinical Takeaways
- VILI is fundamentally an energy-driven disease: While classic volutrauma, barotrauma, and atelectrauma represent specific structural injury patterns, Mechanical Power ($MP$) unifies all ventilatory inputs ($V_T$, pressures, flow, rate) into a cohesive thermodynamic framework of cumulative parenchymal injury.
- Driving Pressure ($\Delta P < 14\text{ cmH}_2\text{O}$) is the bedside compass: Because $\Delta P = V_T / C_{rs}$, it accurately reflects dynamic strain on the functional "baby lung". Any ventilator adjustment that reduces $\Delta P$ reduces VILI risk and improves survival.
- Beware the Frequency Multiplier: High respiratory rates deliver immense dynamic power to fragile alveolar septa. Rate reduction paired with permissive hypercapnia is a core component of energy-protective ventilation.
- Prone Positioning unloads parenchymal energy: Beyond improving ventilation-perfusion matching, prone positioning homogenizes transpulmonary pressure gradients, reduces regional stress concentrations, improves lung compliance, and significantly decreases total mechanical power.
- Normalize power to lung capacity: An absolute power of $15\text{ J/min}$ may be safe in a normal lung ($C_{rs} = 60\text{ mL/cmH}_2\text{O}$), but catastrophic in a severely consolidated baby lung ($C_{rs} = 15\text{ mL/cmH}_2\text{O}$, where $MP/C_{rs} = 1.0\text{ J/min}/(\text{mL/cmH}_2\text{O})$).