Advanced bedside respiratory monitoring bridges the gap between whole-system lung mechanics and regional pathophysiological behavior in critically ill patients with acute respiratory failure and Acute Respiratory Distress Syndrome (ARDS). Conventional ventilator graphics and airway pressure scalars reflect the aggregate behavior of the total respiratory system—lumping the lungs, pleural space, chest wall, diaphragm, and abdomen into a single combined elastance and resistance model. Consequently, surface airway pressure ($P_{aw}$) frequently obscures dangerous lung overdistension, silent regional collapse, and patient-ventilator dyssynchrony.
To individualize lung-protective ventilation and minimize Ventilator-Induced Lung Injury (VILI), advanced physiological monitoring employs three complementary modalities:
- Esophageal Balloon Catheter Manometry: Directly measures esophageal pressure ($P_{es}$) as a surrogate for pleural pressure ($P_{pl}$), enabling partitioning of the respiratory system into chest wall elastance ($E_{cw}$) and lung elastance ($E_L$) and direct calculation of transpulmonary pressure ($P_L$).
- Electrical Impedance Tomography (EIT): Provides continuous, radiation-free, real-time functional cross-sectional imaging of regional lung ventilation distribution, alveolar recruitment/collapse, tidal overdistension, and pulmonary microvascular perfusion.
- Volumetric Capnography: Analyzes carbon dioxide elimination breath-by-breath as a function of expired volume, quantifying anatomical dead space ($V_{D,ana}$), Bohr-Enghoff physiological dead space fraction ($V_D/V_T$), and ventilation-perfusion ($V_A/Q$) heterogeneity via Phase III slope analysis.
+----------------------------------------------------------------------------------------------------+
|                         ADVANCED RESPIRATORY MONITORING TRIAD                                      |
+------------------------------------+---------------------------------------------------------------+
| Modality                           | Primary Clinical Target & Physiological Measurement           |
+------------------------------------+---------------------------------------------------------------+
| Esophageal Balloon Manometry       | - Direct measurement of pleural pressure surrogate ($P_{es}$)  |
|                                    | - Transpulmonary stress: $P_L = P_{aw} - P_{es}$              |
|                                    | - Separation of lung ($E_L$) vs chest wall ($E_{cw}$) elastance|
|                                    | - Patient effort & transdiaphragmatic pressure ($\Delta P_{es}$)|
+------------------------------------+---------------------------------------------------------------+
| Electrical Impedance Tomography    | - Dynamic spatial mapping of regional lung impedance ($\Delta Z$) |
| (EIT)                              | - Quantification of non-dependent vs dependent ventilation    |
|                                    | - Bedside PEEP titration via collapse vs overdistension curves|
|                                    | - Hypertonic saline bolus for regional perfusion & V/Q mapping|
+------------------------------------+---------------------------------------------------------------+
| Volumetric Capnography             | - Fowler's anatomical dead space ($V_{D,ana}$, Phase II)      |
|                                    | - Bohr-Enghoff physiological dead space fraction ($V_D/V_T$)   |
|                                    | - Phase III slope ($S_{III}$) reflecting structural V/Q mismatch|
|                                    | - Alveolar tidal volume ($V_{T,alv}$) & metabolic $VCO_2$ output|
+------------------------------------+---------------------------------------------------------------+
1. Esophageal Balloon Catheter Manometry & Transpulmonary Pressure ($P_L$)
Fundamental Physical & Physiological Principles
The driving pressure measured at the airway opening ($P_{aw}$) reflects the pressure required to distend both the lung parenchyma and the chest wall simultaneously:
$$P_{aw} = P_L + P_{pl}$$Where:
- $P_{aw}$ = Airway opening pressure (or alveolar pressure $P_{alv}$ during static zero-flow conditions).
- $P_{pl}$ = Pleural surface pressure surrounding the lungs.
- $P_L$ = Transpulmonary pressure ($P_L = P_{aw} - P_{pl}$), representing the true physical distending stress applied directly across the alveolar architecture and lung skeleton.
In a normal, non-obese, supine patient, pleural pressure at end-expiration is near atmospheric or slightly positive ($+1\text{ to }+3\text{ cmH}_2\text{O}$), and chest wall compliance is high. However, in critically ill patients with severe obesity (BMI $> 35\text{--}40\text{ kg/m}^2$), intra-abdominal hypertension (IAH, intra-abdominal pressure $> 12\text{--}15\text{ mmHg}$), abdominal compartment syndrome, massive anasarca, chest wall burn eschars, or thoracic cage rigidity, pleural pressure rises markedly ($+10\text{ to }+25\text{ cmH}_2\text{O}$). Under these conditions, an airway plateau pressure ($P_{plat}$) of $35\text{ cmH}_2\text{O}$ may only generate a benign transpulmonary lung stress of $15\text{ cmH}_2\text{O}$, while an applied PEEP of $10\text{ cmH}_2\text{O}$ leaves end-expiratory transpulmonary pressure deeply negative ($-5\text{ cmH}_2\text{O}$), driving relentless dependent alveolar collapse and cyclic atelectrauma.
Because direct clinical measurement of pleural pressure via intrapleural fluid catheters carries high risks of pneumothorax, lung laceration, and localized artifact, esophageal pressure ($P_{es}$) measured within the lower third of the esophagus serves as an accurate and reproducible clinical surrogate for regional pleural pressure in the adjacent mid-dorsal zones.
+----------------------------------------------------------------------------------------------------+
|                                ELASTANCE PARTITIONING EQUATIONS                                    |
+------------------------------------+---------------------------------------------------------------+
| Total Respiratory System Elastance | $E_{rs} = \frac{\Delta P_{aw}}{V_T} = E_L + E_{cw}$            |
+------------------------------------+---------------------------------------------------------------+
| Lung Elastance                     | $E_L = \frac{\Delta P_L}{V_T} = \frac{\Delta (P_{aw} - P_{es})}{V_T}$ |
+------------------------------------+---------------------------------------------------------------+
| Chest Wall Elastance               | $E_{cw} = \frac{\Delta P_{es}}{V_T}$                          |
+------------------------------------+---------------------------------------------------------------+
| Elastance Partition Ratio          | $\frac{E_L}{E_{rs}} = \frac{E_L}{E_L + E_{cw}}$               |
+------------------------------------+---------------------------------------------------------------+
Absolute vs. Elastance-Derived Transpulmonary Pressure Methods
In clinical practice, two distinct methods are utilized to compute transpulmonary pressure:
+----------------------------------------------------------------------------------------------------+
|                         TRANSPULMONARY PRESSURE CALCULATION METHODS                                |
+------------------------------------+---------------------------------------------------------------+
| Method                             | Formula & Theoretical Framework                               |
+------------------------------------+---------------------------------------------------------------+
| Directly Measured (Direct $P_{es}$)| $P_{L} = P_{aw} - P_{es}$                                     |
| (Talmor / Beth Israel Deaconess)   | Assumes measured $P_{es}$ directly represents local dependent   |
|                                    | pleural pressure. Used to titrate PEEP in the EPVent trials   |
|                                    | to ensure dependent $P_{L,exp} \ge 0\text{ to }+2\text{ cmH}_2\text{O}$.|
+------------------------------------+---------------------------------------------------------------+
| Elastance-Derived ($E_L/E_{rs}$)   | $P_{L,insp} = P_{plat} \cdot \left(\frac{E_L}{E_{rs}}\right)$ |
| (Gattinoni / Milan Approach)       | Normalizes for vertical gravitational pleural gradients.      |
|                                    | Reflects global non-dependent alveolar lung stress at         |
|                                    | end-inspiration to prevent overdistension and barotrauma.     |
+------------------------------------+---------------------------------------------------------------+
Step-by-Step Esophageal Balloon Placement and Calibration Protocol
Accurate esophageal manometry requires rigorous adherence to catheter positioning, volume calibration, and dynamic validation. Artifacts from esophageal muscle spasms, cardiac compression, gastric placement, or balloon over-filling render measurements clinically misleading.
+----------------------------------------------------------------------------------------------------+
|                    ESOPHAGEAL BALLOON PLACEMENT & CALIBRATION ALGORITHM                            |
+----------------------------------------------------------------------------------------------------+
| 1. INSERTION:                                                                                      |
|    - Transoral or transnasal advancement of balloon catheter to ~50-55 cm (stomach).               |
|    - Confirm gastric position by positive pressure deflection during gentle epigastric pressure.   |
|                                                                                                    |
| 2. WITHDRAWAL TO LOWER THIRD ESOPHAGUS:                                                            |
|    - Slowly withdraw catheter in 1-2 cm increments to ~35-45 cm depth.                            |
|    - Monitor pressure waveform for transition from positive abdominal to cardiac oscillations.     |
|                                                                                                    |
| 3. BALLOON FILLING VOLUME TITRATION (CALIBRATION):                                                 |
|    - Completely evacuate balloon with syringe (draw negative vacuum).                              |
|    - Inject calibration gas (air) in sequential steps (e.g., 0.5 mL steps from 0.5 to 6.0 mL).     |
|    - Identify linear, artifact-free compliance plateau of the balloon membrane ($V_{opt}$).        |
|                                                                                                    |
| 4. DYNAMIC VALIDATION (OCCLUSION TEST / BAYDUR MANEUVER):                                          |
|    - Perform end-expiratory airway occlusion hold.                                                 |
|    - During spontaneous breathing effort (or passive chest compression):                          |
|      Verify $\Delta P_{es} / \Delta P_{aw} \approx 0.8\text{--}1.2$.                               |
|    - If ratio < 0.8 -> Catheter too deep or underfilled; if ratio > 1.2 -> Catheter too shallow.   |
+----------------------------------------------------------------------------------------------------+
1. Anatomical Insertion and Positioning
- Advance the catheter into the stomach (typically $50\text{--}55\text{ cm}$ at the incisors in adults).
- Verify gastric entry: A gentle manual compression of the upper epigastrium produces a sharp, immediate upward deflection in recorded pressure.
- Slowly withdraw the catheter with balloon evacuated into the lower third of the esophagus (typically $35\text{--}42\text{ cm}$ mark in adults of average height).
- Verify lower esophageal position:
- Disappearance of gastric baseline shifts.
- Appearance of distinct, rhythmic cardiac oscillations superimposed on the respiratory pressure trace (transmitted from the adjacent left atrium and descending aorta).
- Negative deflection during spontaneous inspiratory efforts, or positive deflection during passive mechanical inflation.
2. Balloon Volume Calibration (Titration Curve)
An esophageal balloon is an elastic membrane surrounded by esophageal tissue.
- If underfilled, the balloon walls remain collapsed and do not transmit surrounding pressure ($P_{es}$ underestimation).
- If overfilled, the intrinsic elasticity of the balloon membrane generates internal wall tension, adding false positive pressure artifact ($P_{es}$ overestimation).
- Protocol: Fully evacuate the balloon. Using a dedicated gas-tight micro-syringe, incrementally instill volume in steps of $0.5\text{ mL}$ (from $0.5\text{ mL}$ to $5.0\text{--}6.0\text{ mL}$, depending on manufacturer specifications). Plot balloon filling volume against baseline pressure. Select the operating volume ($V_{opt}$, typically $1.0\text{--}2.5\text{ mL}$) located within the flat, lowest-pressure zone of maximum balloon compliance.
3. Dynamic Occlusion Test (The Baydur Maneuver)
Validation of faithful pressure transmission across the chest wall is mandatory before utilizing $P_{es}$ for clinical decisions:
- In Spontaneously Breathing Patients: Perform an end-expiratory airway occlusion maneuver (holding the airway closed for 3–5 seconds). When the patient makes spontaneous inspiratory efforts against the closed circuit, no gas moves ($\Delta V = 0$). Consequently, the change in alveolar pressure is identical to the change in pleural pressure: $$\frac{\Delta P_{es}}{\Delta P_{aw}} \approx 1.0 \quad (\text{Acceptable clinical range: } 0.8\text{ to } 1.2)$$
- In Fully Paralyzed / Passive Patients: Perform an end-expiratory occlusion and apply gentle, rapid external chest compressions to the lower sternum/rib cage. The ratio of induced $\Delta P_{es}$ to $\Delta P_{aw}$ must equal $0.8\text{--}1.2$.
- Troubleshooting:
- If $\Delta P_{es} / \Delta P_{aw} < 0.8$: Catheter is positioned too deep (in the stomach/distal gastroesophageal junction) or the balloon is underfilled.
- If $\Delta P_{es} / \Delta P_{aw} > 1.2$: Catheter is retracted too high in the upper esophagus (subject to tracheal compression and neck flexion artifacts) or the balloon is overfilled.
Clinical Titration Protocols: EPVent and EPVent-2 Evidence
The application of esophageal manometry in ARDS centers on two primary goals: setting PEEP to prevent expiratory collapse while avoiding inspiratory overdistension.
+----------------------------------------------------------------------------------------------------+
|                         CLINICAL TITRATION GOALS VIA TRANSPULMONARY PRESSURE                       |
+------------------------------------+---------------------------------------------------------------+
| Phase of Respiration               | Physiological Target & Clinical Safety Threshold              |
+------------------------------------+---------------------------------------------------------------+
| End-Expiration ($P_{L,exp}$)       | Target: $P_{L,exp} = \text{PEEP} - P_{es,exp} \ge 0\text{ to }+2\text{ cmH}_2\text{O}$|
|                                    | Prevents cyclic alveolar derecruitment and dependent collapse.|
|                                    | In morbid obesity/IAH, may require PEEP of 18-28 cmH2O.        |
+------------------------------------+---------------------------------------------------------------+
| End-Inspiration ($P_{L,insp}$)     | Target: $P_{L,insp} = P_{plat} - P_{es,insp} < 20\text{--}25\text{ cmH}_2\text{O}$|
| (Direct Method)                    | Prevents global tensile lung strain ($\epsilon > 1.5\text{--}2.0$) and    |
|                                    | volutrauma / alveolar membrane disruption.                    |
+------------------------------------+---------------------------------------------------------------+
| Transpulmonary Driving Pressure    | Target: $\Delta P_L = P_{L,insp} - P_{L,exp} < 10\text{--}12\text{ cmH}_2\text{O}$|
| ($\Delta P_L$)                     | Minimizes dynamic tidal stress and dissipated mechanical energy|
+------------------------------------+---------------------------------------------------------------+
Evidence from Landmark Trials
- EPVent-1 Trial (Talmor et al., NEJM 2008):
- Single-center randomized controlled trial ($n=61$) comparing $P_{es}$-guided PEEP titration against the standard ARDSNet high-PEEP/low-$FiO_2$ protocol in moderate-to-severe ARDS.
- PEEP was adjusted to achieve an end-expiratory transpulmonary pressure ($P_{L,exp}$) between $0\text{ and }+10\text{ cmH}_2\text{O}$ based on $FiO_2$ requirements.
- Findings: The $P_L$-guided group demonstrated significantly superior oxygenation ($PaO_2/FiO_2$ ratio improvement) and improved static respiratory compliance, with a significant reduction in 28-day mortality ($17\%$ vs $39\%$, $p=0.002$).
- EPVent-2 Trial (Beitler et al., JAMA 2019):
- Multi-center international randomized controlled trial ($n=200$) comparing $P_{es}$-guided PEEP titration against an empiric high-PEEP strategy in moderate-to-severe ARDS.
- Findings: No statistically significant difference in the primary composite endpoint of death and days free from mechanical ventilation at day 28.
- Critical Clinical Nuance & Subgroup Translation: In the control arm, high PEEP was aggressively delivered by protocol, achieving near-optimal lung recruitment in average patients. However, in patients with discordant chest wall mechanics (morbid obesity, abdominal distension, severe chest wall stiffness), $P_L$ guidance uniquely prevented profound under-PEEPing (hypoxemia/atelectasis) and over-PEEPing (hemodynamic collapse), establishing esophageal manometry as an indispensable precision tool in complex, non-standard chest wall phenotypes.
2. Electrical Impedance Tomography (EIT)
Physical Principles and Belt Application
Electrical Impedance Tomography (EIT) is a non-invasive, radiation-free bedside imaging technology that generates high-frequency, cross-sectional functional images of regional lung ventilation and perfusion.
+----------------------------------------------------------------------------------------------------+
|                         ELECTRICAL IMPEDANCE TOMOGRAPHY (EIT) SETUP                                |
+------------------------------------+---------------------------------------------------------------+
| Feature                            | Technical Specification & Clinical Operation                  |
+------------------------------------+---------------------------------------------------------------+
| Electrode Configuration            | 16 or 32 equidistant active surface electrodes embedded in a  |
|                                    | flexible silicone belt.                                       |
+------------------------------------+---------------------------------------------------------------+
| Anatomical Application             | Positioned circumferentially around the thorax at the         |
|                                    | 4th to 5th intercostal space (parasternal/nipple line level). |
+------------------------------------+---------------------------------------------------------------+
| Current Injection & Measurement    | Injects imperceptible, high-frequency alternating current     |
|                                    | ($50\text{--}80\text{ kHz}$, $5\text{ mA}$) through adjacent  |
|                                    | electrode pairs; measures boundary voltages on remaining pairs.|
+------------------------------------+---------------------------------------------------------------+
| Temporal & Spatial Resolution      | Frame rate: 20–50 scans/second; spatial resolution:           |
|                                    | $32 \times 32$ pixel matrix normalized to anatomical thorax.  |
+------------------------------------+---------------------------------------------------------------+
The fundamental biophysical principle relies on electrical resistivity changes:
- Air has extremely low electrical conductivity (high impedance). As alveoli inflate with gas during inspiration, local electrical impedance increases markedly ($\Delta Z > 0$).
- Fluid, blood, and collapsed tissue have high electrical conductivity (low impedance).
- By measuring boundary voltage differentials across rotating pairs of electrodes hundreds of times per second, finite-element back-projection algorithms construct real-time dynamic maps of relative impedance change ($\Delta Z$), directly proportional to regional tidal volume distribution ($\Delta V$).
        ANTERIOR (VENTRAL)
    +------------------------+
    |   ROI 1: Ventral       |   <- Non-dependent zone: Prone to OVERDISTENSION
    |                        |
    +------------------------+
    |   ROI 2: Mid-Ventral   |
    +------------------------+
    |   ROI 3: Mid-Dorsal    |
    +------------------------+
    |   ROI 4: Dorsal        |   <- Dependent zone: Prone to COLLAPSE / ATELECTASIS
    +------------------------+
        POSTERIOR (DORSAL)
EIT-Guided Decremental PEEP Titration (The Crossing Point Curve)
One of the most powerful bedside applications of EIT is the determination of optimal patient-specific PEEP through a standardized decremental PEEP titration maneuver.
+----------------------------------------------------------------------------------------------------+
|                      EIT DECREMENTAL PEEP TITRATION PROTOCOL                                       |
+----------------------------------------------------------------------------------------------------+
| 1. ALVEOLAR RECRUITMENT MANEUVER:                                                                  |
|    - Perform CPAP hold ($40\text{ cmH}_2\text{O}$ for 40 sec) or step-wise pressure titration to   |
|      open recruitable lung units.                                                                  |
|                                                                                                    |
| 2. STEPWISE DECREMENTAL TITRATION:                                                                 |
|    - Begin at high PEEP ($24\text{--}20\text{ cmH}_2\text{O}$).                                    |
|    - Decrease PEEP in steps of $2\text{ cmH}_2\text{O}$ every 2–3 minutes down to $6\text{--}4\text{ cmH}_2\text{O}$.|
|    - Continuous EIT acquisition during the final 30 seconds of each PEEP step.                     |
|                                                                                                    |
| 3. ALGORITHMIC REGIONAL IMPEDANCE ANALYSIS:                                                        |
|    - Non-Dependent Regions (Ventral): Track reduction in regional compliance with high PEEP        |
|      -> Quantifies percentage of OVERDISTENDED lung units.                                         |
|    - Dependent Regions (Dorsal): Track loss of regional tidal impedance with decreasing PEEP       |
|      -> Quantifies percentage of COLLAPSED (derecruited) lung units.                               |
|                                                                                                    |
| 4. IDENTIFICATION OF OPTIMAL CROSSING POINT:                                                       |
|    - Plot % Overdistension and % Collapse vs PEEP level.                                           |
|    - Optimal compromise PEEP is identified where:                                                  |
|      $\text{Total Lung Mechanical Loss} = (\% \text{ Overdistension} + \% \text{ Collapse})$ is MINIMAL.|
|    - The intersection point represents the optimal balance between opening dorsal atelectasis      |
|      and sparing ventral hyperinflation.                                                           |
+----------------------------------------------------------------------------------------------------+
(Where $y_i$ represents the dorsoventral coordinate; healthy supine baseline $\approx 45\text{--}50\%$; dorsal collapse shifts $\text{CoV}$ ventrally to $<40\%$.)
Advanced Diagnostic Applications of EIT
+----------------------------------------------------------------------------------------------------+
|                           ADVANCED CLINICAL CAPABILITIES OF EIT                                    |
+------------------------------------+---------------------------------------------------------------+
| Diagnostic Feature                 | Clinical Manifestation & Bedside Interpretation               |
+------------------------------------+---------------------------------------------------------------+
| Occult Pneumothorax Detection      | Sudden, complete loss of dynamic cyclic impedance ($\Delta Z$) |
|                                    | in the ventral region of the affected hemithorax, accompanied |
|                                    | by an elevated baseline static impedance (trapped air).       |
+------------------------------------+---------------------------------------------------------------+
| Asymmetric Ventilation & ETT Depth | Immediate identification of mainstem bronchus intubation      |
|                                    | (unilateral ventilation of right hemithorax with silent left);|
|                                    | unequal distribution in unilateral pneumonia, contusion, flail.|
+------------------------------------+---------------------------------------------------------------+
| EIT-Based Perfusion Mapping        | Rapid central venous bolus of $10\text{ mL}$ $5.85\%$ or $10\%$|
| (Hypertonic Saline Bolus)          | hypertonic saline during an end-expiratory pause. Acts as an   |
|                                    | intravascular conductive tracer, generating a transient       |
|                                    | impedance drop across pulmonary capillary beds.               |
+------------------------------------+---------------------------------------------------------------+
| Direct V/Q Ratio & Shunt / Dead    | Superimposing EIT ventilation ($\Delta Z_{vent}$) with EIT    |
| Space Imaging                      | perfusion ($\Delta Z_{perf}$) maps calculates regional $V/Q$:  |
|                                    | - Shunt units: Perfusion without ventilation ($V/Q = 0$)       |
|                                    | - Alveolar Dead Space: Ventilation without perfusion ($V/Q=\infty$)|
|                                    | - Matched units: Normal gas exchange ($V/Q \approx 1$).        |
+------------------------------------+---------------------------------------------------------------+
| Pendelluft Phenomenon              | Inter-regional gas redistribution occurring without volume    |
|                                    | change at the airway opening during spontaneous breathing      |
|                                    | efforts, where gas shifts asynchronously from non-dependent    |
|                                    | to dependent zones due to localized pleural pressure drops.   |
+------------------------------------+---------------------------------------------------------------+
3. Volumetric Capnography ($V_{CO_2}$ vs. Expired Volume)
While conventional time-based capnography plots $PCO_2$ against time ($PCO_2\text{ vs } t$) to confirm endotracheal tube placement and detect airway obstruction, Volumetric Capnography ($V_{CO_2}\text{ vs } V_E$) integrates instantaneous airway flow and exhaled carbon dioxide concentration to measure breath-by-breath physiological gas exchange, dead space fractions, and structural ventilation heterogeneity.
+----------------------------------------------------------------------------------------------------+
|                               THE THREE PHASES OF VOLUMETRIC CAPNOGRAPHY                           |
+------------------------------------+---------------------------------------------------------------+
| Phase                              | Anatomical & Physiological Meaning                            |
+------------------------------------+---------------------------------------------------------------+
| Phase I (Anatomical Dead Space)    | Initial gas exhaled from apparatus and conducting airways;     |
|                                    | $PCO_2 = 0\text{ mmHg}$ (contains no metabolic $CO_2$).       |
+------------------------------------+---------------------------------------------------------------+
| Phase II (Bronchial Transition)    | S-shaped ascending transition zone; rapid mixing of conducting|
|                                    | airway dead space gas with alveolar gas.                      |
+------------------------------------+---------------------------------------------------------------+
| Phase III (Alveolar Plateau)       | Pure alveolar gas emptying; slope ($S_{III}$) reflects the     |
|                                    | degree of ventilation-perfusion matching and alveolar emptying|
|                                    | time-constant heterogeneity.                                  |
+------------------------------------+---------------------------------------------------------------+
     PCO2 (mmHg)
       ^
    40 |                                  Phase III (Alveolar Plateau)
       |                               .---------------------. (PetCO2)
       |                            .-'  Slope = S_III
       |                         .-'
    20 |                      .-' Phase II (Transition)
       |                   .-'
       |  Phase I         |
     0 +------------------+----------------------------------------->
       0             V_D,ana (Fowler)                        Expired Volume (mL)
Quantitative Mathematical Equations & Dead Space Partitions
+----------------------------------------------------------------------------------------------------+
|                         VOLUMETRIC CAPNOGRAPHY MATHEMATICAL DERIVATIONS                            |
+------------------------------------+---------------------------------------------------------------+
| Metric                             | Mathematical Formula & Clinical Target                        |
+------------------------------------+---------------------------------------------------------------+
| Fowler's Anatomical Dead Space     | Determined by equal-area graphical integration of Phase II:    |
| ($V_{D,ana}$)                      | Area of $CO_2$ under transition curve = Area above curve.     |
|                                    | Normal: $1.5\text{--}2.0\text{ mL/kg}$ IBW ($\approx 150\text{ mL}$).|
+------------------------------------+---------------------------------------------------------------+
| Bohr-Enghoff Physiological         | $$\frac{V_D}{V_T} = \frac{PaCO_2 - P_{\bar{E}}CO_2}{PaCO_2}$$  |
| Dead Space Fraction                | ($P_{\bar{E}}CO_2$ = Mixed expired $CO_2$ tension across full  |
|                                    | exhalation). Normal: $0.25\text{--}0.35$. In severe ARDS: $>0.60$.|
+------------------------------------+---------------------------------------------------------------+
| Alveolar Dead Space Fraction       | $$\frac{V_{D,alv}}{V_{T,alv}} = \frac{PaCO_2 - PetCO_2}{PaCO_2}$$|
| (Severinghaus / Alveolar-Arterial) | Normal: $\approx 0\text{--}0.05$. Elevated in pulmonary       |
|                                    | embolism, high PEEP overdistension, and low cardiac output.   |
+------------------------------------+---------------------------------------------------------------+
| Phase III Slope ($S_{III}$)        | $$S_{III} = \frac{\Delta PCO_2}{\Delta V} \quad (\text{mmHg/L})$$|
| Normalized: $S_{III} / P_{\bar{E}}CO_2$| Steepening indicates marked spatial ventilation heterogeneity,|
|                                    | airway obstruction, or high compliance-time constant mismatch.|
+------------------------------------+---------------------------------------------------------------+
4. Synthesis: Multimodal Bedside Respiratory Monitoring
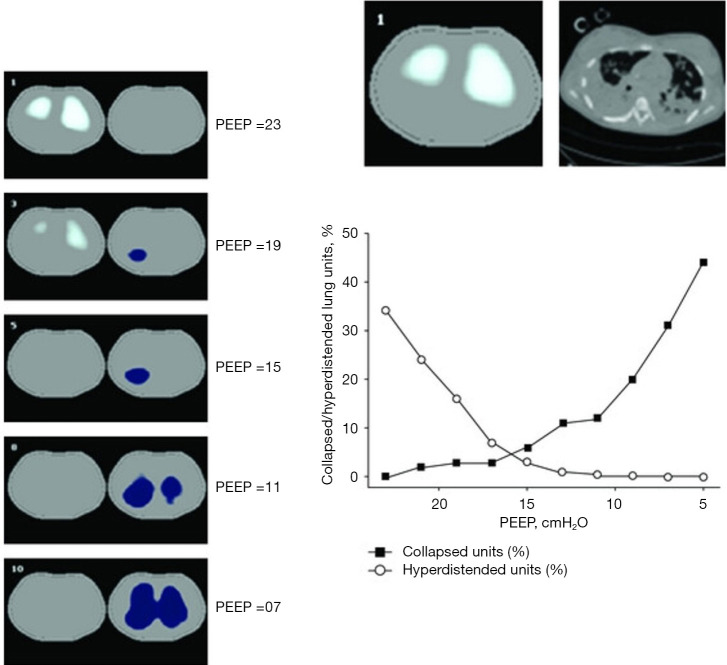 Figure: Real-time decremental PEEP titration guided by Electrical Impedance Tomography (EIT) in Acute Respiratory Distress Syndrome (Translational Pediatrics, 2026, CC-BY 4.0; DOI:
10.21037/tp-2025-aw-684
; PMCID: PMC13071672). Sequential functional EIT images illustrate the progressive emergence of dependent dorsal alveolar collapse (blue, right panel) during decremental PEEP titration from 23 to 5 cmH2O, contrasting with the concurrent relief of non-dependent ventral alveolar overdistension (white, left panel). The bottom-right crossing point curve plots collapsed units (%) versus hyperdistended units (%) across decremental PEEP levels, precisely identifying the optimal compromise PEEP (17 cmH2O) where combined mechanical lung loss is minimized. Top right shows functional EIT ventilation distribution correlated directly with an axial thoracic computed tomography scan.
Bedside Integration and Clinical Summary Matrix
+----------------------------------------------------------------------------------------------------+
|                         BEDSIDE INTEGRATION & CLINICAL SUMMARY MATRIX                              |
+-------------------------+-----------------------------------+--------------------------------------+
| Clinical Scenario       | Advanced Diagnostic Findings      | Targeted Bedside Action              |
+-------------------------+-----------------------------------+--------------------------------------+
| Severe Morbid Obesity   | - $P_{plat} = 36\text{ cmH}_2\text{O}$,| - Increase PEEP from 12 to 18–22     |
| (BMI 48) with ARDS      |   $P_{es,insp} = 22\text{ cmH}_2\text{O}$|   $\text{cmH}_2\text{O}$ to maintain |
|                         | - $P_{L,insp} = +14\text{ cmH}_2\text{O}$|   $P_{L,exp} \ge +2\text{ cmH}_2\text{O}$.|
|                         | - $P_{L,exp} = -6\text{ cmH}_2\text{O}$| - Prevents dependent derecruitment   |
|                         | - EIT shows 35% dorsal collapse   |   without risk of true overdistension.|
+-------------------------+-----------------------------------+--------------------------------------+
| Excessive PEEP          | - $P_{L,insp} = +28\text{ cmH}_2\text{O}$| - Decrement PEEP in 2 cmH2O steps    |
| Overdistension          | - EIT shows >30% non-dependent    |   toward the EIT crossing point.     |
|                         |   overdistension (ventral ROI)    | - Normalizes alveolar dead space and |
|                         | - Volumetric capnography shows    |   restores right ventricular preload.|
|                         |   sharp rise in $V_D/V_T$ (>0.65) |                                      |
+-------------------------+-----------------------------------+--------------------------------------+
| Acute Hemodynamic       | - EIT reveals sudden cessation of | - Emergent needle decompression /    |
| Collapse & Barotrauma   |   cyclic $\Delta Z$ in right hemithorax|   tube thoracostomy.                 |
| (Tension Pneumothorax)  | - Baseline static impedance jumps | - Avoids catastrophic delay awaiting |
|                         | - End-tidal $CO_2$ drops acutely  |   portable chest radiography.        |
+-------------------------+-----------------------------------+--------------------------------------+
| Refractory Hypoxemia:   | - EIT hypertonic saline bolus     | - Confirms massive intrapulmonary    |
| Shunt vs Dead Space     |   reveals robust perfusion in     |   shunt (non-ventilated dorsal units)|
|                         |   unventilated dorsal atelectasis | -> Initiate Prone Positioning or     |
|                         | - Bohr-Enghoff $V_D/V_T$ preserved|    Neuromuscular Blockade.           |
+-------------------------+-----------------------------------+--------------------------------------+
Key Takeaways for Clinical Practice
- Airway Pressures Deceive: High airway plateau pressure ($P_{plat} > 30\text{ cmH}_2\text{O}$) in patients with chest wall stiffening or obesity does not equate to dangerous lung stress ($P_L$). Direct measurement via esophageal manometry prevents inappropriate tidal volume starvation and inadequate PEEP.
- Dynamic Calibration is Essential: Never act on esophageal manometry without performing the Baydur occlusion test ($\Delta P_{es}/\Delta P_{aw} \approx 0.8\text{--}1.2$) and balloon filling volume titration ($V_{opt}$).
- EIT Visualizes Regional Heterogeneity: Whole-lung mechanics obscure regional trade-offs. The EIT crossing point curve objectively balances dependent atelectasis against non-dependent overdistension during decremental PEEP titration.
- Volumetric Capnography Reflects Vascular and Structural Injury: An elevated Bohr-Enghoff dead space fraction ($V_D/V_T > 0.60$) and steepening Phase III slope ($S_{III}$) are powerful, independent prognostic indicators of mortality in ARDS, reflecting microvascular thrombosis and extreme time-constant divergence.