The placement and maintenance of an artificial airway—whether an endotracheal tube (ETT) or a tracheostomy tube—represents one of the most critical interventions in the intensive care unit. While securing a definitive conduit for positive-pressure ventilation, artificial airways bypass the primary humidification, filtration, and warming mechanisms of the upper airway, disrupt natural glottic competence, and impose substantial resistive loads on spontaneous breathing. Optimal clinical outcomes demand rigorous tube sizing, precision cuff pressure titration, evidence-based timing of tracheostomy, structured liberation protocols, and active conditioning of inspired gases.
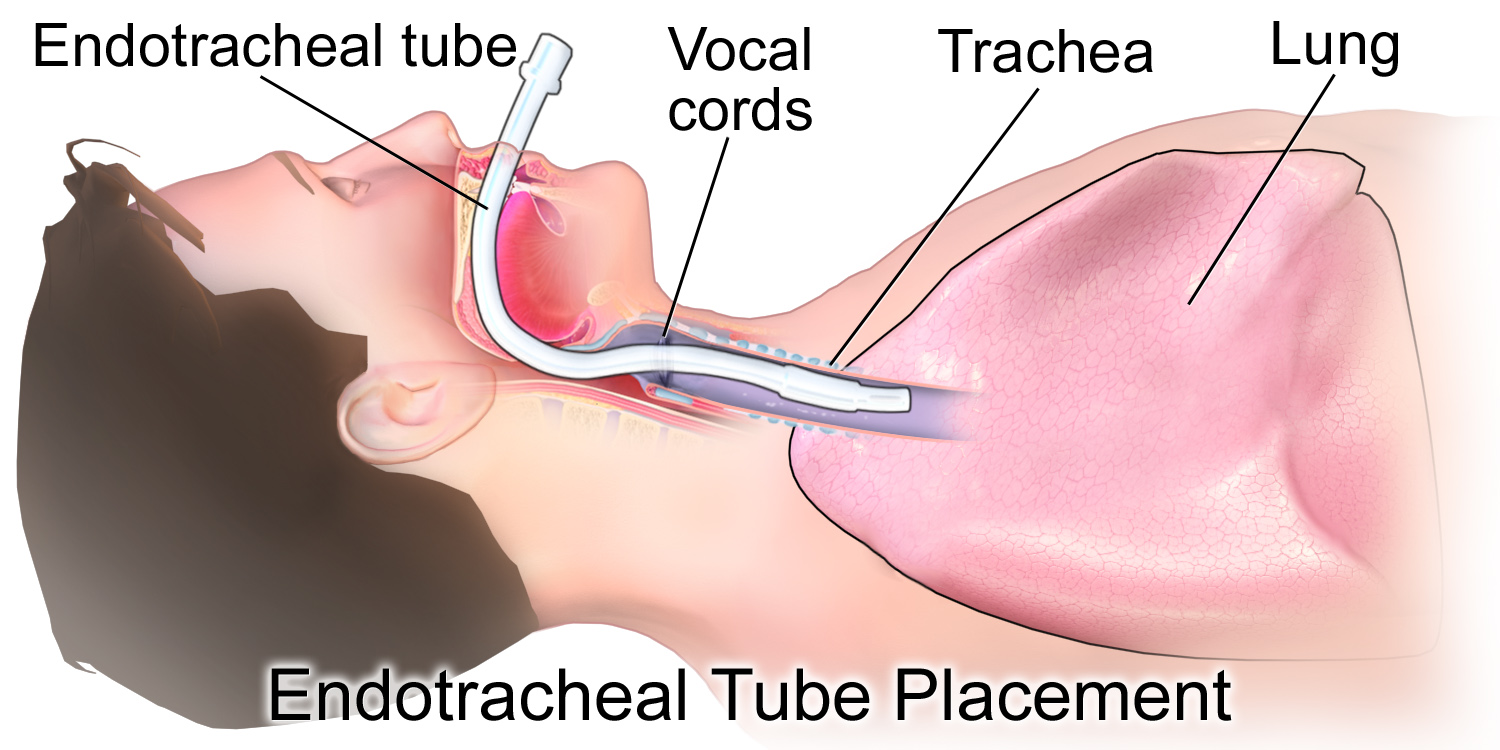 Figure 1: Comprehensive anatomical structure of a standard cuffed endotracheal tube (ETT). Key design components include the universal 15-mm proximal machine adapter, radiopaque longitudinal line for radiographic depth verification, centimeter depth graduation markings, high-volume low-pressure (HVLP) inflatable retention cuff, pilot balloon with an integrated one-way spring valve for manometric pressure titration, and distal beveled tip featuring a Murphy eye to ensure uninterrupted ventilation in the event of primary orifice occlusion.
1. Endotracheal Tube Selection, Sizing, and Depth Management
A. Sizing Algorithms Across the Lifespan
Selecting the appropriate internal diameter (ID) is crucial: an undersized tube dramatically escalates airway resistance and work of breathing, while an oversized tube risks subglottic ischemia, mucosal necrosis, and post-extubation subglottic stenosis.
                  ┌────────────────────────────────────────┐
                  │    Age & Weight-Based ETT Selection    │
                  └───────────────────┬────────────────────┘
                                      │
        ┌─────────────────────────────┼─────────────────────────────┐
        ▼                             ▼                             ▼
 ┌──────────────┐              ┌──────────────┐              ┌──────────────┐
 │   Neonatal   │              │  Pediatric   │              │    Adult     │
 │ (<1 to 1 mo) │              │  (1 to 16 y) │              │   (>16 y)    │
 └──────┬───────┘              └──────┬───────┘              └──────┬───────┘
        │                             │                             │
 ┌──────┴───────────────┐      ┌──────┴───────────────┐      ┌──────┴───────────────┐
 │ <1 kg: 2.5 mm        │      │ Cuffed:              │      │ Female: 7.0–7.5 mm   │
 │ 1–2 kg: 3.0 mm       │      │  (Age/4) + 3.5 mm    │      │ Male:   7.5–8.0 mm   │
 │ 2–3 kg: 3.5 mm       │      │                      │      │ (Use ≥7.5 mm for     │
 │ >3 kg: 3.5–4.0 mm    │      │ Uncuffed (Motoyama): │      │  bronchoscopy/suction│
 └──────────────────────┘      │  (Age/4) + 4.0 mm    │      │  and subglottic port)│
                               └──────────────────────┘      └──────────────────────┘
1. Adult Sizing
- Standard Adult Females: $7.0\text{ mm}$ to $7.5\text{ mm}$ ID (typical length at incisors: $21\text{ cm}$).
- Standard Adult Males: $7.5\text{ mm}$ to $8.0\text{ mm}$ ID (typical length at incisors: $23\text{ cm}$).
- Diagnostic & Interventional Consideration: In critically ill adults anticipated to require diagnostic/therapeutic flexible bronchoscopy (OD $\approx 5.0-6.0\text{ mm}$) or specialized double-lumen configurations, an ETT ID $\ge 7.5-8.0\text{ mm}$ is strongly preferred to maintain adequate cross-sectional lumen for exhalation around the bronchoscope and avoid catastrophic intrinsic positive end-expiratory pressure (auto-PEEP) buildup.
2. Pediatric Sizing Formulas
- Cuffed Endotracheal Tubes (Khine / Duracher Formulas): $$\text{Internal Diameter (mm)} = \frac{\text{Age in years}}{4} + 3.5$$
- Uncuffed Endotracheal Tubes (Modified Cole / Motoyama Formula): $$\text{Internal Diameter (mm)} = \frac{\text{Age in years}}{4} + 4.0$$
- Length / Depth Estimation Formulas: $$\text{Oral Insertion Depth at Lip (cm)} = \frac{\text{Age in years}}{2} + 12$$ $$\text{Oral Depth at Lip (cm)} = \text{ETT Internal Diameter (mm)} \times 3$$
3. Neonatal Sizing by Gestational Age and Birth Weight
| Weight Range | Gestational Age | ETT Internal Diameter (ID) | Depth at Mid-Upper Lip |
|---|---|---|---|
| $< 1000\text{ g}$ | $< 28\text{ weeks}$ | $2.5\text{ mm}$ (uncuffed) | $5.5 - 6.5\text{ cm}$ |
| $1000 - 2000\text{ g}$ | $28 - 34\text{ weeks}$ | $3.0\text{ mm}$ (uncuffed / micro-cuff) | $6.5 - 7.5\text{ cm}$ |
| $2000 - 3000\text{ g}$ | $34 - 38\text{ weeks}$ | $3.5\text{ mm}$ (uncuffed / micro-cuff) | $7.5 - 8.5\text{ cm}$ |
| $> 3000\text{ g}$ | $> 38\text{ weeks}$ (Term) | $3.5 - 4.0\text{ mm}$ | $8.5 - 9.5\text{ cm}$ |
- Neonatal Bedside Depth Rule: $$\text{Depth at Lip (cm)} = \text{Body Weight (kg)} + 6$$
B. Cuffed vs. Uncuffed Tubes: The Pediatric & Neonatal Paradigm Shift
Historically, uncuffed tubes were universally mandated in children $< 8\text{ years}$ based on the classic anatomical belief that the pediatric airway was funnel-shaped with the non-distensible cricoid cartilage acting as the narrowest anatomical constriction ("functional physiological cuff").
             HISTORICAL MODEL                            MODERN MRI/CT EVIDENCE
           (Funnel Configuration)                        (Cylindrical Configuration)
                ┌──────────┐                                    ┌──────────┐
                │ Glottis  │                                    │ Glottis  │ (Narrowest AP &
                └───┬──┬───┘                                    └───┬──┬───┘  Transverse Plane)
                    │  │                                            │  │
                   ╱    ╲                                           │  │
                  ╱      ╲                                          │  │
                 │ Cricoid│ (Narrowest Ring)                        │  │
                 └────────┘                                         │  │
Modern Evidence & Clinical Advantages of Micro-Cuff Tubes
- True Airway Geometry: Contemporary dynamic CT and MRI investigations demonstrated that the human pediatric larynx is elliptical/cylindrical, and the distensible glottic aperture (vocal cords) represents the narrowest cross-sectional dimension.
- Ultra-Thin Polyurethane Micro-Cuffs: Modern pediatric ETTs feature high-volume, low-pressure (HVLP) polyurethane membranes ($10\ \mu\text{m}$ thickness vs. traditional $50\ \mu\text{m}$ PVC). When inflated to low sealing pressures ($15-20\text{ cmH}_2\text{O}$), they conform intimately to the elliptical pediatric subglottis without generating localized focal point pressures exceeding mucosal capillary perfusion pressure.
- Clinical Benefits:
- Substantial reduction in operating room and ICU tube-exchange rates due to excessive peritubular air leak (decreasing repeated airway instrumentation trauma).
- Reliable capnography ($P_{\text{etCO}_2}$) waveforms and precise delivered tidal volume ($V_T$) monitoring during low-flow lung-protective ventilation.
- Significant reduction in the microaspiration of contaminated subglottic secretions into the lower respiratory tract.
C. Cuff Pressure Titration and Mucosal Perfusion
The tracheal mucosal capillary perfusion pressure normally ranges between $25\text{ mmHg}$ and $35\text{ mmHg}$ (equivalent to approximately $34-47\text{ cmH}_2\text{O}$). To maintain an impermeable seal against pharyngeal aspiration while preserving microvascular perfusion:
$$\mathbf{\text{Target Cuff Pressure Range: } 20 - 30\text{ cmH}_2\text{O} \quad (15 - 22\text{ mmHg})}$$ Cuff Pressure Spectrum & Clinical Consequences
< 20 cmH2O 20 - 30 cmH2O > 30 cmH2O
──────┬───────────────────────────────┼────────────────────────────────┬──────
│ ZONE OF ASPIRATION │ THERAPEUTIC WINDOW │ ZONE OF ISCHEMIA
│ • Microaspiration of saliva │ • Complete gas seal │ • Capillary perfusion arrest
│ • Ventilator leak / hypovent │ • Mucosal blood flow intact │ • Mucosal necrosis & ulceration
│ • High VAP incidence │ • Low VAP risk │ • Tracheomalacia & stenosis
│ │ │ • Tracheoesophageal fistula
- Under-inflation ($< 20\text{ cmH}_2\text{O}$): Longitudinal folds form along the deflated cuff wall, creating micro-channels that permit silent microaspiration of contaminated secretions pooled in the subglottic space, precipitating Ventilator-Associated Pneumonia (VAP).
- Over-inflation ($> 30\text{ cmH}_2\text{O}$): Compression of mucosal arterioles leads to tissue ischemia, loss of ciliary architecture, transmural cartilaginous necrosis, tracheomalacia, post-extubation tracheal stenosis, and fatal tracheo-esophageal or tracheo-innominate fistulae.
- Bedside Monitoring Protocol: Cuff pressures MUST be measured objectively using a calibrated aneroid or digital manometer at least every 8–12 hours and after any change in patient positioning (prone positioning, head rotation, or bed elevation adjustments). Digital palpation of the pilot balloon is notoriously inaccurate, misjudging unsafe cuff hyperinflation in over $60\%$ of clinical assessments.
2. Airway Fluid Mechanics & Imposed Work of Breathing
A. Poiseuille's Law and Cross-Sectional Geometry
Laminar gas flow through a cylindrical conduit is governed by the Hagen-Poiseuille equation:
$$\Delta P = \frac{8 \eta L \dot{V}}{\pi r^4} \implies R_{\text{airway}} = \frac{\Delta P}{\dot{V}} = \frac{8 \eta L}{\pi r^4}$$Where:
- $\eta = \text{dynamic gas viscosity}$
- $L = \text{length of the artificial airway}$
- $r = \text{internal radius of the tube } (r = \text{ID}/2)$
- $\dot{V} = \text{gas flow rate}$
       Effect of Internal Diameter on Airway Resistance (Relative Multipliers)
  16x ┌──────────────────────────────────────────────────────────┐
      │                                                         *│ (ID = 4.0 mm)
  12x │                                                          │
      │                                                          │
   8x │                                                          │
      │                                                 *        │ (ID = 6.0 mm)
   4x │                                                          │
      │                                         *                │ (ID = 7.0 mm)
   1x │                         *               │                │ (ID = 8.0 mm)
   0x └─────────────────────────┴───────────────┴────────────────┴
                              8.0 mm          7.0 mm           4.0 mm
Because flow resistance is inversely proportional to the fourth power of the internal radius ($R \propto 1/r^4$), reducing the tube diameter by just $16\%$ (e.g., from an $8.0\text{ mm}$ to a $7.0\text{ mm}$ ETT) nearly doubles airway resistance ($1.7\times$). Furthermore, halving the radius increases resistance by $16\text{-fold}$ ($2^4 = 16$).
Under turbulent flow conditions—frequently encountered during peak inspiratory efforts and high patient flow demands—the pressure drop transitions to the Rohrer equation ($\Delta P = K_1 \dot{V} + K_2 \dot{V}^2$), amplifying the resistive work exponentially.
B. Imposed Work of Breathing ($WOB_{\text{imp}}$) & Tube Compensation
When an intubated patient breathes spontaneously during a Spontaneous Breathing Trial (SBT) or Pressure Support Ventilation (PSV), the presence of the ETT introduces an unnatural resistive load:
$$WOB_{\text{total}} = WOB_{\text{physiologic}} + WOB_{\text{imposed}}$$- Imposed Work of Breathing ($WOB_{\text{imp}}$): The mechanical energy expended solely to overcome the flow resistance of the ETT, connector adapter, and ventilator circuit valves. In an undersized ($6.5-7.0\text{ mm}$) or partially crusted ETT, $WOB_{\text{imp}}$ can account for up to $40-50\%$ of the patient's total respiratory work, mimicking diaphragm fatigue and precipitating false-positive SBT failures.
- Automatic Tube Compensation (ATC): An advanced closed-loop ventilation mode that continuously calculates the instantaneous pressure drop across the ETT ($\Delta P = K_1 \dot{V} + K_2 \dot{V}^2$) and delivers proportional positive pressure during inspiration and negative baseline offset during exhalation, effectively "canceling" the tube's resistive burden at the tracheal level ($P_{\text{carina}} = \text{Set PEEP}$).
- Low-Level Pressure Support ($5-8\text{ cmH}_2\text{O}$): Routinely applied during SBTs as an empirical alternative to ATC to overcome the resistive impedance of an $7.5-8.0\text{ mm}$ ETT.
C. Continuous Subglottic Suctioning (CASS) Tubes
Endotracheal tubes equipped with a dorsal subglottic evacuation lumen located immediately superior to the cuff allow continuous or intermittent evacuation of secretions pooling in the subglottic space.
       Standard ETT vs. Continuous Subglottic Suctioning (CASS) ETT
           Standard ETT                          CASS ETT
        ┌────────────────┐                  ┌────────────────┐
        │ 15mm Connector │                  │ 15mm Connector │
        └───┬────────┬───┘                  └───┬────────┬───┘
            │        │                          │ ┌────┐ │
            │        │                          │ │CASS│ │ (Suction Port)
            │        │                          │ └─┬──┘ │
            │        │                          │   │    │
            │  Main  │                          │   │    │
            │  Shaft │                          │   │    │
            │        │                     ─────┼─( • )──┼─────  Above Cuff)
         ───┴────────┴───                  ┌────┴────────┴────┐
        (      Cuff      )                 (       Cuff       )
         ───┬────────┬───                  └────┬────────┬────┘
            │ Bevel  │                          │ Bevel  │
            └────────┘                          └────────┘
- Mechanism of Action: Eliminates the static reservoir of contaminated oropharyngeal secretions that inevitably leaks past cuff micro-folds during swallowing, patient movement, and respiratory cycle pressure swings.
- Clinical Impact: Multiple meta-analyses demonstrate that dedicated CASS tubes reduce the relative risk of Ventilator-Associated Pneumonia by $45-50\%$, decrease total mechanical ventilation duration by $1.5-2\text{ days}$, and shorten ICU length of stay in patients ventilated for $> 48-72\text{ hours}$.
- Suction Parameters: Intermittent low-pressure vacuum ($-80\text{ to } -120\text{ mmHg}$, $15\text{ seconds}$ on / $15\text{ seconds}$ off) or low-level continuous suction ($-20\text{ to } -30\text{ mmHg}$) with periodic $2-5\text{ mL}$ air flushes to prevent mucosal invagination into the suction eye.
3. Tracheostomy: Sizing, Timing, and Decannulation
A. Anatomy and Tube Architecture
A tracheostomy provides a direct surgical or percutaneous conduit into the cervical trachea (typically between the 2nd and 3rd tracheal rings), eliminating translaryngeal vocal cord contact, bypassing the upper airway dead space, and decreasing airway resistance by shortening the tube length ($L$).
                      Tracheostomy Tube Configurations
      Cuffed Fenestrated                         Cuffed Non-Fenestrated
        ┌─────────────┐                            ┌─────────────┐
        │15mm Machine │                            │15mm Machine │
        │  Connector  │                            │  Connector  │
        └───┬─────┬───┘                            └───┬─────┬───┘
            │     │                                    │     │
       ─────┴─────┴─────                          ─────┴─────┴─────
     [   Neck Flange    ]                       [   Neck Flange    ]
       ─────┬─────┬─────                          ─────┬─────┬─────
            │  *  │ (Fenestration Holes)               │     │
         ───┴─────┴───                              ───┴─────┴───
        (    Cuff     )                            (    Cuff     )
         ───┬─────┬───                              ───┬─────┬───
            │ Tip │                                    │ Tip │
            └─────┘                                    └─────┘
Classification of Tracheostomy Tubes
- Cuffed vs. Uncuffed:
- Cuffed: Mandatory during acute respiratory failure, positive pressure mechanical ventilation, and high aspiration risk to maintain an effective tidal volume seal.
- Uncuffed: Used in long-term stable patients without positive pressure requirements who have intact protective airway reflexes and are undergoing vocal rehabilitation.
- Dual-Cannula vs. Single-Cannula:
- Dual-Cannula (Inner + Outer Cannula): Standard in the ICU. The removable inner cannula can be unlocked, cleaned, and replaced instantly in the event of acute mucus crusting without risking stomal decannulation or tube exchange.
- Single-Cannula: Provides a larger internal lumen for a given outer diameter; common in pediatric patients where dual-cannula wall thickness would excessively compromise the lumen.
- Fenestrated Tubes:
- Feature multiple openings (fenestrations) on the posterior curvature of the outer cannula.
- When the non-fenestrated inner cannula is removed, the cuff is deflated, and the proximal opening is occluded, air diverts cephalad across the vocal cords and subglottis during exhalation, enabling phonation.
- Safety Caveat: NEVER apply positive-pressure ventilation with a fenestrated inner cannula in place; the gas will leak into the pretracheal soft tissues, causing massive subcutaneous emphysema and hypoventilation.
B. Speaking Valves (Passy-Muir Valve / PMV)
The Passy-Muir valve is a one-way, bias-closed silicone diaphragm placed on the $15\text{-mm}$ hub of a tracheostomy tube.
       Passy-Muir One-Way Valve (PMV) Inhalation vs. Exhalation Dynamics
              INHALATION                                  EXHALATION
       (Diaphragm Opens Inward)                    (Diaphragm Snaps Closed)
           Ambient Air / O2                               Exhalation Blocked
                 │││                                             ▲▲▲
                 ▼▼▼                                             XXX
            ┌───────────┐                                   ┌───────────┐
            │\  PMV    /│                                   │─── PMV ───│ (Closed)
            └─┐       ┌─┘                                   └─┐       ┌─┘
              │       │                                       │       │
              │       │                                       │   ▲   │
              │       │                                       │   │   │
              │       │                                       │   │   │
        ──────┴───────┴──────                           ──────┴───│───┴──────
       [     Trachea         ]                         [      Trachea        ]
              │       │                                       │   │   │
              ▼       ▼                                       └───┼───┘
         Lungs Inflate                                            │
                                                        Air Diverts Cephalad
                                                        Past Deflated Cuff
                                                        Through Vocal Cords
                                                        (Phonation & Cough)
ABSOLUTE RULE FOR PASSY-MUIR VALVE APPLICATION: The tracheostomy cuff MUST BE $100\%$ DEFLATED prior to placing a one-way speaking valve. If the cuff remains inflated, the patient can inhale through the one-way valve but cannot exhale through the occluded upper airway, leading to dynamic hyperinflation, catastrophic tension pneumothorax, and rapid cardiovascular collapse.
Physiological and Clinical Benefits of PMV Placement
- Restoration of Subglottic Airway Pressure: Normalizes positive subglottic pressure during the swallow ($+8\text{ to }+10\text{ cmH}_2\text{O}$), reducing laryngeal penetration and silent aspiration.
- Phonation and Communication: Enables audible speech, dramatically improving patient psychological well-being and interaction with clinical staff.
- Restoration of Olfaction & Taste: Cephalad airflow through the pharynx and nasal cavity reactivates olfactory receptors.
- Improved Secretion Clearance: Restores the ability to generate explosive expiratory flows for effective glottic coughing.
C. Timing of Tracheostomy: Evidence from Landmark Trials
Determining the ideal timing of tracheostomy in critically ill patients requiring prolonged mechanical ventilation has been extensively investigated.
         Tracheostomy Timing Paradigm & Landmark Clinical Evidence
 ┌─────────────────────────────────────────────────────────────────────────────┐
 │                         CRITICAL ILLNESS TIMELINE                           │
 │ Day 0          Day 4           Day 7           Day 10             Day 14+   │
 └─┬───────────────┬───────────────┬───────────────┬───────────────────┬───────┘
   │               │               │               │                   │
   ▼               ▼               ▼               ▼                   ▼
Intubation    "Early" Window    "Intermediate"   "Late" Tracheostomy  Prolonged
              (TracMan Trial)    Consensus Point   (TracMan Window)    Intubation
1. The TracMan Randomized Controlled Trial (Young et al., BMJ 2013)
- Study Design: Multicenter trial randomizing 909 adult ICU patients to Early Tracheostomy (within Day 1–4) versus Late Tracheostomy (after Day 10).
- Primary Outcome: 30-day all-cause mortality showed NO statistically significant difference between the early group ($30.8\%$) and late group ($31.5\%$).
- Secondary Outcomes: No significant difference in ICU length of stay or 2-year survival. Crucially, in the late group, $45\%$ of patients successfully extubated prior to day 10, avoiding a surgical procedure altogether.
2. The SETPOINT2 Trial (Bösel et al., JAMA 2022)
- Investigated severe stroke/neurocritical care patients randomized to early ($\le \text{Day 5}$) vs. standard (Day 10–14) tracheostomy.
- Demonstrated no significant difference in 6-month functional neurological outcome (modified Rankin Scale 0–4) or mortality.
3. Modern Clinical Consensus Guidelines
- Severe Traumatic Brain Injury (GCS $\le 8$), Complete Quadriplegia, or Massive Maxillofacial Trauma: Early tracheostomy (Day 3–5) is indicated given the near-certain requirement for protracted mechanical ventilation and airway protection.
- General Medical/Surgical ICU Patients (Sepsis, ARDS, Heart Failure): Daily assessment of extubation trajectory. If liberation is unachievable and mechanical ventilation is anticipated to exceed 14 days, perform elective percutaneous dilatational tracheostomy (PDT) between Day 7 and Day 10.
D. Bedside Decannulation Protocol & Readiness Criteria
Decannulation is the planned permanent removal of the tracheostomy cannula once the underlying respiratory failure and airway compromise have resolved.
                 Structured ICU Decannulation Flowchart
 ┌─────────────────────────────────────────────────────────────────────────────┐
 │                       Decannulation Readiness Screen                        │
 │ • Primary pathology resolved        • Tolerating PMV / Cap > 24-48 hours    │
 │ • Hemodynamically stable            • FiO2 < 0.40, PEEP <= 5 cmH2O          │
 │ • Intact alert sensorium (GCS >= 10)• Peak Cough Flow > 160 L/min           │
 └──────────────────────────────────────┬──────────────────────────────────────┘
                                        │
                                        ▼
 ┌─────────────────────────────────────────────────────────────────────────────┐
 │                        Positive Cuff-Leak Evaluation                        │
 │ Deflate cuff & occlude tube: audible peritubular airflow & exhaled VT > 15% │
 └──────────────────────────────────────┬──────────────────────────────────────┘
                                        │
                                        ▼
 ┌─────────────────────────────────────────────────────────────────────────────┐
 │                     Downsizing & Continuous Capping Trial                   │
 │ Downsize to size 4-6 uncuffed tube; continuous capping for 24-48 hours       │
 │ Monitor: RR < 25, SpO2 > 92%, no stridor, no respiratory distress           │
 └──────────────────────────────────────┬──────────────────────────────────────┘
                                        │
                                        ▼
 ┌─────────────────────────────────────────────────────────────────────────────┐
 │                         Removal & Stomal Occlusion                          │
 │ Remove cannula, apply sterile occlusive dressing, monitor for 24 hours      │
 └─────────────────────────────────────────────────────────────────────────────┘
Step-by-Step Clinical Decannulation Protocol
- Clinical Readiness Criteria:
- Resolution of acute respiratory failure: $\text{FiO}_2 \le 0.40$, $\text{PEEP} \le 5\text{ cmH}_2\text{O}$, minute ventilation $\le 10\text{ L/min}$.
- Neurological adequacy: Patient awake, cooperative, following commands ($\text{GCS} \ge 10-11$), with an active swallow and gag reflex.
- Secretion control: Minimal suctioning requirements ($\le 2$ times per 8-hour nursing shift), thin consistency.
- Effective cough strength: Peak Cough Expiratory Flow ($PCEF$) measured with a peak flow meter $\ge 160\text{ L/min}$ (or maximum expiratory pressure $MEP > 40\text{ cmH}_2\text{O}$).
- Cuff Leak Assessment:
- Suction oral secretions, deflate the cuff completely, and occlude the proximal tube hub with a gloved finger.
- Confirm adequate peritubular air passage during exhalation without stridor or dyspnea.
- Downsizing & Capping Challenge:
- Downsize large cannulas (e.g., Size 8 or 7) to a smaller Size 4 or 6 uncuffed tube to minimize translaryngeal flow resistance around the cannula.
- Apply a solid tracheostomy cap for a continuous 24 to 48-hour challenge (including overnight sleep).
- Decannulation & Post-Care:
- Place patient in semi-Fowler position ($30-45^\circ$).
- Suction stoma and trachea thoroughly.
- Cut stay sutures/retaining bands, smoothly extract the tube during deep inspiration.
- Cover stoma with sterile gauze and an airtight occlusive dressing; instruct patient to press against the dressing with fingers during coughing or speaking to prevent subcutaneous air tracking until the stoma seals secondarily within 48–72 hours.
4. Medical Gas Conditioning and Humidification
During spontaneous non-intubated breathing, the nasal turbinates and upper pharynx warm and humidify ambient air so that upon reaching the Isothermic Saturation Boundary (ISB)—normally located $5\text{ cm}$ distal to the carina—the gas is fully conditioned to core body conditions:
$$\text{Body Temperature and Pressure, Saturated (BTPS)}: \mathbf{37^\circ\text{C}, \quad 100\% \text{ Relative Humidity}, \quad \text{Absolute Humidity } (AH) = 44\text{ mg H}_2\text{O/L}}$$ The Isothermic Saturation Boundary
Upper Airway (Intact) Artificial Airway (Bypassed)
Ambient Air: 21°C, 50% RH Dry Medical Gas: 15-20°C, 0% RH
│ │
(Nose / Pharynx) (ETT / Trach)
│ │
ISB Normal: 5 cm below Carina ISB Shifts Deep into Lung Periphery!
[37°C, 100% RH, 44 mg/L] • Mucociliary clearance arrest
• Inspissation & mucus plugs
• Atelectasis & bacterial invasion
When an artificial airway bypasses the nasopharynx, dry, cold medical gases (relative humidity $0\%$, $AH < 5\text{ mg/L}$) enter the lower tracheobronchial tree directly. Without adequate artificial humidification, the ISB shifts distally into secondary and tertiary bronchioles, causing mucosal drying, cessation of ciliary beat frequency, epithelial ulceration, inspissated mucus plugging, and acute tube occlusion.
A. Heat and Moisture Exchangers (HME / "Artificial Nose")
HMEs are passive conditioning devices fitted between the ETT hub and the ventilator Y-piece.
       HME (Passive "Artificial Nose") Internal Construction & Mechanism
                        Ventilator Wye Connector (Machine Side)
                                      │
                         ┌────────────┴────────────┐
                         │   Bacterial/Viral Foam  │
                         ├─────────────────────────┤
                         │ Hygroscopic Salt Layer  │  Exhalation: Captures Heat & H2O
                         │   (Calcium Chloride)    │  Inhalation: Releases Heat & H2O
                         ├─────────────────────────┤
                         │  Particulate Filter     │
                         └────────────┬────────────┘
                                      │
                            Patient ETT Connector
1. Mechanism of Action
- Exhalation Phase: Warm, fully saturated expired gas ($37^\circ\text{C}, 44\text{ mg/L}$) enters the HME. As it cools across the internal hygroscopic matrix (typically polyurethane foam coated with hygroscopic calcium chloride $\text{CaCl}_2$ or lithium chloride), water vapor condenses and latent thermal energy is absorbed by the element.
- Inhalation Phase: Cold, dry ventilator gas absorbs the stored heat and evaporates the condensed water vapor from the matrix, returning conditioned gas ($30-32^\circ\text{C}$, $AH \ge 30\text{ mg/L}$) to the patient.
2. Physiological Dead Space Penalty ($V_{D,\text{HME}}$)
- HMEs possess an internal physical housing volume of $50\text{ to }100\text{ mL}$.
- Because the HME is situated proximal to the Y-piece, this entire volume constitutes instrumental apparatus dead space ($V_D$).
- In a patient ventilated with an ultra-lung-protective tidal volume ($V_T = 300-360\text{ mL}$ for ARDS at $6\text{ mL/kg}$ PBW), an HME adds a dead space fraction ($V_D / V_T$) of $20-30\%$, precipitating severe respiratory acidosis, hypercapnia, and secondary respiratory drive amplification.
                  Apparatus Dead Space Comparison
       Active Heated Wire Circuit                       Passive HME Circuit
       ┌──────┐          ┌──────┐              ┌──────┐          ┌──────┐
       │ Insp │          │ Exp  │              │ Insp │          │ Exp  │
       └──┬───┘          └──┬───┘              └──┬───┘          └──┬───┘
          │                 │                     │                 │
          └────────┬────────┘                     └────────┬────────┘
                   │                                       │
              [ Wye Piece ]                           [ Wye Piece ]
                   │                                       │
                   │ (Minimal VD ~ 5-10 mL)           [ HME Filter ] (VD ~ 50-100 mL!)
                   │                                       │
             [ Patient ETT ]                         [ Patient ETT ]
3. Contraindications to HME Use
- Copious, thick, or bloody secretions: High risk of rapidly coating and occluding the hygroscopic filter, causing critical airway obstruction and catastrophic intrinsic PEEP.
- Low tidal volume lung-protective ventilation in ARDS: Elimination of apparatus dead space is required to manage refractory hypercapnic acidosis.
- Severe hypothermia (Core Temp $< 32^\circ\text{C}$): Exhaled heat is insufficient to charge the hygroscopic matrix.
- Large peritubular air leaks (uncuffed tubes or bronchopleural fistulae): Expired volume $< 70\%$ of inspired volume prevents adequate thermal/moisture recharging.
- Minute ventilation $> 15\text{ L/min}$: High inspiratory flows exceed the moisture recapture efficiency of the matrix.
B. Heated Humidifiers (HH / Active Heated-Wire Systems)
Active heated humidifiers utilize a temperature-controlled water bath and dual heated-wire inspiratory/expiratory circuits to condition inspired gases actively.
       Active Dual-Heated Wire Humidification Circuit Architecture
                   Ventilator Output (Dry Gas)
                               │
                               ▼
                   ┌───────────────────────┐
                   │  Water Chamber Base   │ (Heated to 37°C)
                   └───────────┬───────────┘
                               │ (37°C, 100% RH, AH = 44 mg/L)
                               │
             ┌─────────────────┴─────────────────┐
             │ Inspiratory Heated Wire Circuit   │ (Maintains T = 39°C along limb)
             └─────────────────┬─────────────────┘
                               ▼
                           Wye Piece (Temp Probe: 37°C)
                               │
                               ▼
                          Patient ETT
1. Performance and Targets
- Core Goals: Deliver inspired gas at $37^\circ\text{C}$ at the patient Y-piece with $100\%$ relative humidity, achieving an Absolute Humidity of $44\text{ mg H}_2\text{O/L}$ (meeting full BTPS physiological specifications).
- Minimum AARC Guideline Standard: Active humidifiers MUST deliver at least $33\text{ mg H}_2\text{O/L}$ of absolute humidity.
2. Dual-Heated Wire Circuits and Rainout Management
- The Problem of Circuit Condensation ("Rainout"): When warm, saturated gas passes through an unheated ventilator circuit exposed to cool ambient ICU air ($21-23^\circ\text{C}$), the gas temperature drops. As gas cools, its water-holding capacity falls ($AH_{\text{max}}$ at $22^\circ\text{C} \approx 19\text{ mg/L}$), causing excess water vapor to condense into liquid droplets within the tubing.
- Clinical Hazards of Rainout:
- Ventilator Autotriggering: Fluid sloshing across flow sensors generates flow oscillations that trigger false ventilator breaths.
- Accidental Lavage: Mobilizing the circuit can flush pooled, non-sterile condensation directly into the patient's lower airways.
- Circuit Resistance Spikes: Liquid occluding circuit corrugations markedly increases inspiratory and expiratory resistance.
- Engineering Solution (Dual Heated-Wire System): Electrical heating wires embedded within both inspiratory and expiratory limbs maintain a slight positive temperature gradient ($+1\text{ to }+2^\circ\text{C}$ above chamber temperature along the tubing length), keeping water in vapor phase until it reaches the patient interface, thereby eliminating rainout without requiring water traps.
C. Head-to-Head Comparison: HME vs. Heated Humidifiers
| Clinical Feature | Heat & Moisture Exchanger (HME) | Active Heated Humidifier (HH) |
|---|---|---|
| Operating Mechanism | Passive moisture/heat recapture from exhaled breath | Active external heating base and water reservoir |
| Delivered Absolute Humidity | $30 - 33\text{ mg H}_2\text{O/L}$ ($70 - 80\%$ BTPS) | $\mathbf{44\text{ mg H}_2\text{O/L}}$ ($100\%$ BTPS) |
| Delivered Temperature | $29 - 32^\circ\text{C}$ | $\mathbf{37^\circ\text{C}}$ |
| Apparatus Dead Space ($V_D$) | $+50\text{ to }100\text{ mL}$ added dead space | Zero added instrumental dead space |
| Airway Resistance Impact | Adds $1 - 3\text{ cmH}_2\text{O/L/s}$; spikes if wet | Minimal baseline circuit resistance |
| Circuit Rainout Risk | Negligible | Low with heated wire; High with non-heated wire |
| VAP Incidence Difference | Equivalent in large RCTs ($\text{RR } \approx 1.0$) | Equivalent in large RCTs ($\text{RR } \approx 1.0$) |
| Primary ICU Indications | Routine, uncomplicated MV ($< 48-72\text{ h}$); Transport | ARDS, severe asthma/COPD, thick secretions, hypothermia |
| Replacement Frequency | Every 48–72 hours (or immediately if soiled) | Circuit changed only per patient / hospital infection policy |
5. Comprehensive Clinical Management & Protocol Summary
                      Airway & Gas Conditioning Checklist
 ┌─────────────────────────────────────────────────────────────────────────────┐
 │ Endotracheal Tube Management                                                │
 │ [ ] Sized appropriately: Adult F (7.0-7.5), Adult M (7.5-8.0)               │
 │ [ ] Insertion depth verified at incisors/lip and confirmed on chest X-ray   │
 │ [ ] Continuous subglottic suctioning active (-80 to -120 mmHg intermittent) │
 │ [ ] Cuff pressure titrated to 20-30 cmH2O with calibrated manometer q8h     │
 ├─────────────────────────────────────────────────────────────────────────────┤
 │ Humidification Protocol                                                     │
 │ [ ] ARDS / Low Vt / Copious Secretions -> Dual-Heated Wire Active Humidifier│
 │ [ ] Routine short-term ventilation -> HME (Monitor for clogging/PCO2 rises) │
 │ [ ] Target core gas temp: 37°C, 100% RH (AH >= 33-44 mg/L)                  │
 ├─────────────────────────────────────────────────────────────────────────────┤
 │ Tracheostomy & Liberation Pathway                                           │
 │ [ ] Elective tracheostomy evaluated between Day 7-10 for prolonged MV       │
 │ [ ] Inner cannula inspected and cleaned every shift                         │
 │ [ ] Passy-Muir Valve ONLY placed after 100% CUFF DEFLATION                  │
 │ [ ] Structured decannulation: leak test -> downsize -> 24-48h cap -> remove │
 └─────────────────────────────────────────────────────────────────────────────┘
- Airway Geometry & Physics: Always select the largest ETT compatible with patient anatomy to minimize resistive work of breathing ($R \propto 1/r^4$), while respecting subglottic boundaries.
- Cuff Pressure Precision: Maintain cuff pressure strictly within $20-30\text{ cmH}_2\text{O}$ to balance microaspiration prevention against mucosal ischemia. Palpation of the pilot balloon is unacceptably inaccurate.
- VAP Prophylaxis: Utilize subglottic suctioning endotracheal tubes in patients expected to remain ventilated $> 48-72\text{ hours}$ to reduce VAP incidence by nearly $50\%$.
- Humidification Strategy: Employ active heated humidifiers in ARDS, severe airway obstruction, and hypothermia to avoid the $50-100\text{ mL}$ dead space penalty and occlusion risks of HMEs.
- Tracheostomy Practice: Avoid early routine tracheostomy ($< \text{Day 4}$) in unselected medical patients; re-evaluate between Days 7–10. Ensure complete cuff deflation prior to speaking valve placement, and adhere to a structured downsizing and capping protocol prior to decannulation.