Mechanical ventilation liberation represents one of the most critical transitions in intensive care medicine. Approximately $40\%$ to $50\%$ of the total duration of mechanical ventilation is dedicated to the process of weaning—the systematic transition from total ventilatory support to unassisted spontaneous breathing. Delayed liberation exposes patients to the progressive risks of ventilator-associated pneumonia (VAP), ventilator-induced diaphragmatic dysfunction (VIDD), tracheobronchial injury, delirium, and increased intensive care unit (ICU) and hospital mortality. Conversely, premature extubation resulting in extubation failure—defined as the requirement for reintubation within $48$ to $72\text{ hours}$—is an independent predictor of adverse outcomes, carrying an attributable mortality rate of $25\%$ to $50\%$, extended hospital length of stay, and frequent tracheostomy placement. To optimize liberation outcomes, critical care practice relies on evidence-based consensus definitions, rigorous daily readiness screening, standardized spontaneous breathing trials (SBTs), advanced physiological and sonographic predictors of weaning success, and targeted post-extubation noninvasive respiratory support strategies.
The ERS/ATS/CHEST Weaning Classification Taxonomy
The European Respiratory Society (ERS), American Thoracic Society (ATS), and American College of Chest Physicians (CHEST) consensus statement categorizes mechanically ventilated patients into three mutually exclusive, prognostically distinct weaning groups based on the difficulty, duration, and trajectory of the liberation process:
                      +----------------------------------------+
                      |    Daily Readiness Screening Passed    |
                      +-------------------+--------------------+
                                          |
                                          v
                      +----------------------------------------+
                      |    Spontaneous Breathing Trial (SBT)   |
                      +-------------------+--------------------+
                                          |
         +--------------------------------+--------------------------------+
         | (Passed SBT 1)                 | (Failed initial SBT)           | (Failed >= 3 SBTs or
         v                                v                                |  > 7 days weaning)
+-----------------+             +-------------------+                      v
| Simple Weaning  |             | Difficult Weaning |            +-------------------+
| * Extubated on  |             | * Successfully    |            | Prolonged Weaning |
|   first attempt |             |   weaned within   |            | * Requires > 7 d  |
| * Low mortality |             |   up to 3 SBTs or |            |   or >= 3 SBTs    |
|   (~5%)         |             |   <= 7 days       |            | * High mortality  |
+-----------------+             +-------------------+            |   (up to 25-30%)  |
                                                                 +-------------------+
| Weaning Category | Diagnostic Definition | Clinical Characteristics & Trajectory | Estimated ICU Mortality |
|---|---|---|---|
| Group 1: Simple Weaning | Patients who proceed from the initial readiness screening through a successful first Spontaneous Breathing Trial (SBT) and achieve sustained extubation on the first attempt without difficulty. | Represents $\sim 55-65\%$ of the general medical-surgical ICU population. Rapid recovery of baseline respiratory mechanics and neuromuscular drive. | Lowest mortality ($\sim 3-5\%$). Short ICU length of stay. |
| Group 2: Difficult Weaning | Patients who fail the initial SBT and require up to 3 consecutive SBTs or up to 7 calendar days from the first failed SBT to achieve successful liberation and extubation. | Represents $\sim 25-30\%$ of mechanically ventilated patients. Commonly driven by reversible residual pathology (e.g., dynamic hyperinflation, mild fluid overload, delayed clearance of sedatives, critical illness weakness). | Intermediate mortality ($\sim 10-15\%$). Moderate ICU length of stay. |
| Group 3: Prolonged Weaning | Patients who fail $\ge 3$ consecutive SBTs or require $> 7$ calendar days of specialized weaning after the first failed SBT. | Represents $\sim 10-15\%$ of long-term mechanically ventilated patients. Often complicated by severe VIDD, critical illness polyneuromyopathy (CIPNM), severe chronic obstructive pulmonary disease (COPD), structural chest wall deformities, or irreversible parenchymal damage; frequently prompts tracheostomy. | Highest mortality ($\sim 25-30\%$ in ICU; up to $40-50\%$ at 1 year). Prolonged hospital stay and high transfer rate to long-term acute care facilities (LTACH). |
Standardized Readiness for Weaning Criteria
Liberation protocols begin with a structured Daily Readiness Screening performed every morning upon cessation or lightening of continuous sedation. Initiating weaning screening requires the objective resolution or substantial improvement of the primary precipitating etiology of acute respiratory failure, alongside fulfillment of four core physiological criteria:
                             DAILY READINESS SCREEN
                                       |
     +------------------+--------------+-----+------------------+
     v                  v                    v                  v
[ Clinical/Etiology ] [ Gas Exchange ]     [ Hemodynamics ]   [ Neuromuscular/CNS ]
* Primary cause       * P/F >= 150-200     * No/low pressors  * RASS -1 to +1
  resolved/resolving  * PEEP <= 5-8 cmH2O  * MAP >= 65 mmHg   * Intact cough
* No pending major    * FiO2 <= 0.40-0.50  * HR < 120-140 bpm * No continuous
  procedures/surgery  * pH >= 7.30-7.35    * No active ischemia neuromuscular blockade
1. Pulmonary Gas Exchange Stability
- Oxygenation Index: Ratio of arterial partial pressure of oxygen to fraction of inspired oxygen ($\text{PaO}_2 / \text{FiO}_2$ or $P/F$ ratio) $\ge 150 - 200\text{ mmHg}$.
- Positive End-Expiratory Pressure ($\text{PEEP}$): $\text{PEEP} \le 5 - 8\text{ cmH}_2\text{O}$.
- Fraction of Inspired Oxygen ($\text{FiO}_2$): $\text{FiO}_2 \le 0.40 - 0.50$.
- Acid-Base Homeostasis: Arterial $\text{pH} \ge 7.30 - 7.35$ with stable or resolving alveolar ventilation (absence of severe acute uncompensated respiratory acidosis or metabolic alkalosis).
2. Hemodynamic & Cardiovascular Stability
- Vasopressor / Inotrope Burden: Absence of active myocardial ischemia, clinically significant refractory dysrhythmias, or unresuscitated shock. Patient must be maintained on no vasopressors or low-dose stable vasopressors: $$\text{Norepinephrine} \le 0.05 - 0.10\ \mu\text{g/kg/min}\quad \text{or}\quad \text{Dopamine} \le 5\ \mu\text{g/kg/min}$$
- Systemic Perfusion: Mean Arterial Pressure ($\text{MAP}$) $\ge 65\text{ mmHg}$ and resting Heart Rate ($\text{HR}$) between $60$ and $120 - 140\text{ beats/min}$.
3. Neurological Status & Mental Alertness
- Consciousness: Richmond Agitation-Sedation Scale (RASS) score between $-1$ (drowsy, sustained eye contact to voice $>10\text{ s}$) and $0$ (alert and calm) or $+1$ (mildly anxious).
- Command Following: Ability to open eyes, track examiner, squeeze hand, or stick out tongue on command (aids in post-extubation airway protection, though not strictly mandatory for spontaneous breathing capacity in all neurocritical care cohorts).
- Neuromuscular Blockade: Complete recovery from neuromuscular blocking agents (Train-of-Four $4/4$ with sustained tetanic response, absence of residual post-paralytic weakness).
4. Respiratory Mechanics & Secretion Burden
- Inspiratory Triggering: Spontaneous initiation of inspiratory efforts capable of triggering the mechanical ventilator.
- Secretions: Manageable pulmonary secretion volume without requirement for tracheal suctioning more frequently than every $2\text{ hours}$.
- Fever & Metabolic Demand: Absence of high fever ($T < 38.5^\circ\text{C}$) to prevent hypercatabolic carbon dioxide production ($\dot{V}\text{CO}_2$) exceeding respiratory pump capacity.
Comprehensive Weaning and Liberation Protocol
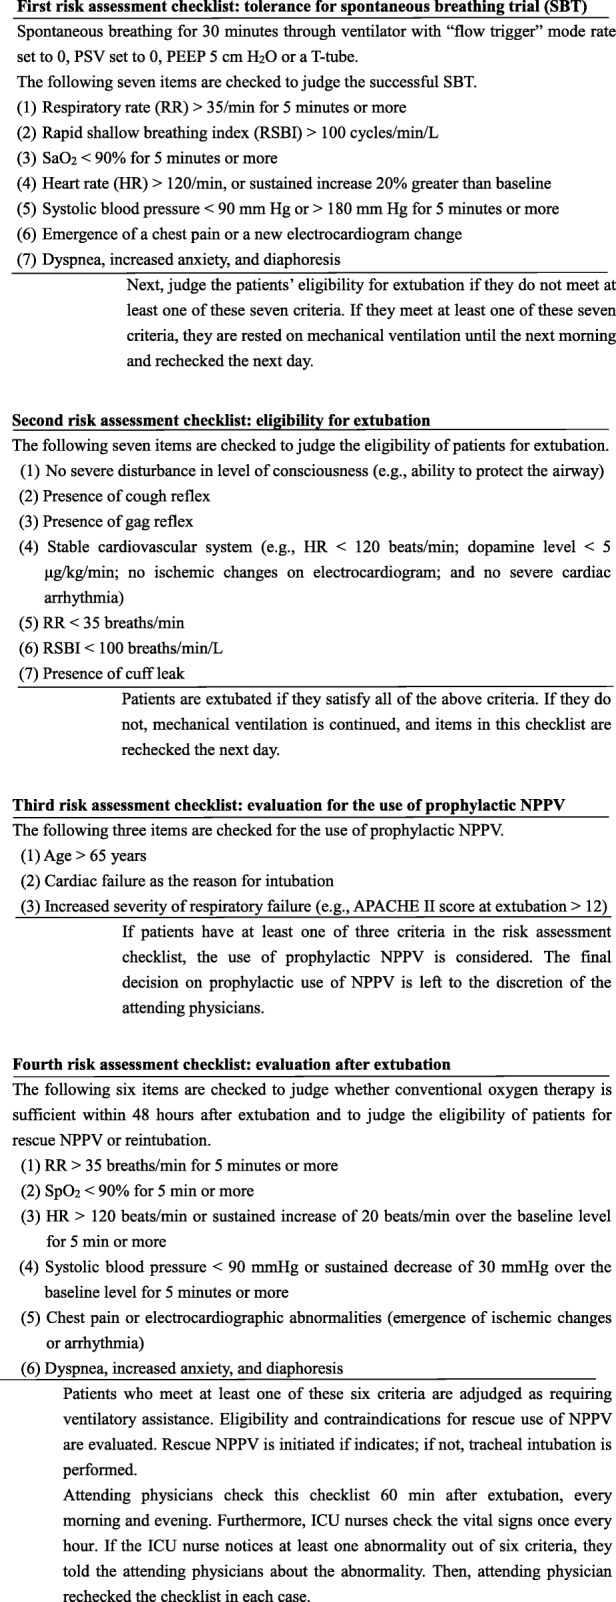 Figure 1: Comprehensive clinical algorithm for mechanical ventilation liberation, demonstrating the sequential workflow from daily readiness screening, spontaneous breathing trial (SBT) execution and objective failure monitoring, airway patency/cuff leak assessment, and risk-stratified post-extubation prophylactic noninvasive respiratory support. Reproduced from Nitta et al., Journal of Intensive Care (2019), DOI: 10.1186/s40560-019-0402-4 under CC-BY 4.0.
The Spontaneous Breathing Trial (SBT)
The Spontaneous Breathing Trial serves as the definitive physiological stress test of the patient's respiratory system and cardiovascular reserve under conditions that simulate unassisted post-extubation breathing.
SBT Techniques: T-Piece vs. Low-Level Pressure Support
For decades, debate centered on whether spontaneous breathing trials should be conducted completely unassisted (via a T-piece circuit or zero pressure support / zero PEEP [PSV 0 / PEEP 0]) or with low-level ventilatory assistance (PSV $5 - 8\text{ cmH}_2\text{O}$ with PEEP $0 - 5\text{ cmH}_2\text{O}$ or Automatic Tube Compensation [ATC]) to overcome the internal resistive work imposed by the endotracheal tube ($W_{\text{tube}}$).
                        SBT TECHNIQUE COMPARISON
                                   |
         +-------------------------+-------------------------+
         v                                                   v
[ T-Piece / PSV 0 + PEEP 0 ]                       [ PSV 5-8 + PEEP 0-5 ]
* True unassisted physiological load               * Overcomes endotracheal tube resistance
* Higher inspiratory work of breathing             * Higher rate of SBT passing
* Excellent specificity for extubation success    * Significantly higher successful extubation rate
* Risk of false-negative SBT failure               * Supported by Subira et al. JAMA 2019 & ATS/CHEST
1. T-Piece / PSV 0 / PEEP 0 (High-Workload Strategy)
- Mechanics: The patient breathes either disconnected from the ventilator on an open T-piece aerosol circuit or connected to the ventilator set to Continuous Positive Airway Pressure (CPAP) $0\text{ cmH}_2\text{O}$ and Pressure Support $0\text{ cmH}_2\text{O}$.
- Physiology: Imposes a higher resistive load than normal post-extubation breathing because of the narrow internal diameter and length of the endotracheal tube (governed by Poiseuille's law, where airway resistance $\Delta P \propto \frac{\dot{V}}{r^4}$).
- Clinical Utility: Offers high specificity; a patient who passes a T-piece SBT has demonstrated unmistakable neuromuscular and cardiorespiratory endurance. However, it exhibits a high false-negative rate, leading to unnecessarily delayed extubation in patients whose diaphragmatic reserve is adequate for extubation but unable to overcome the artificial resistive burden of the tube.
2. Low-Level Pressure Support (PSV 5–8 / PEEP 0–5)
- Mechanics: The patient remains connected to the ventilator circuit with Pressure Support set between $5$ and $8\text{ cmH}_2\text{O}$ (or Automatic Tube Compensation [ATC] at $100\%$) and PEEP set between $0$ and $5\text{ cmH}_2\text{O}$.
- Physiology: The applied $5 - 8\text{ cmH}_2\text{O}$ of inspiratory pressure closely offsets the imposed resistive work of the artificial airway without unloading the native work of breathing of the respiratory muscles.
- Evidence Base (The Subira et al. JAMA 2019 Trial):
- In a multicenter randomized clinical trial of $1{,}153$ difficult-to-wean and standard ICU patients, Subira and colleagues compared an initial SBT of $30\text{ minutes}$ of low-level PSV ($8\text{ cmH}_2\text{O}$ with PEEP $0\text{ cmH}_2\text{O}$) versus $120\text{ minutes}$ of unassisted T-piece breathing.
- Results: The PSV group demonstrated a significantly higher rate of successful extubation ($82.3\%$ vs. $74.0\%$, difference $8.3\%$, $95\%\text{ CI } 3.4-13.0\%$, $P = 0.001$) and a lower reintubation rate without increasing post-extubation respiratory failure.
- Clinical Consensus: The current ATS/CHEST clinical practice guidelines formally issue a strong recommendation that initial SBTs be conducted using low-level pressure support (PSV $5-8\text{ cmH}_2\text{O}$ with PEEP $0-5\text{ cmH}_2\text{O}$) rather than a T-piece.
SBT Duration: 30 Minutes vs. 120 Minutes
Seminal clinical trials (Esteban et al., Perren et al.) confirmed that a $30\text{ minute}$ SBT is diagnostically equivalent to a $120\text{ minute}$ trial in identifying patients capable of sustained unassisted breathing. Over $85\%$ of patients destined to fail an SBT develop objective signs of respiratory muscle exhaustion, gas exchange deterioration, or hemodynamic instability within the first $20$ to $30\text{ minutes}$. Prolonging the trial to $120\text{ minutes}$ in patients without severe cardiopulmonary compromise offers no diagnostic advantage and risks inducing unnecessary diaphragmatic fatigue and structural sarcomere microinjury. Consequently, standard protocolized SBT duration is $30\text{ minutes}$ for uncomplicated patients, reserving $60 - 120\text{ minute}$ trials for select complex patients with borderline chronic cardiopulmonary reserve.
Objective SBT Failure Criteria
During the trial, the patient must be continuously monitored at the bedside. The occurrence of any of the following objective physiological criteria mandates immediate trial termination and resumption of baseline resting ventilatory support:
                          SBT FAILURE DETECTION
                                    |
       +-----------------+----------+----------+-----------------+
       v                 v                     v                 v
[ Tachypnea & Load ] [ Gas Exchange ]     [ Hemodynamics ]     [ Clinical Distress ]
* RR > 35 bpm        * SpO2 < 90%         * HR > 140 bpm or    * Diaphoresis
* RR < 8 bpm         * PaO2 < 55-60 mmHg    delta HR > 20%     * Paradoxical breathing
* RSBI > 105         * pH < 7.30 or       * SBP > 180 or < 90  * Suprasternal tugging
                       delta PaCO2 > 8    * Vasopressor req    * Agitation / Somnolence
- Tachypnea & Ventilatory Distress:
- Respiratory rate ($\text{RR}$) $> 35\text{ breaths/min}$ for $> 5\text{ minutes}$ or severe bradypnea ($\text{RR} < 8\text{ breaths/min}$).
- Severe accessory muscle recruitment (sternocleidomastoid and scalene contraction, suprasternal and intercostal retractions, nasal flaring).
- Thoracoabdominal Asynchrony / Paradox: Inward inspiratory abdominal movement indicating diaphragmatic exhaustion and shift of ventilatory work to ribcage accessory muscles.
- Gas Exchange Deterioration:
- Pulse oximetry $\text{SpO}_2 < 90\%$ (or $\text{PaO}_2 < 55 - 60\text{ mmHg}$) on an $\text{FiO}_2 \ge 0.40 - 0.50$.
- Acute respiratory acidosis: arterial $\text{pH} < 7.30 - 7.32$ or acute elevation of arterial carbon dioxide tension ($\Delta \text{PaCO}_2 > 8 - 10\text{ mmHg}$).
- Cardiovascular & Hemodynamic Instability:
- Severe tachycardia ($\text{HR} > 140\text{ beats/min}$ or sustained increase in $\text{HR} > 20 - 25\%$ over baseline) or new bradycardia ($\text{HR} < 60\text{ beats/min}$).
- Acute hypertension (Systolic Blood Pressure $[\text{SBP}] > 180\text{ mmHg}$) or acute hypotension ($\text{SBP} < 90\text{ mmHg}$ or decrease $> 20\text{ mmHg}$).
- New onset of malignant ventricular or supraventricular arrhythmias, or acute ischemic ST-segment/T-wave changes.
- Neurological & Autonomic Dysfunction:
- Profuse diaphoresis, facial grimacing, autonomic storming.
- Severe agitation, combativeness, anxiety, panic, or progressive somnolence and obtundation.
Diagnostic Predictors of Weaning Success
While the Spontaneous Breathing Trial remains the gold standard functional evaluation, several bedside physiological indices, pulmonary mechanics parameters, and point-of-care ultrasound (POCUS) modalities provide valuable predictive information regarding diaphragmatic workload and respiratory reserve.
                  BEDSIDE WEANING PREDICTORS
                               |
    +------------------+-------+--------+------------------+
    v                  v                v                  v
[ RSBI / Yang-Tobin ] [ P0.1 & MIP ]   [ Ultrasound DE ]  [ Ultrasound DTF ]
* RR / Vt (Liters)    * MIP < -25 cmH2O * Diaphragm        * Diaphragm
* Cutoff < 105          (muscle force)    Excursion          Thickening
* Low work of         * P0.1: 1.0 - 3.5 * DE > 1.0-1.4 cm    Fraction
  breathing             (neural drive)  * Identifies       * DTF > 30-36%
                                          hypomobility     * Identifies VIDD
1. Rapid Shallow Breathing Index (RSBI / Yang-Tobin Index)
First described by Karl Yang and Martin Tobin in 1991, the Rapid Shallow Breathing Index ($\text{RSBI}$) quantifies the development of rapid, shallow breathing—the universal compensatory physiological response to an imbalance between mechanical ventilatory load and neuromuscular capacity.
$$\text{RSBI} = \frac{f}{V_T \text{ (in Liters)}} = \frac{\text{Respiratory Rate (breaths/min)}}{\text{Tidal Volume (L)}}$$- Measurement Technique: Measured using a handheld calibrated spirometer attached to the endotracheal tube (or using the ventilator's unassisted measurement mode) during $1\text{ minute}$ of unassisted spontaneous breathing (PSV 0 / PEEP 0 or T-piece).
- Diagnostic Interpretation:
- $\text{RSBI} < 105\text{ breaths/min/L}$: Predicts successful spontaneous breathing and extubation (high sensitivity $\sim 90\%$, intermediate specificity $\sim 65\%$).
- $\text{RSBI} > 105\text{ breaths/min/L}$: Strong predictor of weaning failure; reflects elevated elastic/resistive loads relative to diaphragmatic strength.
- Serial / Dynamic RSBI: Monitoring the trajectory of RSBI between minute $1$ and minute $30$ of an SBT is superior to a single static measurement; an increase in $\text{RSBI} > 20\%$ during the trial reflects progressive diaphragmatic fatigue.
- Caveat: RSBI measured on PSV $5 - 8\text{ cmH}_2\text{O}$ artificially inflates $V_T$ and decreases $f$, lowering the calculated index by $20 - 40\%$ and producing false-negative results. True RSBI must be calculated during unassisted breathing.
2. Maximum Inspiratory Pressure (MIP / Negative Inspiratory Force [NIF])
- Physiological Principle: Evaluates the global mechanical force-generating capacity of the inspiratory muscles (primarily the diaphragm, external intercostals, and accessory scalenes).
- Measurement Technique: Performed by occluding the inspiratory airway for $20 - 25\text{ seconds}$ (or using a unidirectional Marini valve allowing expiration while blocking inspiration) and recording the maximum negative airway deflection generated during maximal patient effort.
- Diagnostic Threshold:
- $\text{MIP} < -25\text{ to } -30\text{ cmH}_2\text{O}$ (i.e., more negative, such as $-35\text{ or } -50\text{ cmH}_2\text{O}$): Indicates sufficient inspiratory muscle reserve.
- $\text{MIP} > -20\text{ cmH}_2\text{O}$ (i.e., less negative, such as $-15\text{ cmH}_2\text{O}$): Denotes severe inspiratory muscle weakness, critical illness myopathy, or severe VIDD.
3. Airway Occlusion Pressure at 100 ms ($P_{0.1}$ or $P_{100}$)
- Physiological Principle: $P_{0.1}$ measures the negative airway pressure generated during the first $100\text{ ms}$ ($0.1\text{ s}$) of an occluded inspiratory effort against a closed valve. Because $100\text{ ms}$ is shorter than the human conscious reaction time to an airway occlusion ($150 - 200\text{ ms}$), $P_{0.1}$ is entirely independent of patient volition and serves as a pure, objective reflection of central respiratory neuromuscular drive.
- Diagnostic Interpretation:
- Normal Physiological Drive: $P_{0.1} = 1.0 - 3.5\text{ cmH}_2\text{O}$.
- $P_{0.1} > 3.5 - 4.0\text{ cmH}_2\text{O}$: Indicates excessive, unsustainable central respiratory drive, high work of breathing, and impending respiratory muscle exhaustion (high risk of weaning failure).
- $P_{0.1} < 1.0\text{ cmH}_2\text{O}$: Indicates central respiratory depression (residual sedation, encephalopathy, brainstem pathology) or neuromuscular junction failure.
4. Diaphragmatic Point-of-Care Ultrasound (POCUS)
Point-of-care ultrasonography provides non-invasive, radiation-free morphological and dynamic functional assessment of diaphragmatic contractility at the bedside.
                      DIAPHRAGM ULTRASOUND METRICS
                                   |
         +-------------------------+-------------------------+
         v                                                   v
[ Diaphragmatic Excursion (DE) ]            [ Thickening Fraction (DTF) ]
* Subcostal view (liver/spleen window)      * Zone of apposition (8th-10th ICS)
* M-mode tracing along beam axis            * Linear high-frequency probe (10-15 MHz)
* Measures craniocaudal displacement (cm)   * DTF = (T_insp - T_exp) / T_exp * 100%
* Normal / Success: DE > 1.0 - 1.4 cm       * Normal / Success: DTF > 30% - 36%
* < 1.0 cm: Severe hypomobility / paresis   * < 30%: VIDD / contractile dysfunction
A. Diaphragmatic Excursion (DE)
- Probe Placement: Low-frequency ($2.5 - 5\text{ MHz}$) phased-array or curvilinear probe positioned in the right subcostal mid-clavicular line, using the acoustic window of the liver to visualize the right hemidiaphragm.
- Technique: In M-mode, the ultrasound beam is oriented perpendicular to the posterior third of the diaphragmatic dome. The vertical distance between the baseline expiratory position and peak inspiratory displacement represents craniocaudal excursion.
- Threshold for Liberation Success: $$\text{DE} > 1.0 - 1.4\text{ cm during spontaneous unassisted breathing}$$ Values $< 1.0\text{ cm}$ (or paradoxical negative motion) identify diaphragmatic hypomobility, paresis, or phrenic nerve injury.
B. Diaphragm Thickening Fraction (DTF)
- Probe Placement: High-frequency ($10 - 15\text{ MHz}$) linear vascular probe placed perpendicular to the chest wall in the mid-axillary line at the $8\text{th}$ to $10\text{th}$ intercostal space within the zone of apposition where the diaphragm abuts the inner rib cage.
- Technique: In B-mode and M-mode, the diaphragm is identified as a three-layered muscular structure consisting of two hyperechoic parallel lines (pleura and peritoneum) sandwiching a hypoechoic central muscle layer. Diaphragmatic thickness is measured at end-expiration ($T_{\text{exp}}$) and peak inspiration ($T_{\text{insp}}$).
- Mathematical Formula: $$\text{DTF} (\%) = \frac{T_{\text{insp}} - T_{\text{exp}}}{T_{\text{exp}}} \times 100\%$$
- Threshold for Liberation Success: $$\text{DTF} > 30\% - 36\%$$ A $\text{DTF} < 30\%$ confirms significant ventilator-induced diaphragmatic dysfunction (VIDD) with impaired contractile force reserve, predicting SBT failure and post-extubation fatigue.
Extubation Readiness vs. Post-Extubation Management
Successfully passing an SBT confirms that the patient's respiratory pump and cardiovascular reserve can sustain the work of breathing. However, extubation readiness requires a distinct clinical assessment of upper airway patency, secretion clearance mechanics, and post-extubation aspiration risk.
                      POST-SBT EXTUBATION EVALUATION
                                     |
         +---------------------------+---------------------------+
         v                                                       v
[ Airway Patency (Cuff Leak Test) ]            [ Secretion & Protection Mechanics ]
* Deflate cuff, record V_leak                  * Peak Expiratory Flow (PEF > 60 L/min)
* Positive leak: > 110 mL or > 24%             * White Card Test (moistened in 1-2 coughs)
* Failed leak: Laryngeal edema risk            * Secretion suction frequency <= q2h
  -> Steroid premedication >= 4h prior         * Intact bulbar reflexes (swallow/gag)
1. The Cuff Leak Test (CLT) & Laryngeal Edema
Endotracheal intubation induces mechanical friction, mucosal ischemia, and local pressure injury over the vocal cords and subglottic mucosa, predisposing patients to post-extubation laryngeal edema and critical post-extubation stridor.
- High-Risk Populations for Stridor: Intubation duration $> 6$ days, large endotracheal tube size (e.g., $\ge 8.0\text{ mm}$ internal diameter in females), traumatic or emergency intubations, repeated reintubations, female sex, and fluid overload.
- Procedure for Quantitative Cuff Leak Test:
- Suction oral cavity and subglottic space thoroughly.
- Maintain volume-controlled ventilation with a constant square flow waveform; record the baseline inspiratory and expiratory tidal volume ($V_T$).
- Fully deflate the endotracheal tube cuff.
- Measure the expired tidal volume over the subsequent $6$ consecutive respiratory cycles, averaging the lowest $3$ values ($V_{T,\text{deflated}}$).
- Calculate the Cuff Leak Volume: $$V_{\text{leak}} = V_{T,\text{inspired}} - V_{T,\text{deflated}}$$ $$\text{Percent Leak} = \frac{V_{T,\text{inspired}} - V_{T,\text{deflated}}}{V_{T,\text{inspired}}} \times 100\%$$
- Diagnostic Thresholds:
- Adequate Airway Clearance (Positive Leak): $V_{\text{leak}} > 110\text{ mL}$ or $\text{Percent Leak} > 24\%$. Demonstrates adequate space around the ETT; low risk of post-extubation stridor.
- Failed Leak (High Stridor Risk): $V_{\text{leak}} < 110\text{ mL}$ or $< 24\%$. Reflects severe peritubal mucosal edema.
Steroid Premedication Protocol for Failed Cuff Leak
When a failed cuff leak is identified in a patient otherwise ready for liberation, extubation should be postponed to permit prophylactic anti-inflammatory corticosteroid administration to reduce laryngeal mucosal swelling:
- Evidence-Based Corticosteroid Regimens:
- Methylprednisolone: $20\text{ mg}$ IV every $4$ hours for $4$ doses (initiated $12 - 24\text{ hours}$ prior to planned extubation), OR a single dose of $40\text{ mg}$ IV administered at least $\ge 4\text{ to } 6\text{ hours}$ before extubation.
- Dexamethasone: $5\text{ mg}$ IV every $6$ hours for $4$ doses (initiated $24\text{ hours}$ prior).
- Repeat the cuff leak test prior to extubation following steroid administration; ensure re-intubation airway adjuncts (video laryngoscope, bougie, airway exchange catheter) and nebulized racemic epinephrine are immediately available at bedside.
2. Airway Protection and Secretion Clearance Mechanics
Extubation failure frequently stems from the inability to clear secretions rather than ventilatory muscle weakness.
- Voluntary Cough Peak Expiratory Flow ($\text{Cough-PEF}$): Measured using a handheld peak flow meter attached to the ETT. A $\text{Cough-PEF} < 60\text{ L/min}$ reflects severe cough impairment and carries a $5$-fold higher risk of extubation failure.
- White Card Test: A white index card is held $1 - 2\text{ cm}$ from the endotracheal tube connector while the patient is instructed to cough vigorously. Failure to moisten the card in $1$ or $2$ coughs predicts extubation failure due to ineffective cough clearance.
Prophylactic Post-Extubation Respiratory Support: NIV vs. HFNC
Historically, Noninvasive Ventilation (NIV) was applied reactively as "rescue" therapy when patients developed acute respiratory distress after extubation. Multiple randomized trials (Esteban et al., Keenan et al.) proved that rescue NIV in unselected post-extubation respiratory failure does not prevent reintubation and increases mortality due to dangerous delays in necessary reintubation. In contrast, prophylactic noninvasive respiratory support applied immediately upon extubation in predefined high-risk populations significantly reduces post-extubation respiratory failure and reintubation rates.
                      POST-EXTUBATION SUPPORT STRATEGY
                                      |
     +--------------------------------+--------------------------------+
     v                                                                 v
[ High-Risk Patients ]                                        [ Low-Risk Patients ]
* Age >= 65 years                                             * Age < 65 years
* Underlying chronic cardiac/lung disease (COPD, CHF)         * No chronic organ failure
* APACHE II > 12 or SOFA score elevated                       * Strong cough / Low secretions
* Obesity (BMI >= 30)                                         * Single brief intubation (< 48-72h)
* Prolonged mechanical ventilation (> 7 days)                 * Passed 30-minute SBT easily
* Weak cough / high secretions / SBT difficulty               * Post-extubation strategy:
* Post-extubation strategy:                                     Standard low-flow oxygen
  Prophylactic NIV + HFNC or High-Flow Nasal Cannula (HFNC)      or HFNC for comfort
1. Risk Stratification for Post-Extubation Failure
| Risk Category | Clinical Characteristics | Recommended Post-Extubation Modality |
|---|---|---|
| Low-Risk Patients | Age $< 65\text{ years}$; absence of underlying chronic cardiopulmonary disease (COPD, heart failure); $\text{BMI} < 30\text{ kg/m}^2$; duration of mechanical ventilation $< 48 - 72\text{ hours}$; strong voluntary cough ($\text{Cough-PEF} > 60\text{ L/min}$); minimal secretion burden; prompt pass on initial $30\text{ min}$ SBT. | Standard low-flow supplemental oxygen or High-Flow Nasal Cannula (HFNC). Routine prophylactic NIV is not indicated. |
| High-Risk Patients | Presence of $\ge 1$ high-risk feature: Age $\ge 65\text{ years}$; underlying COPD or chronic hypercapnic respiratory disease; congestive heart failure (NYHA III/IV or systolic/diastolic dysfunction); $\text{BMI} \ge 30\text{ kg/m}^2$; prolonged mechanical ventilation ($> 7\text{ days}$); $\text{APACHE II} > 12$ on extubation day; moderate-to-high secretion burden; difficult or prolonged weaning category; development of hypercapnia ($\text{PaCO}_2 > 45\text{ mmHg}$) during the SBT. | Immediate Prophylactic NIV combined with HFNC, or Continuous Prophylactic HFNC. |
2. The Hernandez et al. Clinical Trials (JAMA 2016)
The landmark trials led by Gonzalo Hernández established modern post-extubation protocols:
- High-Flow Nasal Cannula in Low-Risk Patients (JAMA 2016):
- Randomized $527$ low-risk extubated ICU patients to HFNC (flow $10 - 50\text{ L/min}$, $\text{FiO}_2$ titrated for $\text{SpO}_2 \ge 92\%$) versus conventional oxygen therapy.
- Outcome: Prophylactic HFNC significantly reduced the rate of reintubation within $72\text{ hours}$ ($4.9\%$ vs. $12.2\%$, absolute difference $-7.3\%$, $P = 0.004$) and post-extubation respiratory failure.
- HFNC vs. NIV in High-Risk Patients (JAMA 2016):
- Randomized $604$ high-risk patients to HFNC alone versus prophylactic NIV alone.
- Outcome: HFNC alone was non-inferior to prophylactic NIV in preventing reintubation within $72\text{ hours}$ ($22.8\%$ vs. $19.1\%$) and was associated with fewer adverse effects (skin breakdown, patient discomfort, intolerance).
- Combined Prophylactic NIV + HFNC in High-Risk Patients (The HIGH-WEAN Trial, Thille et al. JAMA 2019):
- Randomized $641$ high-risk mechanically ventilated patients across $30$ ICUs to NIV alternating with HFNC (NIV applied for at least $12\text{ hours/day}$, with HFNC applied between NIV sessions) versus HFNC alone.
- Outcome: The combined strategy of prophylactic NIV + HFNC demonstrated a significant reduction in the $7$-day reintubation rate compared to HFNC alone ($11.8\%$ vs. $18.2\%$, absolute difference $-6.4\%$, $P = 0.02$) and significantly decreased post-extubation respiratory failure ($21\%$ vs. $29\%$).
3. Practical Post-Extubation Protocol for High-Risk Patients
For patients meeting high-risk criteria, initiate the following post-extubation bundle immediately upon extubation:
[ Extubation in High-Risk Patient ]
                 |
                 v
[ Immediate Prophylactic NIV Application ]
* Interface: Well-fitted oronasal or total face mask
* Initial Settings: IPAP 10-14 cmH2O, EPAP 5-8 cmH2O
* Duration: Minimum 4 hours continuous session post-extubation
                 |
                 v
[ Transition to HFNC during Breaks ]
* Flow: 50-60 L/min, Temperature: 37°C
* FiO2 titrated to maintain SpO2 92-96% (88-92% in chronic hypercapnia)
* Allows oral intake, expectoration, communication, and comfort
                 |
                 v
[ Maintain Protocolized Cycle for 48 Hours ]
* Minimum cumulative NIV duration: >= 12 hours/day
* Continuous HFNC during all non-NIV intervals
Bedside Troubleshooting of Weaning Failure
When a patient fails an SBT or demonstrates difficult/prolonged weaning, clinicians must systematically investigate the underlying pathophysiological drivers across four organ systems:
                      PATHOPHYSIOLOGY OF WEANING FAILURE
                                       |
     +------------------+--------------+-----+------------------+
     v                  v                    v                  v
[ Respiratory Pump ]   [ Cardiac Failure ]  [ Neuromuscular/CNS ] [ Metabolic / Endocrine ]
* High resistive load  * Diastolic dysfn    * VIDD / CIPNM        * Hypophosphatemia
  (bronchospasm, ETT)  * LV ischemia / CAD  * Phrenic neuropathy  * Hypomagnesemia
* Low compliance       * Loss of positive   * Oversedation        * Hypokalemia
  (edema, effusion)      intrathoracic P    * Encephalopathy      * Hypothyroidism
* Auto-PEEP            * Acute MR                                 * Malnutrition / High CO2
1. Excessive Mechanical Workload
- Increased Resistance ($R_{\text{aw}}$): Severe bronchospasm, thick endobronchial secretions, kinked or undersized artificial airway, upper airway edema.
- Decreased Compliance ($C_{\text{rs}}$): Acute pulmonary edema, worsening atelectasis, consolidation, progressive pulmonary fibrosis, pleural effusions, pneumothorax, severe abdominal compartment syndrome / elevated intra-abdominal pressure.
- Intrinsic PEEP (Auto-PEEP): Dynamic hyperinflation in COPD/asthma patients creates an inspiratory threshold load; every spontaneous breath requires generating negative muscular pressure equal to $\text{PEEP}_i$ before flow can begin.
2. Cardiovascular & Hemodynamic Decompensation (Weaning-Induced Pulmonary Edema)
Transitioning from positive-pressure mechanical ventilation to spontaneous negative-pressure breathing dramatically alters heart-lung interactions:
- Physiology: Negative pleural pressure swings during inspiration increase systemic venous return (elevating right ventricular preload) and increase left ventricular transmural pressure (elevating LV afterload). Furthermore, the abrupt withdrawal of positive airway pressure removes the supportive pneumatic splinting of the left ventricle.
- Clinical Presentation: Acute onset of severe hypertension, tachycardia, new mitral regurgitation, ischemic ST-segment depression, and flash pulmonary edema during the SBT.
- Management: Bedside echocardiography, optimization of fluid balance with loop diuretics, pre-SBT afterload reduction (ACE inhibitors, nitrates), and prophylactic post-extubation NIV with high EPAP.
3. Neuromuscular Pump Failure
- Ventilator-Induced Diaphragmatic Dysfunction (VIDD): Loss of diaphragmatic sarcomere force generation, oxidative stress, and myofibrillar proteolysis resulting from prolonged controlled mechanical ventilation.
- Critical Illness Polyneuromyopathy (CIPNM): Generalized axonal motor neuropathy and myopathy related to systemic inflammatory response syndrome (SIRS), sepsis, prolonged neuromuscular blockade, and high-dose systemic corticosteroid exposure.
4. Metabolic, Endocrine, and Nutritional Derangements
- Electrolyte Depletion: Hypophosphatemia (depletes intracellular ATP, directly causing severe diaphragmatic weakness), hypomagnesemia, and hypokalemia.
- Endocrine Disorders: Severe unaddressed hypothyroidism (myxedema, blunted central ventilatory drive) and adrenal insufficiency.
- Overfeeding & Excessive Carbon Dioxide Production: Excessive caloric administration (particularly carbohydrates) increases the respiratory quotient (RQ) and carbon dioxide production ($\dot{V}\text{CO}_2$), placing an excessive minute ventilation demand on a compromised respiratory pump.
Key Takeaways & Summary
- Classify Weaning Trajectories Systematically: Categorize all weaning patients into Simple Weaning (extubation on first SBT attempt), Difficult Weaning ($\le 3$ SBTs or $\le 7$ days), or Prolonged Weaning ($\ge 3$ SBTs or $> 7$ days) to establish prognosis and risk stratification.
- Standardize Daily Readiness Screening: Perform daily morning screening assessing etiology improvement, oxygenation ($P/F \ge 150-200$ on PEEP $\le 5-8\text{ cmH}_2\text{O}$, $\text{FiO}_2 \le 0.40-0.50$), hemodynamics without high-dose vasopressors, and neurological alertness.
- Conduct SBTs with Low-Level Pressure Support: Utilize PSV $5 - 8\text{ cmH}_2\text{O}$ with PEEP $0 - 5\text{ cmH}_2\text{O}$ for $30\text{ minutes}$ as the preferred, guideline-recommended initial SBT strategy (Subira et al. JAMA 2019).
- Utilize Validated Bedside Predictors: Integrate the Rapid Shallow Breathing Index ($\text{RSBI} < 105$), Airway Occlusion Pressure ($P_{0.1} = 1.0 - 3.5\text{ cmH}_2\text{O}$), and point-of-care diaphragmatic ultrasound ($\text{DE} > 1.0 - 1.4\text{ cm}$, $\text{DTF} > 30 - 36\%$) to evaluate diaphragmatic reserve and work of breathing.
- Evaluate Airway Patency Prior to Extubation: In high-risk patients, perform a Cuff Leak Test ($V_{\text{leak}} > 110\text{ mL}$ or $> 24\%$). Premedicate with intravenous corticosteroids ($\ge 4 - 6\text{ hours}$ prior) if the cuff leak fails.
- Implement Prophylactic Post-Extubation NIV + HFNC in High-Risk Patients: Prevent reintubation in high-risk patients (age $\ge 65$, COPD, CHF, obesity, prolonged mechanical ventilation) by applying immediate prophylactic NIV combined with HFNC for at least 48 hours post-extubation. Avoid rescue NIV in established post-extubation respiratory failure.