Respiratory Distress Syndrome (RDS), historically designated hyaline membrane disease, represents the prototypical disorder of developmental pulmonary immaturity in preterm neonates. The fundamental pathophysiology centers on primary quantitative and qualitative deficiency of endogenous pulmonary surfactant, compounded by structural immaturity of the terminal gas-exchanging units, elevated chest wall compliance, and a vulnerable alveolar-capillary barrier.
Without sufficient surface-active material, alveolar surface tension remains unabatedly elevated throughout the ventilatory cycle, inducing progressive micro-atelectasis, non-compliant lungs, intrapulmonary right-to-left shunting, severe ventilation-perfusion ($V/Q$) mismatch, and secondary epithelial injury. Evidence-based clinical management has evolved dramatically over the past two decades, transitioning from routine delivery room endotracheal intubation and prophylactic mechanical ventilation toward immediate non-invasive respiratory stabilization (Bubble CPAP) and selective early rescue surfactant administration.
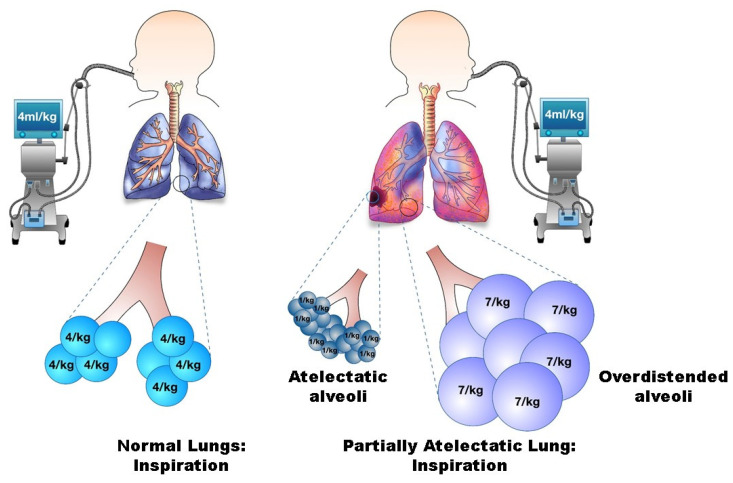 Figure 1: Pathophysiological schematic of regional volutrauma, shear stress, and alveolar instability during mechanical ventilation in surfactant-deficient neonatal RDS. Primary surfactant deficiency markedly increases surface tension, producing widespread micro-atelectasis and structural heterogeneity. Positive-pressure tidal ventilation preferentially routes into the small fraction of compliant, open alveoli, precipitating regional overdistension (volutrauma) and biotrauma, while non-aerated units suffer repetitive collapse and reopening shear strain (atelectrauma). (Source: Carlo WA, Ambalavanan N, et al. J Clin Med 2022; 11(3):557. DOI: 10.3390/jcm11030557).
Biophysics of Endogenous Pulmonary Surfactant
Pulmonary surfactant is an intricately organized, multimolecular lipoprotein complex synthesized, packaged, and secreted into the alveolar liquid lining layer by alveolar epithelial Type II cells (AEC-II).
graph TD
    subgraph AEC2["Type II Alveolar Pneumocyte"]
        LipidSynth["Lipid Synthesis (Endoplasmic Reticulum)"] --> LamellarBody["Lamellar Bodies (Packaging & Storage)"]
        ProteinSynth["SP-B, SP-C, SP-A, SP-D Synthesis"] --> LamellarBody
        ABCA3["ABCA3 Transporter (Active Lipid Uptake)"] --> LamellarBody
    end
    LamellarBody -->|"Exocytosis (ATP / Ca2+)"| AlveolarLumen["Alveolar Hypophase (Fluid Layer)"]
    AlveolarLumen -->|"SP-B & SP-C Activation"| TubularMyelin["Tubular Myelin Meshwork"]
    TubularMyelin --> Monolayer["Interfacial Monolayer (Air-Liquid Interface)"]
    Monolayer -->|"Compression on Exhalation"| ZeroTension["Surface Tension (γ) -> 0 mN/m (Prevents Collapse)"]
Biochemical Composition & Ultrastructure
Endogenous surfactant comprises approximately $90\%$ lipids by weight and $10\%$ specialized surfactant-associated proteins:
Phospholipids ($\approx 80-85\%$ of total mass):
- Dipalmitoylphosphatidylcholine (DPPC / Colfosceril) ($\approx 40-50\%$): Possesses two saturated 16-carbon palmitic acid acyl chains ($16:0/16:0$). The lack of double bonds allows exceptionally dense intermolecular packing at the air-water interface during alveolar compression, lowering surface tension to near $0\text{ mN/m}$.
- Unsaturated Phosphatidylcholines ($\approx 25-30\%$): Impart essential fluidic flexibility to the lipid lattice at physiological body temperature ($37^\circ\text{C}$).
- Phosphatidylglycerol (PG) ($\approx 8-12\%$): A negatively charged phospholipid whose appearance in amniotic fluid serves as a definitive biomarker of biochemical lung maturity. PG promotes lateral spreading of DPPC across the alveolar interface.
- Phosphatidylethanolamine (PE), Phosphatidylinositol (PI), and Sphingomyelin ($\approx 5-10\%$).
Neutral Lipids ($\approx 5-10\%$):
- Predominantly unesterified cholesterol, which modulates monolayer fluidity, film compressibility, and rapid respreading during alveolar expansion.
Surfactant Proteins (SP-A, SP-B, SP-C, SP-D) ($\approx 10\%$):
- Categorized into hydrophobic proteins (SP-B, SP-C) and hydrophilic collectins (SP-A, SP-D).
| Surfactant Protein | Molecular Weight | Structural Class & Gene | Biophysical & Biological Functions |
|---|---|---|---|
| SP-B | $8.7\text{ kDa}$ (homodimer $17.4\text{ kDa}$) | Hydrophobic Saposin-like (SFTPB, Chr 2p11.2) | Essential for lamellar body processing, formation of tubular myelin, rapid insertion/spreading of DPPC into interfacial monolayer, and lowering surface tension to $<5\text{ mN/m}$. |
| SP-C | $4.2\text{ kDa}$ (monomer) | Hydrophobic Poly-valine alpha-helix (SFTPC, Chr 8q21.3) | Anchors the lipid film to the aqueous hypophase; accelerates interfacial adsorption; stabilizes DPPC monolayer during dynamic high-rate respiratory compression. |
| SP-A | $28-36\text{ kDa}$ (octadecamer $650\text{ kDa}$) | Hydrophilic C-type Collectin (SFTPA1, SFTPA2, Chr 10q22) | Regulates surfactant uptake/recycling by AEC-II; innate host defense via opsonization of Gram-negative bacteria and viruses; organizes tubular myelin lattice with SP-B. |
| SP-D | $43\text{ kDa}$ (dodecamer $520\text{ kDa}$) | Hydrophilic C-type Collectin (SFTPD, Chr 10q22) | Innate immunity; microbial agglutination; immune clearance of pulmonary pathogens; suppression of alveolar inflammatory cascades. |
Mathematical Biophysics: The Law of Laplace & Alveolar Stability
The mechanical equilibrium of a curved spherical air-liquid interface is governed by the classical Law of Laplace:
$$P = \frac{2\gamma}{r}$$Where:
- $P$ is the distending (collapsing) pressure across the interface ($\text{dyne/cm}^2$ or $\text{cmH}_2\text{O}$).
- $\gamma$ is the surface tension of the liquid lining ($\text{mN/m}$ or $\text{dyne/cm}$). For pure water or plasma transudate, $\gamma \approx 70-72\text{ mN/m}$ and remains constant regardless of surface area.
- $r$ is the radius of the alveolar sphere ($\text{cm}$ or $\mu\text{m}$).
Consider two communicating alveoli connected to a common terminal bronchiole in a lung devoid of pulmonary surfactant:
- Alveolus 1 (Small radius, $r_1 = 50\,\mu\text{m}$)
- Alveolus 2 (Large radius, $r_2 = 100\,\mu\text{m}$)
Because surface tension $\gamma$ is constant ($\approx 70\text{ mN/m}$):
$$P_1 = \frac{2 \times 70}{50 \times 10^{-4}} = 28{,}000\text{ dyne/cm}^2 \approx 28.5\text{ cmH}_2\text{O}$$$$P_2 = \frac{2 \times 70}{100 \times 10^{-4}} = 14{,}000\text{ dyne/cm}^2 \approx 14.3\text{ cmH}_2\text{O}$$Because $P_1 > P_2$, a steep pressure gradient drives gas from the smaller alveolus into the larger alveolus. Consequently, the smaller alveolus collapses completely (atelectasis), while the larger alveolus becomes progressively hyperinflated.
flowchart TD
    subgraph WithoutSurfactant["SURFACTANT DEFICIENCY (Constant Surface Tension: γ = 70 mN/m)"]
        direction TB
        S1["Small Alveolus (r1 = 50 µm)"] -->|"P1 = 2γ / r1 = 28.5 cmH2O"| HighP["High Collapsing Pressure"]
        S2["Large Alveolus (r2 = 100 µm)"] -->|"P2 = 2γ / r2 = 14.3 cmH2O"| LowP["Low Collapsing Pressure"]
        HighP -->|"Gas Flows from High to Low Pressure"| ShuntFlow["Gas Empties: r1 -> r2"]
        ShuntFlow --> MicroAtelectasis["Complete Alveolar Collapse (Atelectasis) & Adjacent Overdistension"]
    end
    subgraph WithSurfactant["SURFACTANT SUFFICIENCY (Variable Surface Tension: γ(r) ∝ r)"]
        direction TB
        T1["Small Alveolus (r1 = 50 µm)"] -->|"DPPC Compression: γ1 -> 1 mN/m"| EqP1["P1 = 2(1) / 50 = 0.4 cmH2O"]
        T2["Large Alveolus (r2 = 100 µm)"] -->|"DPPC Dilution: γ2 -> 25 mN/m"| EqP2["P2 = 2(25) / 100 = 5.0 cmH2O"]
        EqP1 & EqP2 --> Stable["Pressures Equalized Across System -> Alveolar Stability Maintained at FRC"]
    end
In the presence of endogenous surfactant, surface tension dynamic behavior changes from a constant property to an area-dependent variable: $\gamma = f(A)$.
- During expiration (alveolar deflation, $r \downarrow$), the DPPC molecules are tightly packed, driving surface tension $\gamma$ downward toward near-zero ($0-5\text{ mN/m}$). Consequently, $P = \frac{2\gamma}{r}$ drops to negligible levels, abolishing the collapsing pressure and stabilizing the alveolus at end-expiration (FRC).
- During inspiration (alveolar expansion, $r \uparrow$), the surfactant molecules separate, surface tension increases ($\gamma \approx 25-35\text{ mN/m}$), generating elastic recoil that facilitates passive exhalation.
Genetics of Surfactant Metabolism & Congenital Deficiency Syndromes
SP-B Deficiency (SFTPB gene mutation, autosomal recessive):
- Most common mutation is the 121ins2 frameshift in exon 4.
- Leads to complete absence of mature SP-B protein, failure to generate tubular myelin, and aberrant processing of pro-SP-C.
- Causes lethal neonatal RDS refractory to exogenous surfactant replacement; lung transplantation represents the only definitive survival pathway.
ABCA3 Transporter Deficiency (ABCA3 gene mutation, autosomal recessive):
- ABCA3 is an ATP-binding cassette transporter localized to the limiting membrane of lamellar bodies, essential for transporting phosphatidylcholine and PG into the storage organelle.
- Biallelic loss-of-function mutations produce characteristic "fried-egg" or dense lamellar bodies with eccentric electron-dense cores on transmission electron microscopy, presenting as severe, fatal neonatal RDS or refractory pediatric interstitial lung disease (chILD).
SP-C Deficiency (SFTPC gene mutation, autosomal dominant):
- Often manifests as variable-onset chronic interstitial pneumonitis in older infants or adults due to misfolded protein accumulation and endoplasmic reticulum stress in AEC-II.
Pathophysiology of RDS in Preterm Infants
The onset of RDS is driven by a primary developmental surfactant deficit occurring on a background of an anatomically immature, highly compliant chest wall and non-compliant lung parenchyma.
graph TD
    Preterm["Preterm Birth (< 32 weeks) / Immature AEC-II"] --> PrimaryDef["Primary Quantitative Surfactant Deficiency"]
    PrimaryDef --> HighST["Markedly Elevated Alveolar Surface Tension (γ)"]
    HighST --> DiffuseAtelectasis["Diffuse Micro-Atelectasis & Loss of FRC"]
    DiffuseAtelectasis --> LowComp["Markedly Decreased Static Compliance (C_stat)"]
    DiffuseAtelectasis --> VQ["Intrapulmonary Right-to-Left Shunt (Severe V/Q Mismatch)"]

    LowComp --> HighWOB["Severe Work of Breathing & Tachypnea"]
    HighWOB --> Hypoventilation["Alveolar Hypoventilation -> Respiratory Acidosis (PaCO2 > 60 mmHg)"]
    VQ --> Hypoxemia["Refractory Hypoxemia (PaO2 < 50 mmHg)"]

    Hypoxemia & Hypoventilation --> PVR["Elevated Pulmonary Vascular Resistance (PVR)"]
    PVR --> DuctShunt["Right-to-Left Shunting via PDA / PFO"]

    DiffuseAtelectasis --> ShearStress["Cyclic Alveolar Collapse & Shear Stress (Atelectrauma)"]
    ShearStress --> EpithDamage["Capillary-Alveolar Barrier Disruption"]
    EpithDamage --> FibrinExudate["Plasma Protein & Fibrin Exudation into Lumen"]
    FibrinExudate --> HyalineMembrane["Hyaline Membrane Deposition"]
    FibrinExudate --> Inactivation["Surfactant Inactivation (Fibrinogen, Albumin, Hemoglobin)"]
    Inactivation --> PrimaryDef
Pathophysiological Cascade
Loss of Functional Residual Capacity (FRC):
- Normal neonatal FRC is $25-30\text{ mL/kg}$. In surfactant-deficient RDS, FRC collapses to $<10-15\text{ mL/kg}$.
- The lung operates below its lower inflection point (LIP) on the static pressure-volume curve, requiring immense transpulmonary opening pressures ($>25-35\text{ cmH}_2\text{O}$) with each consecutive spontaneous breath.
Mechanics of the Preterm Thorax:
- Preterm infants have an exceptionally compliant, cartilaginous thoracic cage.
- When the infant generates vigorous negative intrapleural pressure (up to $-30\text{ cmH}_2\text{O}$) to expand stiff, non-compliant alveoli, the chest wall collapses inward rather than expanding the lung parenchyma, producing severe subcostal, intercostal, and sternal retractions (paradoxical seesaw breathing) with minimal effective tidal volume.
Exudative Epithelial Injury & Hyaline Membrane Generation:
- High shear forces generated across collapsed and aerated interfaces disrupt the delicate alveolar-capillary barrier.
- Plasma proteins, specifically fibrin monomer complexes, albumin, and hemoglobin, leak into the alveolar spaces.
- These leaked proteins act as potent competitive inhibitors of endogenous and exogenous surfactant by displacing DPPC from the air-liquid interface.
- Fibrin, cellular debris from necrotic Type I pneumocytes, and inflammatory exudates polymerize into dense, eosinophilic hyaline membranes lining the alveolar ducts and terminal bronchioles within $12-24\text{ hours}$ of life.
Pulmonary Hypertension and Extrapulmonary Shunting:
- Alveolar hypoxia and hypercapnic acidosis induce intense pulmonary arteriolar vasoconstriction, elevating pulmonary vascular resistance (PVR).
- Elevated PVR perpetuates right-to-left extrapulmonary shunting across the patent ductus arteriosus (PDA) and patent foramen ovale (PFO), exacerbating systemic cyanosis and unresponsiveness to supplemental oxygen.
European Consensus Guidelines for Management of RDS
The European Consensus Guidelines on the Management of Respiratory Distress Syndrome (2022/2023 Update) establish rigorous evidence-based recommendations for delivery room stabilization, non-invasive respiratory support, surfactant replacement, and lung-protective mechanical ventilation.
graph TD
    Delivery["Preterm Delivery Room Management"] --> DR_CPAP["Immediate Bubble CPAP 6-8 cmH2O via Short Binasal Prongs + FiO2 0.30 (Avoid Routine Intubation)"]
    DR_CPAP --> NICU_Assess["NICU Admission: Continuous PEEP 6-8 cmH2O & SpO2 Monitoring"]

    NICU_Assess --> ThresholdCheck{"CPAP Failure / Surfactant Threshold Met?<br/>FiO2 >= 0.30 (GA < 28 wk)<br/>FiO2 >= 0.30-0.40 (GA >= 28 wk)<br/>PEEP >= 6 cmH2O or High LUS"}

    ThresholdCheck -- "NO (Stable, FiO2 < 0.30)" --> MaintainCPAP["Maintain Bubble CPAP 6-8 cmH2O<br/>Early Caffeine Citrate (20 mg/kg IV)<br/>Gentle Weaning"]

    ThresholdCheck -- "YES (Surfactant Indicated)" --> SpontBreathing{"Infant Spontaneously Breathing?"}

    SpontBreathing -- "YES" --> LISA["LISA / MIST Technique (Thin Angiocatheter)<br/>Poractant alfa 200 mg/kg<br/>Continue CPAP Throughout"]
    SpontBreathing -- "NO / Apneic / Failing" --> InSurE["InSurE (Intubate-Surfactant-Extubate) or ETT Instillation"]

    LISA --> PostSurf{"Clinical Response (FiO2 < 0.30, Work of Breathing Reduced)?"}
    PostSurf -- "YES" --> MaintainCPAP
    PostSurf -- "NO / Persistent Acidosis / Severe Apnea" --> InvasiveVG["Invasive Mechanical Ventilation (SIPPV/PSV + VG)<br/>Target VT 4.0-5.5 mL/kg, PEEP 5-7 cmH2O"]

    InSurE --> PostSurf
Delivery Room Stabilization & Non-Invasive Support
Delayed Cord Clamping:
- Defer umbilical cord clamping for at least $60\text{ seconds}$ in all stable preterm deliveries to augment placental transfusion, stabilize systemic blood pressure, and expand circulating blood volume.
Immediate Continuous Positive Airway Pressure (CPAP):
- Routine delivery room endotracheal intubation should be strictly avoided.
- Initiate continuous positive airway pressure immediately from birth using a T-piece resuscitator or Bubble CPAP with short binasal prongs or a mask at a PEEP of $6-8\text{ cmH}_2\text{O}$.
- Initial delivery room oxygen titration:
- For $<28\text{ weeks}$ gestation: Start $FiO_2 = 0.30$.
- For $28-31\text{ weeks}$ gestation: Start $FiO_2 = 0.21-0.30$.
- Titrate $FiO_2$ targeting the 25th–75th percentile of normal neonatal transition oxygen saturations ($SpO_2 \ge 80\%$ by $5\text{ min}$, $\ge 85\%$ by $10\text{ min}$).
Sustained Inflations:
- Routine delivery room sustained lung inflations ($>5\text{ seconds}$) are not recommended due to clinical trial evidence indicating increased early mortality.
Surfactant Administration Criteria & Protocols
Surfactant replacement therapy acts as an emergency rescue therapy to restore alveolar interfacial kinetics, re-establish FRC, and halt the cycle of epithelial baro-atelectrauma.
- Early Rescue Timing: Surfactant should be administered early in the disease course (ideally within the first $2-3\text{ hours}$ of life), rather than delayed.
- Threshold Criteria on CPAP:
- Infants $< 28\text{ weeks}$ gestation: Administer surfactant when $FiO_2 \ge 0.30$ on CPAP $\ge 6\text{ cmH}_2\text{O}$.
- Infants $\ge 28\text{ weeks}$ gestation: Administer surfactant when $FiO_2 \ge 0.30-0.40$ on CPAP $\ge 6\text{ cmH}_2\text{O}$.
- Lung Ultrasound Score (LUS): An elevated LUS score ($\ge 8-10$ on a 12-zone protocol) predicts CPAP failure and serves as an objective biomarker for immediate surfactant delivery.
| Surfactant Preparation | Source & Composition | Recommended Initial Dose | Clinical Characteristics |
|---|---|---|---|
| Poractant alfa (Curosurf) | Minced Porcine Lung Extract ($76\text{ mg/mL}$ phospholipids, $1\text{ mg/mL}$ SP-B/SP-C) | $200\text{ mg/kg}$ ($2.5\text{ mL/kg}$) | Initial dose of $200\text{ mg/kg}$ demonstrates superior acute oxygenation improvement, lower repeat-dosing requirement, and reduced mortality compared to $100\text{ mg/kg}$ of poractant or beractant. |
| Beractant (Survanta) | Minced Bovine Lung Extract with added DPPC, palmitic acid, and tripalmitin ($25\text{ mg/mL}$) | $100\text{ mg/kg}$ ($4.0\text{ mL/kg}$) | Effective bovine preparation; larger liquid instillation volume ($4\text{ mL/kg}$) requires split aliquots. |
| Calfactant (Infasurf) | Bovine Calf Lung Lavage ($35\text{ mg/mL}$ phospholipids, high endogenous SP-B) | $105\text{ mg/kg}$ ($3.0\text{ mL/kg}$) | Natural calf lavage formulation with high endogenous SP-B concentration. |
Surfactant Delivery Modalities
- LISA (Less Invasive Surfactant Administration) / MIST (Minimally Invasive Surfactant Therapy):
- Preferred first-line administration modality in spontaneously breathing infants maintained on Bubble CPAP.
- A fine vascular catheter ($16-18\text{ Gauge}$) or semi-rigid surfactant catheter is visualized passing through the vocal cords via direct laryngoscopy or video laryngoscopy while CPAP is maintained.
- Surfactant is slowly instilled over $1-3\text{ minutes}$ during spontaneous breathing, avoiding positive-pressure manual bag ventilation and preventing the tracheal trauma of endotracheal intubation.
- InSurE (Intubation-Surfactant-Extubation):
- Endotracheal intubation, bolus surfactant delivery, brief positive-pressure stabilization ($<15-30\text{ min}$), followed by immediate extubation back to Bubble CPAP.
- Endotracheal Tube Instillation with Mechanical Ventilation:
- Indicated when the infant fails non-invasive stabilization, presents with severe apnea, or exhibits uncompensated respiratory acidosis ($pH < 7.20, PaCO_2 > 65\text{ mmHg}$).
Mechanical Ventilation Strategies in RDS
When non-invasive respiratory support fails and invasive mechanical ventilation is mandated, the strategy must prevent ventilator-induced lung injury (VILI), volutrauma, atelectrauma, and biotrauma.
graph LR
    subgraph InvasiveStrategy["Lung-Protective Mechanical Ventilation in RDS"]
        direction TB
        Mode["Synchronized Mode: SIPPV / P-A/C or PSV"]
        VG["Volume Guarantee (VG) Active: VT 4.0 - 5.5 mL/kg"]
        PEEP["Sufficient PEEP: 5.0 - 7.0 cmH2O (Stabilize FRC)"]
        Ti["Short Inspiratory Time: Ti 0.30 - 0.35 s"]
        Targets["Permissive Hypercapnia (pH 7.22 - 7.35, PaCO2 45 - 60 mmHg)"]
    end
    Mode --> VG
    VG --> PEEP
    PEEP --> Ti
    Ti --> Targets
Volume Guarantee (VG) as Standard of Care
Volume Guarantee combined with synchronized intermittent positive pressure ventilation (SIPPV / P-A/C) or Pressure Support Ventilation (PSV) is the gold standard invasive mode for preterm neonates with RDS.
- The operator sets a target tidal volume ($V_{T,set}$). The ventilator measures exhaled tidal volume ($V_{Te}$) and automatically adjusts the peak inspiratory pressure (PIP) on a breath-by-breath basis within a set maximum pressure limit ($P_{max} = \text{PEEP} + 20-25\text{ cmH}_2\text{O}$).
- Following surfactant administration, lung compliance ($C_{stat}$) often improves dramatically within $15-45\text{ minutes}$. In conventional pressure-limited modes (PCV), this sudden rise in compliance causes dangerous tidal volume spikes and massive volutrauma. Under Volume Guarantee, the ventilator instantly self-weans PIP downward, safeguarding the fragile capillary-alveolar interface from alveolar rupture and intraventricular hemorrhage (IVH).
Initial Ventilator Settings & Blood Gas Targets
| Parameter | Initial Setting Range | Physiological Rationale & Safety Thresholds |
|---|---|---|
| Primary Mode | Synchronized P-A/C (SIPPV) + VG or PSV + VG | Minimizes work of breathing and patient-ventilator asynchrony. |
| Target Tidal Volume ($V_T$) | $4.0 - 5.0\text{ mL/kg}$ (Extremely low birth weight: $4.5-5.5\text{ mL/kg}$) | Prevents volutrauma; accounts for anatomical dead space ($V_D \approx 2.0-2.5\text{ mL/kg}$ including ETT). |
| Positive End-Expiratory Pressure (PEEP) | $5.0 - 7.0\text{ cmH}_2\text{O}$ | Prevents end-expiratory alveolar collapse, maintains FRC, and preserves surfactant function. |
| Inspiratory Time ($T_i$) | $0.30 - 0.35\text{ seconds}$ | Matches the short time constant ($\tau = R_{aw} \times C_{rs} \approx 0.05-0.10\text{ s}$) of stiff RDS lungs; ensures complete expiration. |
| Backup Respiratory Rate ($f$) | $40 - 60\text{ breaths/min}$ | Clears dead space ventilation and supports minute ventilation during central apnea. |
| Flow Trigger Sensitivity | $0.2 - 0.5\text{ L/min}$ | Ultra-sensitive pneumatic triggering to eliminate delayed triggering and ineffective efforts. |
| Target $SpO_2$ Range | $91\% - 95\%$ (Alarm limits: Low $89\%$, High $96\%$) | Avoids hyperoxia-mediated retinopathy of prematurity (ROP) and bronchopulmonary dysplasia (BPD). |
| Target Arterial Blood Gas | $pH: 7.22 - 7.35$ $PaCO_2: 45 - 60\text{ mmHg}$ $PaO_2: 50 - 70\text{ mmHg}$ | Permissive Hypercapnia: Tolerates moderate respiratory acidosis to minimize mechanical ventilation intensity and ventilator-induced lung injury. |
Bedside Troubleshooting, Pharmacotherapy & Red Flags
The administration of intravenous Caffeine Citrate ($20\text{ mg/kg}$ loading dose, followed by $5-10\text{ mg/kg/day}$) should be initiated within the first $2$ hours of life for all infants $<1250\text{ g}$ or $<30\text{ weeks}$ gestation on CPAP. Caffeine stimulates central medullary respiratory drive, increases diaphragmatic contractility, reduces apnea of prematurity, and significantly increases the success rate of non-invasive CPAP, reducing the incidence of bronchopulmonary dysplasia (BPD).
Differential Diagnosis of Surfactant Failure
When an infant fails to exhibit a brisk reduction in $FiO_2$ requirements or develops worsening respiratory acidosis within $2-4\text{ hours}$ of surfactant instillation, systematic evaluation for underlying etiologies must be performed:
graph TD
    Failure["Surfactant Failure / Refractory Hypoxemia"] --> CheckPneu["Rule Out Pneumothorax / Air Leak (Transillumination / CXR / LUS)"]
    Failure --> CheckTube["Verify ETT Position & Patency (Right Mainstem Intubation / Mucus Plug)"]
    Failure --> CheckInfection["Congenital Pneumonia / Sepsis (Group B Streptococcus, Ureaplasma)"]
    Failure --> CheckCard["Hemodynamically Significant PDA (Large Left-to-Right Shunt)"]
    Failure --> CheckPPHN["Persistent Pulmonary Hypertension of the Neonate (PPHN)"]
    Failure --> CheckMalform["Pulmonary Hypoplasia / Congenital Diaphragmatic Hernia / Alveolar Capillary Dysplasia"]
Massive pulmonary hemorrhage occurs in $1-3\%$ of extremely preterm infants following surfactant administration, predominantly in those with an open, hemodynamically significant PDA (hsPDA).
- Pathophysiology: Rapid clearance of alveolar surface tension triggers an instantaneous drop in pulmonary vascular resistance (PVR). The resulting massive increase in left-to-right ductal shunting overwhelms the pulmonary capillary bed, precipitating hemorrhagic pulmonary edema.
- Immediate Management:
- Increase PEEP promptly to $8-10\text{ cmH}_2\text{O}$ to tamponade microvascular capillary transudation.
- Clear the endotracheal tube with gentle in-line suctioning.
- Consider administration of a repeat surfactant dose to replace surfactant inactivated by free hemoglobin and plasma proteins.
- Optimize systemic mean arterial pressure (inotropic support) to minimize left-to-right ductal overflow.
Key Takeaways & Clinical Checklist
- Pathophysiological Core: RDS is primarily caused by quantitative and qualitative deficiency of DPPC and hydrophobic surfactant proteins (SP-B, SP-C), driving elevated surface tension, alveolar instability ($P = 2\gamma/r$), micro-atelectasis, and secondary hyaline membrane deposition.
- Primary Delivery Room Directive: Avoid routine delivery room endotracheal intubation. Stabilize immediately on Bubble CPAP ($6-8\text{ cmH}_2\text{O}$) via short binasal prongs with titrated oxygen ($FiO_2 0.30$).
- Surfactant Dosing & Timing: Administer early rescue Poractant alfa ($200\text{ mg/kg}$) via LISA/MIST if $FiO_2 \ge 0.30$ on CPAP $\ge 6\text{ cmH}_2\text{O}$ for infants $<28\text{ weeks}$ (or $\ge 0.30-0.40$ for $\ge 28\text{ weeks}$).
- Mechanical Ventilation Standard: If invasive ventilation is required, employ synchronized ventilation with Volume Guarantee ($V_T 4.0-5.5\text{ mL/kg}$), physiological PEEP ($5-7\text{ cmH}_2\text{O}$), short inspiratory time ($0.30-0.35\text{ s}$), and permissive hypercapnia ($pH \ge 7.22, PaCO_2 45-60\text{ mmHg}$).
- Surfactant Resistance & Red Flags: Promptly investigate for pneumothorax, congenital pneumonia, PPHN, large PDA, or rare congenital surfactant protein genetic mutations (SFTPB, ABCA3) when surfactant fails to improve oxygenation.