Persistent pulmonary hypertension of the newborn (PPHN) is the syndrome in which pulmonary vascular resistance (PVR) fails to fall after birth, so that pulmonary arterial pressure remains at or above systemic levels and the fetal pattern of right-to-left shunting through the ductus arteriosus and the foramen ovale persists. The resulting hypoxaemia is disproportionate to any parenchymal lung disease, labile with handling and arousal, and poorly responsive to inspired oxygen alone. PPHN affects roughly 1–2 per 1,000 live births, mainly term and late-preterm infants, and is a leading reason for neonatal extracorporeal membrane oxygenation (ECMO) referral.
PPHN is a haemodynamic syndrome with many causes, not a single disease. The pulmonary vasculature may be structurally normal but abnormally reactive, structurally remodelled, or frankly hypoplastic; each category predicts a different response to vasodilators and a different prognosis. Management rests on three simultaneous pillars: recruit and stabilise the lung so that oxygen and inhaled drugs reach ventilated alveoli; reduce PVR selectively; and defend systemic blood pressure and coronary perfusion so that the pressure-loaded right ventricle (RV) does not fail. Inhaled nitric oxide (iNO) is the most important selective pulmonary vasodilator, but it is neither the first step nor a substitute for these physiological foundations.
Developmental Physiology and the Mechanistic Classification of PPHN
The Normal Pulmonary Vascular Transition
In fetal life pulmonary blood flow is low because PVR is high, maintained by hypoxic pulmonary vasoconstriction, by the fluid-filled unexpanded lung, and by mediators that favour vasoconstriction. With delivery, lung inflation and rising oxygen tension remove hypoxic vasoconstriction; endothelial shear stress increases nitric oxide (NO) and prostacyclin (PGI$_2$) synthesis; bradykinin is released; and vasoconstrictors such as endothelin-1 and thromboxane recede. Loss of the low-resistance placental circulation simultaneously raises systemic vascular resistance (SVR). The aortopulmonary gradient reverses, the ductus closes functionally, and pulmonary blood flow rises to become the entire cardiac output.
Failure of the Transition and the Physics of Shunting
When PVR stays elevated, pulmonary arterial pressure approaches or exceeds systemic pressure and the fetal shunts fail to close. Deoxygenated blood then bypasses the lungs, so systemic arterial oxygen content falls despite a recruited lung. Two mechanical features dominate the bedside behaviour. Shunt direction is set by the instantaneous balance between PVR and SVR, so agitation, hypoxaemia, acidosis or hypotension can precipitate abrupt desaturation. And because resistance is inversely proportional to the fourth power of radius and to the number of parallel vessels, anatomically minor changes have outsized haemodynamic effects.
PVR is the transpulmonary pressure gradient divided by pulmonary blood flow:
$$PVR = \frac{\overline{PAP} - PAWP}{\dot{Q}_p}$$where $\overline{PAP}$ = mean pulmonary artery pressure ($\text{mmHg}$); $PAWP$ = pulmonary artery wedge pressure ($\text{mmHg}$); and $\dot{Q}_p$ = pulmonary blood flow ($\text{L}\cdot\text{min}^{-1}$). The unit is the Wood unit ($\text{mmHg}\cdot\text{L}^{-1}\cdot\text{min}^{-1}$), and the transpulmonary gradient is $TPG = \overline{PAP} - PAWP$. Because geometry sets resistance, $PVR \propto \frac{L}{N\,r^{4}}$, where $L$ = vessel length, $N$ = number of parallel vessels and $r$ = radius; a fall in $N$ (hypoplasia) or in $r$ (remodelling) raises PVR steeply.
Maladaptation, Maldevelopment and Underdevelopment
Maladaptation (vasoreactive PPHN) describes structurally near-normal lungs whose vessels constrict abnormally. It is the commonest and most treatment-responsive group, usually driven by parenchymal disease that produces hypoxaemia, hypercarbia and acidosis — meconium aspiration syndrome, respiratory distress syndrome, pneumonia, sepsis or asphyxia. Because the vascular bed is intact, relieving the vasoconstrictor stimulus often restores the transition.
Maldevelopment (remodelled PPHN) describes a normal complement of structurally remodelled vessels: medial hypertrophy, adventitial thickening and extension of smooth muscle into intra-acinar arteries. Causes include idiopathic PPHN, chronic fetal hypoxaemia, in-utero ductal constriction from non-steroidal anti-inflammatory exposure, and trisomy 21. These vessels dilate poorly, so response to iNO is limited and adjuncts or ECMO are more often needed.
Underdevelopment (hypoplastic PPHN) describes a reduced cross-sectional area of the vascular bed, as in congenital diaphragmatic hernia, oligohydramnios, congenital pulmonary airway malformation and alveolar capillary dysplasia with misalignment of pulmonary veins (ACDMPV). ACDMPV is intrinsically unsalvageable, and recognising it prevents futile escalation.
Clinical Recognition and Haemodynamic Assessment
Labile Hypoxaemia and the Ductal Gradient
PPHN typically declares itself within the first 24 hours in a term or late-preterm infant with respiratory distress and cyanosis. Its signature is labile hypoxaemia: saturation swings widely with crying, suctioning or handling and improves transiently with sedation and recruitment. Because a right-to-left ductal shunt delivers unsaturated blood to the descending aorta, paired pre-ductal (right hand) and post-ductal (foot) oximetry often shows a step-down:
$$\Delta SpO_2 = SpO_{2,\text{pre-ductal}} - SpO_{2,\text{post-ductal}} \geq 10\%$$A gradient of 5–10% or more supports ductal right-to-left shunting, but its absence does not exclude PPHN — shunting may be predominantly atrial, or the ductus may already have closed. The gradient is therefore specific but insensitive, and it never replaces echocardiography.
The Hyperoxia Test and Its Limitations
The hyperoxia test applies an $FiO_2$ of 1.0 for 10–15 minutes and measures pre-ductal $PaO_2$. A value above about 150–250 mmHg argues against fixed cyanotic congenital heart disease, while a $PaO_2$ below 100 mmHg is consistent with either PPHN or cyanotic heart disease. It discriminates poorly between the two, and its modern role is limited to settings where echocardiography is not immediately available.
Echocardiographic Interrogation
Echocardiography is the diagnostic and monitoring cornerstone, because it establishes pulmonary arterial pressure, defines shunt direction and excludes structural heart disease. A tricuspid regurgitation (TR) jet allows non-invasive estimation of systolic pulmonary arterial pressure.
The peak TR jet velocity $v_{TR}$ yields the right-ventricular–to–right-atrial pressure gradient:
$$PASP = 4\,v_{TR}^{2} + RAP$$where $PASP$ = pulmonary artery systolic pressure ($\text{mmHg}$); $v_{TR}$ = peak TR jet velocity ($\text{m}\cdot\text{s}^{-1}$); and $RAP$ = estimated right atrial pressure ($\text{mmHg}$, conventionally 3–5 in neonates). The jet is often undetectable when the pressure load is severe, and its absence is itself informative.
Additional findings include flattening or leftward bowing of the interventricular septum, graded by the systolic and diastolic eccentricity index; RV dilatation and hypertrophy; reduced RV function on tricuspid annular plane systolic excursion; and shortened pulmonary artery acceleration time. The direction of flow across the ductus and foramen ovale tracks the evolving pressure balance, and the same study must exclude total anomalous pulmonary venous connection, transposition and other duct-dependent lesions. Coexisting left ventricular dysfunction is critical to identify, because it changes inotrope selection and warns against indiscriminate vasodilation.
Quantifying Severity and Timing Escalation
Oxygenation in PPHN reflects both parenchymal disease and shunt, so the ventilator's contribution must be measured rather than assumed. Two composite indices integrate the cost of support with the achieved oxygenation.
The Oxygenation Index
where $MAP$ = mean airway pressure ($\text{cmH}_2\text{O}$); $FiO_2$ = fraction of inspired oxygen (dimensionless, 0–1); and $PaO_2$ = arterial oxygen tension ($\text{mmHg}$). The $OI$ is dimensionless.
$OI$ rises with more aggressive ventilation or a higher oxygen requirement and falls as oxygenation improves. For example, an infant on $MAP = 15\ \text{cmH}_2\text{O}$ and $FiO_2 = 1.0$ with $PaO_2 = 45\ \text{mmHg}$ has $OI = (15 \times 1.0 \times 100)/45 \approx 33$. Widely used thresholds, never a substitute for judgement, are: $OI > 15\text{–}20$ prompts consideration of pulmonary vasodilators; $OI > 25$ despite optimised lung volume and blood pressure justifies escalation such as iNO or high-frequency oscillatory ventilation; and a sustained $OI \geq 40$ over 4 hours is the classic trigger for ECMO referral.
The Oxygen Saturation Index
When arterial access is unavailable, pulse oximetry substitutes for $PaO_2$:
$$OSI = \frac{MAP \times FiO_2 \times 100}{SpO_2}$$where $SpO_2$ = pulse oximetric oxygen saturation ($\%$). Between 90% and 97%, $OSI$ tracks $OI$ closely and is useful for trending; the conventional escalation thresholds are $OSI > 15\text{–}20$ for vasodilators and $OSI \geq 20\text{–}25$ for refractory disease, though the two indices are not interchangeable at the extremes of saturation. The infant above, at $SpO_2 = 93\%$, has $OSI = (15 \times 1.0 \times 100)/93 \approx 16$.
Target a pre-ductal $SpO_2$ of 91–95% (roughly $PaO_2$ 55–80 mmHg), a $PaCO_2$ of 40–50 mmHg, and a mean arterial pressure appropriate for gestational age. There is no benefit to supranormal oxygenation, and both hypocarbia and hypercarbia are harmful.
A Stepwise Escalation Algorithm
The sequence matters: pulmonary vasodilators work only in a recruited lung with an adequate systemic pressure head.
graph TD
    A["Term or late-preterm infant with severe hypoxaemia"] --> B["Confirm PPHN by echocardiography<br/>and exclude cyanotic heart disease"]
    B --> C["Optimise lung volume, systemic blood pressure,<br/>temperature, glucose and sedation"]
    C --> D{"Pre-ductal SpO2 < 90%<br/>or OI >= 25 despite optimisation?"}
    D -->|"No"| E["Continue gentle conventional ventilation<br/>and frequent reassessment"]
    D -->|"Yes"| F["Start iNO at 20 ppm"]
    F --> G{"Acute vasoreactivity response<br/>PaO2 rise >= 20 mmHg or OI fall >= 20%?"}
    G -->|"Yes"| H["Continue iNO; wean FiO2 first,<br/>then wean iNO in 1 ppm steps"]
    G -->|"No"| I["Add sildenafil, milrinone or a prostacyclin analogue;<br/>consider HFOV for recruitment"]
    I --> J{"OI >= 40 sustained, refractory hypoxaemia,<br/>or haemodynamic collapse?"}
    J -->|"Yes"| K["Refer or initiate ECMO if eligible"]
    J -->|"No"| L["Re-examine lung volume, air leak,<br/>sedation and systemic perfusion"]
    H --> M["Monitor for rebound PPHN<br/>during weaning"]
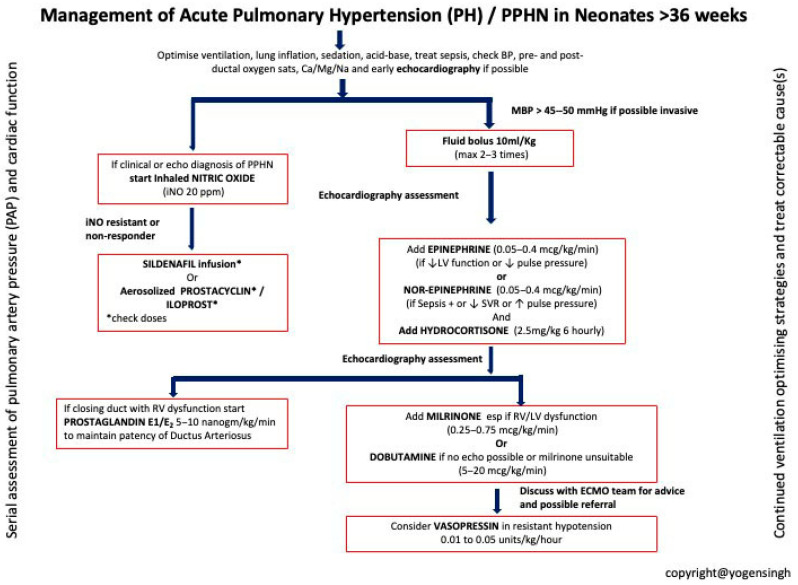 Figure 1: A pragmatic escalation pathway for PPHN in a centre with access to inhaled nitric oxide, emphasising optimisation of lung volume and systemic blood pressure before and alongside selective pulmonary vasodilation. (Source: Chojnacka K, Singh Y, Gahlaut S, Blaz W, Jerzak A, Szczapa T. Biomedicines 2025. DOI: 10.3390/biomedicines13102332).
Ventilation and Supportive Physiology
Recruit Without Overdistending
The relationship between lung volume and PVR is U-shaped. At low volumes, atelectasis and the resulting hypoxic vasoconstriction raise PVR; at high volumes, overdistension compresses the intra-alveolar capillaries and again raises PVR. Ventilation therefore targets the nadir of that curve — an open, stable lung held at functional residual capacity without tidal overdistension, using adequate but not excessive PEEP, tidal volumes of roughly 4–6 mL/kg, and a mean airway pressure high enough to recruit but not to tamponade the pulmonary capillaries. High-frequency oscillatory ventilation can recruit with a lower tidal amplitude and is a reasonable rescue, but it cannot correct an underlying volume error.
Carbon Dioxide, pH and Pulmonary Vascular Tone
Carbon dioxide and hydrogen ion concentration potently regulate pulmonary vascular tone. Hypercarbia and acidosis constrict the pulmonary circulation and sensitise it to hypoxia, whereas alkalosis dilates it. Mild permissive hypercarbia to a $PaCO_2$ of about 40–50 mmHg supports pulmonary blood flow without the cerebral vasoconstriction and ischaemia that historic hyperventilation strategies inflicted; deliberate hyperventilation below 30 mmHg is no longer acceptable. Metabolic acidosis from poor perfusion, hypothermia or hypocalcaemia must be corrected aggressively.
Systemic Blood Pressure and Right Ventricular Perfusion
Systemic hypotension is among the commonest and most correctable causes of deterioration. It lowers SVR relative to PVR, increasing right-to-left shunting, and it simultaneously reduces coronary perfusion to a hypertrophied, pressure-loaded RV, which can precipitate RV failure and cardiovascular collapse. Volume should be given judiciously, mindful of pulmonary oedema in a failing RV, and persistent hypotension should be treated with inotropes or vasopressors rather than with further increases in airway pressure.
Handling, Sedation and Thermal Stability
Because PVR is exquisitely labile, suctioning, line changes and unnecessary handling should be minimised, coordinated and pre-emptive. Adequate analgesia and sedation blunt the catecholamine surges that raise both SVR and PVR, and normothermia, normoglycaemia and normal ionised calcium remove additional vasoconstrictor stimuli. A calm, warm, well-perfused infant on a well-recruited lung is already receiving most of the therapy that PPHN requires.
Inhaled Nitric Oxide
Mechanism of Selective Pulmonary Vasodilation
iNO is delivered to the alveolus, diffuses across the alveolar membrane and binds the haem moiety of soluble guanylate cyclase (sGC) within pulmonary vascular smooth muscle. Activated sGC converts guanosine triphosphate to cyclic guanosine monophosphate (cGMP), which activates protein kinase G, lowers intracellular calcium and relaxes the smooth muscle. Selectivity arises from rapid inactivation: as NO enters the bloodstream it binds haemoglobin and becomes methaemoglobin within seconds, so its effect is confined to the pulmonary vasculature and does not cause systemic hypotension. The same property dictates its principal limitation — NO reaches only ventilated alveoli, so it dilates vessels in well-ventilated regions and can worsen ventilation–perfusion matching if the lung is collapsed. Recruitment is therefore a prerequisite for response, not an optional extra.
Dose, Acute Vasoreactivity and the Responder
The starting dose is 20 ppm, the dose validated in the pivotal trials; higher doses add nothing and increase methaemoglobin and nitrogen dioxide exposure. An acute vasoreactivity response is defined as an absolute rise in $PaO_2$ of at least 20 mmHg, or a fall in $OI$ of at least 20%, within 30–60 minutes. Responders can be weaned progressively; non-responders should be reassessed for an unrecruited lung, systemic hypotension, a misdiagnosed structural lesion or an intrinsically unsalvageable vasculopathy before dose escalation. The evidence base is best understood as a reduction in the use of ECMO rather than in mortality or bronchopulmonary dysplasia.
Weaning and Rebound Pulmonary Hypertension
Abrupt cessation of iNO can trigger rebound pulmonary hypertension, a potentially lethal deterioration driven by suppressed endogenous NO synthesis and up-regulated phosphodiesterase activity after a period of exogenous supply. Weaning should therefore be gradual: reduce to 5 ppm once stable, wean $FiO_2$ before the drug where possible, then step down by 1 ppm every 1–4 hours, watching for rebound below 5 ppm. Sildenafil introduced before or during weaning smooths the transition.
Never stop iNO abruptly. Rebound is most likely at low doses and in the first hours after withdrawal. If it occurs, restart iNO at the last effective dose, optimise lung volume and systemic pressure, and add or increase a phosphodiesterase-5 inhibitor before attempting withdrawal again.
Methaemoglobinaemia and Nitrogen Dioxide Exposure
Two toxicities require surveillance. Nitrogen dioxide forms when NO meets oxygen in the circuit and is a pulmonary irritant; inspired NO$_2$ should be kept below about 3 ppm. Methaemoglobin forms as NO binds haemoglobin and reduces oxygen-carrying capacity; it should be measured 4–8 hours after starting iNO and daily thereafter. Levels above roughly 2.5–5% warrant dose reduction or temporary withdrawal.
Monitor methaemoglobin and inspired NO$_2$ per unit protocol. A rising methaemoglobin level with paradoxically worsening oxygenation is an iatrogenic emergency: reduce or stop the drug, exclude other oxidant exposure, and consider methylene blue, ascorbate or exchange transfusion in severe cases. Do not overlook coexisting lung injury from NO$_2$.
Adjunct Pulmonary Vasodilators and Rescue Therapies
Pulmonary vasodilators act on distinct limbs of the cGMP–cAMP signalling network and can be combined when a single agent is insufficient.
| Agent | Mechanism | Typical dose | Key adverse effects |
|---|---|---|---|
| Inhaled nitric oxide | Activates soluble guanylate cyclase → cGMP → selective pulmonary vasodilation | $20\ \text{ppm}$, wean to $1\ \text{ppm}$ | Methaemoglobinaemia, NO$_2$ exposure, rebound PPHN |
| Sildenafil | Phosphodiesterase-5 inhibition → increased cGMP; potentiates and sustains iNO | IV load $0.4\ \text{mg}\cdot\text{kg}^{-1}$, then $1.6\ \text{mg}\cdot\text{kg}^{-1}\cdot\text{day}^{-1}$ (or $0.5\text{–}1\ \text{mg}\cdot\text{kg}^{-1}$ enterally every 6 h) | Systemic hypotension, retinopathy concerns in preterm infants, priapism |
| Milrinone | Phosphodiesterase-3 inhibition → increased cAMP; inotrope, lusitrope and vasodilator | $0.33\text{–}0.75\ \mu\text{g}\cdot\text{kg}^{-1}\cdot\text{min}^{-1}$ (avoid bolus) | Hypotension, arrhythmia, thrombocytopenia |
| Epoprostenol (prostacyclin) | IP-receptor activation → increased cAMP; potent vasodilation and platelet inhibition | IV $1\text{–}2\ \text{ng}\cdot\text{kg}^{-1}\cdot\text{min}^{-1}$, titrated | Systemic hypotension, flushing, bleeding, bronchospasm |
| Iloprost | Inhaled prostacyclin analogue; regional pulmonary vasodilation | Inhaled $1\text{–}2.5\ \mu\text{g}$ every 2–4 h | Similar to epoprostenol, with less systemic hypotension when inhaled |
| Magnesium sulfate | Calcium antagonism and smooth-muscle relaxation | Load $40\text{–}50\ \text{mg}\cdot\text{kg}^{-1}$, then $10\text{–}40\ \text{mg}\cdot\text{kg}^{-1}\cdot\text{h}^{-1}$ | Hypotension, hypermagnesaemia, respiratory depression |
| Bosentan | Endothelin receptor antagonist | $1\ \text{mg}\cdot\text{kg}^{-1}$ enterally every 12 h | Hepatotoxicity, hypotension, anaemia |
Sildenafil, Milrinone and Prostacyclin Analogues
Sildenafil inhibits phosphodiesterase-5, the enzyme that degrades cGMP, and therefore amplifies and prolongs the effect of endogenous and inhaled NO; it is used enterally or intravenously both as an adjunct and as a bridge during iNO weaning. Milrinone raises cyclic AMP and is particularly valuable when PPHN coexists with left ventricular dysfunction or low cardiac output, but it is a systemic vasodilator and must be used within a plan for blood-pressure support. Prostacyclin analogues — epoprostenol intravenously and iloprost by inhalation — raise cyclic AMP, dilate the pulmonary bed and inhibit platelet aggregation, with the inhaled route limiting systemic hypotension. All can cause hypotension, so they are added one at a time with continuous haemodynamic monitoring.
Sedation, Analgesia and Neuromuscular Blockade
Analgesia and sedation reduce the catecholamine surges that raise PVR and destabilise shunt fraction, and they lower oxygen consumption. Neuromuscular blockade is reserved for infants who remain refractory because of agitation or who need controlled ventilation for lung recruitment; it abolishes the spontaneous breathing that helps maintain lung volume and does not improve outcome when used routinely, so it should be time-limited and reviewed frequently.
Inotropes, Vasopressors and Surfactant
Because systemic pressure determines shunt direction, vasoactive support is central rather than adjunctive. Norepinephrine raises SVR through $\alpha_1$ agonism while providing modest $\beta_1$ inotropy; vasopressin raises SVR through $V_1$ receptors without raising pulmonary artery pressure and may even lower it. Dobutamine increases cardiac output but lowers SVR and may worsen right-to-left shunting, so it is used cautiously. Surfactant is indicated when the cause is a surfactant-deficient parenchymal disease such as meconium aspiration, respiratory distress syndrome or pneumonia; by improving recruitment it also improves the delivery of iNO to ventilated alveoli.
Extracorporeal Membrane Oxygenation
ECMO remains the ultimate rescue when pulmonary vasodilation and maximal ventilation fail. Referral criteria include a sustained $OI \geq 40$ for more than 4 hours, an alveolar–arterial oxygen gradient above 600 mmHg for 4–12 hours, or refractory hypoxaemia accompanied by haemodynamic collapse despite iNO and adjuncts.
Confirm reversible or bridgeable disease; exclude alveolar capillary dysplasia, severe irreversible lung disease and major intracranial haemorrhage; ensure adequate lung recruitment and blood-pressure support before referral; and remember that earlier consultation is safer than a late, haemodynamically collapsed transfer.
Key Takeaways
- PPHN is the failure of the normal postnatal fall in PVR, with right-to-left shunting through the ductus arteriosus and foramen ovale producing hypoxaemia that is labile and disproportionate to parenchymal disease.
- Classify the mechanism — maladaptation (vasoreactive, most responsive), maldevelopment (remodelled, less responsive) or underdevelopment (hypoplastic, sometimes unsalvageable) — because it predicts the response to vasodilators and the ceiling of therapy.
- Recognise PPHN from labile hypoxaemia and a pre-ductal minus post-ductal $SpO_2$ gradient, but confirm it with echocardiography, which estimates $PASP = 4\,v_{TR}^{2} + RAP$ and defines shunt direction.
- Quantify severity with $OI = (MAP \times FiO_2 \times 100)/PaO_2$ and, when arterial sampling is unavailable, the oxygen saturation index; escalate at $OI > 25$ and refer for ECMO at a sustained $OI \geq 40$.
- Ventilate to the nadir of the U-shaped volume–PVR relationship: recruit without overdistending, avoid atelectasis and hyperoxia, target $PaCO_2$ 40–50 mmHg, and correct acidosis.
- Defend systemic blood pressure and coronary perfusion, because hypotension increases right-to-left shunting and threatens the pressure-loaded RV.
- Inhaled nitric oxide at 20 ppm is a selective cGMP-mediated pulmonary vasodilator that works only in recruited lung; define response by acute vasoreactivity, wean slowly to avoid rebound, and monitor methaemoglobin and NO$_2$.
- Add sildenafil, milrinone or prostacyclin analogues when the iNO response is inadequate, use sedation and targeted inotropes or vasopressors, give surfactant for the underlying parenchymal disease, and escalate to ECMO early when refractory.