Meconium-stained amniotic fluid (MSAF) complicates 4–22% of births and up to 23–52% of pregnancies beyond 42 weeks, yet only 3–12% of exposed infants develop meconium aspiration syndrome (MAS). Meconium is a sterile, viscous, bile-pigmented slurry whose passage in utero signals hypoxia and acidosis, which trigger a vagal discharge increasing peristalsis and relaxing the anal sphincter.
MAS is respiratory failure in an infant born through MSAF, unexplained by another diagnosis, with typical radiology; it affects the near-term, term and post-term infant, because meconium is rarely passed before 34 weeks. Its therapeutic difficulty is structural: the lung holds both atelectatic, surfactant-deficient units that resist recruitment and overdistended, gas-trapped units that rupture easily, so air leak often converts a controlled course into a catastrophe.
Respiratory failure in a neonate born through MSAF, not otherwise explained, with typical radiology. Severity: mild (FiO₂ < 0.40 for < 48 h), moderate (FiO₂ > 0.40 for > 48 h without air leak), severe (ventilation > 48 h and/or pulmonary hypertension).
Definition, Epidemiology and Clinical Recognition
Incidence rises exponentially from 38 to 42 weeks. About 20% of affected infants are non-vigorous at birth, one third require ventilation, 5–12% die, 15–20% develop pulmonary hypertension and 15–33% sustain air leak; MAS explains about 10% of neonatal respiratory failure.
Recognition
The term or post-term infant has meconium staining of skin, nails and cord, with tachypnoea, cyanosis, retractions, a barrel chest and widespread crackles within hours. The radiograph shows hyperinflation with coarse "cotton-wool" infiltrates alternating with hypertransparent areas and may reveal air leak; radiographic severity correlates poorly with clinical severity. Severity is quantified by the oxygenation index, $\text{OI} = (\text{MAP} \times \text{FiO}_2 \times 100)/P_a\text{O}_2$, where MAP is mean airway pressure (cmH₂O) and PₐO₂ preductal arterial oxygen tension (mmHg); an OI above 40 sustained for over 4 hours is an ECMO threshold.
Pathophysiology
Five processes converge on ventilation–perfusion mismatch and air leak (Figure 1).
Meconium as a marker of fetal distress
Meconium passage is a vagally mediated response to hypoxia and acidosis, associated with placental insufficiency, pre-eclampsia and intrauterine infection. Thick meconium, a pathological cardiotocograph and fetal acidosis increase the risk of established disease.
Mechanical airway obstruction: complete and ball-valve
A complete plug prevents gas entry, so subtended alveoli collapse and shunt. Partial obstruction produces a ball-valve effect: gas enters on positive pressure but cannot readily leave, so each breath adds volume and units overdistend. An obstructed unit's behaviour is governed by its time constant:
$$\tau = R \times C$$where $\tau$ is the respiratory time constant (s), $R$ airway and tissue resistance (cmH₂O·s·L⁻¹) and $C$ respiratory system compliance (L·cmH₂O⁻¹). Emptying is exponential, $V(t) = V_0 \, e^{-t/\tau}$, with $V_0$ the end-inspiratory volume (mL), so the retained fraction at end-expiration is $e^{-T_e/\tau}$ and complete emptying requires $T_e$ of about three time constants. Meconium raises $R$ and lengthens $\tau$: with $R = 60$ cmH₂O·s·L⁻¹ and $C = 0.005$ L·cmH₂O⁻¹, $\tau \approx 0.3$ s, so $T_e$ must exceed 0.9 s; a $T_e$ of 0.4 s retains $e^{-0.4/0.3} \approx 0.26$, trapping a quarter of each breath and stacking volume until alveoli rupture.
A neonate with MAS may have a time constant several times normal, so an apparently reasonable rate can cause occult gas trapping. Prefer lower rates, longer expiratory times and vigilance for a rising end-expiratory volume.
Chemical pneumonitis and the inflammatory cascade
Meconium lipids and proteins are directly toxic to alveolar epithelium and endothelium and recruit neutrophils with complement activation, releasing interleukin-1, interleukin-6, interleukin-8 and tumour necrosis factor, producing chemical pneumonitis with capillary leak and oedema. Meconium also impairs the bacteriostatic property of amniotic fluid, so secondary infection must be considered although meconium is sterile.
Surfactant inactivation
Meconium fatty acids and bile salts displace surfactant from the alveolar surface, reduce surfactant proteins A and B and accelerate conversion of active large aggregates into less active forms, producing a surfactant-deficient, low-compliance lung with atelectasis and shunt.
Pulmonary hypertension
Pulmonary vascular resistance rises through hypoxia-, hypercapnia- and acidosis-driven vasoconstriction, remodelling after intrauterine hypoxia, and compression of vessels by hyperexpanded units. Right-to-left shunting worsens hypoxaemia and further raises resistance; PPHN is the principal determinant of severity and mortality.
Secondary air leak
Gas trapping and the pressures needed to recruit collapsed segments rupture alveolar and perivascular tissue, and air tracks into the interstitium, mediastinum, pleura and pericardium. Air leak is thus a predictable mechanical consequence of MAS.
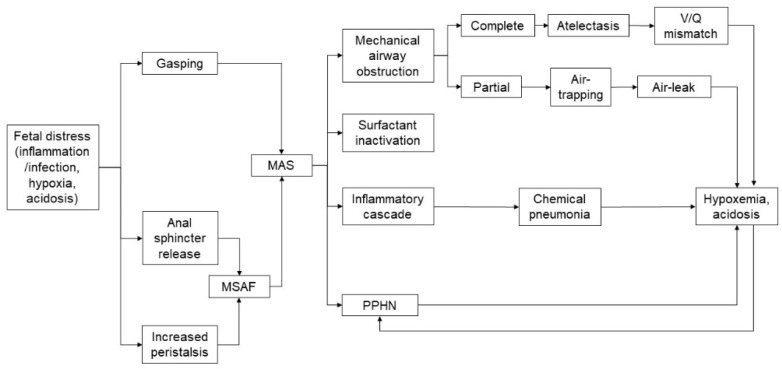 Figure 1: Pathophysiology of MAS: obstruction with ball-valve trapping, surfactant inactivation, chemical pneumonitis and pulmonary hypertension converge on V/Q mismatch and air leak. (Source: Monfredini C, Cavallin F, Villani PE, et al. Children (Basel) 2021;8(3):230. DOI: 10.3390/children8030230).
Delivery-Room Management and the Reversal of Practice
Historical rationale
The first recommendation for tracheal suctioning dates to 1960, when Stanley James reasoned that aspirated meconium should be removed before it migrated distally; by the mid-1970s, routine oro- and nasopharyngeal and endotracheal suctioning had become standard.
Evidence that changed practice
A 2000 multicentre trial showed no benefit of intubation and tracheal suctioning in vigorous meconium-stained infants, narrowing the recommendation to non-vigorous infants, and a 2004 trial showed no benefit of intrapartum oro- and nasopharyngeal suctioning before shoulder delivery in term infants. Intubation of non-vigorous infants persisted until 2015, when the International Liaison Committee on Resuscitation judged the evidence insufficient and restricted intubation to infants with suspected airway obstruction; the 2020 consensus confirmed this.
Current NRP approach
Current Neonatal Resuscitation Program (NRP) guidance manages an infant born through MSAF by the standard algorithm: if vigorous and breathing effectively, give routine care and do not suction the trachea; if not breathing effectively, provide positive pressure ventilation without delay and reserve intubation for suspected airway obstruction. The change was driven by procedure-related harm (apnoea, bradycardia, airway and oesophageal injury, vocal cord trauma, stridor) and by the delay to effective ventilation.
Do not routinely intubate and suction non-vigorous infants born through meconium-stained fluid. Prioritise positive pressure ventilation and reserve intubation for suspected airway obstruction. Gastric lavage is not recommended.
Ventilation Strategy for MAS
About 40% of infants with MAS require mechanical ventilation, and no randomised trial defines an optimal strategy.
Gentle ventilation and permissive hypercapnia
Use the lowest pressures and tidal volumes achieving adequate gas exchange, with a pragmatic peak inspiratory pressure ceiling of 25 cmH₂O beyond which high-frequency ventilation should be considered. Tolerate hypercapnia, targeting pH 7.25–7.40 and PₐCO₂ 40–55 mmHg to avoid respiratory alkalosis.
PEEP, tidal volume and expiratory time
PEEP of about 5–7 cmH₂O stents open obstructed airways, recruits atelectatic units and reduces cyclic shear, but excessive PEEP overdistends trapped regions. Expiratory time should be generous, because gas trapping is the dominant hazard, and tidal volumes should stay physiological with volume-targeted modes.
Surfactant
Exogenous surfactant is recommended for intubated infants with FiO₂ > 0.50, as a bolus or bronchoalveolar lavage, improving oxygenation and reducing ECMO use; evidence for reduced mortality or air leak is lacking, and lavage remains investigational.
Inhaled nitric oxide
For pulmonary hypertension, start inhaled nitric oxide (iNO) at 20 ppm after optimising recruitment and haemodynamic support, typically when the oxygenation index reaches 15–25. A response is a rise in PₐO₂ of at least 20 mmHg within 30 minutes; higher doses add nothing. Wean slowly to avoid rebound.
High-frequency ventilation
High-frequency oscillatory ventilation (HFOV) reduces barotrauma, improves recruitment homogeneity and lowers air-leak risk, and is rational when peak inspiratory pressure exceeds 25–28 cmH₂O, with mean airway pressure titrated to avoid overdistension.
Antibiotics
Prophylactic antibiotics are not indicated: meconium is sterile and uncomplicated MAS is not linked to sepsis. Start broad-spectrum antibiotics when perinatal infectious risk factors are present and stop at 48–72 hours if cultures are negative.
flowchart TD
    A["Infant born through meconium-stained fluid"] --> B{"Vigorous and breathing effectively?"}
    B -->|"Yes"| C["Routine care; no tracheal suctioning"]
    B -->|"No"| D["Positive pressure ventilation; intubate only if obstruction suspected"]
    D --> E["Assess severity"]
    E -->|"Mild"| F["Oxygen; preductal SpO2 92-97 percent"]
    E -->|"Moderate"| G["Nasal CPAP 6-8 cmH2O"]
    E -->|"Severe"| H["Intubate; volume-targeted ventilation; PEEP 5-7; PIP below 25 cmH2O"]
    H --> I["Surfactant if FiO2 above 0.50; antibiotics if infection suspected"]
    H --> K{"Hypoxaemia or oxygenation index 15-25?"}
    K -->|"Yes"| L["Start inhaled nitric oxide 20 ppm"]
    K -->|"No"| M["Continue lung-protective ventilation"]
    L --> N{"Improving?"}
    N -->|"Yes"| O["Wean iNO slowly"]
    N -->|"No"| P["HFOV; ECMO if oxygenation index above 40"]
Pulmonary Air-Leak Syndromes
Air from ruptured alveoli tracks along fascial planes; the syndromes differ by compartment, and their danger depends on whether that compartment can decompress. Risk factors combine vulnerable tissue (MAS, RDS, prematurity, resuscitation) with injudicious ventilation — high peak pressures, large tidal volumes, uneven regional ventilation, low or excessive PEEP and asynchrony.
| Syndrome | Site | Mechanism | Recognition | Management |
|---|---|---|---|---|
| Pneumothorax | Pleural space | Alveolar rupture through visceral pleura | Asymmetry, reduced breath sounds, positive transillumination | Aspirate if symptomatic; drain if persistent |
| Tension pneumothorax | Pleural space, pressurised | One-way leak with mediastinal shift | Sudden desaturation, bradycardia, hypotension | Immediate needle decompression, then drain |
| Pulmonary interstitial emphysema | Perivascular interstitium | High transpulmonary pressure forces gas into interstitium | Early hyperinflation with reticular or cystic lucencies | Reduce PIP and mean pressure; consider HFOV |
| Pneumomediastinum | Mediastinum | Gas along peribronchial sheaths | "Angel wing" sign; neck crepitus | Usually conservative |
| Pneumopericardium | Pericardial sac | Gas dissecting into pericardium | Muffled heart sounds, bradycardia; lucent halo around heart | Pericardiocentesis for tamponade |
| Pneumoperitoneum | Peritoneum | Gas tracking through the diaphragm | Abdominal distension; free gas under diaphragm | Observe; decompress if ventilation compromised |
| Subcutaneous emphysema | Subcutaneous tissue | Gas from mediastinum or pleura | Palpable crepitus of chest wall and neck | Supportive; treat the source |
Tension pneumothorax and pulmonary interstitial emphysema
A one-way pleural leak admits gas during inspiration but not expiration, so intrapleural pressure rises, the mediastinum shifts, venous return falls and cardiac output collapses; the presentation — desaturation, bradycardia, hypotension and a tense, distended chest — is a clinical diagnosis treated before imaging. Pulmonary interstitial emphysema (PIE), the dissection of gas along perivascular and interlobular septa under high transpulmonary pressure, appears as early hyperinflation with reticular or cystic lucencies and often antedates pneumothorax, signalling the need to reduce airway pressures.
Pneumomediastinum, pneumopericardium and pneumoperitoneum
Pneumomediastinum is usually well tolerated, producing the "angel wing" or continuous diaphragm sign and neck crepitus. Pneumopericardium is far more dangerous: the pericardium cannot decompress itself, so gas causes tamponade with muffled heart sounds, bradycardia and collapse, and pericardiocentesis is definitive. Gas tracking through the mediastinum can also reach the peritoneum, mimicking a perforated viscus, though it is usually managed conservatively in a ventilated infant with other air leak.
Recognition and Emergency Management
Clinical signs and transillumination
Suspect air leak when a ventilated neonate deteriorates abruptly. Cardinal signs are asymmetry, reduced breath sounds and a sudden rise in oxygen requirement; tension physiology adds mediastinal shift, a distended abdomen and cardiovascular collapse. Cold-light transillumination is a rapid adjunct: light transmitted through pleural gas glows brightly, whereas normal lung attenuates it.
Radiography and ultrasound
A radiograph confirms pneumothorax as a lucent hemithorax with absent lung markings and a visible visceral pleural edge, while in the supine infant air collects anteriorly and may appear only as an unusually sharp cardiothymic outline. Lung ultrasound — absent lung sliding and a lung point — is a useful adjunct but must not delay decompression in a crashing infant.
Needle thoracentesis versus chest drain
In a stable infant, image-guided needle aspiration with a 22- to 24-gauge cannula and three-way tap, inserted just above the rib, may evacuate the air and obviate a drain; a drain is required for persistent, recurrent or large leaks and bilateral collections. In tension pneumothorax, needle decompression is immediate and is followed by a formal chest drain with an underwater seal.
Needle aspiration can be definitive for a stable infant with a small collection, but a chest drain is mandatory when the lung fails to re-expand or leak persists on positive pressure ventilation.
Time-critical emergencies
Tension pneumothorax and pneumopericardium both obstruct venous return, but the interventions differ: pleural air is released by thoracentesis and drainage, pericardial air by pericardiocentesis. Muffled heart sounds, raised venous pressure and a lucent halo around the heart suggest pneumopericardium.
Sudden desaturation, bradycardia and hypotension during positive pressure ventilation with a positive transillumination justify immediate needle decompression; imaging that delays decompression converts a reversible emergency into a cardiac arrest.
flowchart TD
    A["Sudden desaturation, bradycardia or hypotension on ventilation"] --> B["Asymmetry, absent breath sounds, mediastinal shift, distended abdomen"]
    B --> C["Cold-light transillumination"]
    C --> D{"Bright glow with absent lung markings?"}
    D -->|"Yes"| E["Tension pneumothorax; do not wait for radiograph"]
    D -->|"No"| F["Urgent radiograph or lung ultrasound"]
    E --> G["Immediate needle thoracentesis above the rib with three-way tap"]
    G --> H["Insert chest drain with underwater seal"]
    F --> I{"Air leak confirmed?"}
    I -->|"Yes"| J["Aspirate if symptomatic; drain if persistent"]
    I -->|"No"| K["Reassess for pneumopericardium, PIE or tube obstruction"]
    E --> L{"Collapse despite pleural decompression?"}
    L -->|"Yes"| M["Suspect pneumopericardium; perform pericardiocentesis"]
    L -->|"No"| H
Prevention
Lung-protective ventilation
Use volume-targeted modes to avoid large tidal volumes, keep peak inspiratory pressure below the air-leak threshold, and set PEEP to prevent cyclic collapse without overdistending trapped lung. Avoid asynchrony, since an active expiratory effort against a delivered breath raises transpulmonary pressure abruptly; when these measures fail, high-frequency oscillation distributes ventilation more homogeneously.
The "PIP creep" trap
The most insidious error is gradual, unscrutinised escalation of peak inspiratory pressure. Faced with falling saturation, the clinician increases PIP; some compliant units open, but overdistended, badly ventilated units receive the same pressure and rupture. Because improvement is transient, another increment follows — a self-reinforcing cycle in which the pursuit of oxygenation creates the air leak that worsens it.
Any upward trend in peak inspiratory pressure without improved oxygenation should prompt a change in strategy. Recruit with appropriate PEEP and expiratory time, treat pulmonary hypertension, and escalate to high-frequency ventilation rather than raising peak pressure indefinitely.
Key Takeaways
- MAS is respiratory failure in an infant born through meconium-stained fluid; MSAF complicates 4–22% of births, but only 3–12% of exposed infants develop MAS.
- Its pathophysiology converges on complete and ball-valve airway obstruction, chemical pneumonitis, surfactant inactivation, pulmonary hypertension and secondary air leak.
- The time constant $\tau = R \times C$ explains gas trapping: meconium lengthens $\tau$, and if expiratory time is shorter than about three time constants, gas stacks and ruptures alveoli.
- Current NRP guidance does not recommend routine intubation and tracheal suctioning for non-vigorous infants born through MSAF; ventilate without delay and reserve intubation for suspected airway obstruction.
- Ventilation should be gentle and lung-protective, with permissive hypercapnia, PEEP about 5–7 cmH₂O and a generous expiratory time; use surfactant for a high oxygen requirement, iNO for pulmonary hypertension and antibiotics only when infection is suspected.
- Tension pneumothorax and pneumopericardium are time-critical emergencies treated by needle decompression and drainage, and by pericardiocentesis, without awaiting radiography.
- Prevention rests on lung-protective ventilation, correct PEEP, adequate expiratory time and vigilance against "PIP creep".