High-frequency oscillatory ventilation (HFOV) is a lung-protective mode that holds a near-constant, recruited lung volume while oscillating airway pressure around a fixed mean airway pressure (MAP). A piston or electromagnetic diaphragm superimposes a small sinusoidal oscillation on a continuous bias flow of fresh gas, so each "breath" is a fraction of anatomical dead space.
Tidal volumes of $1-2\text{ mL/kg}$ at $8-15\text{ Hz}$ ($480-900$ oscillations/min) are smaller than the neonatal dead space ($\approx 2.2\text{ mL/kg}$), so gas exchange cannot rest on bulk convection alone, and HFOV recruits additional transport mechanisms. Because the oscillator also withdraws gas during an active expiratory phase, it differs fundamentally from high-frequency jet ventilation (HFJV), in which exhalation is passive. These two features — sub-dead-space volumes and active expiration — explain how the oscillator is set, monitored, and misapplied.
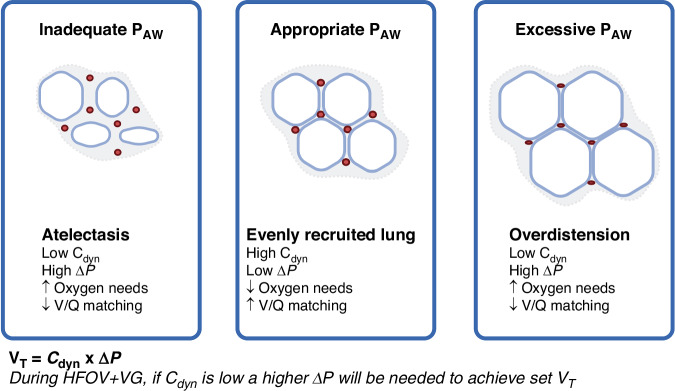 Figure 1: During HFOV the mean airway pressure determines the lung-volume state, which in turn governs dynamic compliance, oxygenation, and pulmonary perfusion; even when the targeted tidal volume is correct, an inappropriate mean airway pressure produces an unnecessarily high pressure amplitude and uneven regional volume delivery. (Source: Tingay DG, Dahm SI, Sett A. Pediatric Research 2025. DOI: 10.1038/s41390-025-04015-y).
Physical Principles of Oscillation
The Oscillator, Bias Flow, and Mean Airway Pressure
HFOV does not deliver discrete breaths. A piston or electromagnetic diaphragm oscillates a column of gas while a continuous bias flow of heated, humidified gas sweeps the circuit. The bias flow supplies fresh gas, washes expired carbon dioxide out of the circuit, and sustains the mean airway pressure against which the oscillation is superimposed. At the airway opening the result is a near-sinusoidal pressure waveform with a small peak-to-trough excursion (the amplitude) around a steady, high mean.
The design dissociates oxygenation from ventilation. MAP — also called the continuous distending pressure (CDP) — is the sustained pressure holding the lung inflated, and it is the principal determinant of alveolar recruitment, functional residual capacity, and oxygenation. Amplitude and frequency set the tiny tidal volume and therefore carbon dioxide clearance. This decoupling is the central conceptual feature of HFOV (Figure 1).
On HFOV the mean airway pressure, not the amplitude, governs oxygenation. Because the lung is held open continuously rather than cyclically recruited and de-recruited, oxygenation is optimised by titrating MAP to the point of maximal recruitment — the open-lung strategy — and then finding the lowest pressure that preserves it.
Tidal Volume, Frequency, and Active Expiration
The frequency of oscillation relates to the period of a single oscillation by the reciprocal relationship:
$$T = \frac{1}{f}$$where $T$ is the period of one oscillation in seconds ($\text{s}$) and $f$ is the frequency in hertz ($\text{Hz}$, oscillations per second). Because clinicians also think in breaths per minute:
$$f_{\text{min}} = 60\,f \quad\Rightarrow\quad 8-15\text{ Hz} = 480-900\text{ oscillations/min}$$The delivered oscillatory tidal volume depends on both the pressure amplitude and the frequency. At fixed frequency and mechanics the volume moved rises in proportion to the amplitude; at fixed amplitude, raising the frequency reduces the volume, because the same pressure is applied for a shorter time against the impedance of the respiratory system and endotracheal tube:
$$V_T \approx k \cdot \frac{\Delta P}{f}$$where $V_T$ is the delivered oscillatory tidal volume ($\text{mL}$ or $\text{mL/kg}$), $\Delta P$ is the airway pressure amplitude set at the ventilator (the "power", in $\text{cmH}_2\text{O}$), $f$ is the frequency ($\text{Hz}$), and $k$ is a lumped constant reflecting the elastance, resistance, and inertance of the respiratory system and endotracheal tube. A stiff, low-compliance lung transmits less of the set amplitude to the alveoli and therefore delivers a smaller volume for the same dial setting.
HFOV's other defining feature is that expiration is active: the oscillator reversibly withdraws gas from the airway, whereas HFJV relies on passive elastic recoil. Active expiration reduces dependence on expiratory time and makes gas trapping less likely than with jet ventilation — provided that excessive MAP does not over-distend the lung.
Mechanisms of Gas Transport During HFOV
Bulk Convection and Taylor Dispersion
Bulk convection — direct movement of gas down the tracheobronchial tree — explains transport only in the most proximal airways. The dominant mechanism at high frequency is Taylor dispersion, or augmented axial diffusion. Oscillatory flow has a parabolic velocity profile, so gas in the centre of the lumen travels faster than gas near the wall, and each flow reversal continuously redistributes gas radially. Axial transport is thereby enhanced by orders of magnitude over molecular diffusion, allowing fresh gas to penetrate deeply despite the tiny stroke volume; the steeper velocity gradients at higher frequency sustain this effect.
Gas transport during HFOV arises from several simultaneous mechanisms: bulk convection, Taylor dispersion (augmented axial diffusion), pendelluft, molecular diffusion, and cardiogenic mixing. No single mechanism is sufficient; together they maintain gas exchange with tidal volumes below dead space.
Pendelluft, Molecular Diffusion, and Cardiogenic Mixing
Pendelluft ("pendulum air") is gas shuttling between adjacent units of differing time constants or regional impedance without ever reaching the airway opening, mixing regions that bulk flow would bypass. It is especially relevant in the heterogeneous, partly atelectatic preterm lung, and is one reason regional recruitment matters.
Molecular diffusion completes transport across the terminal gas-exchanging units, following Fick's law across the alveolar–capillary membrane. Because carbon dioxide is far more soluble than oxygen, it equilibrates rapidly once delivered, so diffusion is rarely the rate-limiting step for $\text{CO}_2$ clearance at the volumes used clinically.
Cardiogenic mixing describes agitation of alveolar gas by transmitted cardiac oscillations and pulsatile pulmonary blood flow, which augments peripheral mixing and is most appreciable when cardiac output is good. A falling cardiac output can therefore degrade gas exchange for reasons unrelated to the ventilator settings.
Ventilator Settings and Their Physiological Meaning
Mean Airway Pressure: The Oxygenation Lever
MAP is titrated against oxygenation. A common starting point is a MAP $1-2\text{ cmH}_2\text{O}$ above that required on conventional ventilation, followed by escalation in $1-2\text{ cmH}_2\text{O}$ steps to recruit atelectatic lung. The goal is the lowest distending pressure that achieves the target oxygenation, usually an $\text{FiO}_2 \le 0.30-0.40$, judged alongside radiographic lung inflation. Escalating MAP beyond radiographic full inflation converts a recruitment strategy into a hyperinflation strategy.
Increase MAP in $1-2\text{ cmH}_2\text{O}$ steps until oxygenation improves and the radiograph shows the diaphragm at the eighth to ninth posterior rib. Then reduce MAP in $1-2\text{ cmH}_2\text{O}$ steps to find the closing pressure at which oxygenation deteriorates, and set MAP just above it.
Amplitude, Power, and Frequency: The Ventilation Levers
Carbon dioxide clearance is governed principally by the delivered tidal volume, which is manipulated through the amplitude and, to a lesser extent, the frequency. The classical proportionality is:
$$\dot{V}_{CO_2} \propto f \cdot V_T^{2}$$where $\dot{V}_{CO_2}$ is carbon dioxide elimination ($\text{mL/min}$). Substituting the volume–amplitude relationship $V_T \approx k \cdot \Delta P / f$:
$$\dot{V}_{CO_2} \propto f \cdot \left(\frac{\Delta P}{f}\right)^{2} = \frac{\Delta P^{2}}{f}$$The squared dependence on amplitude makes amplitude the most powerful lever for hypercapnia: a small rise in $\Delta P$ produces a proportionally larger rise in tidal volume and thus in clearance. The inverse dependence on frequency explains the counter-intuitive observation that lowering the frequency can lower the $\text{PaCO}_2$ — at fixed amplitude a slower oscillation delivers a larger volume, and the squared volume term outweighs the reduced rate.
For persistent hypercapnia, first exclude tube obstruction, leak, or disconnection. Then increase amplitude (power) in small steps, reassessing $\text{PaCO}_2$ or transcutaneous $\text{CO}_2$. If needed, decrease frequency by $1\text{ Hz}$ to raise delivered volume. Do not raise MAP to correct hypercapnia.
Inspiratory:Expiratory Ratio, Bias Flow, and the Clinical Wiggle
The inspiratory-to-expiratory (I:E) ratio is usually $1:1$ or $1:2$. It influences mean airway pressure and the expiratory time available for gas egress: a ratio favouring inspiration raises mean pressure, whereas adequate expiratory time limits gas trapping. Bias flow is typically set between $8$ and $20\text{ L/min}$ in neonates — high enough to clear circuit carbon dioxide and sustain the oscillation without requiring excessive amplitude.
Clinically, the oscillation is confirmed by the "wiggle": a fine visible vibration of the infant's chest wall and, on many ventilators, of the tubing. Its presence and amplitude are a real-time surrogate for transmission of the oscillator to the lung. A diminished or absent wiggle demands an immediate search for the "DOPES" causes — Displacement of the tube, Obstruction, Pneumothorax, Equipment failure, and Stacked breaths — and in particular for a circuit leak, tube malposition or blockage, or pneumothorax.
| Parameter | Typical Neonatal Setting | Physiological Meaning | Titration Goal |
|---|---|---|---|
| Mean airway pressure (MAP / CDP) | $1-2\text{ cmH}_2\text{O}$ above prior CMV MAP (commonly $10-14\text{ cmH}_2\text{O}$) | Sustained lung inflation; sets FRC and recruited volume | Oxygenation: escalate in $1-2\text{ cmH}_2\text{O}$ steps to $\text{FiO}_2 \le 0.30-0.40$, then reduce to closing pressure |
| Amplitude / power ($\Delta P$) | Set to produce a visible wiggle, then titrated to $\text{PaCO}_2$ | Determines delivered tidal volume ($V_T \approx k\,\Delta P / f$) | Ventilation: increase for hypercapnia (squared effect) |
| Frequency ($f$) | $10-15\text{ Hz}$ ($10\text{ Hz}$ term/MAS; $12-15\text{ Hz}$ ELBW) | Sets the period ($T = 1/f$) and, via impedance, the delivered volume | Ventilation: decrease by $1\text{ Hz}$ if amplitude alone is insufficient |
| I:E ratio | $1:1$ or $1:2$ | Affects mean pressure and expiratory time | Avoid gas trapping |
| Bias flow | $8-20\text{ L/min}$ | Fresh-gas washout of $\text{CO}_2$; sustains the oscillation | Adequate amplitude with minimum flow |
| $\text{FiO}_2$ | Titrated to target $\text{SpO}_2$ $91-95\%$ | Oxygen delivery | Wean below $0.40$ as MAP is optimised |
Indications and the Trial Evidence
Where HFOV Is Used
HFOV is principally a rescue mode for infants in whom conventional ventilation cannot achieve adequate gas exchange at acceptable pressures. Recognised rescue indications include severe respiratory distress syndrome (RDS) with refractory hypoxaemia or hypercapnia, air-leak syndromes such as pulmonary interstitial emphysema and pneumothorax with bronchopleural fistula, meconium aspiration syndrome (MAS), congenital diaphragmatic hernia (CDH), and persistent pulmonary hypertension of the newborn (PPHN) with severe parenchymal disease. The small tidal volumes and low alveolar pressure swings are attractive in air leak, because they minimise the cyclic stretch that propagates air dissection; in CDH and MAS, HFOV provides recruitment and carbon dioxide clearance while limiting peak pressures.
Oscillation Versus Conventional Ventilation
Whether HFOV should be used early and electively, rather than as a rescue, has been tested in large randomised trials and systematic reviews. The consistent conclusion is that elective HFOV does not clearly reduce death or bronchopulmonary dysplasia, and may signal harm when applied with a low-volume strategy or in inexperienced hands. Practice has therefore shifted: HFOV is best regarded as a rescue strategy for selected infants rather than a routine first-line mode. Outcomes depend less on the mode itself than on how it is applied — the distinction between high-volume (open-lung) and low-volume strategies has proved decisive, and unit expertise, access to transcutaneous $\text{CO}_2$ monitoring, and prompt recognition of over-distension materially influence results.
| Feature | Conventional ventilation (with volume guarantee) | High-frequency oscillatory ventilation |
|---|---|---|
| Tidal volume | $4-6\text{ mL/kg}$ | $1-2\text{ mL/kg}$ (often below dead space) |
| Rate | $30-60$ breaths/min | $480-900$ oscillations/min ($8-15\text{ Hz}$) |
| Expiration | Passive (elastic recoil) | Active (oscillator withdraws gas) |
| Lung volume | Cyclic inflation and deflation | Near-constant volume at set MAP |
| Main oxygenation lever | $\text{FiO}_2$, PEEP, MAP | MAP (CDP) |
| Main $\text{CO}_2$ lever | Tidal volume and rate | Amplitude ($\Delta P$), then frequency |
| Principal hazard | Volutrauma and atelectrauma | Over-distension, air leak, impaired venous return |
| Typical role | First-line support | Rescue after failed conventional ventilation |
Monitoring, Troubleshooting, and Weaning
Assessing Lung Inflation
Lung inflation is the single most important monitoring task, because over-distension causes most of the mode's serious complications. Serial chest radiographs are the anchor: the diaphragm should lie at the eighth to ninth posterior rib with no more than nine ribs visible, and bowing below the ninth rib signals dangerous hyperinflation. Oxygenation is a continuous physiological surrogate — a falling $\text{SpO}_2$ or rising oxygen requirement despite escalating MAP suggests either inadequate recruitment or, paradoxically, over-distension with capillary compression. Electrical impedance tomography can refine the assessment in research settings, but the radiograph, oxygenation, and haemodynamics remain the practical bedside triad.
Manipulating CO₂ Clearance
Hypercapnia is corrected by increasing the delivered volume, not the distending pressure. Amplitude is increased in small increments, because of its squared effect on $\text{CO}_2$ elimination, and the response confirmed with arterial or transcutaneous $\text{CO}_2$ measurements. If maximal amplitude is insufficient, reducing the frequency by $1\text{ Hz}$ raises the delivered volume at constant amplitude and can produce a further fall in $\text{PaCO}_2$. Persistent hypercapnia despite these measures should prompt a search for mechanical causes: a leaking or obstructed endotracheal tube, a blocked circuit, inadequate bias flow, or a pneumothorax. A clinician must never respond to hypercapnia by increasing MAP, which only worsens over-distension.
Air Leak, Over-Inflation, and Under-Inflation
Over-inflation is the most feared acute event on HFOV. Excessive MAP raises intrathoracic pressure, compresses the pulmonary capillaries, and impedes venous return, producing falling oxygenation, systemic hypotension, and reduced cardiac output — a picture that can mimic sepsis or cardiac failure. The response is a prompt reduction of MAP by $1-2\text{ cmH}_2\text{O}$ steps with concurrent reassessment of oxygenation, blood pressure, and the radiograph. Tension pneumothorax requires immediate needle decompression, because positive-pressure oscillation enlarges it rapidly. Under-inflation with atelectasis presents as poor oxygenation and low lung volume, and is corrected by increasing MAP. Asymmetric inflation or wiggle should raise suspicion of an endobronchial tube position, a mucus plug, or a localised pneumothorax.
Falling oxygenation with systemic hypotension on HFOV is hyperinflation until proven otherwise. Reduce MAP immediately in $1-2\text{ cmH}_2\text{O}$ steps and reassess. Do not increase MAP for a falling $\text{SpO}_2$ until over-distension has been excluded.
flowchart TD
    Start["Neonate on HFOV: confirm wiggle, tube position, circuit integrity"] --> Gas["Measure oxygenation and ventilation"]
    Gas --> Oxy{"Oxygenation adequate? FiO2 0.30-0.40 or less"}
    Oxy -->|"No, hypoxaemia"| MapUp["Increase MAP by 1-2 cmH2O"]
    MapUp --> CXR["Assess CXR: diaphragm at 8-9 posterior ribs"]
    CXR --> Over{"Over-distension or hypotension?"}
    Over -->|"Yes"| MapDown["Reduce MAP by 1-2 cmH2O"]
    MapDown --> Gas
    Over -->|"No"| Oxy
    Oxy -->|"Yes"| Vent{"Ventilation adequate? PaCO2 4.5-6.5 kPa"}
    Vent -->|"No, hypercapnia"| AmpUp["Increase amplitude 1-2 units"]
    AmpUp --> Vent
    Vent -->|"Persistent hypercapnia"| FreqDown["Decrease frequency by 1 Hz"]
    FreqDown --> Vent
    Vent -->|"Yes"| Wean["Wean MAP then amplitude; transition to conventional ventilation or CPAP"]
    Wean --> Gas
Weaning and Transition
Weaning begins once oxygenation is stable on an $\text{FiO}_2 \le 0.40$ with acceptable gas exchange. MAP is reduced first, in $1\text{ cmH}_2\text{O}$ decrements every few hours, reassessing oxygenation and lung volume after each step, because excessive distension is the mode's principal risk. Amplitude is then reduced as ventilation permits. When MAP has fallen to roughly $8-10\text{ cmH}_2\text{O}$ and the infant is stable, many units transition to a volume-guaranteed conventional mode before considering extubation to non-invasive support. The transition should be planned and unhurried, watching for atelectasis as the distending pressure falls.
Practical Set-Up and Initial Parameters
Confirm that the oscillator circuit is correctly assembled and leak-free, that the heated humidifier is working (inadequate humidification risks necrotising tracheobronchitis), and that an appropriately sized, securely positioned endotracheal tube is in place. Ensure the sedation and analgesia plan is adequate, since an unsettled infant fights the oscillator and transmits less of the amplitude to the lung; some units use brief neuromuscular blockade during initial recruitment.
For initial parameters, set the MAP $1-2\text{ cmH}_2\text{O}$ above the prior conventional MAP (higher in CDH and MAS, where a greater distending pressure is often required), the frequency at $10\text{ Hz}$ for term infants and $12-15\text{ Hz}$ for extremely low birth weight infants, and the amplitude to produce a clearly visible wiggle before titrating to the $\text{PaCO}_2$. Begin the I:E ratio at $1:1$ or $1:2$ and the bias flow between $8$ and $20\text{ L/min}$. After any change, reassess the blood gas, the chest radiograph, and haemodynamics rather than the ventilator numbers alone.
A sudden loss of the chest-wall wiggle is never normal. Check for tube displacement or obstruction, circuit disconnection or leak, pneumothorax, and equipment failure before adjusting any ventilator setting.
Key Takeaways
- HFOV holds the lung open at a constant mean airway pressure and superimposes a small oscillation, delivering tidal volumes of $1-2\text{ mL/kg}$ at $8-15\text{ Hz}$ ($480-900$ oscillations/min) — often below anatomical dead space.
- Oxygenation is controlled by MAP through alveolar recruitment; ventilation is controlled predominantly by the amplitude, with frequency as a secondary lever.
- HFOV is distinguished from HFJV by its active expiratory phase, in which the oscillator withdraws gas rather than relying on passive elastic recoil.
- Because tidal volume is smaller than dead space, gas transport depends on bulk convection, Taylor dispersion, pendelluft, molecular diffusion, and cardiogenic mixing acting together.
- Carbon dioxide clearance scales with $f \cdot V_T^{2}$, and since $V_T \approx k\,\Delta P / f$, it scales with $\Delta P^{2}/f$ — making amplitude the dominant lever and explaining why a lower frequency can improve $\text{CO}_2$ clearance.
- Use HFOV as a rescue mode for severe RDS, air-leak syndromes, MAS, CDH, and PPHN; randomised evidence shows no clear mortality or BPD benefit from elective use, and outcomes depend heavily on an open-lung strategy and local expertise.
- Monitor lung inflation with radiographs (diaphragm at the eighth to ninth posterior rib) and oxygenation, and treat falling oxygenation with hypotension as over-distension requiring an immediate MAP reduction.