Congenital diaphragmatic hernia (CDH) is the herniation of abdominal viscera through a defect in the diaphragm into the thoracic cavity, occurring in approximately 1 in 2,500 to 3,500 live births. It is not principally a surgical disease of the diaphragm but a developmental disorder of the lung. The herniated viscera and the underlying genetic and teratogenic insult together produce bilateral pulmonary hypoplasia, delayed surfactant maturation, and a structurally abnormal pulmonary vascular bed. It is the resulting pulmonary hypertension, rather than the size of the diaphragmatic defect, that determines early survival.
The management of CDH has therefore shifted decisively from an operative emergency to a physiological one. The infant who reaches the neonatal intensive care unit is stabilised before, not after, surgical repair: mask ventilation is avoided, the stomach and herniated bowel are decompressed, the trachea is intubated early, and the ventilator is used gently enough to avoid injuring a lung that has very little reserve. This chapter covers the embryology that explains the physiology, the prenatal tools that forecast severity, the delivery-room and early intensive-care stabilisation, the rationale for delayed repair, ventilatory and vasodilator strategy, and the narrow place of extracorporeal membrane oxygenation (ECMO).
Embryology and the Origins of Pulmonary Hypoplasia
Failure of Pleuroperitoneal Fold Fusion
The diaphragm is assembled from four embryonic components: the septum transversum, the paired pleuroperitoneal folds, the dorsal oesophageal mesentery, and the muscles of the body wall. The pleuroperitoneal folds, which appear around the fourth to fifth week and expand posterolaterally, are the structures whose failure of fusion produces the common posterolateral (Bochdalek) defect. Failure of the fold to close with the septum transversum and dorsal mesentery by the eighth to tenth week leaves a persistent pleuroperitoneal canal through which the returning midgut passes into the thorax. Approximately 70–75% of defects are posterolateral, 85% of these occur on the left, and a minority are right-sided or bilateral.
The defect is not simply a hole. Aberrant pleuroperitoneal fold development is accompanied by disturbed retinoid, fibroblast growth factor, and other signalling, so that maldevelopment of the diaphragm and of the lung share an upstream cause. This is the basis of the two-hit hypothesis: a primary developmental lung abnormality is compounded by the secondary mechanical compression of the herniated viscera.
CDH lung disease is best understood as two superimposed insults. The first hit is an intrinsic defect in lung and vascular branching that predates herniation. The second hit is mechanical: viscera occupying the thoracic cavity compress the developing lung, shift the mediastinum, and further restrict alveolar and vascular growth. Both hits must be addressed, which is why reduction of the hernia alone does not normalise the lung.
Alveolar, Airway and Mesenchymal Dysmaturation
The hypoplastic lung has fewer alveoli and fewer generations of airways, a thickened interalveolar mesenchyme, and a reduced total gas-exchange surface area. Both lungs are affected, the ipsilateral more than the contralateral, and the severity on the contralateral side depends on the degree of mediastinal shift. Because gas transfer is proportional to surface area and inversely proportional to membrane thickness, the reduction in alveolar number and the increase in septal thickness together impose a fixed diffusive limitation that no ventilator setting can abolish. Surfactant synthesis is also immature for gestational age, reflecting a reduced population of type II pneumocytes, so a component of respiratory distress syndrome-like physiology may coexist.
Pulmonary Vascular Abnormalities and Pulmonary Hypertension
Structural Remodelling and Rarefaction of the Pulmonary Bed
The pulmonary vasculature in CDH is not merely constricted but underdeveloped. The number of pulmonary arterial branches is reduced, medial smooth muscle is hypertrophied, the adventitia is thickened, and smooth muscle extends abnormally into intra-acinar vessels. Because vascular resistance is inversely proportional to the fourth power of vessel radius and to the number of parallel vessels, both rarefaction and luminal narrowing raise pulmonary vascular resistance (PVR) steeply. The hypertensive, poorly compliant right ventricle is asked to eject against this high resistance, and right ventricular failure may supervene. Left ventricular hypoplasia and dysfunction are also common in CDH and contribute to pulmonary venous hypertension, a point of practical importance because it warns against indiscriminate pulmonary vasodilation.
The Postnatal Transition and Labile Shunting
After birth, as the fluid-filled lung is recruited and oxygen tension rises, PVR should fall below systemic vascular resistance and the fetal shunts should close. In CDH the fall is blunted. Pulmonary arterial pressure remains at or above systemic pressure, and deoxygenated blood continues to shunt right-to-left across the patent ductus arteriosus and foramen ovale. Because shunt direction is set moment to moment by the balance between PVR and systemic vascular resistance, handling, hypoxaemia, acidosis, or hypotension can precipitate abrupt desaturation. The clinical signature is a pre-ductal to post-ductal saturation gradient with labile hypoxaemia disproportionate to the radiographic parenchymal disease.
PVR is the transpulmonary pressure gradient divided by pulmonary blood flow:
$$PVR = \frac{\overline{PAP} - PAWP}{\dot{Q}_p}$$where $\overline{PAP}$ = mean pulmonary artery pressure ($\text{mmHg}$), $PAWP$ = pulmonary artery wedge pressure ($\text{mmHg}$), and $\dot{Q}_p$ = pulmonary blood flow ($\text{L}\cdot\text{min}^{-1}$). The unit is the Wood unit ($\text{mmHg}\cdot\text{L}^{-1}\cdot\text{min}^{-1}$). Because geometry sets resistance, $PVR \propto \frac{1}{N\,r^{4}}$, where $N$ = number of parallel vessels and $r$ = vessel radius; the loss of $N$ in CDH raises PVR sharply.
Prenatal Diagnosis and Prognostication
Ultrasound and the Observed-to-Expected Lung-to-Head Ratio
CDH is increasingly diagnosed antenatally, which allows planned delivery at a centre able to provide gentle ventilation, pulmonary vasodilators, and ECMO. The key sonographic measure is the lung-to-head ratio (LHR), calculated on a transverse axial image at the level of the four-chamber view as the area of the contralateral lung divided by the head circumference. A raw LHR of less than 0.6 predicts poor outcome and a ratio above 1.35 is associated with survival, but the raw value is biased by gestational age. The observed-to-expected LHR corrects for this:
$$o/e\,LHR = \frac{\text{observed } LHR}{\text{expected } LHR \text{ for gestational age}} \times 100\%$$An $o/e\,LHR$ below about 25% defines severe hypoplasia with a high risk of mortality, 25–35% is moderate, and above 35% is milder disease.
Liver and Stomach Position, and Magnetic Resonance Imaging
Position of the liver is the single most powerful binary prognostic marker. An intrathoracic or "up" liver reflects a large defect with substantial visceral herniation and predicts a materially worse outcome than an intra-abdominal liver, independent of the LHR. Intrathoracic stomach position, graded from anterior to posterior, provides a complementary and reproducible grade of severity. Fetal magnetic resonance imaging can measure total fetal lung volume and also identifies associated anomalies, and echocardiography detects structural cardiac disease present in a minority of infants.
Fetal Intervention in Selected Centres
Fetoscopic endoluminal tracheal occlusion exploits the observation that obstructing the fetal trachea traps lung fluid, raises intrapulmonary pressure, and stretches the airways, driving lung growth. Randomised evidence has shown improved survival in severe left-sided CDH, and the procedure is offered only in experienced fetal centres to carefully selected fetuses, usually on the basis of a very low $o/e\,LHR$ and an intrathoracic liver. It carries real risks, including preterm birth and the need for timely removal of the balloon, and it is not a cure.
The three most useful antenatal discriminators of severity are the $o/e\,LHR$, the liver position, and the stomach position. These are used together, not in isolation, to counsel families and to plan the level of postnatal support.
Delivery-Room and Immediate Stabilisation
Avoid Mask Ventilation and Intubate Early
The single most important delivery-room principle is that a suspected CDH infant must not be bag-mask ventilated. Positive pressure applied by face mask passes preferentially into the stomach and the herniated bowel, distending intrathoracic viscera, worsening lung compression and mediastinal shift, and impeding venous return. Where CDH is known antenatally, the infant should be intubated early, ideally with a T-piece resuscitator that limits the delivered pressure, and ventilated with the smallest pressures that achieve adequate gas exchange.
Gastric and Bowel Decompression
A large-bore orogastric or nasogastric tube, typically 8–10 Fr, should be placed immediately and connected to continuous low suction. Decompressing the gastrointestinal tract reduces the thoracic volume occupied by bowel, improving both lung recruitment and cardiac filling. The tube is left on free drainage or gentle suction for the entire preoperative period.
Preductal Targets and Gentle Ventilation
A pre-ductal pulse oximeter is placed on the right hand as soon as possible. The pre-ductal saturation target is approximately 85–95%, deliberately avoiding hyperoxia, which is a potent stimulus to oxidative injury and does not correct the shunt. Ventilation follows the principle of "gentle ventilation": peak inspiratory pressures are kept low, tidal volumes are small, and a degree of permissive hypercapnia is accepted. A $PaCO_2$ of 45–65 mmHg and a pH of at least about 7.20 are tolerated in exchange for lower airway pressures, because the hypoplastic lung is far more vulnerable to barotrauma and volutrauma than to moderate hypercarbia.
- Do not bag-mask ventilate; intubate early with a T-piece resuscitator.
- Place a large-bore orogastric/nasogastric tube to continuous low suction.
- Apply a pre-ductal (right hand) pulse oximeter.
- Target pre-ductal $SpO_2$ 85–95%; avoid hyperoxia.
- Use low peak pressures and accept permissive hypercapnia.
- Establish vascular access and secure invasive monitoring early.
- Transfer to a centre with pulmonary vasodilator and ECMO capability.
Delayed Surgical Repair and Perioperative Physiology
The Case Against Immediate Repair
Historic practice treated CDH as a surgical emergency, with repair performed within hours of birth. This approach is now abandoned. Immediate operation on an unstable infant exposes a labile pulmonary circulation to anaesthesia, surgical manipulation, and fluid shifts, and it precipitates pulmonary hypertensive crises without correcting the underlying hypoplasia. The defect itself is not immediately life-threatening; the pulmonary hypertension and hypoxaemia are. Modern practice therefore defers repair.
Stabilisation Before Repair
Repair is undertaken once the infant has achieved physiological stability: acceptable pre-ductal oxygenation on gentle ventilation, control of pulmonary hypertension, adequate systemic perfusion and urine output, and no evidence of a severe pulmonary hypertensive crisis. In practice this usually means a delay of several days, and in the sickest infants repair may be postponed substantially or performed on ECMO. The rationale is that the hypoplastic lung has its best chance of recruiting and the pulmonary vasculature its best chance of relaxing once the physiological storm has settled.
Do not treat the diaphragmatic defect as a surgical emergency. Operating on a physiologically unstable CDH infant provokes pulmonary hypertensive crises and worsens outcome; the correct emergency is the physiology, not the hole.
Ventilatory Strategy and Pulmonary Vasodilation
Conventional Gentle Ventilation
Conventional ventilation is the first-line strategy. Pressure-controlled ventilation is preferred because it directly limits the pressure applied to a lung with reduced compliance. Peak inspiratory pressures are kept at or below about 25 cmH$_2$O, positive end-expiratory pressure at 3–5 cmH$_2$O, and tidal volumes at roughly 4–6 mL/kg. The aim is to recruit lung volume without overdistension, and to accept modest hypercapnia rather than escalate pressure.
Respiratory system compliance is the change in volume per unit change in pressure:
$$C_{rs} = \frac{\Delta V}{\Delta P} = \frac{V_T}{P_{plat} - PEEP}$$where $C_{rs}$ = respiratory system compliance ($\text{mL}\cdot\text{cmH}_2\text{O}^{-1}$), $\Delta V = V_T$ = tidal volume ($\text{mL}$), $P_{plat}$ = plateau pressure ($\text{cmH}_2\text{O}$), and $PEEP$ = positive end-expiratory pressure ($\text{cmH}_2\text{O}$). Because CDH lungs have few alveoli and thickened mesenchyme, $C_{rs}$ is very low, so any given tidal volume requires a disproportionately high driving pressure $\Delta P = P_{plat} - PEEP$. This is why volume-targeted ventilation must be applied with a strict pressure ceiling rather than a volume mandate.
High-Frequency Ventilation as Rescue
When conventional gentle ventilation cannot sustain oxygenation, high-frequency oscillatory ventilation (HFOV) or high-frequency jet ventilation (HFJV) may be used as rescue. A randomised trial comparing HFOV with conventional ventilation in CDH found no difference in the primary outcome of bronchopulmonary dysplasia or death, so high-frequency ventilation is not a routine first choice; it is a rescue tool in centres experienced with it. Its attraction is that it can recruit and ventilate with very small tidal volumes, but the trade-off is that high mean airway pressures may overdistend the hypoplastic lung and impair venous return.
Recruitment Versus Overdistension
The relationship between lung volume and pulmonary vascular resistance is U-shaped. At low lung volumes, atelectasis and hypoxic vasoconstriction raise PVR; at high volumes, alveolar overdistension compresses the intra-alveolar capillaries and again raises PVR, while also increasing the risk of air leak in a lung whose interstitial integrity is fragile. Ventilation therefore seeks the nadir of that curve: a lung held open at functional residual capacity without tidal overdistension. Contralateral pneumothorax in a CDH infant, in whom the contralateral lung is the principal source of gas exchange, is a catastrophic complication.
Iatrogenic rupture of the relatively normal contralateral lung is among the most lethal complications of CDH ventilation. Keep peak and mean airway pressures as low as gas exchange permits, and suspect pneumothorax immediately in any infant who deteriorates abruptly.
Inhaled Nitric Oxide and Adjunct Pulmonary Vasodilators
Inhaled nitric oxide (iNO) is a selective pulmonary vasodilator that reduces PVR in ventilated lung regions and can improve oxygenation in infants with CDH-associated pulmonary hypertension. However, it does not consistently reduce mortality, and its main recognised benefit is a reduction in the need for ECMO. Response is variable because the vessels are structurally abnormal and because left ventricular dysfunction may limit the benefit of vasodilation. Sildenafil, milrinone, and prostacyclin analogues are used as adjuncts, selected according to the echocardiographic picture: milrinone is attractive when there is coexisting left ventricular dysfunction, whereas sildenafil and prostacyclin act more directly on the pulmonary bed. All of these agents work best in a recruited lung with an adequate systemic pressure head.
Extracorporeal Membrane Oxygenation
ECMO is reserved for infants with refractory hypoxaemia or haemodynamic collapse despite optimised gentle ventilation, pulmonary vasodilators, and systemic support. A sustained oxygenation index of 40 or more, or an inability to maintain pre-ductal saturation despite maximal therapy, are the usual triggers. The timing of ECMO relative to surgical repair remains controversial: some centres repair the defect on ECMO, others use ECMO purely as a bridge to recovery and postpone repair until decannulation. Mortality among CDH infants who require ECMO remains high, on the order of 50%, and ECMO does not reverse pulmonary hypoplasia; it buys time for the lung to recruit and for pulmonary vascular resistance to fall. Absolute contraindications include lethal associated anomalies, severe intraventricular haemorrhage, and irreversible lung disease.
Monitoring Targets and Escalation
Quantifying the Severity of Oxygenation Failure
Oxygenation in CDH reflects both parenchymal hypoplasia and shunt, so the ventilator's contribution must be quantified rather than assumed. The oxygenation index (OI) integrates mean airway pressure, oxygen requirement, and achieved arterial oxygenation:
where $MAP$ = mean airway pressure ($\text{cmH}_2\text{O}$), $FiO_2$ = fraction of inspired oxygen (dimensionless, 0–1), and $PaO_2$ = arterial oxygen tension ($\text{mmHg}$). The index is dimensionless. When arterial access is unavailable, the oxygen saturation index substitutes pulse oximetry:
$$OSI = \frac{MAP \times FiO_2 \times 100}{SpO_2}$$where $SpO_2$ = pre-ductal pulse oximetric oxygen saturation (%). Between 90% and 97%, $OSI$ tracks $OI$ closely and is useful for trending. Widely used escalation thresholds are $OI > 25$ despite optimised lung volume and blood pressure, which justifies iNO or high-frequency rescue, and a sustained $OI \geq 40$, which prompts ECMO referral.
Ventilation and Physiological Targets
| Parameter | Target or Initial Setting | Rationale and Limit |
|---|---|---|
| Pre-ductal $SpO_2$ | 85–95% | Avoid hyperoxia; accept a modest shunt |
| Mode | Pressure-controlled CMV | Directly limits airway pressure |
| Peak inspiratory pressure | $\leq 25\ \text{cmH}_2\text{O}$ | Protect the hypoplastic lung from barotrauma |
| Positive end-expiratory pressure | 3–5 $\text{cmH}_2\text{O}$ | Recruit without overdistending |
| Tidal volume | 4–6 $\text{mL}\cdot\text{kg}^{-1}$ | Small volumes, strict pressure ceiling |
| $PaCO_2$ | 45–65 $\text{mmHg}$ | Permissive hypercapnia is tolerated |
| pH | $\geq 7.20$ | Correct only severe acidosis |
| Mean arterial pressure | Appropriate for gestation | Defend coronary perfusion to the right ventricle |
| Lactate | Falling or $< 3\ \text{mmol}\cdot\text{L}^{-1}$ | Marker of adequate systemic perfusion |
| Temperature | 36.5–37.5 $^\circ\text{C}$ | Avoid cold stress that raises PVR |
Immediate Stabilisation and Escalation Algorithm
graph TD
    A["Suspected or confirmed CDH at birth"] --> B["Do not bag-mask ventilate;<br/>intubate immediately"]
    B --> C["Large-bore orogastric/nasogastric tube<br/>to continuous low suction"]
    C --> D["Gentle conventional ventilation:<br/>PIP <= 25 cmH2O, PEEP 3-5 cmH2O"]
    D --> E["Preductal SpO2 85-95%,<br/>PaCO2 45-65 mmHg, pH >= 7.20"]
    E --> F{"Preductal SpO2 >= 85%<br/>and perfusion adequate?"}
    F -->|"Yes"| G["Continue gentle ventilation and<br/>defer repair until physiologically stable"]
    F -->|"No"| H["Optimise sedation, volume,<br/>inotropes and systemic blood pressure"]
    H --> I["Echocardiography; start iNO 20 ppm<br/>if pulmonary hypertension dominates"]
    I --> J{"OI >= 25 or persistent<br/>hypoxaemia despite iNO?"}
    J -->|"No"| G
    J -->|"Yes"| K["Trial HFOV or HFJV as rescue;<br/>avoid overdistension"]
    K --> L{"OI >= 40 sustained, refractory<br/>hypoxaemia or haemodynamic collapse?"}
    L -->|"Yes"| M["Refer or initiate ECMO as a<br/>bridge to recovery and repair"]
    L -->|"No"| G
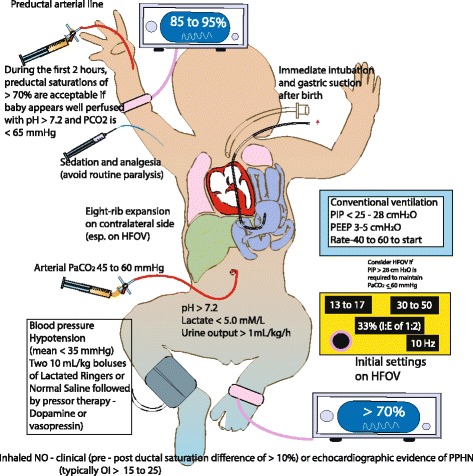 Figure 1: Delivery-room and early intensive-care management of CDH, showing bowel decompression, avoidance of bag-mask ventilation, early intubation with pressure-limited ventilation, pre-ductal saturation targets, vasodilator therapy for pulmonary hypertension, and blood-pressure support. (Source: Chandrasekharan PK, Rawat M, Madappa R, Rothstein DH, Lakshminrusimha S. Maternal Health, Neonatology and Perinatology 2017. DOI: 10.1186/s40748-017-0045-1).
Key Takeaways
- CDH is a disease of the lung and its vasculature, not merely a hole in the diaphragm: failure of pleuroperitoneal fold fusion permits visceral herniation that compounds an intrinsic defect in alveolar and vascular development, producing bilateral pulmonary hypoplasia and pulmonary hypertension.
- The hypoplastic lung has fewer alveoli and airway generations, thickened mesenchyme, and immature surfactant, so it has very low compliance and tolerates pressure poorly; ventilation must be gentle, with pressures at or below about 25 cmH$_2$O and small tidal volumes.
- Prenatal severity is graded by the observed-to-expected lung-to-head ratio, together with liver and stomach position; a very low $o/e\,LHR$ identifies infants at high risk and may prompt referral for fetal tracheal occlusion in selected centres.
- Never bag-mask ventilate a suspected CDH infant: positive pressure distends the herniated bowel, worsens lung compression, and impairs venous return. Intubate early, decompress the stomach with a large-bore tube, and target a pre-ductal $SpO_2$ of 85–95%.
- Accept permissive hypercapnia ($PaCO_2$ 45–65 mmHg, pH $\geq 7.20$) in exchange for lower airway pressures, because barotrauma to the hypoplastic lung is more dangerous than moderate hypercarbia.
- Surgical repair is delayed until the infant is physiologically stable; the emergency is the pulmonary hypertension and hypoxaemia, not the diaphragmatic defect.
- Inhaled nitric oxide, other pulmonary vasodilators, high-frequency rescue ventilation, and ECMO are escalation tools for refractory pulmonary hypertension and hypoxaemia; ECMO is a bridge that buys time for lung recruitment and vascular relaxation, not a therapy that reverses hypoplasia.