Apnea of prematurity is the commonest respiratory disorder of preterm life and, in the extremely low-birth-weight (ELBW, birth weight $<1000$ g) infant, the most frequent reason that invasive ventilation is prolonged or reintubation becomes necessary. It reflects an immature respiratory control system rather than lung parenchymal disease, so it differs fundamentally from respiratory distress syndrome: the drive to breathe, upper-airway reflex control and chemoreceptor responses are all developmentally incomplete. Treating this control failure is as important as the mechanical strategy used to support gas exchange.
This chapter addresses the maturation of respiratory control, the mechanisms of apnea, caffeine therapy, non-invasive support, and the readiness for and support after extubation.
Definitions, Epidemiology and Maturation of Respiratory Control
The clinical definition
Apnea is a respiratory pause of at least 20 seconds, or a shorter pause accompanied by bradycardia (heart rate $<100$ beats/min) or desaturation (usually $S_{pO_2}$ below 90%, or below 85% in many units); a brief pause with profound desaturation is more hazardous than an isolated 20-second pause without haemodynamic consequence. Periodic breathing — at least three pauses of 3 to 10 seconds separated by less than 20 seconds of breathing — marks the same instability and is usually benign in isolation. Apnea of prematurity is a diagnosis of exclusion: sepsis, necrotising enterocolitis, hypoglycaemia, anaemia, hypothermia, seizures, a symptomatic patent ductus arteriosus (PDA) and opioid exposure must each be excluded.
The apnea–hypopnea index
$$\text{AHI} = \frac{N_{ap} + N_{hyp}}{T_{sleep}}$$where $N_{ap}$ and $N_{hyp}$ are the apnea and hypopnea counts, $T_{sleep}$ the total sleep time in hours ($\text{h}$), and the index is in events per hour. The AHI falls with advancing postmenstrual age (PMA) and quantifies maturation and treatment effect.
Incidence and gestational age
The incidence is inversely and steeply related to gestational age (GA): virtually all infants born before 28 weeks, roughly half to four-fifths at 28 to 31 weeks, a minority at 32 to 33 weeks and under 10% at 34 to 36 weeks; it is rare at term. It declares itself after the first day of life and resolves by 36 to 40 weeks' PMA, later in ELBW infants; onset after the second week or persistence beyond 43 to 44 weeks should prompt a search for another cause.
Maturation of respiratory control
The respiratory rhythm is generated by a distributed brainstem network centred on the pre-Bötzinger complex. Three developmental features destabilise it. Central chemosensitivity to carbon dioxide is blunted, so the apneic threshold lies close to the eupneic $P_{aCO_2}$ and small fluctuations silence breathing. Active (rapid-eye-movement) sleep occupies an unusually large proportion of sleep, and during it chemosensitivity and upper-airway dilator tone are lowest, so events cluster in active sleep. Finally, the carotid-body chemoreceptors mature faster than the central receptors and are initially uncalibrated, generating periodic breathing.
Why preterm apnea is a control problem An immature, unstable brainstem network with exaggerated inhibitory tone explains its response to methylxanthines and non-invasive pressure.
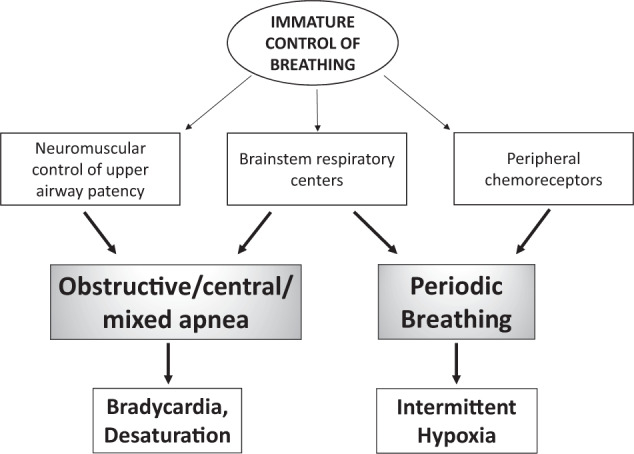 Figure 1: Immature central and peripheral chemoreceptor responses and diminished neuromuscular control of upper-airway patency produce prolonged apneas with bradycardia and desaturation, alongside shorter respiratory pauses and periodic breathing. (Source: Erickson G, Dobson NR, Hunt CE. J Perinatol 2021;41(9):2111–2123. DOI: 10.1038/s41372-021-01010-z).
Mechanisms and Classification of Apnea
Central, obstructive and mixed apnea
A central apnea is a pause in which inspiratory effort ceases while the airway remains patent. An obstructive apnea is an inspiratory effort against an obstructed pharynx: the small, compliant upper airway collapses because genioglossus and other dilator muscles are hypotonic during sleep. Most events are classed as mixed, beginning centrally and acquiring obstruction during recovery. The distinction is therapeutic — applied pressure splints the airway, whereas caffeine restores drive.
| Type | Respiratory effort | Airway | Principal mechanism | Share |
|---|---|---|---|---|
| Central | Absent | Patent | Failure of brainstem inspiratory output | 10–25% |
| Obstructive | Present | Obstructed | Pharyngeal collapse against hypotonic dilators | 10–25% |
| Mixed | Absent, then present | Patent, then obstructed | Central pause, then obstruction during recovery | 50–75% |
The brainstem, neurotransmitters and reflexes
Within the brainstem the balance of signalling is shifted towards inhibition. Adenosine acting at $A_1$ receptors depresses respiration and terminates breathing as a negative-feedback brake; caffeine antagonises it. GABA, glycine and endogenous opioids also suppress output, and because the hypoxic ventilatory response is biphasic — a brief increase then sustained depression — recurrent hypoxia reinforces further apnea.
The laryngeal chemoreflex, in which fluid in the larynx triggers apnea, bradycardia and swallowing, is exaggerated in the preterm infant; it links refluxate or secretions to prolonged events and explains why unnecessary suctioning can precipitate them. The immature carotid bodies have a high resting discharge and a depressogenic response to sustained hypoxia, and the arousal response is blunted, so the infant may remain apneic rather than waking.
Pharmacological Therapy: Caffeine as First-Line
The mechanism of methylxanthines
Caffeine citrate is first-line. It is a methylxanthine acting principally as a competitive antagonist at adenosine $A_1$ and $A_{2A}$ receptors, releasing the brainstem respiratory network from adenosine-mediated inhibition. It also increases central chemoreceptor responsiveness to carbon dioxide, lowering the apneic threshold; improves diaphragmatic contractility and neuromuscular transmission; and reduces periodic breathing and the hypoxic depression of ventilation. It is a weaker phosphodiesterase inhibitor than theophylline, giving it a wider therapeutic margin.
Dosing and monitoring
Caffeine is given as the citrate salt, which is approximately half caffeine base by mass. The standard regimen is a load of 20 mg/kg intravenously or orally, followed 24 hours later by 5 to 10 mg/kg once daily; many units use 5 mg/kg/day and reserve 10 mg/kg/day for persistent events. The dose–concentration relationship is:
$$C_{ss} = \frac{F \cdot S \cdot D}{CL \cdot \tau}$$where $C_{ss}$ is the steady-state plasma concentration ($\text{mg/L}$), $F$ the oral bioavailability (dimensionless, $\approx 1$), $S$ the salt factor (caffeine base to citrate $\approx 0.5$), $D$ the dose per interval ($\text{mg/kg}$), $CL$ the clearance ($\text{L/kg/h}$) and $\tau$ the dosing interval ($\text{h}$). Because clearance rises with PMA and the half-life falls from roughly 100 hours in the most immature infants towards 40 to 50 hours near term, the same dose produces higher concentrations earlier in life. Monitoring is clinical — apneas, bradycardias and desaturations — and routine levels are unnecessary; the therapeutic range is approximately 8 to 20 mg/L.
Caffeine citrate at a glance Load 20 mg/kg IV or oral, then maintain 5–10 mg/kg once daily from 24 hours. The citrate:base ratio is 2:1, so 20 mg/kg citrate equals 10 mg/kg base. Confirm caffeine is established before extubation and continue it afterwards.
The evidence for early caffeine
The Caffeine for Apnea of Prematurity (CAP) trial randomised more than 2,000 infants of 500 to 1,250 g. The composite primary outcome of death or bronchopulmonary dysplasia (BPD) at 36 weeks was not significantly reduced, but caffeine reduced BPD, PDA and the duration of ventilation, and at 18 to 21 months improved the combined outcome of death or major neurodevelopmental disability and reduced cerebral palsy. Later follow-up showed attenuated but persistent benefit without harm. Systematic reviews of early caffeine, started within 2 to 3 days, suggest further reductions in BPD and extubation failure, though certainty is lower.
Doxapram and methylxanthine toxicity
Doxapram is a respiratory stimulant acting on carotid-body and central chemoreceptors, given as a continuous infusion and used historically for apnea refractory to caffeine. Evidence for benefit on important outcomes is weak, and it causes hypertension, tachycardia, jitteriness, feeding intolerance, hyperglycaemia and metabolic acidosis, with animal evidence of cerebral white-matter injury. It is reserved for infants in whom caffeine and non-invasive support have failed and intubation is being avoided.
Methylxanthine toxicity Caffeine may cause tachycardia, jitteriness, feeding intolerance and reflux, increased urine output and hyperglycaemia; seizures are a rare manifestation of high serum levels. Caffeine is preferred over theophylline because of its longer half-life, once-daily dosing and fewer adverse effects.
Non-Pharmacological Support and Escalation
Nasal CPAP and nasal IPPV
Non-invasive support is the mainstay. Nasal continuous positive airway pressure (nCPAP) at 6 to 8 cmH$_2$O splints the compliant pharynx, abolishes the obstructive component of mixed events and recruits alveoli, improving functional residual capacity and oxygenation. Nasal intermittent positive-pressure ventilation (NIPPV) superimposes pressure breaths above the CPAP baseline; synchronised to the infant's own effort it reduces the work of breathing and the apneic burden and reduces extubation failure compared with nCPAP, most clearly below 28 weeks.
Positioning, minimal handling and precipitants
Care is clustered to minimise handling, and cold, pain and unnecessary suctioning are avoided because each triggers the laryngeal chemoreflex. Prone positioning improves diaphragm mechanics and reduces apnea but requires continuous monitoring; supine sleeping must be restored before discharge. Correction of anaemia, electrolyte disturbance, sepsis, hypothermia and a symptomatic PDA all reduce events.
Escalation to invasive ventilation
Invasive ventilation is indicated when apnea recurs despite optimal caffeine and non-invasive support, when events require repeated stimulation or cause cardiovascular compromise, when respiratory acidosis develops (pH $<7.20$ to $7.25$ with a rising $P_{aCO_2}$), or when the oxygen requirement climbs despite adequate pressure. Intubation may be brief, providing airway protection while the infant matures.
Escalation triggers Recurrent events needing stimulation, a rising $F_{iO_2}$, respiratory acidosis, or cardiovascular instability despite caffeine and optimal nCPAP/NIPPV. Plan a brief period of ventilation rather than risk an emergency intubation.
Extubation Readiness in the ELBW Infant
Domains of assessment
Extubation readiness is a composite judgement, not a single number. The clinician integrates drive, ventilator settings, blood gases, oxygen requirement, spontaneous tidal volume, secretion burden, airway patency, cardiovascular stability, nutrition and pharmacologic state. A high pre-extubation apnea burden is among the strongest predictors of failure and must be observed over at least 12 to 24 hours.
| Domain | Bedside criterion | Rationale |
|---|---|---|
| Respiratory drive | No significant apnea or bradycardia in the preceding 12–24 h | Predicts sustained spontaneous effort |
| Ventilator settings | PIP $\leq$ 16–18 cmH$_2$O, PEEP $\leq$ 5–6 cmH$_2$O, rate $\leq$ 15–20/min, $F_{iO_2}$ $\leq$ 0.30 | Low support implies adequate compliance |
| Blood gases | pH $\geq$ 7.25 and $P_{aCO_2} < 60$ mmHg | Avoids post-extubation respiratory acidosis |
| Spontaneous tidal volume | 4–6 mL/kg with adequate minute ventilation | Confirms effective spontaneous effort |
| Secretions and airway | Infrequent suction, no atelectasis, a leak around the tube | A blocked or oversized tube predicts failure |
| Cardiovascular | No significant PDA, stable blood pressure, no rising inotropes | Instability predisposes to apnea |
| Nutrition and pharmacologic | Adequate intake, normoglycaemia, no significant anaemia, caffeine established, minimal sedation | Substrate for work; methylxanthine reduces extubation failure |
The spontaneous breathing trial and sedation hold
A spontaneous breathing trial (SBT) places the infant on a low or absent mandatory rate — typically nCPAP or a very low backup rate — for 30 to 120 minutes while drive, pattern, oxygenation and carbon dioxide are observed. Direct neonatal evidence is limited, but it is a structured, reversible test. In parallel, a sedation hold minimises opioid exposure, which itself depresses respiratory control. Caffeine should be established, anaemia corrected, and extubation planned for the morning.
Predictors and Consequences of Extubation Failure
Who fails, and why it matters
Extubation failure — reintubation within 48 to 72 hours — occurs in roughly one-fifth to two-fifths of ELBW infants. Risk is highest with greater immaturity, a high pre-extubation apnea burden, a higher $F_{iO_2}$ or mean airway pressure, a higher $P_{aCO_2}$, increased secretions, a haemodynamically significant PDA, sepsis, upper-airway obstruction, anaemia, and absent or inadequate caffeine. Each failure is not neutral: reintubation restarts ventilator-induced lung injury and is associated with prolonged ventilation, BPD, ventilator-associated pneumonia, airway trauma, longer stay, higher mortality and worse neurodevelopment. The threshold for reintubation should be low once failure is apparent, but the strategy should make the first extubation succeed.
The cost of delayed reintubation Prolonged bag-and-mask stimulation, worsening acidosis or recurrent severe desaturations after extubation should prompt reintubation rather than repeated rescue.
Post-Extubation Support: Choosing the Interface
CPAP, NIPPV or high-flow nasal cannula
All but the most mature, lowest-risk infants should be extubated onto positive pressure. nCPAP at 6 cmH$_2$O or more reduces respiratory failure and reintubation and is the minimum standard; NIPPV, especially synchronised, reduces failure further, with the greatest benefit below 28 weeks and in infants with prior apnea. Heated, humidified high-flow nasal cannula (HFNC) is better tolerated and causes less nasal trauma, and some trials show non-inferiority in lower-risk infants, but the pressure it delivers is variable and unmeasured; it is best used as a step-down interface rather than for the highest-risk ELBW infant.
flowchart TD
    A["ELBW infant on invasive ventilation"] --> B{"Drive, apnea burden, gases, FiO2, secretions and cardiovascular stability acceptable?"}
    B -->|"No"| C["Correct anaemia, PDA, sepsis and secretions; optimise nutrition; continue invasive support"]
    C --> B
    B -->|"Yes"| D["Caffeine established; perform spontaneous breathing trial and sedation hold"]
    D --> E{"Tolerates SBT without apnea, acidosis or desaturation?"}
    E -->|"No"| C
    E -->|"Yes"| F["Elective extubation to non-invasive support"]
    F --> G{"Gestational age < 28 weeks, high apnea burden, or prior extubation failure?"}
    G -->|"Yes"| H["Nasal IPPV or synchronised NIPPV with CPAP >= 6 cmH2O"]
    G -->|"No"| I["Nasal CPAP 6-8 cmH2O"]
    H --> J{"Apnea, rising FiO2 or respiratory acidosis within 72 h?"}
    I --> J
    J -->|"No"| K["Wean non-invasive support and caffeine as maturity advances"]
    J -->|"Yes"| L["Optimise interface and pressure; consider NIV-NAVA; reintubate if refractory"]
Continued caffeine and neural assist
Caffeine must be continued after extubation: prophylactic methylxanthines reduce extubation failure, and stopping it at extubation removes support for drive at the moment the infant is most vulnerable. Where apnea and asynchrony coexist, or repeated failure suggests an unstable control system, neurally adjusted ventilatory assist (NAVA) triggers and cycles the ventilator from the electrical activity of the diaphragm (Edi), improving synchrony and delivering support in proportion to neural drive; non-invasive NAVA may stabilise an infant who fails conventional NIPPV (Chapter 13).
The ELBW extubation bundle Correct anaemia, treat a symptomatic PDA and sepsis, establish caffeine, suction and confirm a leak, choose NIPPV for the highest-risk infant and CPAP otherwise, and extubate in the morning.
Key Takeaways
- Apnea of prematurity is a pause of at least 20 seconds, or a shorter pause with bradycardia or desaturation; incidence falls with advancing gestation.
- Central, obstructive and mixed events reflect immature brainstem control, exaggerated inhibitory tone, the laryngeal chemoreflex and blunted hypoxic responses.
- Caffeine citrate is first-line: load 20 mg/kg, maintain 5–10 mg/kg/day, remembering the 2:1 citrate-to-base ratio.
- The CAP trial showed caffeine reduces BPD, PDA and ventilation duration and improves early neurodevelopment; doxapram is a weak second-line agent.
- nCPAP and synchronised NIPPV treat the obstructive and central components; clustered care and correction of precipitants reduce events.
- Extubation readiness is a composite of drive, settings, gases, tidal volume, secretions, cardiovascular stability, nutrition and caffeine status.
- Extubation failure, occurring in one-fifth to two-fifths of ELBW infants, is predicted by immaturity and apnea burden and worsens BPD and neurodevelopment.
- Extubate onto NIPPV or CPAP, continue caffeine, and consider NIV-NAVA when synchrony and drive remain limiting.