Neurally adjusted ventilatory assist (NAVA) is the only widely adopted neonatal mode in which the ventilator reads the patient's neural command directly rather than inferring it from a pneumatic surrogate. Conventional triggered modes — pressure support (PSV), assist-control, and synchronised intermittent mandatory ventilation — detect effort indirectly, through airway pressure, gas flow, or both. Those surrogates are conditioned by a compliant, leaky, small-bore circuit, so the signal is delayed and distorted: trigger latency of 50–200 ms is routine, and ineffective triggering and auto-triggering are frequent. NAVA bypasses the circuit. It samples the electrical activity of the diaphragm ($E_{di}$) from electrodes embedded in a specialised oesophageal catheter and uses that myoelectric signal both to trigger each breath and to scale its amplitude, breath by breath.
The conceptual change is from pressure-targeted to drive-proportional assistance. In PSV the clinician fixes an inspiratory pressure and the infant's drive decides only when to breathe; in NAVA the infant's drive determines how much pressure is delivered during every breath, instantaneously and continuously. The assist can therefore vary from breath to breath and within a breath, following the fluctuating neural output of a preterm infant whose respiratory centre is immature, whose chest wall is highly compliant, and whose diaphragm fatigues readily.
This chapter covers the physiological basis of the $E_{di}$ signal; the control equation, settings, and titration of NAVA; the use of $E_{di}$ as a monitoring tool; the mode's advantages, pitfalls, and neonatal evidence base; and a set-up and titration algorithm.
Physiological Basis of the Edi Signal
The crural diaphragm as a bioelectric generator
The diaphragm is the principal muscle of inspiration, and its crural fibres form a sphincter-like band around the oesophagus as they insert on the lumbar vertebrae. When the phrenic motor neurones fire, the depolarising crural fibres generate an electric field that is largest at the hiatus. A catheter lying in the oesophageal lumen at that level sits inside the field, and closely spaced electrodes record it as a surface electromyogram; the signal is amplified, band-pass filtered to reject motion and cardiac frequencies, and displayed as the $E_{di}$ waveform. In neonatal practice the catheter is a 6–7 French feeding tube carrying a linear array of nine electrodes, so it serves for enteral nutrition and gastric decompression and is not an additional line.
The $E_{di}$ signal is a direct index of phrenic nerve output — of central respiratory drive transmitted to the muscle — not of pressure, flow, or volume. It rises with increased chemical drive (hypercapnia, hypoxia, metabolic acidosis), increased mechanical load, and arousal, and falls with sedation, hypocapnia, hyperoxia, and — importantly — when the ventilator unloads the diaphragm. That last property makes the signal both a control variable and a monitor of the adequacy of support.
The phrenic signal precedes gas movement by tens of milliseconds. A myoelectric trigger therefore pre-empts the pneumatic consequences of effort, which is why NAVA can remain synchronous when even the fastest flow trigger cannot keep pace with a tachypnoeic preterm infant.
Signal characteristics
Two features are reported at the bedside. The $E_{di}$ peak is the phasic amplitude of inspiratory effort; the $E_{di}$ minimum is the tonic activity that maintains end-expiratory lung volume, and a rising minimum suggests loss of functional residual capacity. Neuroventilatory efficiency relates $E_{di}$ to the tidal volume generated and falls as the system becomes stiffer or more obstructed. None of these is a resuscitation endpoint alone, but trends over hours and the response to a change in support are clinically informative.
$E_{di}$ — electrical activity of the diaphragm, measured in microvolts ($\mu\text{V}$), sampled continuously from the crural diaphragm. $E_{di}$ peak — the phasic (inspiratory) amplitude of the signal. $E_{di}$ minimum — the tonic (end-expiratory) component, an index of active expiratory braking and lung-volume maintenance. Neuroventilatory efficiency — $E_{di}$ peak divided by the resulting tidal volume; a stiffness and obstruction index.
Principle of Operation and the Control Equation
The control loop
Once the catheter is correctly positioned, the ventilator processes $E_{di}$ continuously and applies a proportional law: the instantaneous inspiratory pressure above positive end-expiratory pressure (PEEP) is the product of the $E_{di}$ amplitude and a single user-set gain, the NAVA level.
$$P_{insp}(t) = \text{NAVA level} \times E_{di}(t)$$and therefore
$$P_{aw}(t) = \text{NAVA level} \times E_{di}(t) + \text{PEEP}$$where $P_{insp}(t)$ is the instantaneous inspiratory pressure above PEEP ($\text{cmH}_2\text{O}$), $P_{aw}(t)$ is the total airway pressure ($\text{cmH}_2\text{O}$), NAVA level is the proportionality gain ($\text{cmH}_2\text{O}$ per $\mu\text{V}$), $E_{di}(t)$ is the instantaneous diaphragm electrical activity ($\mu\text{V}$), and PEEP is the end-expiratory pressure ($\text{cmH}_2\text{O}$).
The equations state the central teaching point of the mode: pressure is not selected, it is earned. A stronger or more prolonged neural effort receives proportionally more support; a lesser effort receives less. Because there is no fixed target pressure and no mandatory volume, the assist cannot exceed what the respiratory centre is asking for, within the limits set by the NAVA level.
The NAVA level carries units of $\text{cmH}_2\text{O}$ per $\mu\text{V}$. A level of $1.0$ therefore delivers $1\ \text{cmH}_2\text{O}$ of inspiratory pressure for every microvolt of $E_{di}$ above the trigger threshold, so the typical neonatal range of $0.5$–$2.0$ spans a very wide band of assistance. Small changes in the gain produce large changes in delivered pressure.
Triggering, cycling, and backup
Inspiration is triggered when $E_{di}$ crosses a threshold, $E_{di} \geq E_{di,trig}$, typically $0.5$–$1.0\ \mu\text{V}$ above baseline. Because the trigger is myoelectric it precedes any measurable change in airway pressure or flow, so the ventilator begins pressurising before the infant's effort has moved gas, removing the pneumatic trigger delay. Cycling to expiration follows the decline of $E_{di}$ to a proportion of its peak. A backup mode is always configured, with an apnoea time of a few seconds, to cover central apnoea and periodic breathing of prematurity. PEEP is set conventionally, on the basis of oxygenation and lung recruitment, and is not derived from $E_{di}$.
Settings and Titration
Initial settings
| Parameter | Typical neonatal initial value | Titration goal / safety limit |
|---|---|---|
| NAVA level | $1.0\ \text{cmH}_2\text{O}/\mu\text{V}$ | Locate the breakpoint; set $0.5$–$1.0$ below it |
| PEEP | $5$–$6\ \text{cmH}_2\text{O}$ | Oxygenation, FRC, and haemodynamics |
| $E_{di}$ trigger | $0.5$–$1.0\ \mu\text{V}$ | Low enough to sense all efforts, high enough to reject cardiac artefact |
| Backup rate / apnoea time | Conventional mode, apnoea $2$–$5\ \text{s}$ | Never leave unconfigured |
| Alarm limits | $E_{di}$ minimum and peak, PIP, $V_T$, $SpO_2$ | Detect drive loss and over-assist |
A set-up and titration algorithm
flowchart TD
    A["Infant requiring invasive or non-invasive respiratory support"] --> B["Insert Edi catheter as a gastric tube and allow to settle"]
    B --> C{"Valid Edi signal? P wave and QRS present on the electrogram channels"}
    C -->|"No"| D["Reposition or withdraw the catheter by 0.5-1 cm and recheck"]
    D --> C
    C -->|"Yes"| E["Select NAVA; set PEEP 5-6 cmH2O and Edi trigger 0.5-1.0 microvolt"]
    E --> F["Set backup conventional mode with apnoea time 2-5 s"]
    F --> G["Record baseline Edi peak and peak inspiratory pressure"]
    G --> H["Increase NAVA level in 0.5 cmH2O/microvolt steps"]
    H --> I{"Does PIP keep rising as the gain increases?"}
    I -->|"Yes"| H
    I -->|"No - breakpoint reached"| J["Set NAVA level 0.5-1.0 below the breakpoint"]
    J --> K["Reassess synchrony, Edi peak, gas exchange, and comfort"]
    K --> L{"Diaphragm still overloaded?"}
    L -->|"Edi high and PIP rising"| H
    L -->|"Stable"| M["Maintain; review daily and after any handling of the tube"]
    M --> K
Titrating the NAVA level: the Edi–pressure relationship
The NAVA level is titrated by observing the relationship between the gain and the pressure it produces. As the level rises in $0.5\ \text{cmH}_2\text{O}/\mu\text{V}$ steps, peak inspiratory pressure (PIP) rises, because each microvolt of drive now buys more pressure; the $E_{di}$ peak stays roughly constant, since the infant is still asking for the same effort and the ventilator is meeting more of it. At a certain gain, however, PIP stops rising. This is the breakpoint, and it marks the point at which the respiratory system can no longer translate additional pressure into additional inflation. Beyond the breakpoint the $E_{di}$ peak begins to fall, as the generous assist suppresses drive through negative feedback. The correct setting is conventionally $0.5$–$1.0\ \text{cmH}_2\text{O}/\mu\text{V}$ below the breakpoint: enough to unload the diaphragm, not so much as to abolish neural drive and encourage disuse.
Increase the NAVA level slowly, watch the PIP and the $E_{di}$ peak together, and stop when PIP plateaus. A falling $E_{di}$ peak with an unchanged clinical state means the assist is now excessive; a persistently high $E_{di}$ peak with a rising PIP means the diaphragm is still overloaded.
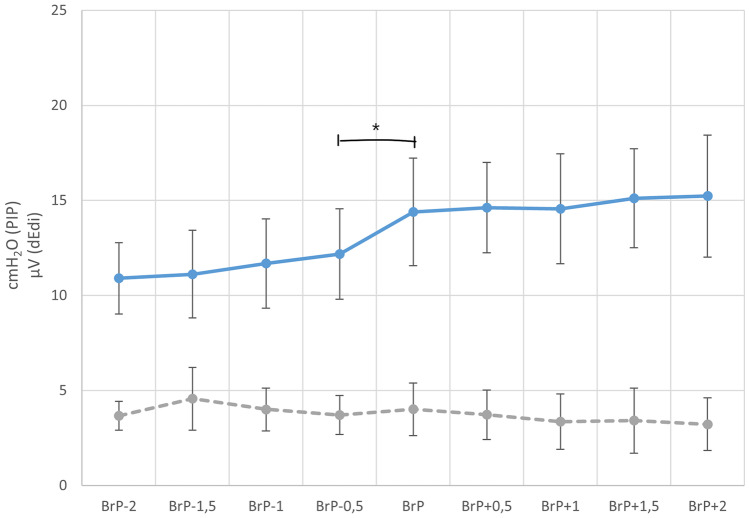 Figure 1: The Edi–pressure relationship defines the titration target: PIP rises with NAVA level until the breakpoint, beyond which additional gain no longer raises pressure and diaphragm drive falls. (Source: Lefevere J, Van Delft B, Vervoort M, Cools W, Cools F. Eur J Pediatr 2022. DOI: 10.1007/s00431-021-04244-3).
The Edi Signal as a Monitoring Tool
Quantifying neural respiratory drive
Because $E_{di}$ is displayed continuously, NAVA converts the ventilator into a respiratory-drive monitor. An $E_{di}$ peak that is high and rising indicates increased neural effort, whether from worsening lung mechanics, inadequate support, metabolic acidosis, or pain. A low $E_{di}$ peak in an infant who is nevertheless distressed suggests that the problem is not drive but obstruction, a malpositioned tube, or a pneumothorax. Serial $E_{di}$ measurement is therefore useful when the clinical picture and the ventilator data disagree.
Detecting asynchrony
Asynchrony is diagnosed directly from the $E_{di}$ and pressure waveforms. Ineffective triggering appears as an $E_{di}$ deflection without a ventilator breath; auto-triggering as a ventilator breath without a preceding $E_{di}$ rise; double cycling as two pressure cycles within one neural effort; and reverse triggering as a pressure cycle that evokes a subsequent $E_{di}$ deflection. Because the $E_{di}$ trace is the neural timeline, it exposes asynchrony that a flow or pressure trace alone can only infer.
Assessing extubation readiness and titrating support
$E_{di}$ also informs readiness for extubation. A low $E_{di}$ peak on modest support, or a large fall in $E_{di}$ when support is temporarily reduced, suggests that the diaphragm is not overloaded and that the infant may tolerate removal of the tube; a persistently high $E_{di}$ despite escalation argues for continuing support. Used this way, $E_{di}$ complements the conventional criteria of $FiO_2$, PEEP, and blood-gas stability.
Advantages of NAVA
Synchrony and proportionality
The mode's principal advantage is near-instantaneous, proportional synchrony. Trigger delay is reduced to the electromechanical latency of the ventilator, and because pressure follows drive breath to breath, the infant retains control of respiratory timing, tidal volume, and end-expiratory volume. This preserves the variability that characterises normal breathing and avoids the imposed regularity of pressure-targeted modes.
Tolerance of leaks and non-invasive use
Because the trigger signal is myoelectric and independent of the breathing circuit, NAVA functions in the presence of large leaks. This makes non-invasive NAVA (NIV-NAVA) uniquely feasible: synchronised, proportional assistance can be delivered through nasal prongs or a mask even when mouth leak would defeat a pneumatic trigger. NIV-NAVA is therefore used both as primary support for respiratory distress syndrome and as post-extubation support.
Avoiding over-assist and disuse atrophy
Pressure-targeted modes can deliver more pressure than the infant needs, suppressing drive and promoting ventilator-induced diaphragmatic dysfunction and disuse atrophy. In NAVA the ceiling on assist is set by neural output itself, and the fall in $E_{di}$ beyond the breakpoint provides an observable guard against over-assist. Whether this translates into preserved diaphragmatic strength remains an open question, but the physiological rationale is strong.
| Feature | NAVA | Pressure-support ventilation (PSV) |
|---|---|---|
| Trigger signal | Diaphragm $E_{di}$ (myoelectric) | Airway pressure or flow (pneumatic) |
| Inspiratory pressure | Proportional to instantaneous $E_{di}$ | Fixed by the clinician, breath to breath |
| Trigger delay | Minimal (myoelectric) | 50–200 ms typical |
| Performance with leaks | Robust; suitable for NIV | Degraded; trigger failure common |
| Breath-to-breath variability | Preserved | Largely abolished by fixed pressure |
| Monitoring of drive | Continuous $E_{di}$ | None |
| Requirement | Intact respiratory drive and dedicated catheter | None specific |
Limitations, Pitfalls and Contraindications
Signal artefacts
The commonest technical problem is cardiac electrical activity. The heart lies close to the oesophagus, and the QRS complex can contaminate the $E_{di}$ trace, especially in the smallest infants and when the catheter is slightly high. Because NAVA averages cardiac and diaphragmatic activity, this artefact can inflate the apparent $E_{di}$ peak, trigger breaths when the diaphragm is silent, or produce a continuous baseline that masks true effort. Careful positioning and inspection of the electrogram channels — which should show a clear P wave and QRS as landmarks — are the main safeguards.
Catheter malposition and displacement
Correct function requires the electrode array to sit at the crural diaphragm. A catheter that has migrated into the stomach, or has been withdrawn too far, records a poor or absent signal; displacement during handling, feeding, or transport is common. The position should be verified whenever the $E_{di}$ trace becomes implausible and after any episode of care that could have moved the tube. Occlusion of the gastric lumen by feeds or secretions can also blunt the signal.
Dependence on drive and anatomical contraindications
NAVA is a mode for infants who have respiratory drive. It cannot support central apnoea, profound drive suppression, deep sedation, or neuromuscular blockade; in these situations the backup mode does the ventilating and NAVA adds nothing. Absolute or relative contraindications include recent oesophageal or gastrointestinal surgery, oesophageal atresia or tracheo-oesophageal fistula, and anatomical anomalies that preclude safe passage or correct positioning of the catheter. In congenital diaphragmatic hernia the diaphragm itself is abnormal, so $E_{di}$ may be low or asymmetrically recorded and the interpretative assumptions of the mode are weakened. Cost, limited ventilator availability, and a genuine learning curve for both nursing and medical staff further restrict adoption.
There is no intact respiratory drive, the oesophagus is freshly operated on or anomalous, or the catheter cannot be positioned at the crural diaphragm. In these circumstances the mode cannot deliver proportional assist, and the backup conventional mode becomes the actual ventilation.
Evidence Base in Neonates
Physiological studies
Early neonatal studies established the physiological case. NAVA improves patient–ventilator synchrony compared with PSV and reduces the asynchrony index; it lowers PIP and the work of breathing; and it can be applied non-invasively without the trigger failure that leaks cause in pneumatic modes. $E_{di}$ falls as the NAVA level is raised, confirming that the mode unloads the diaphragm, and the breakpoint has been demonstrated directly in preterm infants on NIV-NAVA, as shown in Figure 1.
Clinical outcomes
Clinical evidence is much thinner. Cochrane reviews of NAVA compared with other triggered modes, and of diaphragm-triggered non-invasive support, concluded that the available trials were small and that there is insufficient evidence of benefit on clinically important outcomes such as bronchopulmonary dysplasia, duration of ventilation, or mortality. Randomised comparisons of NIV-NAVA with nasal CPAP after extubation have shown physiological advantages and, in some studies, lower rates of reintubation, but the trials are underpowered and their results are not consistent. Observational series report feasibility in bronchopulmonary dysplasia, congenital diaphragmatic hernia, and evolving lung disease, but none is large enough to change practice alone.
No large multicentre randomised trial has demonstrated that NAVA improves long-term neonatal outcomes over well-delivered conventional or pressure-support ventilation. NAVA should be chosen for its physiological properties — synchrony, proportionality, and leak tolerance — not on the basis of proven mortality or bronchopulmonary dysplasia benefit.
The honest position, therefore, is that NAVA is a physiologically elegant mode with a compelling mechanistic rationale and a modest, largely physiological evidence base. Its place is in units with the equipment, expertise, and monitoring discipline to use it well, and in infants in whom synchrony is the dominant clinical problem.
Key Takeaways
- NAVA reads the electrical activity of the diaphragm ($E_{di}$) directly and delivers pressure in proportion to it, so assistance scales breath by breath with neural drive.
- The control law is $P_{insp}(t) = \text{NAVA level} \times E_{di}(t)$, with the NAVA level expressed in $\text{cmH}_2\text{O}$ per $\mu\text{V}$; pressure is earned, not selected.
- The NAVA level is titrated by finding the breakpoint at which PIP stops rising with increasing gain, then setting the level $0.5$–$1.0\ \text{cmH}_2\text{O}/\mu\text{V}$ below it.
- Triggering is myoelectric and therefore fast and leak-tolerant, which makes NIV-NAVA possible where pneumatic triggers fail.
- $E_{di}$ is also a monitoring tool: it quantifies drive, exposes asynchrony, and informs extubation readiness and the titration of support.
- Cardiac artefact, catheter malposition or displacement, and dependence on intact respiratory drive are the principal pitfalls; recent oesophageal or gastrointestinal surgery and anatomical anomalies are contraindications.
- The neonatal evidence base is dominated by small physiological studies; large trials showing improved long-term clinical outcomes are still lacking.