Oesophageal atresia (EA) is a congenital interruption of the oesophageal lumen, and a tracheoesophageal fistula (TEF) is an abnormal communication between the tracheobronchial tree and the oesophagus. Together they occur in approximately 1 in 2,500 to 4,500 live births, making them the commonest congenital malformation of the oesophagus. In about 85% of infants the fistula connects the distal oesophageal segment to the trachea, and this communication is what turns a surgical problem into a ventilatory one: positive pressure follows the path of least resistance into the stomach rather than the lungs.
The diagnosis is usually apparent within minutes — frothing, drooling, coughing and desaturation with the first feed, and a feeding tube that will not pass beyond about 10 cm. The physiological threat is subtler. A distal fistula is a wider and shorter conduit to the stomach than the bronchial tree is to the alveoli, so ventilation produces gastric distension, cephalad displacement of the diaphragm, loss of functional residual capacity, and respiratory failure that mimics primary lung disease. This chapter covers the embryology, the associated anomalies, pre-operative stabilisation, ventilatory strategy, and peri-operative care.
Embryology and the Anatomy of the Fistula
Failure of the Tracheoesophageal Septum
In the fourth week of gestation the ventral foregut is a single tube that must be partitioned longitudinally into a dorsal oesophagus and a ventral trachea. The tracheoesophageal septum, a mesenchymal ridge growing caudally, fuses the lateral walls to divide the two channels. Partial or disordered fusion produces the malformation spectrum: failure of separation without interruption yields an H-type fistula (Gross type E), whereas failure of the dorsal tube to recanalise after its sixth-week obliteration yields atresia, and the level of arrest determines whether the fistula is proximal, distal or both.
In the commonest arrangement the upper pouch is blind and thick-walled, separated from the lower pouch by a variable gap, while the distal oesophagus arises from the trachea at or just above the carina. The fistula is short, muscular and several millimetres across, and it is this calibre that makes it a low-resistance leak.
The Gross Classification
The Gross classification describes five anatomical patterns. Type C, atresia with a distal fistula, accounts for about 85% of cases, isolated atresia (type A) for about 8%, and the H-type fistula without atresia (type E) for about 4%; the proximal (type B) and double (type D) fistulae are rare.
| Type | Anatomy | Approximate frequency | Clinical features |
|---|---|---|---|
| A | Oesophageal atresia without fistula; both segments blind | 5–8% | Gasless abdomen; long gap; copious secretions; pure atresia |
| B | Proximal pouch fistula with distal atresia | ~2% | Rare; spillage through the upper fistula causes upper-lobe infiltrates |
| C | Distal fistula from the lower pouch to the trachea | 85–87% | Commonest; air in the stomach, distension and respiratory distress |
| D | Both proximal and distal fistulae | ~1% | Very rare; combines the features of types B and C |
| E | H-type fistula without atresia | ~4% | Feeding initially normal; recurrent cough, choking, cyanosis and pneumonia |
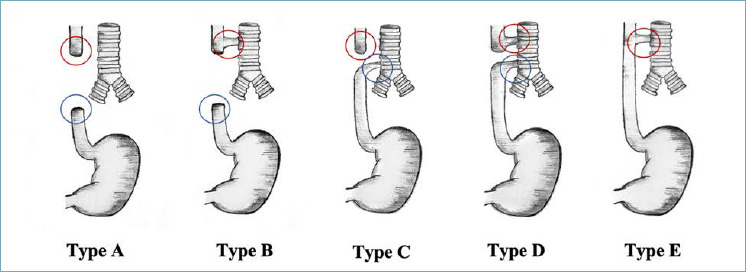 Figure 1: The Gross A–E classification of oesophageal atresia and tracheoesophageal fistula, showing the dominant distal-fistula form (type C, about 85%), isolated atresia (type A, about 8%) and the H-type fistula (type E, about 4%). (Source: Ludwig K, De Bartolo D, Salerno A, Ingravallo G, Cazzato G, Giacometti C, Dall'Igna P. Pathologica 2022. DOI: 10.32074/1591-951X-553).
The Isolated Atresia with a Blind Pouch
Type A behaves differently because there is no fistula: no air reaches the stomach, so the abdominal radiograph is gasless, and the problem is chronic aspiration of secretions pooled in a dilated, thick-walled upper pouch rather than gas steal. The pouch is stiff and difficult to decompress, predisposing to aspiration during induction of anaesthesia, and the long gap usually requires staged repair or oesophageal replacement. It must be suctioned continuously throughout the peri-operative period.
Associated Anomalies and Pre-operative Assessment
The VACTERL Association
Between 50 and 70% of infants with EA/TEF have at least one additional anomaly, and it is often this anomaly set, rather than the oesophageal lesion, that determines outcome. The VACTERL association comprises Vertebral defects, Anal atresia, Cardiac defects, Tracheoesophageal fistula with oesophageal atresia, Renal anomalies and Limb (especially radial) defects.
Screen every infant before surgery: examine and image the spine; inspect the anus and perineum; perform echocardiography; obtain a renal ultrasound; and examine the limbs and thumbs. Document the findings formally, because they alter the anaesthetic plan and the surgical approach.
Mandatory Screening Before Repair
Echocardiography is the single most important pre-operative test. Structural heart disease occurs in 20–30% of infants and includes septal defects, tetralogy of Fallot and a right-sided aortic arch, which changes the side of surgical access. Renal ultrasonography identifies horseshoe or absent kidneys and hydronephrosis, and spinal imaging detects vertebral and cord anomalies with anaesthetic and neurological implications. Surgical consultation follows immediately, but the timing of repair is set by physiological stability, not by the clock.
Pre-operative Stabilisation
Decompression of Pouch and Stomach
The foundational manoeuvre is continuous decompression of the upper pouch with a large-bore tube — a Replogle or similar sump tube on continuous low suction — so that swallowed saliva is removed before it can be aspirated. The tube must never occlude or be clamped, since secretions accumulate within minutes. Where a distal fistula is present, air also enters the stomach, so a second orogastric tube on free drainage prevents distension under the pressures used to ventilate the lungs.
Positioning, Secretions and the Mask-Ventilation Trap
The infant is nursed head-up at about 30 degrees, which reduces gravitational reflux of gastric contents into the fistula and pouch, and is turned and suctioned frequently. The single most dangerous delivery-room intervention is positive-pressure ventilation by face mask: because the fistula is the path of least resistance, gas enters the stomach, elevates the diaphragm and worsens respiratory failure while creating the conditions for gastric rupture. Where ventilation is required the infant must be intubated, using the lowest effective pressures. These principles are shared with congenital diaphragmatic hernia.
A Pre-operative Stabilisation and Ventilation Algorithm
graph TD
    A["Suspected EA/TEF: polyhydramnios,<br/>excessive secretions, failed tube passage"] --> B["Nil by mouth; Replogle tube to<br/>continuous low suction in upper pouch"]
    B --> C["Head-up 30 degrees; frequent<br/>suctioning and turning"]
    C --> D["Do NOT bag-mask ventilate;<br/>intubate with low-pressure circuit"]
    D --> E["Radiographs, echocardiography,<br/>renal and vertebral imaging"]
    E --> F{"Adequate gas exchange and<br/>perfusion on gentle ventilation?"}
    F -->|"Yes"| G["Spontaneous or minimally assisted<br/>ventilation: PIP <= 20-25 cmH2O, PEEP 4-5 cmH2O"]
    F -->|"No"| H["Deepen tube tip if anatomy allows;<br/>reduce PIP; decompress the stomach"]
    H --> I{"Gastric distension, hypercapnia<br/>or hypoxaemia persisting?"}
    I -->|"No"| G
    I -->|"Yes"| J["Consider gastrostomy for<br/>continuous gastric decompression"]
    J --> K{"Refractory respiratory failure<br/>despite optimised strategy?"}
    K -->|"No"| G
    K -->|"Yes"| L["Extracorporeal support as a bridge;<br/>ligate the fistula at the earliest opportunity"]
The Ventilation Challenge
The Fistula as a Low-Resistance Leak
The trachea delivers each breath into two resistances in parallel: the lower airways and lung, $R_L$, and the fistula, $R_F$. Sharing approximately the same driving pressure, gas divides in inverse proportion to resistance.
For laminar flow, tube resistance follows the Hagen–Poiseuille relation
$$R = \frac{8\,\mu\,L}{\pi\,r^{4}}$$where $\mu$ = gas viscosity ($\text{Pa}\cdot\text{s}$), $L$ = length ($\text{m}$) and $r$ = radius ($\text{m}$), so $R$ carries units of $\text{Pa}\cdot\text{s}\cdot\text{m}^{-3}$. For two parallel conduits sharing a driving pressure:
$$\dot V_F = \frac{R_L}{R_L + R_F}\,\dot V_{tot}, \qquad \dot V_L = \frac{R_F}{R_L + R_F}\,\dot V_{tot}$$where $\dot V_{tot}$, $\dot V_F$ and $\dot V_L$ are the total, fistula and lung flows ($\text{mL}\cdot\text{s}^{-1}$). Hence
$$\frac{\dot V_F}{\dot V_L} = \frac{R_L}{R_F} = \frac{R_L\,\pi\,r_F^{4}}{8\,\mu\,L_F}$$Because radius enters to the fourth power, a fistula only 1–2 mm across offers a resistance far below that of the bronchial tree, so the stomach can command a large fraction of each breath.
Gastric Distension, Diaphragmatic Splinting and Respiratory Failure
Inflation of the stomach raises intra-abdominal pressure and displaces both hemidiaphragms cephalad. Because the diaphragm is the principal neonatal inspiratory muscle, this directly reduces tidal volume and functional residual capacity, while the raised intra-abdominal pressure impedes venous return and can reduce cardiac output. The spiral is self-reinforcing: positive pressure inflates the stomach, the stomach splints the diaphragm, higher pressure is needed for the same ventilation, and more gas is diverted through the fistula. Unchecked, this culminates in gastric perforation, tension pneumoperitoneum and cardiovascular collapse.
Recognising Ventilation Through a Fistula
Fistula steal is a clinical and radiological diagnosis, suspected in any intubated infant with EA/TEF who needs escalating pressures for worsening gas exchange while the chest radiograph shows poor lung volume and a distended stomach.
A rising peak pressure needed for a stable tidal volume, increasing abdominal girth with a tympanitic abdomen, an enlarging gastric bubble on serial radiographs, and poor carbon dioxide clearance despite unchanged settings all point to gas diversion rather than parenchymal disease.
Ventilation Strategy
Intubation and the Position of the Tube Tip
Intubation is mandatory whenever respiratory support is needed, and tube position is the most powerful lever. Where anatomy permits, the tip is advanced distal to the fistula but above the carina, confirmed by auscultation, radiography and, where available, flexible bronchoscopy. A tip below the fistula removes the communication from the ventilated circuit and converts a decompensated parallel system into a single series circuit; this is possible only when enough trachea remains between fistula and carina. A tube placed too deep intubates the right main bronchus and produces left-sided collapse.
Pressure Ceilings, Spontaneous Breathing and PEEP
The strategy minimises the driving pressure available to the fistula. Peak pressures are kept as low as practicable, typically no more than about 20–25 $\text{cmH}_2\text{O}$; inspiratory times are short; and spontaneous breathing is preserved where possible, because negative-pressure inspiration distributes gas more favourably between lung and fistula than positive pressure does. PEEP is used cautiously: it recruits lung and stabilises functional residual capacity, but excessive PEEP raises mean airway pressure and may increase flow through a patent fistula. A PEEP of about 4–5 $\text{cmH}_2\text{O}$, titrated to oxygenation and haemodynamics, is a reasonable start, with permissive hypercapnia accepted in preference to high pressures provided pH is preserved.
First exclude the fistula by positioning the tube tip distal to it; second, lower the driving pressure; third, decompress the stomach. Only then escalate respiratory support, because escalation without decompression enlarges the leak.
Gastric Perforation, Gastrostomy and Extracorporeal Support
The stomach of an infant with a large distal fistula is at genuine risk of rupture under positive pressure.
A tense, rapidly enlarging abdomen with hypotension, bradycardia and falling saturations during ventilation of an infant with a distal fistula indicates gas entering the peritoneum. Stop positive-pressure ventilation where possible, decompress the stomach, and call for emergency surgical decompression and fistula ligation.
When distension recurs despite orogastric decompression, a gastrostomy on open drainage vents the stomach continuously without sacrificing the whole breath to the leak. In extreme cases, or when ventilation cannot be achieved at tolerable pressures, extracorporeal support is used as a bridge, with the fistula ligated at the earliest safe opportunity to remove the shunt.
The Laryngeal Cleft and Associated Airway Lesions
Associated airway anomalies complicate ventilation. A laryngeal cleft allows gas to escape into the oesophagus above the level of the fistula, adding a second leak that is unaffected by the position of the endotracheal tube; tracheomalacia, subglottic stenosis and vocal cord palsy instead increase resistance to effective ventilation. With a laryngeal cleft, the strategy must account for both leaks, and cleft repair may be required before stable ventilation can be achieved.
Peri-operative and Post-operative Ventilation
Anastomotic Tension and Leak
The fresh oesophageal anastomosis is the vulnerable structure: an oedematous, tension-bearing suture line in a poorly vascularised segment, endangered by mechanical traction and by positive airway pressure transmitted to the posterior suture line. The post-operative strategy is therefore the gentlest that maintains acceptable gas exchange. Risk factors for leak include long gaps, low birth weight, prematurity and excessive anastomotic tension. A leak presents with pneumothorax, mediastinal or pleural air, sepsis, or a change in chest-drain character, and demands prompt recognition and often re-exploration.
Analgesia, Sedation and the Stiff Blind Pouch
Adequate analgesia is more than comfort: it reduces respiratory drive and work of breathing, and therefore the pressures the anastomosis must tolerate. Multimodal analgesia, with opioid infusions titrated to a validated neonatal pain scale and regional techniques where available, is preferred to deep continuous sedation, which prolongs ventilation and impairs secretion clearance. In isolated atresia the stiff blind pouch remains a reservoir requiring suction and decompression throughout the peri-operative period and, when repair is staged across a long gap, well beyond it.
Key Takeaways
- EA/TEF results from failure of the tracheoesophageal septum to partition the foregut; the Gross classification defines five patterns, of which the distal-fistula form (type C) accounts for about 85%.
- Isolated atresia (type A) has no fistula, a gasless abdomen and a stiff, aspiration-prone pouch; it is a problem of secretion clearance and long-gap repair, not gas steal.
- Associated anomalies affect 50–70% of infants, so every infant needs a VACTERL screen, with echocardiography the most important pre-operative test.
- Pre-operative stabilisation means nil by mouth, continuous upper-pouch suction, free gastric drainage where a fistula is present, head-up positioning, and avoidance of face-mask positive-pressure ventilation.
- A distal fistula is a low-resistance parallel path, so gas is diverted to the stomach in proportion to resistance and the fourth power of fistula radius, producing distension, diaphragmatic splinting and worsening respiratory failure.
- Management centres on positioning the tube tip distal to the fistula where possible, keeping airway pressures low, favouring spontaneous breathing, and using PEEP cautiously.
- Gastric perforation is a lethal crisis; refractory distension may require gastrostomy or extracorporeal support with early fistula ligation, and after repair the anastomosis is protected by gentle ventilation and multimodal analgesia.