Children are not miniature adults. The pediatric respiratory system undergoes dramatic anatomical, structural, and physiological transformations from extreme prematurity through adolescence. Understanding these unique developmental characteristics is essential for the clinician managing neonatal and pediatric mechanical ventilation. Failure to account for high chest wall compliance, narrow airway geometry, elevated baseline airway resistance, closing capacity exceeding resting functional residual capacity (FRC), and high metabolic oxygen consumption precipitously accelerates respiratory failure, dynamic airway collapse, and catastrophic peri-intubation hypoxemic arrest.
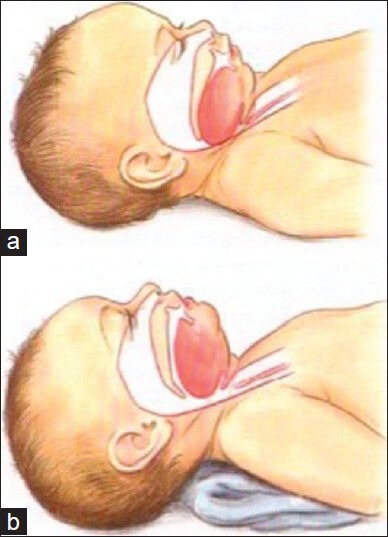 Figure 1: Comparative upper airway anatomical configuration in infancy illustrating: (a) Neutral supine posture wherein a large, protuberant occiput induces involuntary cervical flexion, driving the disproportionately large tongue base posteriorly against the pharyngeal wall to create acute upper airway occlusion. (b) Restoration of pharyngeal patency and visual/laryngeal axial alignment following placement of a sub-shoulder roll (sniffing position). Source: Harless J, Ramaiah R, Bhananker SM. Int J Crit Illn Inj Sci. 2014;4(1):65-70. DOI: 10.4103/2229-5151.128015. PMCID: PMC3982373.
graph TD
    A["Developmental Anatomical & Physiological Features"] --> B["Airway Geometry"]
    A --> C["Thoracic Mechanics"]
    A --> D["Metabolic Demand"]

    B --> B1["Large Tongue + Cephalad Larynx (C3-C4)"]
    B --> B2["Floppy Omega Epiglottis + Angle of Insertion"]
    B --> B3["Narrowest Segment: Functional Cricoid Ring"]

    C --> C1["High Chest Wall Compliance (Ccw >> CL)"]
    C --> C2["Horizontal Rib Angle (Ineffective Pump-Handle)"]
    C --> C3["Low Baseline FRC with Closing Capacity > FRC"]
    C --> C4["Diaphragm Type I Fibers: 10-25% (Term/Preterm)"]

    D --> D1["High Basal VO2 (6-8 mL/kg/min)"]
    D --> D2["Rapid Desaturation Velocity during Apnea"]

    B3 --> E["Precipitous Poiseuille Resistance Amplification (R ∝ 1/r⁴)"]
    C1 --> F["Paradoxical Inward Retractions & Alveolar Derecruitment"]
    C3 --> F
    C4 --> G["Rapid Diaphragmatic Muscle Fatigue"]
    D2 --> H["Extremely Narrow Peri-Intubation Apneic Window"]
Developmental Upper and Lower Airway Anatomy
The infant and young child possess distinct upper airway configurations that create significant mechanical vulnerability and require specific technical approaches during non-invasive support, bag-mask ventilation, and direct or video laryngoscopy.
graph LR
    subgraph Pediatric["Pediatric Airway Profile"]
        P1["Large Occiput"] --> P2["Involuntary Neck Flexion in Supine"]
        P3["Large Tongue / Small Mandible"] --> P4["Posterior Pharyngeal Obstruction"]
        P5["Cephalad Larynx (C3-C4)"] --> P6["Acute Angle with Visual Axis"]
        P7["Floppy Omega-Shaped Epiglottis"] --> P8["Requires Straight (Miller) Blade to Lift"]
        P9["Cricoid Funnel / Narrowing"] --> P10["Subglottic Edema Bottleneck"]
    end
    subgraph Adult["Adult Airway Profile"]
        A1["Flat Occiput"] --> A2["Neutral Cervical Alignment"]
        A3["Proportional Tongue"] --> A4["Stable Pharyngeal Space"]
        A5["Caudal Larynx (C5-C6)"] --> A6["Linear Line-of-Sight Axis"]
        A7["Broad Flat Leaf Epiglottis"] --> A8["Easily Indirectly Lifted (Macintosh)"]
        A9["Cylindrical Larynx"] --> A10["Glottis / Vocal Cords Narrowest"]
    end
Craniofacial and Laryngeal Morphometry
- Occipital Prominence: The pediatric cranium features a disproportionately large, protuberant occiput relative to the torso. When placed supine on a flat surface, the infant head is forced into passive flexion, projecting the base of the tongue against the posterior pharyngeal wall and occluding the extrathoracic airway.
- Relative Macroglossia and Micrognathia: The infant tongue occupies a significantly larger proportion of the oral cavity. Combined with a relatively small, retrognathic mandible, any loss of pharyngeal dilator muscle tone (such as during induction of anesthesia or encephalopathy) causes immediate posterior airway collapse.
- Cephalad and Anterior Laryngeal Position: The infant larynx is positioned more cephalad (vertebral level $C_3-C_4$ at birth, descending to $C_4-C_5$ by mid-childhood, and reaching $C_5-C_6$ in adults). This superior and anterior location creates a more acute, angulated trajectory between the oral cavity, pharyngeal axis, and tracheal axis, complicating direct line-of-sight visualization during direct laryngoscopy.
- Omega-Shaped ($\Omega$), Floppy Epiglottis: The pediatric epiglottis is narrow, elongated, folded longitudinally (omega-shaped), and highly compliant. It projects posteriorly at a 45-degree angle over the laryngeal inlet. Because of its flexibility, the epiglottis cannot reliably be displaced indirectly via tension placed on the hypoepiglottic ligament with a curved Macintosh blade; instead, direct elevation with a straight blade (e.g., Miller blade) is often required.
- Funnel-Shaped Larynx and the Cricoid Ring: While the vocal cords constitute the narrowest dynamic aperture in adults, the pediatric airway has historically been described as a conical funnel where the subglottic lumen at the level of the non-distensible, complete cartilaginous cricoid ring represents the narrowest anatomical constriction. Although modern dynamic magnetic resonance imaging (MRI) demonstrates an elliptical geometry in conscious infants, the rigid, non-expanding nature of the cricoid cartilage makes the subglottic mucosal sleeve extraordinarily vulnerable to pressure-induced ischemic necrosis, circumferential edema, and life-threatening post-extubation stenosis.
| Anatomical Parameter | Neonate / Infant | Child (2–8 Years) | Adult |
|---|---|---|---|
| Occiput Size | Markedly prominent (promotes flexion) | Moderately prominent | Flat / small relative to torso |
| Tongue to Pharynx Ratio | Disproportionately large | Intermediate | Proportional |
| Laryngeal Level | $C_3 - C_4$ | $C_4 - C_5$ | $C_5 - C_6$ |
| Epiglottis Morphology | Long, stiff/floppy $\Omega$-shaped, acute angle | Intermediate | Broad, flat, flexible leaf |
| Laryngeal Geometry | Funnel / conical (subglottic narrowing) | Transitional | Cylindrical (glottic aperture narrowest) |
| Narrowest Airway Segment | Cricoid ring (rigid cartilaginous ring) | Cricoid / glottis transition | Rima glottidis (vocal cords) |
| Tracheal Length | $4 - 5\text{ cm}$ | $6 - 8\text{ cm}$ | $10 - 14\text{ cm}$ |
Because the infant's large occiput forces the cervical spine into flexion when lying flat on a firm mattress, never place an occipital pillow under an infant. Instead, place a 1 to 2 cm folded towel or roll under the shoulders and interscapular region. This aligns the oral, pharyngeal, and laryngeal axes into the optimal neutral "sniffing" posture, relieving pharyngeal obstruction and maximizing direct line-of-sight during laryngoscopy.
Poiseuille's Law and Pediatric Airway Resistance
Airway resistance ($R_{aw}$) in the tracheobronchial tree is governed by the principles of fluid dynamics described by the Hagen-Poiseuille relationship for laminar airflow:
For laminar gas flow through a cylindrical conduit, the pressure drop ($\Delta P$) across the airway is proportional to gas flow ($\dot{V}$) and airway resistance ($R_{aw}$):
$$\Delta P = \dot{V} \cdot R_{aw}$$Where Hagen-Poiseuille's law defines resistance as:
$$R_{aw} = \frac{8 \cdot \eta \cdot l}{\pi \cdot r^4}$$Where:
- $\eta$ = Dynamic gas viscosity ($\text{Pa}\cdot\text{s}$)
- $l$ = Airway segment length ($\text{cm}$)
- $r$ = Internal radius of the airway lumen ($\text{mm}$)
Under turbulent conditions (such as high-velocity flow through an obstructed subglottis or endotracheal tube), resistance becomes even more sensitive to luminal narrowing:
$$R_{turbulent} \propto \frac{\rho \cdot l}{r^5}$$Where $\rho$ represents gas density ($\text{g/L}$).
graph TD
    A["Baseline Infant Subglottic Airway (Radius = 2.0 mm, Area = 12.57 mm²)"] -->|1.0 mm Circumferential Edema| B["Edematous Subglottis (Radius = 1.0 mm, Area = 3.14 mm²)"]
    C["Baseline Adult Subglottic Airway (Radius = 4.0 mm, Area = 50.27 mm²)"] -->|1.0 mm Circumferential Edema| D["Edematous Subglottis (Radius = 3.0 mm, Area = 28.27 mm²)"]

    B --> E["75% Cross-Sectional Area Loss<br>16-Fold (1600%) Resistance Increase (Laminar)<br>32-Fold (3200%) Resistance Increase (Turbulent)"]
    D --> F["44% Cross-Sectional Area Loss<br>3.16-Fold (316%) Resistance Increase (Laminar)"]

    E --> G["Severe Stridor, Work of Breathing Surge, Imminent Exhaustion"]
    F --> H["Mild Dysphonia, Moderate Exertional Dyspnea"]
Mathematical Proof of 1 mm Subglottic Edema
To illustrate the profound impact of luminal narrowing in the infant versus the adult, consider the development of $1.0\text{ mm}$ of uniform circumferential mucosal edema (subglottic croup, post-extubation edema, or trauma):
Infant Airway Mechanics
- Initial inner diameter: $D_0 = 4.0\text{ mm} \implies r_0 = 2.0\text{ mm}$
- Initial cross-sectional area: $$A_0 = \pi \cdot (r_0)^2 = \pi \cdot (2.0)^2 = 4\pi \approx 12.57\text{ mm}^2$$
- Following $1.0\text{ mm}$ of circumferential mucosal edema, the new radius becomes $r_1 = 2.0 - 1.0 = 1.0\text{ mm}$
- Post-edema cross-sectional area: $$A_1 = \pi \cdot (r_1)^2 = \pi \cdot (1.0)^2 = 1\pi \approx 3.14\text{ mm}^2$$
- Percentage reduction in cross-sectional area: $$\Delta A = \frac{A_0 - A_1}{A_0} \times 100 = \frac{4\pi - 1\pi}{4\pi} \times 100 = \mathbf{75.0\% \text{ reduction}}$$
- Relative change in laminar airway resistance: $$\frac{R_1}{R_0} = \left(\frac{r_0}{r_1}\right)^4 = \left(\frac{2.0}{1.0}\right)^4 = 2^4 = \mathbf{16\text{-fold increase } (1600\%)}$$
- Relative change in turbulent airway resistance: $$\frac{R_{1, turb}}{R_{0, turb}} = \left(\frac{r_0}{r_1}\right)^5 = \left(\frac{2.0}{1.0}\right)^5 = 2^5 = \mathbf{32\text{-fold increase } (3200\%)}$$
Adult Airway Mechanics
- Initial inner diameter: $D_0 = 8.0\text{ mm} \implies r_0 = 4.0\text{ mm}$
- Initial cross-sectional area: $$A_0 = \pi \cdot (4.0)^2 = 16\pi \approx 50.27\text{ mm}^2$$
- Following $1.0\text{ mm}$ circumferential edema: $r_1 = 4.0 - 1.0 = 3.0\text{ mm}$
- Post-edema cross-sectional area: $$A_1 = \pi \cdot (3.0)^2 = 9\pi \approx 28.27\text{ mm}^2$$
- Percentage reduction in cross-sectional area: $$\Delta A = \frac{16\pi - 9\pi}{16\pi} \times 100 = \frac{7}{16} \times 100 = \mathbf{43.75\% \text{ reduction}}$$
- Relative change in laminar airway resistance: $$\frac{R_1}{R_0} = \left(\frac{4.0}{3.0}\right)^4 = (1.333)^4 \approx \mathbf{3.16\text{-fold increase } (316\%)}$$
The exact same $1\text{ mm}$ mucosal swelling that produces mild hoarseness in an adult creates a catastrophic 75% luminal occlusion and a 16-fold to 32-fold surge in airway resistance in an infant. This triggers severe work of breathing, intercostal and subcostal retractions, inspiratory stridor, dynamic airway collapse, and rapid ventilatory exhaustion.
Chest Wall and Lung Mechanics
The respiratory mechanics of the neonate and infant are characterized by an inverse relationship between chest wall compliance ($C_{cw}$) and lung compliance ($C_L$), creating an inherently unstable mechanical operating point for resting lung volumes.
graph TD
    A["Highly Cartilaginous Rib Cage"] --> B["Excessively High Chest Wall Compliance (Ccw >> CL)"]
    C["Low Alveolar Number & Thick Septa"] --> D["Low Lung Compliance (CL)"]

    B & D --> E["Inward Elastic Recoil of Lung Overwhelms Outward Recoil of Chest Wall"]
    E --> F["Severely Reduced Static Functional Residual Capacity (FRC)"]
    F --> G["Closing Volume (CV) + Residual Volume (RV) = Closing Capacity (CC)"]
    G --> H["Closing Capacity Exceeds Resting FRC (CC >= FRC)"]
    H --> I["Tidal Breathing Falls Within Airway Closure Zone"]
    I --> J["Microatelectasis, Intrapulmonary Shunting, Refractory Hypoxemia"]
Chest Wall Compliance vs. Lung Compliance
In healthy adults, the outward elastic recoil of the rigid, bony thoracic cage balances the inward elastic recoil of the lung parenchyma at approximately $40-50\%$ of Total Lung Capacity (TLC), establishing an optimal resting FRC well above the Closing Capacity (CC).
In neonates and infants:
- Excessively Compliant Chest Wall ($C_{cw} \gg C_L$): The pediatric rib cage is composed predominantly of pliable cartilage rather than ossified bone. Consequently, the chest wall exerts almost zero outward spring-back recoil pressure.
- Horizontal Rib Orientation: Ribs in infants emerge horizontally from the vertebral column rather than sloping downward in the oblique adult configuration. When the intercostal muscles contract, they cannot produce the classic "bucket-handle" (transverse expansion) or "pump-handle" (anteroposterior expansion) increases in intrathoracic volume. Rib cage elevation merely stabilizes the thoracic wall rather than generating significant negative intrapleural pressure.
- Closing Capacity Exceeds FRC ($CC \ge FRC$): Because the outward thoracic recoil is minimal, the static balance point between lung and chest wall occurs at an exceptionally low volume ($\approx 10-15\%\text{ TLC}$). In infants, the Closing Capacity—the volume at which small non-cartilaginous terminal airways collapse during expiration—is higher than the resting FRC. Consequently, normal resting tidal ventilation occurs within the range of airway closure, predisposing infants to dependent microatelectasis, low ventilation-perfusion ($\dot{V}/\dot{Q}$) matching, and substantial right-to-left intrapulmonary shunt.
graph LR
    subgraph Adult Mechanics
        A1["Outward Chest Wall Recoil (+Pcw)"] <--> A2["Inward Lung Recoil (-PL)"]
        A1 & A2 --> A3["Resting FRC ≈ 45% TLC"]
        A3 --> A4["FRC >> Closing Capacity"]
        A4 --> A5["Airways Remain Patent Throughout Expiration"]
    end
    subgraph Pediatric Mechanics
        P1["Minimal Outward Recoil (Cartilage)"] <--> P2["Strong Inward Lung Recoil"]
        P1 & P2 --> P3["Resting FRC ≈ 15-20% TLC"]
        P3 --> P4["Closing Capacity ≥ FRC"]
        P4 --> P5["Airways Collapse During Normal Tidal Expiration"]
    end
Dynamic FRC Generation in the Spontaneously Breathing Infant
To prevent total alveolar derecruitment at end-expiration, the intact, non-intubated infant utilizes active physiological mechanisms to maintain an elevated dynamic FRC above the static equilibrium volume:
- Laryngeal Braking (Expiratory Grunting): The infant dynamically adducts the vocal cords during early and mid-expiration, creating physiological end-expiratory resistance that slows expiratory flow and maintains an elevated positive end-expiratory airway pressure.
- Tachypnea with Short Expiratory Time ($T_E$): By maintaining a rapid respiratory rate, inspiration is initiated before complete passive exhalation occurs, trapping a small residual volume (intrinsic PEEP) to keep terminal airways open.
- Tonic Diaphragmatic Contraction: Post-inspiratory diaphragmatic tone persists into early expiration, functioning as an internal brake against lung deflation.
When an infant is sedated, paralyzed, or intubated, the endotracheal tube stents open the vocal cords, completely abolishing natural laryngeal braking and post-inspiratory diaphragmatic tone. Static FRC collapses immediately to sub-closing capacity levels. Every mechanically ventilated pediatric patient must receive an extrinsic baseline PEEP of 5 to 7 cmH2O to restore and maintain anatomical FRC.
Diaphragmatic Muscle Fiber Composition and Fatigue Kinetics
The infant respiratory system relies almost exclusively on the diaphragm as the primary driver of tidal ventilation due to the horizontal rib orientation and compliant rib cage. However, the infant diaphragm is histochemically and biomechanically poorly equipped for sustained heavy workloads.
graph TD
    A["Sustained High Work of Breathing<br>(Edema, Atelectasis, Bronchospasm)"] --> B["Diaphragmatic Muscle Fiber Stress"]
    B --> C{"Fiber Composition"}
    C -->|Adult Diaphragm: 50-55% Type I| D["Sustained Aerobic Endurance & Fatigue Resistance"]
    C -->|Term Infant: 25% Type I| E["Rapid Glycogen Depletion & Lactate Accumulation"]
    C -->|Preterm Infant: 10% Type I| E

    E --> F["Diaphragmatic Contractile Failure"]
    F --> G["Loss of Tidal Volume & Severe Inward Retractions"]
    G --> H["Acute Hypercapnia, Respiratory Acidosis, Cardiorespiratory Arrest"]
Histochemical Maturation of the Diaphragm
- Type I Muscle Fibers: Slow-twitch, high-oxidative, fatigue-resistant fibers rich in mitochondria and myoglobin, designed for continuous aerobic work.
- Type IIc / IIa / IIb Muscle Fibers: Fast-twitch, low-oxidative, highly glycolytic fibers that generate rapid contractile force but fatigue quickly under continuous strain.
| Patient Population | Diaphragm Type I (Fatigue-Resistant) Fibers | Diaphragm Type II (Fatigue-Prone) Fibers | Clinical Fatigue Propensity |
|---|---|---|---|
| Preterm Infant (< 30 weeks) | $\approx 10\%$ | $\approx 90\%$ | Extremely High (minutes to fatigue) |
| Full-Term Neonate | $\approx 25\%$ | $\approx 75\%$ | High (hours under high load) |
| Child (2 Years) | $\approx 40\%$ | $\approx 60\%$ | Moderate |
| Adult | $\mathbf{50 - 55\%}$ | $\mathbf{45 - 50\%}$ | Low (High Endurance Reserve) |
Intercostal and Diaphragmatic Interaction
When an infant experiences respiratory distress (e.g., bronchiolitis, pneumonia, or RDS), the high negative intrapleural pressures generated by the contracting diaphragm pull the excessively compliant, cartilaginous chest wall inward rather than expanding the lung parenchyma. This phenomenon—manifested clinically as suprasternal, intercostal, subcostal, and substernal retractions—represents wasted mechanical work. A substantial portion of the energy consumed by the diaphragm is dissipated deforming the chest wall rather than moving alveolar gas, accelerating the depletion of glycogen reserves in Type II muscle fibers and leading to sudden neuromuscular ventilatory arrest.
Gas Exchange and Metabolic Dynamics
In addition to structural and mechanical vulnerabilities, the baseline metabolic rate of infants and young children places immense strain on the oxygen delivery and carbon dioxide elimination systems.
graph LR
    A["Pediatric Metabolic Rate: VO2 = 6-8 mL/kg/min"] --> B["2x-3x Higher Than Adult (3-4 mL/kg/min)"]
    C["Resting Alveolar Functional Residual Capacity: Low"] --> D["Small Oxygen Reservoir at Apnea"]

    B & D --> E["Apneic Desaturation Velocity: Extremely Rapid (dSaO2/dt)"]
    E --> F["Critical Hypoxemia within 30-45 Seconds of Apnea"]
    F --> G["Hypoxemic Bradycardia & Asystolic Cardiac Arrest"]
Basal Oxygen Consumption ($\dot{V}O_2$) and Carbon Dioxide Production ($\dot{V}CO_2$)
- Infant $\dot{V}O_2$: $6 - 8\text{ mL/kg/min}$
- Adult $\dot{V}O_2$: $3 - 4\text{ mL/kg/min}$
- Infant Minute Ventilation Target: To eliminate the proportionally higher metabolic $\dot{V}CO_2$, the resting minute ventilation in infants must be $200 - 300\text{ mL/kg/min}$ (compared to $80 - 100\text{ mL/kg/min}$ in adults). Because tidal volume is biologically constrained by lung mass ($V_T \approx 6 - 8\text{ mL/kg}$ across all mammalian species), this elevated minute ventilation is achieved almost entirely via a high physiological respiratory rate ($30 - 50\text{ breaths/min}$ in neonates).
Desaturation Kinetics During Apnea
The time required for an arterial oxygen saturation ($SpO_2$) to fall from $100\%$ to $\le 85\%$ during apnea is governed by the ratio of the oxygen reservoir size (functional residual capacity multiplied by alveolar oxygen fraction, $FRC \times F_A O_2$) to the rate of cellular oxygen consumption ($\dot{V}O_2$):
$$t_{desat} \propto \frac{\text{Oxygen Reservoir}}{\text{Oxygen Consumption}} = \frac{FRC \cdot F_A O_2}{\dot{V}O_2}$$In the infant:
- The numerator ($FRC$) is reduced ($15-20\text{ mL/kg}$ vs $30-35\text{ mL/kg}$ in adults).
- The denominator ($\dot{V}O_2$) is doubled ($6-8\text{ mL/kg/min}$ vs $3-4\text{ mL/kg/min}$).
- Consequently, the time to critical desaturation during apnea is shortened by a factor of 3 to 4. A paralyzed infant can desaturate from $100\%$ to life-threatening hypoxemia ($< 70\%$) within 30 to 45 seconds, compared to 4 to 6 minutes in a healthy adult.
Because of extremely rapid desaturation kinetics, standard bag-mask pre-oxygenation must always be accompanied by continuous apneic oxygenation via high-flow nasal cannula (HFNC) or low-flow nasal prongs ($1-2\text{ L/kg/min}$ of $100\%\text{ }FiO_2$) during pediatric intubation attempts. Hypoxemia in infants rapidly precipitates vagal bradycardia, reduced cardiac output, and asystole.
Alveolar Development and Collateral Ventilation
The microarchitectural development of the pulmonary parenchyma continues long after birth, passing through distinct histological stages:
timeline
    title Human Pulmonary Development Stages
    Pseudoglandular (Weeks 5-17) : Major conducting airways formed : Non-respiratory epithelium
    Canalicular (Weeks 16-26) : Formation of respiratory bronchioles : Capillary bed approaches epithelium : Surfactant synthesis starts (W24)
    Saccular (Weeks 24-38) : Terminal clusters expand into saccules : Primary septation begins : Surfactant stores mature
    Alveolar (Week 36 to ~8 Years) : Secondary septation creates 300-500 million true alveoli : Thinning of double-capillary network into single layer
- Alveolar Number and Surface Area:
- At birth, the full-term neonate possesses only approximately $20 - 50\text{ million}$ primitive terminal saccules.
- Through the process of secondary septation, alveolar multiplication continues vigorously throughout the first 2 to 3 years of life and extends up to approximately 8 years of age, reaching the adult complement of $300 - 500\text{ million}$ alveoli.
- Alveolar gas exchange surface area expands exponentially from $\approx 2.8\text{ m}^2$ at birth to $> 100\text{ m}^2$ in adulthood.
- Absence of Collateral Channels of Ventilation:
- Pores of Kohn (inter-alveolar communications): Absent or non-functional in infants; develop after 2 to 3 years of age.
- Canals of Lambert (bronchiole-alveolar communications): Absent in early childhood; mature between 6 and 8 years of age.
- Channels of Martin (inter-bronchiolar communications): Poorly developed in infancy.
In adult lungs, collateral channels allow inspired gas to bypass an occluded bronchiole, maintaining alveolar aeration from adjacent lung segments. In infants and children $< 5$ years old, the complete lack of collateral ventilation means that mucus plugging of a small airway results in immediate, complete segment or lobar resorption atelectasis.
Clinical Implications for Mechanical Ventilation
Translating these developmental anatomical and physiological imperatives into clinical practice requires a structured approach to airway management, positioning, and ventilator configuration.
graph TD
    A["Pediatric Mechanical Ventilation Protocol"] --> B["Positioning & Airway Control"]
    A --> C["Ventilator Parameter Configuration"]
    A --> D["Hemodynamic & Lung Protection"]

    B --> B1["Sub-Shoulder Roll (Sniffing Posture)"]
    B --> B2["Micro-Cuffed ETT with Monitored Pressure (< 20-22 cmH2O)"]
    B --> B3["Continuous Apneic Oxygenation"]

    C --> C1["Mandatory Baseline PEEP 5-7 cmH2O (Establish FRC)"]
    C --> C2["Tidal Volume 5-7 mL/kg (Strict Ideal Body Weight)"]
    C --> C3["Physiological Respiratory Rate Scaled to Age"]
    C --> C4["Short Inspiratory Time (0.3-0.8 s) to Prevent Incomplete Exhalation"]

    D --> D1["Limit Driving Pressure (ΔP < 15 cmH2O)"]
    D --> D2["Humidified Circuit (Avoid Micro-Airway Plugging)"]
Airway Instrumentation and Endotracheal Tube Selection
- Micro-Cuffed Endotracheal Tubes: Modern pediatric practice strongly favors micro-cuffed ETTs (with ultra-thin polyurethane cuffs situated low on the tube shaft) over uncuffed tubes across all age groups, including neonates. Cuffed tubes provide a reliable seal at low cuff pressures ($< 20\text{ cmH}_2\text{O}$), reduce circuit air leaks, enable accurate tidal volume and end-tidal $CO_2$ monitoring, lower the risk of re-intubation due to sizing errors, and protect against aspiration.
- Cuff Pressure Monitoring: Cuff pressure must be maintained strictly below capillary perfusion pressure ($< 20 - 22\text{ cmH}_2\text{O}$) to prevent ischemic pressure ulceration over the non-yielding cricoid ring.
| Patient Age Group | Uncuffed ETT Internal Diameter (mm) | Cuffed ETT Internal Diameter (mm) | Approximate Insertion Depth at Lip (cm) | Initial Respiratory Rate (breaths/min) |
|---|---|---|---|---|
| Preterm (< 1000 g) | $2.5$ | Generally not recommended | $6.0 - 6.5$ | $40 - 60$ |
| Neonate (Term, 3.5 kg) | $3.0 - 3.5$ | $3.0$ | $9.0 - 9.5$ | $30 - 45$ |
| Infant (6–12 months) | $3.5 - 4.0$ | $3.5$ | $10.0 - 11.5$ | $25 - 35$ |
| Child (2–4 years) | $\frac{\text{Age}}{4} + 4.0$ (4.5–5.0) | $\frac{\text{Age}}{4} + 3.5$ (4.0–4.5) | $\frac{\text{Age}}{2} + 12.0$ | $20 - 28$ |
| Child (6–8 years) | $\frac{\text{Age}}{4} + 4.0$ (5.5–6.0) | $\frac{\text{Age}}{4} + 3.5$ (5.0–5.5) | $\frac{\text{Age}}{2} + 12.0$ | $18 - 24$ |
| Adolescent / Adult | $7.0 - 8.0$ | $7.0 - 8.0$ | $21.0 - 23.0$ | $12 - 16$ |
Initial Mechanical Ventilator Settings and Titration Protocol
graph LR
    A["Pediatric Ventilator Initiation"] --> B["Mode: Pressure-Controlled (PC-CMV / PRVC)"]
    B --> C["Set PEEP: 5-7 cmH2O (Restore FRC above Closing Volume)"]
    C --> D["Set VT Target: 5-7 mL/kg (Scaled to Ideal Body Weight)"]
    D --> E["Set Inspiratory Time (Ti): 0.35-0.70 s (Scaled to Time Constant)"]
    E --> F["Set RR: Scaled to Age to Match Metabolic VCO2"]
| Parameter | Recommended Initial Value | Physiological Rationale & Safety Threshold |
|---|---|---|
| Ventilation Mode | PC-CMV or PRVC (Volume Target PC) | Decelerating flow profile mitigates high peak inspiratory pressure ($PIP$) across narrow pediatric airways. |
| PEEP Target | $\mathbf{5 - 7\text{ cmH}_2\text{O}}$ (up to $8-10\text{ in ARDS}$) | Restores static FRC above Closing Capacity ($CC$), splints open terminal airways, and counters chest wall collapse. |
| Tidal Volume ($V_T$) | $\mathbf{5 - 7\text{ mL/kg}}$ (Ideal Body Weight) | Avoids volutrauma and overdistension of small total lung capacity units ($TLC$). |
| Inspiratory Time ($T_I$) | Neonate: $0.30 - 0.40\text{ s}$ Infant: $0.40 - 0.55\text{ s}$ Child: $0.60 - 0.80\text{ s}$ | Scaled to short respiratory system time constant ($\tau = R_{aw} \times C_{rs}$). Avoids gas trapping and auto-PEEP. |
| Driving Pressure ($\Delta P$) | $\le 14 - 15\text{ cmH}_2\text{O}$ | $\Delta P = P_{plat} - \text{PEEP}$; keeping driving pressure low prevents barotrauma in compliant rib cage systems. |
| Humidification | Active heated humidification ($37^\circ\text{C}, 44\text{ mg/L}$) | Crucial in pediatric circuits to prevent inspissation of mucus in narrow ETT lumens ($< 4.0\text{ mm}$). |
Bedside Troubleshooting and High-Risk Pitfalls
In an infant, the distance from the vocal cords to the carina is merely 4 to 5 cm. Advancing the endotracheal tube just 1 to 2 cm too deeply results in immediate right mainstem intubation, rapid complete left lung atelectasis, severe right-sided tension pneumothorax, and cardiovascular collapse. Always auscultate axillary lung fields symmetrically, verify post-intubation chest radiography (ETT tip positioned at $T_2-T_3$, midway between thoracic inlet and carina), and secure the tube meticulously to the maxilla.
Although infants have short time constants ($\tau$) in parenchymal lung disease due to low compliance ($C_{rs}$), diseases characterized by severe peripheral airway narrowing (e.g., viral bronchiolitis, status asthmaticus) dramatically elevate airway resistance ($R_{aw}$). This lengthens the expiratory time constant ($\tau = R_{aw} \cdot C_{rs}$). If the set respiratory rate is too high or the expiratory time ($T_E$) is too short ($< 3-5\tau$), dynamic hyperinflation and intrinsic PEEP (Auto-PEEP) will develop, leading to thoracic overdistension, tension physiology, and severe reduction in systemic venous return.
Key Takeaways and Summary
- Airway Geometry: The pediatric airway is characterized by a prominent occiput, relative macroglossia, a cephalad larynx ($C_3-C_4$), a floppy omega-shaped epiglottis, and a non-distensible cricoid ring that acts as a functional bottleneck.
- Resistance Scaling: Airway resistance is inversely proportional to the fourth power of the radius ($R \propto 1/r^4$ for laminar flow; $1/r^5$ for turbulent flow). Just $1.0\text{ mm}$ of subglottic circumferential edema obliterates $75\%$ of an infant's airway cross-sectional area and causes a 16-fold (1600%) surge in airway resistance.
- Thoracic Wall Compliance and FRC: The infant chest wall is predominantly cartilaginous and highly compliant ($C_{cw} \gg C_L$), exerting minimal outward recoil. Consequently, the resting static FRC lies below the Closing Capacity ($CC \ge FRC$), causing small airways to collapse during normal tidal expiration unless preserved by intrinsic braking or extrinsic PEEP ($5-7\text{ cmH}_2\text{O}$).
- Diaphragmatic Fatigue Vulnerability: Neonatal diaphragmatic muscle contains only $10-25\%$ Type I slow-twitch fatigue-resistant fibers (compared to $50-55\%$ in adults). Sustained high workloads of breathing rapidly exhaust glycogen stores, causing sudden neuromuscular ventilatory failure.
- Metabolic Velocity: Basal oxygen consumption in infants ($\dot{V}O_2 \approx 6-8\text{ mL/kg/min}$) is more than double that of adults, resulting in rapid oxygen desaturation ($< 45\text{ seconds}$) during apnea.