Pediatric Acute Respiratory Distress Syndrome (PARDS) is a life-threatening form of acute, non-cardiogenic, inflammatory pulmonary edema resulting in severe hypoxemic respiratory failure, reduced lung compliance, and increased physiological dead space. Following the landmark 2015 Pediatric Acute Lung Injury Consensus Conference (PALICC-1), significant clinical evidence and technological advances necessitated the comprehensive Second Pediatric Acute Lung Injury Consensus Conference (PALICC-2) updated recommendations in 2023.
PALICC-2 establishes refined diagnostic thresholds, introduces classifications for non-invasive respiratory support and patients "at risk," stratifies severity utilizing the mean airway pressure ($mPaw$)-weighted Oxygenation Index ($\text{OI}$) and Oxygen Saturation Index ($\text{OSI}$), and mandates strict lung-protective ventilation and evidence-based adjunctive protocols.
flowchart TD
    A["Suspected Acute Respiratory Deterioration in Pediatric Patient"] --> B{"Meets Core PALICC-2 Entry Criteria?<br/>• Age: Gestational age > 42 wks to 18 yrs<br/>• Timing: ≤ 7 days from clinical insult<br/>• Imaging: New parenchymal infiltrate(s)<br/>• Non-cardiogenic: Not fully explained by LV failure/fluid"}

    B -- "No" --> C["Manage Alternative Etiology (Congenital Heart Disease, Fluid Overload, Neuromuscular)"]
    B -- "Yes" --> D{"Current Respiratory Support Modality"}

    D -- "NIV / CPAP ≥ 5 cmH2O or HFNC" --> E{"Oxygenation Impairment"}
    E -- "CPAP/BiPAP: P/F ≤ 300 or S/F ≤ 264" --> F["Non-Invasive PARDS"]
    E -- "HFNC (Age-based flow) & FiO2 ≥ 0.40" --> G["At-Risk for PARDS"]

    D -- "Invasive Mechanical Ventilation (PEEP ≥ 5 cmH2O)" --> H{"Calculate Oxygenation Metric<br/>(OI or OSI when SpO2 ≤ 97%)"}

    H -- "4.0 ≤ OI < 8.0  OR  5.0 ≤ OSI < 7.5" --> I["Mild Invasive PARDS"]
    H -- "8.0 ≤ OI < 16.0  OR  7.5 ≤ OSI < 12.3" --> J["Moderate Invasive PARDS"]
    H -- "OI ≥ 16.0  OR  OSI ≥ 12.3" --> K["Severe Invasive PARDS"]

    F --> L["Time-Limited NIV Trial (1-2 h)<br/>• Monitor work of breathing & p-ROXI<br/>• Rapid escalation if failing"]
    I --> M["Standard Lung-Protective Ventilation<br/>• Vt 5-8 mL/kg; Pplat ≤ 28; ΔP ≤ 15<br/>• Titrate PEEP: 8-10 cmH2O"]
    J --> N["Optimized Protective Strategy<br/>• Vt 4-6 mL/kg; PEEP 10-15 cmH2O<br/>• Target SpO2 88-92%; Early Cisatracurium"]
    K --> O["Refractory Escalation Ladder<br/>• Deep Sedation + NMBA (≤ 48 h)<br/>• Prone Positioning (≥ 16 h/day)<br/>• Inhaled NO Rescue (10-20 ppm)<br/>• Evaluate for VV-ECMO (OI ≥ 40 or refractory)"]
PALICC-2 Consensus Definition & Diagnostic Framework
The PALICC-2 definition standardizes pediatric lung injury diagnosis across heterogeneous international clinical settings, accounting for anatomical variations, variable arterial blood gas availability, and the rising utilization of non-invasive modalities.
A diagnosis of PARDS requires satisfying all four foundational domains:
- Age: Children beyond the perinatal period (gestational age $> 42\text{ weeks}$ or post-menstrual equivalent) up to 18 years.
- Timing: Acute onset within 7 days of a recognized clinical insult (e.g., viral pneumonia, sepsis, aspiration, major trauma, transfusion).
- Origin of Edema: Acute respiratory failure not fully explained by cardiogenic pulmonary edema, acute left ventricular dysfunction, or isolated systemic fluid overload.
- Chest Imaging: New parenchymal infiltrate(s) on chest radiography, computed tomography (CT), or lung ultrasound (LUS) demonstrating bilateral B-lines or consolidation consistent with acute parenchymal pulmonary disease.
Non-Invasive vs. Invasive PARDS Criteria
PALICC-2 established clear bifurcations between non-invasive support, invasively ventilated patients, and vulnerable children categorized as "At-Risk":
| Clinical Category | Respiratory Support Interface | Diagnostic Thresholds & Oxygenation Criteria |
|---|---|---|
| At-Risk for PARDS | High-Flow Nasal Cannula (HFNC) or Low-level Non-invasive Support | • Age-based minimum flow rates on HFNC ($\ge 2\text{ L/kg/min}$ in infants $< 1\text{ yr}$, $\ge 1.5\text{ L/kg/min}$ in $1-5\text{ yrs}$, $\ge 1.0\text{ L/kg/min}$ in $> 5\text{ yrs}$ or absolute flow $\ge 20-30\text{ L/min}$) • $FiO_2 \ge 0.40$ to maintain $SpO_2 92-97\%$ • Incomplete radiological criteria or emerging infiltrates |
| Non-Invasive PARDS | Non-Invasive Positive Pressure Ventilation (BiPAP) or CPAP $\ge 5\text{ cmH}_2\text{O}$ via full face mask/helmet | • Full radiological criteria met (new bilateral or unilateral infiltrates) • Arterial blood gas: $PaO_2/FiO_2 \le 300$ • Non-invasive surrogate: $SpO_2/FiO_2 \le 264$ (with $SpO_2 \le 97\%$) |
| Invasive PARDS | Endotracheal Tube or Tracheostomy with Invasive Mechanical Ventilation ($PEEP \ge 5\text{ cmH}_2\text{O}$) | • Full radiological criteria met • Severity stratified continuously using $\text{OI}$ or $\text{OSI}$ |
Oxygenation Metrics & Severity Stratification
In adult ARDS (Berlin definition), severity is stratified by the $PaO_2/FiO_2$ ratio without incorporating the distending airway pressure. In pediatric critical care, mean airway pressure ($mPaw$) varies markedly depending on endotracheal tube size, chest wall elastance, and clinician ventilator strategy. PALICC-2 mandates the Oxygenation Index ($\text{OI}$) as the primary stratification metric and the Oxygen Saturation Index ($\text{OSI}$) as the primary non-invasive surrogate.
Oxygenation Index ($\text{OI}$)
Continuous metric reflecting the mean airway pressure cost per unit of arterial oxygenation:
$$\text{OI} = \frac{mPaw \times FiO_2 \times 100}{PaO_2}$$Where:
- $mPaw$ = Mean Airway Pressure ($\text{cmH}_2\text{O}$)
- $FiO_2$ = Fraction of Inspired Oxygen ($0.21 - 1.00$)
- $PaO_2$ = Arterial Partial Pressure of Oxygen ($\text{mmHg}$)
Oxygen Saturation Index ($\text{OSI}$)
Continuous pulse-oximetry surrogate for patients without indwelling arterial access:
$$\text{OSI} = \frac{mPaw \times FiO_2 \times 100}{SpO_2}$$Validation Constraint: Valid only when $SpO_2 \le 97\%$. When $SpO_2 > 97\%$, the flat upper plateau of the oxyhemoglobin dissociation curve prevents accurate mathematical extrapolation of $PaO_2$.
flowchart LR
    subgraph Invasive_Severity["Invasive PARDS Severity Stratification"]
        direction TB
        MILD["Mild PARDS<br/>4.0 ≤ OI < 8.0<br/>5.0 ≤ OSI < 7.5"]
        MOD["Moderate PARDS<br/>8.0 ≤ OI < 16.0<br/>7.5 ≤ OSI < 12.3"]
        SEV["Severe PARDS<br/>OI ≥ 16.0<br/>OSI ≥ 12.3"]
        MILD --> MOD --> SEV
    end
PALICC-2 Invasive Severity Classification Matrix
| Severity Tier | Invasive Oxygenation Index ($\text{OI}$) | Pulse Oximetry Surrogate ($\text{OSI}$) | Ventilatory & Clinical Presentation |
|---|---|---|---|
| Mild PARDS | $4.0 \le \text{OI} < 8.0$ | $5.0 \le \text{OSI} < 7.5$ | Mild alveolar collapse, responsive to moderate PEEP ($6-8\text{ cmH}_2\text{O}$); driving pressures generally within safe limits. |
| Moderate PARDS | $8.0 \le \text{OI} < 16.0$ | $7.5 \le \text{OSI} < 12.3$ | Diffuse alveolar flooding, worsening ventilation-perfusion mismatch, moderate compliance loss; PEEP $10-14\text{ cmH}_2\text{O}$. |
| Severe PARDS | $\text{OI} \ge 16.0$ | $\text{OSI} \ge 12.3$ | Severe refractory hypoxemia, dense dependent consolidation, high risk of acute cor pulmonale and barotrauma; requires aggressive multimodal rescue. |
PALICC-2 Lung-Protective Mechanical Ventilation Strategy
The primary goal of invasive mechanical ventilation in PARDS is maintaining adequate gas exchange while preventing Ventilator-Induced Lung Injury (VILI)—specifically barotrauma, volutrauma, atelectrauma, and biotrauma.
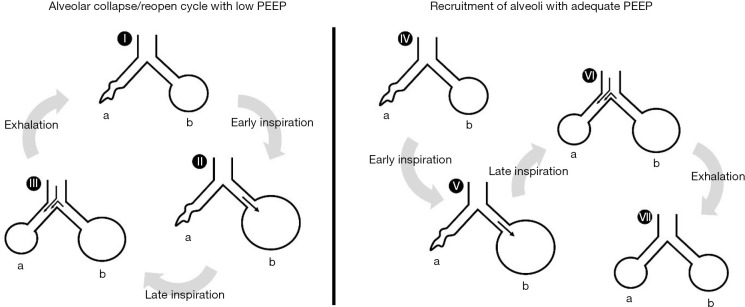 Figure 1: Pathophysiological mechanisms of cyclic alveolar collapse and shear stress (atelectrauma) with low PEEP versus alveolar stabilization and recruitment with adequate PEEP in heterogeneous lung injury and Pediatric Acute Respiratory Distress Syndrome (PARDS). Sourced from Allen et al., Translational Pediatrics 2026; DOI:
10.21037/tp-2025-aw-684
.
Tidal Volume ($V_t$) Titration & Baby Lung Concept
In PARDS, the functional aerated lung volume (the "baby lung") is drastically reduced due to inflammatory consolidation and atelectasis. Standardizing tidal volumes to ideal body weight rather than actual weight is imperative to prevent regional overdistension.
- Standard Starting Target: $5 - 8\text{ mL/kg}$ predicted body weight (PBW).
- Poorly Compliant / Severe Lungs: Reduce to $3 - 6\text{ mL/kg}$ PBW when respiratory system compliance ($C_{rs}$) is severely diminished or plateau pressures exceed safe thresholds.
Driving Pressure ($\Delta P$) and Plateau Pressure ($P_{plat}$) Limits
- Plateau Pressure Ceiling ($P_{plat}$): Maintain $P_{plat} \le 28\text{ cmH}_2\text{O}$ in patients with normal chest wall compliance.
- Increased Chest Wall Elastance: In conditions with severe chest wall rigidity, high intra-abdominal pressure, ascites, or severe anasarca, a higher ceiling of $P_{plat} \le 32\text{ cmH}_2\text{O}$ is permissible provided transpulmonary driving pressure remains controlled.
- Driving Pressure Target ($\Delta P$): $$\Delta P = P_{plat} - \text{PEEP} = \frac{V_t}{C_{rs}}$$ Target $\Delta P \le 14 - 15\text{ cmH}_2\text{O}$. Elevated driving pressure is the single strongest mechanical predictor of mortality in PARDS.
PEEP Titration and Open Lung Physiology
Positive End-Expiratory Pressure must be set to prevent end-expiratory alveolar collapse, recruit unstable alveolar units, restore Functional Residual Capacity (FRC), and reduce regional shear stress without inducing capillary compression or RV afterload elevation.
PALICC-2 recommends titrating PEEP according to validated pediatric PEEP/FiO2 titration grids while actively assessing bedside compliance and hemodynamics:
| Target $FiO_2$ | Mild PARDS PEEP ($\text{cmH}_2\text{O}$) | Moderate / Severe PARDS PEEP ($\text{cmH}_2\text{O}$) |
|---|---|---|
| 0.30 | $5$ | $8$ |
| 0.40 | $5 - 8$ | $8 - 10$ |
| 0.50 | $8 - 10$ | $10 - 12$ |
| 0.60 | $10$ | $12 - 14$ |
| 0.70 | $10 - 12$ | $14$ |
| 0.80 | $12 - 14$ | $14 - 16$ |
| 0.90 | $14$ | $16 - 18$ |
| 1.00 | $14 - 15$ | $18 - 22$ |
Gas Exchange & Permissive Hypercapnia Targets
- Oxygenation Targets:
- On Low PEEP ($< 10\text{ cmH}_2\text{O}$): Target $SpO_2 92 - 97\%$.
- On High PEEP ($\ge 10\text{ cmH}_2\text{O}$): Accept permissive hypoxemia targeting $SpO_2 88 - 92\%$ to avoid lethal oxygen toxicity and excessive airway pressures.
- Permissive Hypercapnia:
- Accept arterial $pH 7.20 - 7.25$ (and down to $7.15$ in refractory severe cases) to facilitate ultra-lung-protective low $V_t$ ventilation.
- Contraindications: Acute intracranial hypertension, severe traumatic brain injury, acute severe pulmonary hypertension, severe metabolic acidosis, or uncompensated hemodynamic instability.
Stepwise Ventilatory Titration & Escalation Ladder
flowchart TD
    subgraph Ladder["PALICC-2 Stepwise Management Ladder"]
        STEP1["<b>Step 1: Baseline Lung Protection</b><br/>• Mode: PC-CMV or PRVC<br/>• Vt: 5-8 mL/kg PBW (titrate to 3-6 if Crs low)<br/>• Target Pplat ≤ 28 cmH2O, ΔP ≤ 15 cmH2O<br/>• PEEP titration via PEEP/FiO2 scale"]

        STEP2["<b>Step 2: Moderate PARDS Optimization (OI 8-16)</b><br/>• Increase PEEP (10-15 cmH2O)<br/>• Permissive hypercapnia (pH ≥ 7.20)<br/>• Target SpO2 88-92%<br/>• Early targeted Neuromuscular Blockade (Cisatracurium)"]

        STEP3["<b>Step 3: Severe PARDS Rescue (OI ≥ 16)</b><br/>• Prone Positioning (≥ 16 h/day)<br/>• Deep sedation + continuous NMBA (≤ 48 h)<br/>• Inhaled Nitric Oxide (iNO 10-20 ppm) for acute RV dysfunction/refractory hypoxemia<br/>• Recruitment maneuvers (slow incremental PEEP staircase)"]

        STEP4["<b>Step 4: Refractory PARDS & Extracorporeal Support</b><br/>• High-Frequency Oscillatory Ventilation (HFOV rescue)<br/>• Veno-Venous (VV) ECMO Evaluation (OI ≥ 40 or refractory hypercapnia with pH < 7.15)"]

        STEP1 --> STEP2 --> STEP3 --> STEP4
    end
Evidence-Based Adjuvant Therapies
flowchart LR
    A["Severe PARDS (OI ≥ 16)"] --> B["Prone Positioning<br/>≥ 16 h/day"]
    A --> C["Early NMBA<br/>Continuous ≤ 48 h"]
    A --> D["Inhaled NO<br/>Rescue: 10-20 ppm"]
    A --> E["Surfactant Therapy<br/>NOT Routinely Recommended"]
    A --> F["Extracorporeal Life Support<br/>VV vs VA ECMO"]
1. Prone Positioning
- Mechanism: Re-distributes transpulmonary pressure gradients, promotes dorsal alveolar recruitment, improves ventilation-perfusion matching, and reduces dorsal alveolar strain.
- PALICC-2 Recommendation: Strongly recommended for severe PARDS ($\text{OI} \ge 16$ or $\text{OSI} \ge 12.3$).
- Dosage / Duration: Minimum of $16 - 24\text{ hours/day}$ in continuous sessions until significant sustained oxygenation improvement occurs.
Ensure endotracheal tube depth is verified and secured prior to proning. Utilize alternating head and limb positioning every 2 hours ("swimmer's position") with pressure-relieving hydrocolloid dressings over facial and pelvic bony prominences to prevent pressure ulceration and nerve neuropraxia.
2. Neuromuscular Blockade (NMBA)
- Mechanism: Eliminates patient-ventilator asynchrony, reduces oxygen consumption, prevents reverse triggering and pendelluft phenomenon, and controls transpulmonary pressure spikes.
- PALICC-2 Recommendation: Early targeted continuous infusion of non-depolarizing NMBA (e.g., cisatracurium) is recommended for moderate-to-severe PARDS for a duration of $\le 48\text{ hours}$. Routine prolonged paralysis beyond 48 hours is discouraged due to ICU-acquired weakness and myopathy.
3. Inhaled Pulmonary Vasodilators (iNO & Prostacyclin)
- Mechanism: Inhaled nitric oxide (iNO, $5 - 20\text{ ppm}$) selectively dilates pulmonary vasculature in well-ventilated lung units, decreasing intrapulmonary shunt, reducing pulmonary vascular resistance (PVR), and unloading the right ventricle.
- PALICC-2 Recommendation: Not recommended routinely for all PARDS patients. Recommended as a rescue therapy in severe PARDS with documented acute pulmonary hypertension, severe acute cor pulmonale / RV failure, or refractory hypoxemia failing other strategies. Discontinue if no objective improvement occurs within 4–6 hours.
4. Exogenous Surfactant Therapy
- PALICC-2 Recommendation: Exogenous surfactant is not routinely recommended in pediatric patients with secondary PARDS (direct or indirect lung injury) due to a lack of demonstrable mortality benefit in large multicenter trials. May be considered selectively in specific primary surfactant deficiency phenotypes (e.g., severe neonatal transition or select tracheobronchial aspiration).
5. Extracorporeal Life Support (ECLS / ECMO)
Cannulation Modalities
- Veno-Venous (VV) ECMO: The modality of choice for isolated severe hypoxemic and/or hypercapnic respiratory failure with preserved cardiac function (single dual-lumen bicaval Avalon cannula or separate internal jugular and femoral vein cannulae).
- Veno-Arterial (VA) ECMO: Indicated when severe PARDS is complicated by myocardial failure, septic cardiomyopathy, or severe acute cor pulmonale with refractory shock.
PALICC-2 Extracorporeal Indications
- Severe Hypoxemia: $\text{OI} \ge 40$ sustained for $> 4\text{ hours}$ despite optimal protective ventilation, proning, and adjuvant therapy.
- Refractory Hypercapnia: Severe uncompensated respiratory acidosis ($pH < 7.15$) with plateau pressures exceeding safe limits.
- ECMO "Rest" Ventilation: Once on ECMO, immediately de-escalate ventilator parameters to rest settings ($V_t 2-4\text{ mL/kg}$, PEEP $10-12\text{ cmH}_2\text{O}$, Peak Inspiratory Pressure $< 20-25\text{ cmH}_2\text{O}$, Rate $10-15\text{ breaths/min}$, $FiO_2 \le 0.40$) to allow biological lung recovery and halt mechanical power dissipation.
Summary Protocol for Bedside PARDS Management
| Clinical Stage | Diagnostic Metric Threshold | Primary Ventilatory Strategy | Key Adjunctive Considerations |
|---|---|---|---|
| Non-Invasive / At-Risk | $P/F \le 300$, $S/F \le 264$ on CPAP $\ge 5$ | CPAP or BiPAP with tight interface seal | Close monitoring of respiratory effort and p-ROXI; limit NIV trial to 1–2 hours if no improvement. |
| Mild PARDS | $4 \le \text{OI} < 8$ ($5 \le \text{OSI} < 7.5$) | $V_t 5-8\text{ mL/kg}$, PEEP $6-10\text{ cmH}_2\text{O}$, $P_{plat} \le 28$ | Light-to-moderate analgo-sedation; preserve spontaneous breathing if synchronized. |
| Moderate PARDS | $8 \le \text{OI} < 16$ ($7.5 \le \text{OSI} < 12.3$) | $V_t 4-6\text{ mL/kg}$, PEEP $10-14\text{ cmH}_2\text{O}$, $\Delta P \le 14$ | Early targeted NMBA ($\le 48\text{ h}$); fluid-conservative strategy; target $SpO_2 88-92\%$. |
| Severe PARDS | $\text{OI} \ge 16$ ($OSI \ge 12.3$) | Ultra-protective $V_t 3-6\text{ mL/kg}$, PEEP $14-18\text{ cmH}_2\text{O}$ | Prone positioning $\ge 16\text{ h/day}$; iNO rescue for RV dysfunction; assess ECMO eligibility. |
| Refractory PARDS | $\text{OI} \ge 40$ or $pH < 7.15$ | Transition to VV-ECMO rest ventilation | Lung rest settings; minimize mechanical power; anticoagulation and organ protection. |
Key Takeaways
- Continuous Metric Stratification: In invasively ventilated pediatric patients, always calculate the mean airway pressure-weighted Oxygenation Index ($\text{OI}$) or the pulse oximetry surrogate Oxygen Saturation Index ($\text{OSI}$) (when $SpO_2 \le 97\%$) rather than isolated $P/F$ ratios.
- Driving Pressure Is Paramount: Titrate tidal volumes ($3-6\text{ mL/kg}$ PBW in severe PARDS) and PEEP to minimize driving pressure ($\Delta P \le 14-15\text{ cmH}_2\text{O}$) and maintain plateau pressure $P_{plat} \le 28\text{ cmH}_2\text{O}$.
- Early Multimodal Rescue: In severe PARDS ($\text{OI} \ge 16$), initiate prone positioning ($\ge 16\text{ h/day}$) and early targeted neuromuscular blockade without delay.
- Timely Extracorporeal Escalation: Initiate early consultation for VV-ECMO when $\text{OI} \ge 40$ or uncompensated hypercapnia persists, shifting the patient promptly to lung-rest ventilation.