Pediatric High-Frequency Oscillatory Ventilation (HFOV) is an advanced mode of invasive mechanical ventilation that delivers ultra-low, sub-deadspace tidal volumes ($V_{T,hf} \approx 1-2\text{ mL/kg} < V_D$) at supra-physiological frequencies ($f = 3-15\text{ Hz}$, equivalent to $180-900\text{ breaths/min}$). By establishing a continuous, elevated mean airway pressure ($mPaw$ or $\bar{P}_{aw}$) upon which active bidirectional pressure oscillations are superimposed, HFOV operationalizes the "open-lung" concept. It maintains alveolar recruitment and maximizes functional residual capacity (FRC) while virtually eliminating the large cyclical pressure swings and dynamic alveolar strain responsible for classic ventilator-induced lung injury (VILI), including volutrauma, atelectrauma, and biotrauma.
flowchart TD
    subgraph INSP_EXP["Active Bidirectional Oscillatory Cycle"]
        Piston["Electromagnetic Piston / Diaphragm Oscillator"]
        BiasFlow["Continuous Bias Flow (15–30 L/min) + Heated Humidifier"]
        Piston -- "Forward Stroke (Active Positive Pressure Wave)" --> InspAirway["Airway Inflow (Axial High-Velocity Core)"]
        Piston -- "Backward Stroke (Active Negative Suction Wave)" --> ExpAirway["Airway Outflow (Peripheral Annular Boundary Layer)"]
    end

    subgraph GAS_TRANSPORT["Non-Conventional Gas Transport Mechanisms"]
        InspAirway --> Convection["1. Bulk Convection (Direct Proximal Alveolar Ventilation)"]
        InspAirway --> Taylor["2. Taylor Dispersion (Enhanced Axial Mixing via Parabolic Velocity Gradients)"]
        InspAirway --> Streaming["3. Asymmetric Velocity Profiles (Axial Inflow / Boundary Layer Outflow)"]
        InspAirway --> Pendelluft["4. Pendelluft Effect (Inter-regional Gas Redistribution across Heterogeneous Tau)"]
        InspAirway --> Cardiogenic["5. Cardiogenic Mixing (Pulsatile Cardiac Parenchymal Perturbations)"]
        InspAirway --> Diffusion["6. Molecular Diffusion (Distal Alveolar-Capillary Gas Exchange)"]
    end

    subgraph CLINICAL_TARGETS["Dual Physiological Separation"]
        Convection & Taylor & Streaming & Pendelluft & Cardiogenic & Diffusion --> Ventilation["Ventilation (CO2 Clearance)<br/>DCO2 = f × VT²<br/>Regulated by: Amplitude (ΔP) & Frequency (Hz)"]
        BiasFlow --> Oxygenation["Oxygenation (PaO2 / SaO2)<br/>Continuous FRC Recruitment<br/>Regulated by: mPaw & FiO2"]
    end
Physical Principles and Non-Conventional Gas Transport Mechanisms
In conventional mechanical ventilation (CMV), alveolar ventilation relies almost exclusively on bulk convective flow, requiring tidal volumes exceeding anatomical dead space ($V_T > V_D \approx 2-3\text{ mL/kg}$). When $V_T < V_D$, conventional gas exchange ceases. In HFOV, bulk convection is augmented and surpassed by six distinct physical transport mechanisms that operate simultaneously across different generations of the tracheobronchial tree.
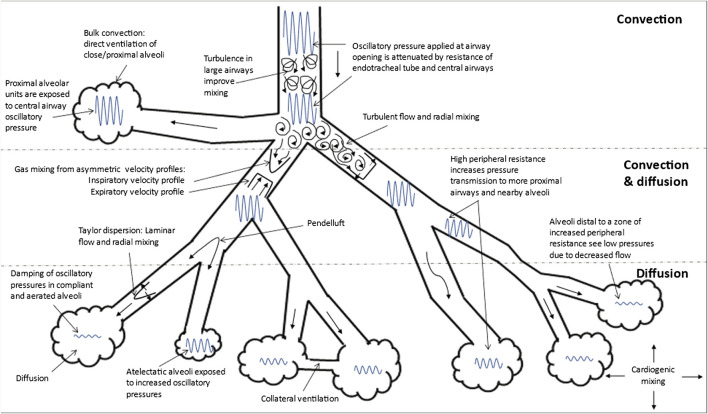 Figure 1: Physiological framework of gas transport mechanisms during High-Frequency Oscillatory Ventilation across the tracheobronchial tree. Gas exchange transitions from convective dominance in proximal conducting airways to combined convective-diffusive Taylor dispersion in intermediate branches, and pure molecular diffusion at the alveolar-capillary junction. Asymmetric velocity profiles, Pendelluft mixing across units with heterogeneous time constants, collateral ventilation, and cardiogenic oscillations collectively facilitate massive carbon dioxide elimination despite sub-deadspace tidal volumes. Source: Miller AG, Tan HL, Smith BJ, Rotta AT, Lee JH. Front Physiol. 2022;13:813478. DOI: 10.3389/fphys.2022.813478.
1. Bulk Convection (Direct Alveolar Ventilation)
Although the delivered tidal volume during HFOV ($V_{T,hf} \approx 1-2\text{ mL/kg}$) is smaller than the total anatomical dead space, branching tracheobronchial geometry dictates that proximal alveolar units subtended by short, central conducting airways (generations 5–10) are located within a convective volume less than $V_{T,hf}$. Consequently, these proximal alveolar acini undergo direct bulk alveolar ventilation identical to conventional tidal breathing.
2. Taylor Dispersion (Taylor-Aris Longitudinal Dispersion)
In laminar and transitional oscillatory flow regimes, fluid velocity is non-uniform across the airway cross-section, forming a parabolic profile with maximum velocity at the center and zero velocity at the airway wall. The high axial velocity gradient stretches the concentration front along the longitudinal axis of the airway, while radial molecular diffusion continuously transfers gas molecules between high-velocity central streamlines and stagnant boundary layers. This interaction between convective velocity shear and radial diffusion exponentially enhances the effective longitudinal diffusion coefficient ($D_{eff}$), facilitating rapid axial transport far exceeding simple molecular diffusion:
$$D_{eff} = D_{mol} + \frac{r^2 \bar{u}^2}{48 D_{mol}}$$Where:
- $D_{eff}$ = Effective longitudinal diffusion coefficient ($\text{cm}^2/\text{s}$)
- $D_{mol}$ = Molecular diffusion coefficient of gas ($\text{cm}^2/\text{s}$)
- $r$ = Airway radius ($\text{cm}$)
- $\bar{u}$ = Mean cross-sectional gas velocity ($\text{cm}/\text{s}$)
3. Asymmetric Velocity Profiles (Nonlinear Axial Streaming)
Due to convective acceleration and boundary layer dynamics at airway bifurcations, the velocity profile during high-frequency inspiration is sharp, narrow, and bullet-shaped, concentrating fresh gas along the central core of the bronchial lumen. In contrast, the active expiratory stroke produces a blunt, flattened parabolic velocity profile where gas flows outward predominantly along the peripheral boundary layer adjacent to the airway mucosa. This spatial asymmetry creates a continuous bidirectional counter-current loop (axial convective streaming): fresh inspired gas advances down the airway core while carbon-dioxide-rich alveolar gas retreats along the airway periphery, minimizing coaxial dead space rebreathing.
4. Pendelluft Effect (Inter-Regional Collateral Gas Redistribution)
In heterogeneous lung pathology (such as PARDS or aspiration syndromes), adjacent alveolar units possess widely discordant regional compliances ($C_{rs,i}$) and airway resistances ($R_{aw,i}$), producing markedly disparate regional time constants ($\tau_i = R_{aw,i} \times C_{rs,i}$). During rapid oscillatory cycling:
- Units with short time constants (stiff, non-compliant or low-resistance zones) fill and empty rapidly out of phase with the ventilator waveform.
- Units with long time constants (high-resistance or highly compliant zones) fill and empty slowly.
When the global oscillatory cycle transitions between inspiration and expiration, gas shifts laterally from fast-filling, early-equilibrating alveolar units into slower, lagging adjacent units before exiting the lung (the Pendelluft phenomenon). This asynchronous inter-alveolar gas redistribution homogenizes alveolar ventilation and facilitates recruitment of slow alveolar compartments without requiring high peak driving pressures.
5. Molecular Diffusion
At the terminal respiratory bronchioles, alveolar ducts, and alveolar-capillary membranes (generations 17–23), the cumulative total cross-sectional area of the respiratory zone increases exponentially ($> 100\text{ m}^2$). Convective bulk flow velocity approaches zero. Gas transport across this microscopic zone depends entirely on molecular diffusion driven by partial pressure gradients ($\Delta P_{O_2}$ and $\Delta P_{CO_2}$) governed by Fick's Law of Diffusion.
6. Cardiogenic Mixing and Collateral Ventilation
The mechanical systole and diastole of the heart transmit physical pressure pulsations (pulsatile parenchymal shearing) directly into the adjacent lung lobes (particularly the left lower lobe, lingula, and right middle lobe). These pulsations generate localized parenchymal micro-distortions and vortices that accelerate peripheral gas mixing. Collateral pathways (pores of Kohn, canals of Lambert, and channels of Martin) provide low-resistance inter-alveolar channels that bypass obstructed peripheral bronchioles.
High-Frequency Gas Transport & Carbon Dioxide Elimination ($DCO_2$)
In conventional ventilation, minute ventilation ($\dot{V}_E$) is a linear product of frequency and tidal volume:
$$\dot{V}_{E,\text{conv}} = f \times V_T \implies \dot{V}CO_2 \propto f \times V_T$$In High-Frequency Oscillatory Ventilation, physical dispersion mechanisms dictate that gas transport and carbon dioxide clearance are characterized by the High-Frequency Carbon Dioxide Transport Coefficient ($DCO_2$):
Where:
- $DCO_2$ = Gas transport coefficient of carbon dioxide ($\text{mL}^2/\text{s}$ or $\text{cm}^6/\text{s}$)
- $f$ = Oscillatory frequency in Hertz ($\text{Hz}$, where $1\text{ Hz} = 60\text{ cycles/min}$)
- $V_{T,hf}$ = Delivered high-frequency tidal volume ($\text{mL}$)
- $V_{T,hf} \propto \frac{\Delta P}{f \times R_{aw}}$
This quadratic dependence on tidal volume ($V_{T,hf}^2$) introduces a fundamental clinical principle in high-frequency ventilation: delivered tidal volume exerts a far greater impact on carbon dioxide removal than frequency.
flowchart TD
    subgraph FREQ_PARADOX["The High-Frequency Ventilation Paradox"]
        A["Clinician Desires to Decrease PaCO2 (Increase Ventilation)"] --> B{"Choose Primary Ventilator Adjustment"}

        B -- "Option 1: Increase Amplitude (ΔP / Power)" --> C["Increases Piston Displacement"]
        C --> D["Direct Increase in Delivered VT,hf"]
        D --> E["Exponential Increase in DCO2 (VT,hf²)"]
        E --> F["Rapid Decrease in PaCO2"]

        B -- "Option 2: DECREASE Frequency (f in Hz)" --> G["Lengthens Oscillatory Cycle Period (T = 1/f)"]
        G --> H["Piston Travels Farther per Stroke (Longer Inspiratory Time)"]
        H --> I["Substantial Increase in Delivered VT,hf"]
        I --> J["Net DCO2 Increases (f × VT,hf² Rises despite lower f)"]
        J --> F

        B -- "Option 3: INCREASE Frequency (f in Hz)" --> K["Shortens Cycle Period (T = 1/f)"]
        K --> L["Piston Reversed Before Volume Transmitted (Attenuated VT,hf)"]
        L --> M["Net DCO2 Falls (Loss of VT,hf² outweighs higher f)"]
        M --> N["UNINTENDED RISE in PaCO2 (Hypercapnic Deterioration)"]
    end
In conventional mechanical ventilation, increasing respiratory rate decreases $PaCO_2$. In HFOV, increasing frequency ($f$) REDUCES delivered tidal volume ($V_T$) due to circuit impedance and gas inertia, resulting in a NET REDUCTION in $DCO_2$ and an INCREASE in $PaCO_2$.
- To lower $PaCO_2$ (blow off $CO_2$): Increase Amplitude ($\Delta P$) or DECREASE Frequency ($f$).
- To raise $PaCO_2$ (treat hypocapnia): Decrease Amplitude ($\Delta P$) or INCREASE Frequency ($f$).
Core Parameter Titration & Mathematical Adjustments
HFOV provides independent control over oxygenation and ventilation through separate physical operational controls.
flowchart LR
    subgraph OXYGENATION["Oxygenation Controls"]
        direction TB
        mPaw["Mean Airway Pressure (mPaw / P̄aw)<br/>• Sets Constant Alveolar Distension (FRC)<br/>• Recruits & Stabilizes Atelectatic Alveoli"]
        FiO2["Inspired Oxygen Fraction (FiO2)<br/>• Controls Alveolar Oxygen Partial Pressure"]
        mPaw & FiO2 --> LungVol["Optimizes Lung Volume<br/>(Target: 8–9 Posterior Ribs on CXR)"]
    end

    subgraph VENTILATION["Ventilation (CO2 Clearance) Controls"]
        direction TB
        Amp["Amplitude (ΔP / Power / Stroke Volume)<br/>• Regulates Peak-to-Peak Pressure Swing<br/>• Primary Determinant of VT,hf"]
        Freq["Frequency (f in Hz)<br/>• Sets Number of Cycles per Second<br/>• Inverse Relationship with Delivered VT,hf"]
        Bias["Bias Flow (15–30 L/min)<br/>• Flushes Exhaled CO2 from Circuit<br/>• Facilitates mPaw Generation"]
        IE["Inspiratory Time (I:E Ratio)<br/>• Typically 33% (1:2) or 50% (1:1)"]
        Amp & Freq & Bias & IE --> DCO2_Out["Regulates DCO2 = f × VT²<br/>(Target: pH 7.25–7.40, PaCO2 45–60 mmHg)"]
    end
Parameter Initialization and Age-Stratified Reference Matrix
| Parameter | Neonates ($< 3\text{ kg}$) | Infants ($3-10\text{ kg}$) | Children ($10-30\text{ kg}$) | Adolescents ($> 30\text{ kg}$) | Clinical Titration Endpoints & Limits |
|---|---|---|---|---|---|
| Frequency ($f$) | $10-15\text{ Hz}$ | $8-10\text{ Hz}$ | $6-8\text{ Hz}$ | $4-6\text{ Hz}$ | Higher frequency in smaller patients prevents excessive $V_T$ delivery and peripheral overdistension. |
| Initial $mPaw$ | $\text{CMV } mPaw + 2-3\text{ cmH}_2\text{O}$ | $\text{CMV } mPaw + 3-5\text{ cmH}_2\text{O}$ | $\text{CMV } mPaw + 4-6\text{ cmH}_2\text{O}$ | $\text{CMV } mPaw + 5-8\text{ cmH}_2\text{O}$ | Range: $15-35\text{ cmH}_2\text{O}$. Titrate to open lung ($FiO_2 < 0.60$ with target lung volume). |
| Amplitude ($\Delta P$) | $20-30\text{ cmH}_2\text{O}$ | $30-45\text{ cmH}_2\text{O}$ | $40-60\text{ cmH}_2\text{O}$ | $55-80\text{ cmH}_2\text{O}$ | Adjust until visible chest wiggle extends to umbilicus (infants) or mid-thigh (older children). |
| Bias Flow | $10-15\text{ L/min}$ | $15-20\text{ L/min}$ | $20-25\text{ L/min}$ | $25-35\text{ L/min}$ | Must exceed peak oscillatory demand to prevent circuit rebreathing and maintain stable $mPaw$. |
| Inspiratory % ($I:E$) | $33\%\text{ (1:2)}$ | $33\%\text{ (1:2)}$ | $33\%\text{ (1:2)}$ | $33\%\text{ (1:2)}$ | Default $33\%$ promotes passive expiratory time; $50\%\text{ (1:1)}$ used selectively for severe hypercapnia. |
High-Volume Strategy: Stepwise Recruitment & Deflation Titration
The "open-lung strategy" in HFOV aims to recruit non-aerated, consolidated alveolar units using sustained $mPaw$ increments, followed by continuous maintenance at optimal FRC along the deflation limb of the static pressure-volume hysteresis loop.
flowchart TD
    A["Transition from CMV to HFOV"] --> B["Set Initial mPaw = Conventional mPaw + 3 to 5 cmH2O<br/>Set FiO2 = 1.0 (or pre-switch level)"]
    B --> C["Incremental Recruitment Phase:<br/>Increase mPaw by 1–2 cmH2O every 2–3 minutes<br/>Continuously monitor SpO2, Heart Rate, Arterial BP, and CVP"]

    C --> D{"SpO2 Improves and Reaches Target ≥ 92%?"}
    D -- "Yes" --> E["Alveolar Opening Pressure (P_open) Reached<br/>Begin Stepwise Weaning of FiO2"]
    D -- "No / Hemodynamic Drop" --> F["Check for Dynamic Overdistension / Tamponade<br/>Obtain Urgent CXR & Assess CVP / Pulse Pressure"]

    E --> G["Wean FiO2 in Steps of 0.05–0.10 until FiO2 ≤ 0.50–0.60"]
    G --> H["Decremental Deflation Phase (Find Closing Pressure P_close):<br/>Decrease mPaw by 1 cmH2O every 10–15 min"]

    H --> I{"SpO2 Drops by > 2–3% or Falls Below 88%?"}
    I -- "No" --> H
    I -- "Yes (P_close Identified)" --> J["Perform Re-recruitment Maneuver (Set mPaw back to P_open for 2 min)"]
    J --> K["Set Final Optimal Operating mPaw = P_close + 2 to 3 cmH2O<br/>(Maintains lung on stable deflation limb with minimal distending stress)"]
    K --> L["Obtain Baseline Post-Recruitment CXR:<br/>Confirm 8–9 Posterior Rib Expansion above Diaphragm Dome"]
The gold standard for assessing appropriate HFOV mean airway pressure is serial evaluation of right hemidiaphragm position on anteroposterior (AP) chest radiography:
- Optimal Inflation: Hemidiaphragm dome positioned at the level of the 8th to 9th posterior rib (or 6th anterior rib).
- Under-inflation / Atelectasis ($< 8\text{ posterior ribs}$): Inadequate FRC, persistent intrapulmonary shunt. Increase $mPaw$ in steps of $1-2\text{ cmH}_2\text{O}$.
- Overdistension ($> 9.5-10\text{ posterior ribs}$, flattened diaphragms, narrow cardiac silhouette): Severe risk of pulmonary barotrauma, capillary compression, right ventricular afterload escalation, and systemic venous return impairment. Reduce $mPaw$ immediately.
Clinical Indications, Contraindications, and Safety Profiles
Clinical Indications
According to the Second Pediatric Acute Lung Injury Consensus Conference (PALICC-2) guidelines, HFOV is indicated as an advanced rescue modality or specialized lung-protective strategy in specific clinical scenarios:
- Severe Refractory Hypoxemic PARDS:
- Failure of conventional lung-protective ventilation despite optimization ($V_T = 4-6\text{ mL/kg}$, high PEEP $\ge 12-15\text{ cmH}_2\text{O}$, neuromuscular blockade, and prone positioning).
- High Oxygenation Index: $\text{OI} \ge 16-20$ or Oxygen Saturation Index: $\text{OSI} \ge 12.3$.
- Excessive peak inspiratory pressures ($P_{plat} > 28-32\text{ cmH}_2\text{O}$) or driving pressures ($\Delta P > 15\text{ cmH}_2\text{O}$) on CMV.
- Gross Air Leak Syndromes:
- Massive pulmonary interstitial emphysema (PIE).
- Persistent bronchopleural fistulas (BPF) with large continuous pleural air loss.
- Refractory pneumothoraces or pneumomediastinum on CMV (HFOV minimizes cyclical peak airway pressures and pleural shear stress).
- Severe Neonatal / Infant Meconium Aspiration Syndrome (MAS) and Congenital Diaphragmatic Hernia (CDH):
- When delivered with inhaled nitric oxide (iNO), HFOV provides homogeneous alveolar recruitment, maximizing lung surface area for optimal iNO-mediated pulmonary vasodilation.
Absolute and Relative Contraindications
flowchart TD
    subgraph CONTRAINDICATIONS["Contraindications to HFOV"]
        A["Severe Obstructive Airway Disease (Status Asthmaticus / Severe Bronchiolitis)"] --- A1["Risk of dynamic gas trapping, profound auto-PEEP, parenchymal rupture"]
        B["Severe Intracranial Hypertension / Acute TBI"] --- B1["High intrathoracic pressure impairs cerebral venous drainage (reduces CPP)"]
        C["Severe Uncorrected Hemodynamic Instability / Hypovolemia"] --- C1["Impaired venous return (decreased preload) leads to immediate cardiovascular collapse"]
        D["Small-Bore Uncuffed Endotracheal Tubes with Excessive Peritubular Leak"] --- D1["Inability to maintain target mPaw and deliver effective oscillatory amplitude"]
    end
Cardiovascular-Pulmonary Interactions & Hemodynamic Monitoring
The high sustained intrathoracic pressure applied during HFOV directly influences biventricular cardiac performance.
flowchart LR
    mPawHigh["Elevated Mean Airway Pressure (mPaw)"] --> PleuralP["Increased Mean Pleural & Pericardial Pressure"]

    PleuralP --> PreloadDec["Reduces Superior & Inferior Vena Cava Pressure Gradients<br/>↓ Right Ventricular Preload (EDV)"]

    mPawHigh --> AlveolarP["Alveolar Compression (Zone 1 / 2 Physiology)"]
    AlveolarP --> PVRInc["↑ Pulmonary Vascular Resistance (PVR)<br/>↑ RV Afterload & RV Systolic Wall Stress"]

    PreloadDec & PVRInc --> RVDilate["Acute RV Strain & Dilation<br/>Septal Flattening / Leftward Shift (Reverse Bernheim)"]
    RVDilate --> LVComp["Impaired LV Diastolic Filling<br/>↓ Stroke Volume & Mean Arterial Pressure"]
- Preload Optimization: Ensure adequate intravascular volume before HFOV initiation (fluid challenge $10-20\text{ mL/kg}$ crystalloid if under-filled).
- Inotropic / Vasopressor Support: Have norepinephrine or epinephrine infusions prepared to counteract high-intrathoracic-pressure-induced venous return reduction.
- Echocardiographic Surveillance: Perform bedside focused cardiac ultrasound (POCUS) to monitor RV dimension, interventricular septal flattening, and inferior vena cava collapsibility during $mPaw$ titration.
Systematic Arterial Blood Gas Troubleshooting
| Blood Gas Derangement | Primary Physiological Cause | Systematic Ventilator Adjustments (Ranked by Priority) |
|---|---|---|
| Severe Hypoxemia ($PaO_2 < 60\text{ mmHg}$, $SpO_2 < 88\%$) | • Inadequate alveolar recruitment ($mPaw$ below opening pressure) • Atelectasis / derecruitment • Secretion plugging or circuit disconnect | 1. Increase $mPaw$ by $1-2\text{ cmH}_2\text{O}$ every $5-10\text{ min}$ (target lung volume 8–9 ribs). 2. Increase $FiO_2$ as temporary bridge. 3. Verify chest wiggle and suction endotracheal tube with closed inline suction. 4. Obtain urgent CXR to evaluate for pneumothorax or under-inflation. |
| Hyperoxia / Overdistension ($PaO_2 > 100\text{ mmHg}$, $FiO_2 < 0.40$) | • Excessive alveolar distension • Pulmonary capillary squash (high West zone 1) | 1. Wean $FiO_2$ to $\le 0.40-0.50$. 2. Decrease $mPaw$ in steps of $1\text{ cmH}_2\text{O}$ while maintaining $SpO_2 92-97\%$. |
| Respiratory Acidosis / Hypercapnia ($PaCO_2 > 65\text{ mmHg}$, $\text{pH} < 7.20$) | • Inadequate $V_{T,hf}$ delivery • Excessive frequency attenuating stroke volume • Partial ETT obstruction or circuit decoupling | 1. Increase Amplitude ($\Delta P$ / Power) in increments of $3-5\text{ cmH}_2\text{O}$ to increase chest wiggle. 2. DECREASE Frequency ($f$) by $1-2\text{ Hz}$ to widen the stroke cycle and increase $V_{T,hf}$. 3. Verify cuff seal and increase bias flow if $mPaw$ is unstable. 4. Switch $I:E$ ratio to $50\%\text{ (1:1)}$ if already at minimum frequency and maximum amplitude. |
| Respiratory Alkalosis / Hypocapnia ($PaCO_2 < 35\text{ mmHg}$, $\text{pH} > 7.50$) | • Excessive $V_{T,hf}$ causing alveolar hyperventilation • Risk of cerebral vasoconstriction and ischemic injury | 1. Decrease Amplitude ($\Delta P$) in increments of $3-5\text{ cmH}_2\text{O}$. 2. INCREASE Frequency ($f$) by $1-2\text{ Hz}$ to attenuate delivered $V_{T,hf}$. |
Bedside Emergency Algorithm: Loss of Chest Wiggle
Chest wiggle factor (CWF) is the continuous physical exam monitor of high-frequency power transmission from the ventilator piston through the artificial airway to the patient's chest wall.
flowchart TD
    LossWiggle["SUDDEN LOSS OR ASYMMETRY OF CHEST WIGGLE"] --> Disconnect{"Is Ventilator Oscillating & Circuit Connected?"}

    Disconnect -- "No" --> Reconnect["Immediate Manual Ventilation with Bag-Valve-Mask (PEEP Valve Attached) & Fix Circuit"]
    Disconnect -- "Yes" --> Auscultate["Immediate Bedside Assessment:<br/>Auscultate Bilateral Chest & Palpate Trachea"]

    Auscultate --> CheckPath{"Identify Clinical Phenomenon"}

    CheckPath -- "Complete Bilateral Loss of Wiggle + Rising PaCO2" --> ETT_Block["Acute Endotracheal Tube Obstruction (Mucus Plug / Kink)"]
    ETT_Block --> Suction["1. Pass closed suction catheter immediately<br/>2. Instill 1–2 mL sterile saline if tenacious secretions<br/>3. If catheter does not pass: EXTUBATE & RE-INTUBATE IMMEDIATELY"]

    CheckPath -- "Unilateral Loss of Wiggle + Ipsilateral Breath Sounds Absent" --> OneSided{"Check Tracheal Position & Percussion"}

    OneSided -- "Hyperresonant Hemithorax + Tracheal Deviation + Hemodynamic Collapse" --> TensionPTX["TENSION PNEUMOTHORAX"]
    TensionPTX --> Decompress["Immediate Needle Thoracocentesis (2nd Intercostal Space, Mid-Clavicular Line)<br/>Followed by Emergent Tube Thoracostomy (Chest Tube)"]

    OneSided -- "Wiggle Present on Right, Absent on Left" --> Mainstem["Right Mainstem ETT Migration"]
    Mainstem --> Reposition["Withdraw ETT by 0.5–1.0 cm until Bilateral Wiggle Restored"]
Structured Weaning Protocol & Liberation from HFOV
Liberation from HFOV is undertaken systematically once the underlying acute lung pathology has resolved and gas exchange has stabilized at safe airway pressures.
flowchart TD
    A["Patient Stable on HFOV<br/>(Normal ABG, Hemodynamically Stable)"] --> B["Step 1: Wean FiO2 First"]
    B --> C{"Is FiO2 ≤ 0.40–0.50?"}

    C -- "No" --> D["Continue gradual FiO2 decrements of 0.05 every 2–4 h while SpO2 ≥ 92%"]
    C -- "Yes" --> E["Step 2: Wean Mean Airway Pressure (mPaw)"]

    E --> F["Decrease mPaw by 1–2 cmH2O every 4–8 h<br/>Monitor SpO2 and lung volume on CXR"]
    F --> G{"Is mPaw ≤ 14–18 cmH2O (Peds) or ≤ 10–12 cmH2O (Neonate)?"}

    G -- "No" --> F
    G -- "Yes" --> H["Step 3: Wean Amplitude (ΔP)"]
    H --> I["Decrease Amplitude by 2–4 cmH2O as PaCO2 allows<br/>(Target: PaCO2 40–50 mmHg with mild chest wiggle)"]

    I --> J{"Ready for Transition to Conventional Ventilation (CMV)?"}
    J -- "Criteria Met:<br/>• FiO2 ≤ 0.40<br/>• mPaw ≤ 16–18 cmH2O<br/>• ΔP low<br/>• Spontaneous respiratory efforts present" --> K["Transition to Pressure-Controlled CMV or CPAP/PSV<br/>• Set CMV PEEP = HFOV mPaw minus 3–4 cmH2O (typically 8–10 cmH2O)<br/>• Set CMV Ppeak to achieve Vt 5–7 mL/kg<br/>• Perform recruitment maneuver if derecruitment occurs during switch"]
Critical Clinical Pearls & High-Yield Pitfalls
Disconnecting an HFOV circuit for suctioning causes catastrophic derecruitment of functional residual capacity, collapsing unstable alveoli that required hours of stepwise $mPaw$ titration to open. Always use an airtight inline closed-suction catheter system. If an accidental disconnection occurs, a recruitment maneuver ($mPaw$ increased by $3-5\text{ cmH}_2\text{O}$ for $1-2\text{ minutes}$) should be performed immediately upon reconnection.
Although patient-ventilator asynchrony (active coughing, bucking against oscillations) increases peak airway pressure and compromises gas exchange, prolonged continuous neuromuscular blockade is associated with critical illness myopathy and atelectasis. Titrate deep analgosedation (e.g., fentanyl/midazolam or dexmedetomidine) and reserve continuous neuromuscular blockade strictly for the initial $24-48\text{ hours}$ of acute recruitment or severe refractory hypoxemia.
Because HFOV delivers massive flow velocities ($15-30\text{ L/min}$ bias flow) directly into an artificial airway, inadequate active humidification will rapidly desiccate bronchial secretions, leading to lethal endotracheal tube crusting and total airway occlusion within hours. Maintain continuous servo-controlled heated humidification delivering $37^\circ\text{C}$ at $100\%$ relative humidity ($44\text{ mg } H_2O/\text{L}$).