Pediatric critical care clinicians frequently encounter severe, acute pulmonary failure arising not from primary infectious pneumonia, but from mechanical disruption, thermal and chemical epithelial destruction, or hematological microvascular occlusion. Pediatric thoracic trauma, smoke and burn inhalation injuries, and Sickle Cell Acute Chest Syndrome (ACS) represent three distinct etiologies that share rapid clinical kinetics, severe ventilation-perfusion ($V_A/Q$) mismatch, compliance collapse, and extreme susceptibility to secondary ventilator-induced lung injury (VILI). Managing these conditions requires an in-depth understanding of pediatric anatomical compliance, the toxicokinetics of volatile combustive byproducts, and the rheological dynamics of sickled erythrocytes under hypoxic stress.
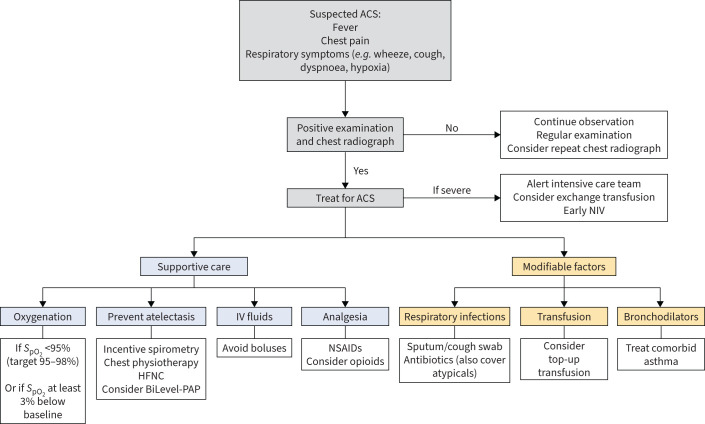 Figure 1: Evidence-based clinical decision algorithm for Acute Chest Syndrome (ACS) in pediatric sickle cell disease, outlining sequential escalation from noninvasive continuous and bi-level positive airway pressure (CPAP/BiPAP) to invasive mechanical ventilation, transfusion thresholds (simple versus automated red cell exchange), and rescue therapeutics. Reproduced under CC BY-NC 4.0 from Ahmed B, Arigliani M, Gupta A. Eur Respir Rev 2024; 33(173): 240005. DOI:
10.1183/16000617.0005-2024
.
Thoracic Trauma in Children
Biomechanical Mechanics of the Pediatric Chest Wall
The pediatric thoracic cage possesses marked anatomical and mechanical differences compared to the adult thorax. In infants and young children:
- Cartilaginous Mineralization: The ribs are composed primarily of pliable cartilage with incomplete ossification.
- Chest Wall Compliance ($C_{cw}$): Pediatric chest wall compliance is exceedingly high ($C_{cw} \gg C_L$), offering minimal structural resistance to external blunt impact.
- Kinetic Energy Transmission: Blunt kinetic impact (e.g., motor vehicle collisions, pedestrian-auto trauma, falls) compresses the thoracic cage without fracturing the ribs. The force is transmitted directly to the underlying pulmonary parenchyma, mediastinum, and cardiac structures.
Because the structural spring constant $K_{\text{rib}}$ of pediatric ribs is low, large inward deflections occur without bone failure, precipitating extensive parenchymal contusion, laceration, and alveolar hemorrhage in the complete absence of external skeletal fractures.
The absence of rib fractures on initial pediatric chest radiography never excludes lethal intrathoracic injury. In children, up to $70\%$ of severe pulmonary contusions and tracheobronchial disruptions occur with a completely intact bony thorax.
graph TD
    A["Blunt Kinetic Impact to Anterior Thorax"] --> B["High Compliance Pediatric Rib Cage Deflects Inward"]
    B --> C{"Bony Fracture?"}
    C -- "No Rib Fractures (70%)" --> D["Direct Energy Shockwave to Lung Parenchyma"]
    C -- "Rib Fractures Present" --> D
    D --> E["Alveolar-Capillary Shear Stress & Rupture"]
    E --> F["Alveolar Hemorrhage & Interstitial Edema"]
    E --> G["Surfactant Inactivation & Regional Micro-Atelectasis"]
    F & G --> H["Surge in Regional Elastance (E_L) & Shunt Fraction (Qs/Qt)"]
    H --> I["Severe Hypoxemic Respiratory Failure"]
Pulmonary Contusion: Pathophysiology and Ventilatory Titration
Pulmonary contusion represents direct mechanical trauma to the alveolar-capillary membrane, initiating a three-phase pathophysiological response:
- Primary Mechanical Disruption (0–2 hours): Disruption of microvascular endothelial junctions and alveolar epithelial integrity leads to intra-alveolar hemorrhage, hemoptysis, and interstitial extravasation of blood and plasma.
- Inflammatory Surge & Progressive Edema (6–24 hours): Infiltration of polymorphonuclear neutrophils, release of pro-inflammatory cytokines (IL-1$\beta$, TNF-$\alpha$, IL-6, IL-8), and reactive oxygen species generation induce secondary inflammation that extends beyond the initial impact zone into uninjured adjacent parenchyma.
- Compliance Collapse & Venous Admixture: Extravasated serum proteins and hemoglobin directly inactivate pulmonary surfactant. Regional alveolar surface tension ($\gamma$) escalates:
As alveolar radius $r$ diminishes and surface tension $\gamma$ climbs, closing pressure exceeds ambient airway pressure, resulting in progressive micro-atelectasis, severe ventilation-perfusion mismatch ($V_A/Q \rightarrow 0$), and an elevated physiological right-to-left shunt ($Q_s/Q_t > 25\%$).
graph TD
    subgraph Pathophysiology of Pulmonary Contusion
        PC1["Blunt Energy Delivery"] --> PC2["Alveolar Hemorrhage & Interstitial Plasma Flooding"]
        PC2 --> PC3["Surfactant Inactivation by Fibrin & Hemoglobin"]
        PC3 --> PC4["Regional Alveolar Instability & Derecruitment"]
        PC4 --> PC5["Localized Compliance Plunge: C_rs = dV / dP"]
        PC5 --> PC6["Venous Admixture & Extreme Shunt (Qs/Qt)"]
    end
Ventilator Management Principles in Severe Contusion
- Lung-Protective Tidal Volume ($V_T$): Deliver $4-7\text{ mL/kg}$ based on predicted body weight (PBW). Avoid regional overdistension in non-contused, highly compliant "baby lung" units.
- Driving Pressure Limitation: Maintain driving pressure $\Delta P = P_{\text{plat}} - \text{PEEP} \le 14\text{ cmH}_2\text{O}$ (or transpulmonary driving pressure $\Delta P_L \le 10-12\text{ cmH}_2\text{O}$).
- PEEP Optimization: Titrate positive end-expiratory pressure ($8-12\text{ cmH}_2\text{O}$) using decremental PEEP titration or lung ultrasound to maintain functional residual capacity (FRC) and prevent cyclical recruitment-derecruitment atelectrauma.
- Judicious Fluid Strategy: Limit crystalloid administration after restoring intravascular volume and organ perfusion. Excessive fluid loading preferentially transudates into the injured, hyperpermeable contused capillary beds, worsening pulmonary edema.
Tension Pneumothorax, Hemothorax, and Tracheobronchial Rupture
graph TD
    subgraph Thoracic Trauma Triage Algorithm
        TT1["Pediatric Thoracic Blunt / Penetrating Trauma"] --> TT2{"Hemodynamic Instability + Absent Breath Sounds?"}
        TT2 -- "Yes: Hypotension, Tracheal Deviation, Distended Veins" --> TT3["Immediate Needle Decompression (2nd ICS MCL or 4th/5th ICS AAL)"]
        TT3 --> TT4["Formal Tube Thoracostomy (Chest Tube Decompression)"]
        TT2 -- "No: Stable" --> TT5["E-FAST Ultrasound & Low-Dose Chest CT"]
        TT5 --> TT6{"Massive Air Leak / Pneumomediastinum?"}
        TT6 -- "Continuous Air Bubbling + Non-expanding Lung" --> TT7["Suspect Tracheobronchial Rupture: Urgent Bronchoscopy"]
        TT6 -- "Hemothorax / Simple Pneumothorax" --> TT8["Targeted Tube Thoracostomy & PEEP Stabilization"]
    end
1. Tension Pneumothorax
- Mechanism: One-way valve air leak from lacerated parenchyma or tracheobronchial tear into the pleural space.
- Pathophysiology: Progressive intrapleural pressure rise ($P_{\text{pleural}} > P_{\text{atm}}$) collapses the ipsilateral lung, shifts the mediastinum contralaterally, compresses the superior and inferior vena cava, acutely diminishes right ventricular preload, and causes obstructive shock and arrest.
- Emergency Intervention:
- Needle Decompression: Large-bore angiocatheter (14–18 gauge depending on age) inserted in the 2nd intercostal space at the midclavicular line or the 4th/5th intercostal space at the anterior axillary line.
- Tube Thoracostomy: Placement of a dedicated, appropriately sized chest tube ($16-24\text{ Fr}$ in children; $24-28\text{ Fr}$ for hemothorax) connected to a water-seal drainage system at $-10\text{ to }-20\text{ cmH}_2\text{O}$ suction.
2. Massive Hemothorax
- Definition: Pleural blood loss $> 15-20\text{ mL/kg}$ initially upon chest tube placement or ongoing continuous hemorrhage $> 2-3\text{ mL/kg/h}$ for $> 3-4\text{ consecutive hours}$.
- Management: Urgent autotransfusion/massive transfusion protocol activation and immediate pediatric cardiothoracic surgical consultation for exploratory thoracotomy or video-assisted thoracoscopic surgery (VATS).
3. Tracheobronchial Disruption
- Mechanism: Sudden compressive deceleration against a closed glottis, crushing the large airways against the thoracic vertebral column (most commonly within $1-2\text{ cm}$ of the carina or mainstem bronchi).
- Clinical Hallmarks: Massive subcutaneous emphysema of neck/torso, persistent pneumomediastinum, and a continuous massive air leak through the chest tube with complete failure of the lung to re-expand despite high-volume negative pleural suction ("Fallen Lung Sign").
- Airway Management: Flexible fiberoptic bronchoscopy to confirm tear site; placement of the endotracheal tube distal to the tear under direct visualization, or selective single-lung ventilation of the uninjured bronchus pending primary surgical reconstruction.
Thermal and Smoke Inhalation Injury
Smoke inhalation injury is a major determinant of mortality in pediatric burn patients, multiplying burn-related mortality by up to 20-fold. Inhalation injury presents across three distinct anatomical and physiological zones:
graph TD
    A["Structure Fire / Closed-Space Combustion"] --> B["Thermal Heat Exposure"]
    A --> C["Toxic Chemicals & Soot Particulates"]
    A --> D["Systemic Asphyxiants"]

    B --> E["Supraglottic Upper Airway: Thermal Burns, Blistering, Rapid Massive Edema"]
    C --> F["Tracheobronchial Tree: Ciliary Paralysis, Mucosal Necrosis, Fibrin-Soot Casts"]
    C --> G["Alveolar Parenchyma: Chemical Pneumonitis, Non-Cardiogenic ARDS"]
    D --> H["COHb (Left Shift, Cellular Anoxia) & Cyanide (Cytochrome c Oxidase Inhibition)"]
Upper Airway Thermal Injury and the Precarious Pediatric Airway
The upper airway (nasopharynx, oropharynx, larynx) serves as an efficient heat sink. Direct thermal burn injury rarely extends below the true vocal cords because of rapid heat dissipation and reflex laryngospasm. However, the resulting inflammatory supraglottic edema is rapid and severe:
- Pediatric Funnel Airway: In infants and young children, the airway is narrowest at the cricoid ring, and baseline cross-sectional airway area ($A$) is small ($A = \pi r^2$).
- Poiseuille's Resistance Surges: According to Poiseuille's Law:
A single millimeter of circumferential mucosal edema in an infant with a baseline $4\text{ mm}$ airway radius reduces the functional lumen radius to $2\text{ mm}$, precipitating a 16-fold ($1600\%$) surge in airway resistance and work of breathing.
Fluid resuscitation of cutaneous burns accelerates soft-tissue extravasation and pharyngeal edema. A child who is comfortable and conversational at hour 2 post-injury may develop complete, un-intubatable upper airway closure by hour 6. Definitive early intubation with an appropriately sized cuffed ETT is mandatory upon identifying facial burns, singed eyebrows/vibrissae, soot in oral secretions, voice changes, or early stridor.
Lower Airway Chemical Injury and Inhaled Fibrin Cast Formation
Combustion of synthetic materials (plastics, polymers, wood) releases aldehydes, acrolein, hydrochloric acid, phosgene, and sulfur dioxide. These dissolve in airway moisture to create corrosive acids and alkalis, initiating:
- Loss of Ciliary Clearance & Mucosal Sloughing: Denudation of the pseudostratified ciliated columnar epithelium impairs mucociliary transport.
- Exudative Cast Formation: Plasma extravasation into the bronchial lumen exposes tissue factor, activating the extrinsic coagulation cascade. Fibrin polymerizes around sloughed epithelial cells, neutrophils, and carbonaceous soot particles, forming dense, obstructing bronchial casts.
- Ball-Valve Airway Obstruction: Plugs in medium and small bronchioles generate severe regional air trapping, auto-PEEP, atelectasis, and necrotizing tracheobronchitis.
graph TD
    subgraph Inhalation Airway Cast Pathogenesis
        AC1["Inhaled Acrolein / Aldehydes / Soot"] --> AC2["Tracheobronchial Mucosal Necrosis & Denudation"]
        AC2 --> AC3["Capillary Hyperpermeability + Tissue Factor Release"]
        AC3 --> AC4["Intraluminal Fibrin Polymerization"]
        AC4 --> AC5["Dense Fibrin-Epithelial-Soot Cast Generation"]
        AC5 --> AC6["Total Segmental Airway Plugging & Atelectasis"]
    end
Inhaled Nebulization Regimen for Cast Cleansing
To lyse and clear endobronchial fibrin casts without inducing systemic coagulopathy, initiate a standardized alternating nebulization protocol:
| Agent | Dose / Concentration | Mechanism of Action | Clinical Goal |
|---|---|---|---|
| Inhaled Heparin | $5,000-10,000\text{ IU}$ in $3\text{ mL NS}$ q4h | Inhibits local thrombin generation; blocks fibrin polymerization in the airway lumen | Arrests progression of new fibrin cast accretion without systemic anticoagulation |
| Nebulized N-Acetylcysteine (NAC) | $2-4\text{ mL}$ of $10\%\text{ or }20\%$ solution q4h | Cleaves disulfide bonds in mucin and denatured protein complexes | Liquefies viscous mucus and softens solid cast matrix |
| Nebulized Bronchodilator | Albuterol ($2.5-5\text{ mg}$) or Levalbuterol | Selective $\beta_2$-adrenoceptor agonist | Prevents NAC-induced reactive bronchospasm; enhances mucociliary transport |
graph LR
    subgraph Alternating Inhaled Mucolytic Bundle
        H["Inhaled Heparin (5,000-10,000 IU)"] -->|"q4h Alternating"| B["Nebulized Albuterol (2.5-5 mg)"]
        B --> NAC["Nebulized N-Acetylcysteine (2-4 mL 10-20%)"]
        NAC -->|"q4h Alternating"| H
    end
High-Frequency Percussive Ventilation (HFPV) in Inhalation Injury
Standard volume-controlled ventilation frequently fails in severe inhalation injury because dense cast plugging creates extreme mechanical heterogeneity: high peak pressures rupture open units (causing pneumothorax and pneumomediastinum), while plugged units remain atelectatic.
High-Frequency Percussive Ventilation (HFPV / VDR-4) delivers high-frequency sub-tidal percussive gas pulses ($200-600\text{ cycles/min}$) superimposed on a conventional low-frequency breathing cycle ($10-20\text{ breaths/min}$):
- Laminar Shearing and Cast Mobilization: The high-velocity mini-bursts travel down the center of the airway while expiratory gases exit along the airway periphery (asymmetric velocity profiles), clearing viscous secretions and shearing fibrin casts toward the central trachea.
- Diffusion & Convection: Delivers effective gas exchange at significantly lower peak alveolar pressures, mitigating barotrauma and reducing secondary VILI.
Systemic Toxicity: Carbon Monoxide and Cyanide
graph TD
    subgraph Toxic Inhalation Asphyxiants
        T1["Smoke Inhalation in Enclosed Space"] --> T2["Carbon Monoxide (CO) Exposure"]
        T1 --> T3["Hydrogen Cyanide (HCN) Exposure"]

        T2 --> T4["CO binds Hb with 200-250x affinity vs O2"]
        T4 --> T5["Haldane Shift: Leftward shift of Oxy-Hb curve"]
        T5 --> T6["Severe Tissue Cellular Hypoxia (Normal PaO2, Low CaO2)"]

        T3 --> T7["CN- binds Ferric Iron (Fe3+) in Cytochrome c Oxidase"]
        T7 --> T8["Arrest of Mitochondrial Electron Transport Chain"]
        T8 --> T9["Lethal Lactic Acidosis + Uncoupling of Cellular Respiration"]
    end
1. Carbon Monoxide ($CO$) Poisoning
- Pathophysiology: Affinity of hemoglobin for $CO$ is $200-250\text{ times}$ greater than for $O_2$, creating carboxyhemoglobin ($COHb$). $CO$ alters the allosteric conformation of the remaining hemoglobin subunits, shifting the oxyhemoglobin dissociation curve to the left (the Haldane effect) and preventing oxygen unloading to ischemic peripheral tissues.
- Toxicokinetics of $COHb$ Clearance:
- Standard dual-wavelength pulse oximeters ($SpO_2$) cannot distinguish oxyhemoglobin from carboxyhemoglobin; they measure both as "functional oxygen saturation" and give falsely normal readings ($99-100\%$). An arterial/venous blood gas co-oximetry panel is required.
- Administer immediate $100\%\text{ FiO}_2$ through a non-rebreather mask or endotracheal tube until $COHb < 3-5\%$.
- Hyperbaric Oxygen (HBO) Indications: $COHb > 25\%$ (or $> 15-20\%$ in pregnant patients/neonates), loss of consciousness, persistent metabolic acidosis ($\text{pH} < 7.20$), refractory cardiac ischemia, or persistent neurological deficits.
2. Hydrogen Cyanide ($HCN$) Poisoning
- Source: Combustion of wool, silk, polyurethane, polyacrylonitrile plastics, and synthetic furnishings.
- Mechanism: Cyanide binds to the ferric ($\text{Fe}^{3+}$) ion of mitochondrial cytochrome c oxidase (complex IV), halting oxidative phosphorylation and aerobic ATP production. Cells switch to anaerobic glycolysis, producing severe lactic acidosis.
- Diagnostic Clues: Inhalation victim with normal/high $PaO_2$, elevated mixed venous $SvO_2$ (inability of peripheral tissue to extract oxygen), and refractory serum lactate $> 8-10\text{ mmol/L}$.
- Antidote: Hydroxocobalamin ($70\text{ mg/kg}$ IV up to $5\text{ g}$ over 15 minutes). Hydroxocobalamin binds cyanide with high affinity to form non-toxic cyanocobalamin (vitamin $B_{12}$), which is excreted in the urine.
Acute Chest Syndrome in Sickle Cell Disease
Acute Chest Syndrome (ACS) is the leading cause of intensive care admission and mortality in pediatric patients with Sickle Cell Disease (SCD; genotypes $HbSS$, $HbS\beta^0\text{-thal}$, $HbSC$).
graph TD
    A["Initiating Trigger: Vaso-occlusive Crisis, Fat Embolism, Infection"] --> B["Hypoventilation & Chest Wall Splinting"]
    B --> C["Regional Alveolar Hypoxemia & Acidosis"]
    C --> D["Deoxygenation of HbS: Polymerization of Sickle Fibers"]
    D --> E["Erythrocyte Sickling, Rigidity, & Adhesion to Endothelium"]
    E --> F["Pulmonary Microvascular Vaso-Occlusion & Ischemia"]
    F --> G["Pulmonary Infarction & Severe Local Inflammation"]
    G --> H["Endothelin-1 Surge, Free Heme Toxicity, NO Scavenging"]
    H --> I["Surfactant Inactivation & Extensive Lobar Consolidation"]
    I --> C
Pathophysiological Cascade: The Vicious Cycle of Sickling
ACS is characterized by a rapidly propagating, self-amplifying cycle:
- Trigger Phase: A vaso-occlusive pain crisis (VOC) affecting the ribs, sternum, or spine leads to voluntary splinting, shallow breathing, and localized micro-atelectasis. Alternatively, bone marrow infarction releases necrotic fat droplets and free fatty acids into the venous circulation, lodging in the pulmonary microvasculature.
- Polymerization Phase: Local alveolar hypoxia ($PO_2 \downarrow$) and hypercapnic acidosis ($\text{pH} \downarrow$) induce the hydrophobic polymerization of deoxygenated sickle hemoglobin ($HbS$) molecules into rigid 14-strand helical fibers:
Because the delay time for polymerization ($\tau_{\text{delay}}$) is inversely proportional to the 30th to 40th power of intracellular $HbS$ concentration, even modest drops in local oxygen tension or cellular dehydration trigger rapid erythrocyte sickling. 3. Endothelial Adhesion & Micro-thrombosis: Rigid sickled erythrocytes, activated leukocytes, and platelets adhere to vascular cell adhesion molecule-1 (VCAM-1) and P-selectin on the pulmonary capillary endothelium, causing microvascular occlusion. 4. Intravascular Hemolysis & NO Depletion: Intravascular shearing releases free hemoglobin into plasma, which scavenges endogenous endothelial nitric oxide ($\text{NO}$):
$$\text{Hb}(\text{Fe}^{2+}) + \text{NO} \longrightarrow \text{MetHb}(\text{Fe}^{3+}) + \text{NO}_3^-$$Depletion of bioavailable $\text{NO}$ causes intense pulmonary vasoconstriction, acute pulmonary arterial hypertension, and acute right ventricular afterload strain.
Diagnostic Criteria and Severity Stratification
According to the National Institutes of Health (NIH) and international consensus guidelines, ACS is defined by:
- A new pulmonary infiltrate on chest radiography involving at least one complete lung segment, PLUS
- At least one of the following clinical signs/symptoms:
- Fever ($\ge 38.5^\circ\text{C}$)
- Respiratory distress (tachypnea, intercostal retractions, grunting, nasal flaring)
- Cough, wheezing, or chest pain
- Acute hypoxemia ($> 3\%$ drop in baseline room air $SpO_2$ or absolute $SpO_2 < 92\%$)
| Severity Tier | Clinical & Radiographic Presentation | Oxygenation / Laboratory Metrics | Primary Therapeutic Strategy |
|---|---|---|---|
| Mild ACS | Single-lobe consolidation, mild tachypnea, mild chest pain | Room air $SpO_2 \ge 92-95\%$; $Hb \ge 7-8\text{ g/dL}$; baseline platelets | Incentive spirometry, IV hydration (maintenance), broad-spectrum IV antibiotics, multimodal analgesia |
| Moderate ACS | Multi-lobar involvement, progressive tachypnea, moderate retractions | $SpO_2 < 92\%$ on room air; $Hb$ drop $1-2\text{ g/dL}$ below baseline; platelets declining | Supplemental $O_2$, trial of HFNC or CPAP, Simple Transfusion ($10\text{ mL/kg}$ PRBCs) |
| Severe / Critical ACS | Multi-lobar/pan-lobar consolidation, exhaustion, altered mental status, acute cor pulmonale | $\text{PaO}_2/\text{FiO}_2 \le 200$; platelet count $< 100 \times 10^9/\text{L}$; rapidly falling $Hb$; lactic acidosis | ICU admission, Automated Red Cell Exchange (RCE), NIV/Invasive ventilation, iNO, ECMO readiness |
Transfusion Decision Pathway: Simple vs. Exchange Transfusion
graph TD
    A["Diagnosis of Acute Chest Syndrome in SCD"] --> B{"Assess Clinical Severity & Progression"}

    B -- "Mild / Moderate: Single Lobe, Stable Work of Breathing, Hb > 7-8" --> C["Simple PRBC Transfusion (10-15 mL/kg)"]
    C --> D["Target Hb: 9.5-10.5 g/dL (Never exceed 11 g/dL)"]

    B -- "Severe / Rapidly Deteriorating: Multi-Lobar, PaO2/FiO2 < 200, Platelets < 100k, Encephalopathy" --> E["Automated Red Cell Exchange Transfusion (RCE)"]
    E --> F["Replace Sickled HbS with HbA Units"]
    F --> G["Target: HbS < 30%, Total Hb 10-11 g/dL, Preserved Blood Viscosity"]
- Hyperviscosity Risk: In patients with sickle cell disease, whole blood viscosity escalates exponentially when total hemoglobin rises above $11\text{ g/dL}$ while high fractions of $HbS$ ($> 30\%$) remain present. Never perform a simple transfusion if baseline hemoglobin is $\ge 9.0-10.0\text{ g/dL}$, as this will cause hyperviscosity syndrome and stroke.
- Automated Red Blood Cell Exchange (RCE / Erythrocytapheresis): The gold standard for severe ACS. It removes circulating rigid $HbS$-containing erythrocytes while simultaneously infusing normal $HbA$ donor units, lowering $HbS < 30\%$ without increasing total hematocrit or blood viscosity.
- Manual Exchange: If automated apheresis is unavailable, perform manual exchange via isovolumetric aliquots ($5-10\text{ mL/kg}$ phlebotomy followed by equal-volume $PRBC$ transfusion).
Noninvasive Support and Invasive Mechanical Ventilation in ACS
graph TD
    subgraph Respiratory Support Escalation in ACS
        RS1["Early ACS: SpO2 < 95% or Pain Splinting"] --> RS2["Incentive Spirometry (10 breaths/2h) + High-Flow Nasal Cannula (1-2 L/kg/min)"]
        RS2 --> RS3{"Persistent Hypoxia / Work of Breathing?"}
        RS3 -- "Yes" --> RS4["CPAP (5-8 cmH2O) or BiPAP (IPAP 10-14 / EPAP 5-8 cmH2O)"]
        RS4 --> RS5{"Exhaustion, Worsening Consolidation, PaO2/FiO2 <= 150?"}
        RS5 -- "Yes" --> RS6["Invasive Endotracheal Intubation & Lung-Protective Ventilation"]
        RS6 --> RS7["Adjuvant Inhaled Nitric Oxide (iNO 10-20 ppm) & Early VV-ECMO"]
    end
Noninvasive Ventilation (NIV)
- First-Line Escalation: Continuous Positive Airway Pressure (CPAP $5-8\text{ cmH}_2\text{O}$) or Bi-level Positive Airway Pressure (BiPAP, IPAP $10-14\text{ cmH}_2\text{O}$, EPAP $5-8\text{ cmH}_2\text{O}$) recruits micro-atelectatic alveolar segments, unloads fatigued inspiratory muscles, restores FRC, and prevents progression to invasive mechanical ventilation.
Invasive Mechanical Ventilation
Invasive mechanical ventilation in patients with sickle cell disease is associated with significant morbidity and prolonged ICU stays, but is life-saving in refractory respiratory failure.
- Ventilator Settings:
- Tidal Volume: $5-7\text{ mL/kg}$ PBW.
- PEEP: $8-12\text{ cmH}_2\text{O}$ to maintain alveolar patency and reverse chest splinting.
- Driving Pressure: $\Delta P \le 13-14\text{ cmH}_2\text{O}$.
- Permissive Hypercapnia: Allowed ($\text{pH} \ge 7.25-7.30$), but severe acidosis ($\text{pH} < 7.20$) must be avoided because hydrogen ion accumulation promotes $HbS$ deoxygenation and polymerization.
Targeted Adjuvants: Inhaled Nitric Oxide and ECMO
- Inhaled Nitric Oxide (iNO): Administered at $10-20\text{ ppm}$. Selectively vasodilates ventilated pulmonary vascular beds, improves $V_A/Q$ matching, reduces right ventricular afterload in acute pulmonary hypertension, and increases the oxygen affinity of $HbS$.
- Extracorporeal Membrane Oxygenation (ECMO): In pediatric patients with severe ACS progressing to refractory ARDS ($\text{OI} > 40$ or $P/F < 80$ despite exchange transfusion, prone positioning, and iNO), venovenous (VV) ECMO provides lung rest and oxygenation while hemolysis and inflammation resolve.
Comparative Matrix: Pathophysiology and Ventilatory Tactics
| Clinical Feature | Pediatric Pulmonary Contusion | Inhalation Cast Injury | Acute Chest Syndrome (SCD) |
|---|---|---|---|
| Primary Anatomical Target | Alveolar-capillary membrane & interstitial space | Tracheobronchial epithelium & small airways | Pulmonary microvasculature & capillary beds |
| Biomechanical Mechanism | High kinetic energy transfer through compliant rib cage | Chemical sloughing & intraluminal fibrin-soot casting | $HbS$ hydrophobic polymerization & micro-thrombosis |
| Ventilation Abnormality | Severe $V_A/Q$ shunt with preserved or elevated airway resistance | Ball-valve gas trapping, high Raw, heterogeneous auto-PEEP | Intrapulmonary shunt + pulmonary vascular dead space ($V_D/V_T$) |
| Ventilator Strategy | Lung-protective $V_T$ ($4-6\text{ mL/kg}$), PEEP $8-12\text{ cmH}_2\text{O}$, $\Delta P \le 14$ | HFPV / VDR, high inspiratory flow, prolonged expiration | Early NIV (CPAP/BiPAP), open-lung PEEP ($8-12$), prevent severe acidosis |
| Key Targeted Pharmacotherapy | Judicious crystalloid fluid restriction; analgesia | Inhaled Heparin + Nebulized NAC + $\beta_2$-agonists; Hydroxocobalamin / HBO | Exchange Transfusion ($HbS < 30\%$), iNO ($10-20\text{ ppm}$), IV Macrolide + Cephalosporin |
| Lethal Pitfall to Avoid | Overzealous fluid loading worsening contused lung edema | Delayed intubation of developing supraglottic edema | Simple transfusion in non-anemic patient ($\rightarrow$ hyperviscosity) |
Key Takeaways and Summary
- Pediatric Thorax Elasticity: The highly compliant pediatric chest wall transmits significant blunt energy directly to the lung parenchyma, causing severe contusions and tracheobronchial tears without rib fractures.
- Early Airway Protection in Burns: Upper airway thermal injury causes rapid pharyngeal edema that is accelerated by burn fluid resuscitation. Secure the airway early before anatomical landmarks are lost.
- Inhalation Cast Clearance: Chemical injury produces intraluminal fibrin-soot casts. Treat with alternating inhaled heparin ($5,000-10,000\text{ IU}$) and nebulized N-acetylcysteine with bronchodilators to preserve airway patency.
- Asphyxiant Management: Treat carbon monoxide exposure with immediate $100\%\text{ FiO}_2$ to shorten $COHb$ half-life from 320 to 80 minutes; treat severe cyanide-induced lactic acidosis with IV hydroxocobalamin ($70\text{ mg/kg}$).
- Sickle Cell ACS Transfusion Strategy: Use simple transfusion for moderate anemia ($Hb \text{ target } 10\text{ g/dL}$); execute automated red cell exchange (RCE) for severe or rapidly worsening ACS to reduce $HbS < 30\%$ while strictly maintaining total $Hb \le 10-11\text{ g/dL}$ to prevent hyperviscosity.
- Lung-Protective Mechanical Support: Prioritize early CPAP/BiPAP in ACS and contusion; when invasive mechanical ventilation is necessary, enforce driving pressure restriction ($\Delta P \le 14\text{ cmH}_2\text{O}$) and optimize PEEP to prevent cyclical atelectrauma.