Liberating the critically ill infant or child from invasive mechanical ventilation represents a delicate physiological transition from positive-pressure mechanical support to unassisted, spontaneous negative-pressure breathing. Premature extubation exposes the pediatric patient to catastrophic upper airway obstruction, progressive atelectasis, respiratory muscle exhaustion, and emergent reintubation—an event independently associated with a four- to five-fold increase in pediatric intensive care unit (PICU) mortality, prolonged hospital stay, and secondary subglottic trauma. Conversely, unduly delayed extubation increases exposure to ventilator-associated pneumonia (VAP), ventilator-induced lung injury (VILI), ventilator-induced diaphragmatic dysfunction (VIDD), and cumulative sedative toxicity.
A structured, evidence-based approach integrating standardized readiness screening, objective spontaneous breathing trials (SBT), bedside physiological mechanics, point-of-care diaphragmatic ultrasonography (POCUS), and proactive post-extubation upper airway management is essential for optimizing liberation outcomes across neonates, infants, and children.
graph TD
    A["Daily Morning Screening<br/>Resolution of Primary Pathology"] --> B{"Readiness Criteria Met?<br/>• Hemodynamics: Low/No Inotropes<br/>• Gas Exchange: OI ≤ 4-5, OSI ≤ 5<br/>• Ventilator: P/F ≥ 200-250, FiO2 ≤ 0.40-0.45, PEEP ≤ 5-6<br/>• Neurologic: Intact Cough/Gag, Responsive"}

    B -- "No" --> C["Continue Lung-Protective Ventilation<br/>Address Reversible Causes & Screen Daily"]
    B -- "Yes" --> D["Conduct Spontaneous Breathing Trial (SBT)<br/>Duration: 30–120 Minutes<br/>Mode: PS 5–8 / PEEP 5 or CPAP 5 cmH2O"]

    D --> E{"SBT Tolerance Assessment<br/>• Stable HR/BP (Δ < 20%)<br/>• Age-appropriate RR (no tachypnea)<br/>• No severe retractions / paradox<br/>• Stable gas exchange (SpO2 ≥ 92-95%, ΔpH < 0.07-0.10)"}

    E -- "Failed SBT" --> F["Abort Trial & Return to Baseline Support<br/>Investigate Failure: Diaphragm Weakness, Overload, Sedation"]
    E -- "Passed SBT" --> G["Upper Airway & Extubation Readiness<br/>1. Pediatric Cuff Leak Test (CLT)<br/>2. Airway Protection & Secretion Load<br/>3. Diaphragm Ultrasound (DTF > 25-35%, DE)"]

    G --> H{"Cuff Leak Present & Low Risk?"}
    H -- "Pass (Leak > 10-15% or Audible)" --> I["Proceed to Planned Extubation<br/>Ensure Post-Extubation O2 / HFNC Available"]
    H -- "Failed CLT / High Risk" --> J["Dexamethasone Protocol: 0.5 mg/kg Q6H<br/>(4–6 doses over 12–24h prior to re-testing)<br/>Plan Prophylactic Post-Extubation HFNC/NIV"]

    J --> I
Structured Pediatric Weaning Framework
The process of liberating pediatric patients from mechanical ventilation encompasses three distinct phases: (1) disease stabilization and weaning of mandatory ventilation, (2) formal assessment of extubation readiness via a spontaneous breathing trial, and (3) endotracheal tube removal with post-extubation monitoring.
ERS/ATS Pediatric Weaning Classification
Standardized definitions established by the European Respiratory Society (ERS) and American Thoracic Society (ATS) stratify pediatric patients into three diagnostic weaning categories:
graph LR
    subgraph S1["Simple Weaning"]
        A1["Successful extubation on the<br/>first spontaneous breathing trial<br/>without difficulty (~65–75% PICU cohort)"]
    end

    subgraph S2["Difficult Weaning"]
        B1["Requires up to 3 SBTs or<br/>up to 7 days from the initial<br/>failed SBT to achieve extubation"]
    end

    subgraph S3["Prolonged Weaning"]
        C1["Fails ≥ 3 SBTs or requires<br/>> 7 days of mechanical support<br/>following the first failed SBT"]
    end
- Simple Weaning: Successful extubation on the initial attempt following the first formal SBT without post-extubation failure within 48 hours. This comprises the majority (65–75%) of routine pediatric ICU admissions.
- Difficult Weaning: Patients who fail their initial SBT and require up to 3 SBTs or up to 7 days from the first trial to achieve successful extubation.
- Prolonged Weaning: Patients who fail 3 or more consecutive SBTs or require greater than 7 days of mechanical ventilation following the first failed attempt. This high-risk subset includes children with severe chronic lung disease, underlying neuromuscular disorders, anatomical airway anomalies, or severe post-cardiac surgery diaphragmatic injury.
flowchart TD
    subgraph PUMP["PUMP: Neuromuscular Drive & Capacity"]
        P1["Central Respiratory Center"] --> P2["Phrenic Nerve Conduction"]
        P2 --> P3["Diaphragmatic Contractility (DTF, DE)"]
        P3 --> P4["Chest Wall / Intercostal Muscles"]
    end

    subgraph LOAD["LOAD: Mechanical & Metabolic Demand"]
        L1["Resistive Load (Small ETT, Airway Edema, Bronchospasm)"]
        L2["Elastic Load (Atelectasis, Reduced Lung Compliance)"]
        L3["Cardiovascular Load (LV Afterload Shift, Shunts)"]
        L4["Metabolic Work (Fever, Sepsis, Agitation)"]
    end

    PUMP <-->|"Dynamic Balance (WOB)"| LOAD
Readiness Screening Criteria
Prior to initiating an SBT, children must meet objective physiological criteria confirming resolution or significant improvement of the primary pathology, hemodynamic stability, adequate gas exchange on low ventilatory support, and neurological responsiveness:
| Organ System / Domain | Physiological Parameter | Target Threshold for Readiness | Clinical Rationale & Pearls |
|---|---|---|---|
| Primary Disease | Underlying pulmonary/systemic etiology | Resolving / stabilized phase | Ensures pathological triggers (e.g., active bronchiolitis, ARDS) are controlled. |
| Gas Exchange & Oxygenation | Oxygenation Index ($OI$) | $OI \le 4.0 - 5.0$ | Reflects low oxygenation tension load; $OI = \frac{\text{MAP} \times \text{FiO}_2 \times 100}{\text{PaO}_2}$. |
| Oxygen Saturation Index ($OSI$) | $OSI \le 5.0$ | Non-invasive pulse oximetric surrogate; $OSI = \frac{\text{MAP} \times \text{FiO}_2 \times 100}{\text{SpO}_2}$. | |
| $\text{PaO}_2 / \text{FiO}_2$ Ratio ($P/F$) | $\ge 200 - 250\text{ mmHg}$ | Acceptable alveolar-capillary gas diffusion capacity. | |
| $\text{FiO}_2$ Requirement | $\le 0.40 - 0.45$ | Easily delivered via simple low-flow or non-invasive post-extubation devices. | |
| Positive End-Expiratory Pressure ($\text{PEEP}$) | $\le 5.0 - 6.0\text{ cmH}_2\text{O}$ | Alveolar recruitment maintained at baseline physiological distending pressures. | |
| Ventilatory Dynamics | Spontaneous Respiratory Effort | Consistent spontaneous breaths | Initiates breaths reliably; no reliance on deep backup rates. |
| Peak Airway Pressure / Pressure Support | $\text{PIP} \le 20-22\text{ cmH}_2\text{O}$ or $\Delta P \le 10$ | Low mandatory driving pressure required to achieve normal $V_T$ ($6-8\text{ mL/kg}$). | |
| Hemodynamics | Vasoactive-Inotropic Score (VIS) | $\text{VIS} \le 5.0$ (or low-dose single agent) | Ensures adequate cardiovascular reserve without imminent shock. |
| Cardiac Rhythm & Perfusion | Normal sinus rhythm, lactate $< 2\text{ mmol/L}$ | Capable of tolerating the abrupt increase in LV afterload following extubation. | |
| Neurology & Sedation | Sedation Depth (State Behavioral Scale / COMFORT-B) | Awake, interactive, SBS $-1\text{ to }0$ | Able to maintain upper airway tone, clear secretions, and protect airway. |
| Airway Reflexes | Vigorous cough and gag on suctioning | Essential to prevent aspiration and subglottic mucous plugging. |
The Second Pediatric Acute Lung Injury Consensus Conference (PALICC-2) strongly recommends protocolized daily extubation readiness testing for all mechanically ventilated children. Protocol-driven weaning consistently reduces total ventilator days, accidental extubation rates, and PICU length of stay without escalating extubation failure rates.
Spontaneous Breathing Trial in Pediatrics
The Spontaneous Breathing Trial is the definitive diagnostic challenge to evaluate whether the pediatric patient's respiratory muscle capacity can sustain the metabolic work of breathing ($WOB$) once the mechanical ventilator is disconnected.
graph TD
    A["Initiate Pediatric SBT<br/>Verify Baseline Sedation & Suction ETT"] --> B{"Select Trial Modality"}

    B --> C["Pressure Support (PS 5–8 / PEEP 5 cmH2O)<br/>• Offsets Imposed ETT Work (WOB_imp)<br/>• Preferred in Small Infants (ETT ≤ 4.0 mm)"]
    B --> D["Continuous Positive Airway Pressure (CPAP 5 cmH2O)<br/>• True Assessment of Unassisted Diaphragm Capacity<br/>• Standard PALICC-2 Recommened Modality"]
    B --> E["T-Piece Trial<br/>• Rarely Used in Young Pediatrics<br/>• Extreme WOB_imp from Small ETT Caliber"]

    C & D --> F["Run Trial for 30–60 Minutes<br/>(Extend to 120 mins in High-Risk/Borderline Cases)"]

    F --> G{"Continuously Monitor Failure Criteria"}
    G -- "Tachypnea (> 2 SD above age norm)<br/>Retractions / Diaphoresis / Flaring<br/>HR change > 20% / Hypotension<br/>Acidosis: ΔpH > 0.08 or PaCO2 > 55-60<br/>SpO2 < 90-92% on FiO2 ≤ 0.50" --> H["SBT Failure: Terminate Trial<br/>Resume Baseline Mechanical Support"]
    G -- "Stable Mechanics, Normal Gas Exchange,<br/>Comfortable Respiratory Effort" --> I["SBT Passed: Evaluate Upper Airway & Extubate"]
Modalities: Overcoming Imposed Work of Breathing ($WOB_{imp}$)
Because endotracheal tubes in pediatrics have small internal diameters ($ID = 2.5 - 6.0\text{ mm}$), resistive pressure drops across the artificial airway are governed by Poiseuille's law and turbulent flow dynamics:
$$\Delta P_{\text{resistive}} = \frac{8 \cdot \eta \cdot l \cdot \dot{V}}{\pi \cdot r^4} + K_2 \cdot \dot{V}^2$$Where:
- $\eta$ is gas viscosity,
- $l$ is ETT length,
- $r$ is internal radius ($ID/2$),
- $\dot{V}$ is instantaneous inspiratory flow,
- $K_2$ is the Rohrer coefficient for non-linear turbulent convective acceleration.
A decrease in tube radius by half increases laminar resistance by a factor of 16 ($r^4$), imposing substantial resistive work ($WOB_{imp}$) that does not exist once the child is extubated to native upper airways.
flowchart LR
    A["Endotracheal Tube Caliber<br/>(Radius r)"] -->|"Poiseuille Law: R ∝ 1/r⁴"| B["Imposed Resistance (WOB_imp)"]
    B --> C{"SBT Modality Choice"}
    C -->|"PS 5–8 cmH2O"| D["Overcomes WOB_imp<br/>Prevents Artificial Fatigue"]
    C -->|"CPAP 5 cmH2O"| E["Maintains FRC<br/>Tests True Native Muscle Capacity"]
    C -->|"T-Piece (0 cmH2O)"| F["High WOB_imp<br/>Risk of Premature Diaphragm Failure"]
Modality Comparison
- Low-Level Pressure Support ($PS 5-8\text{ cmH}_2\text{O} / \text{PEEP } 5\text{ cmH}_2\text{O}$):
- Physiological Mechanism: The inspiratory pressure boost matches the computed pressure drop across the narrow ETT, neutralizing $WOB_{imp}$ while the child generates tidal volume independently.
- Clinical Role: Widely utilized in small infants ($ETT \le 4.0\text{ mm}$) where unassisted breathing through the tube would induce rapid muscle fatigue unrelated to intrinsic lung pathology.
- CPAP Mode ($5\text{ cmH}_2\text{O}$ with $PS = 0\text{ cmH}_2\text{O}$):
- Physiological Mechanism: Provides physiological distending pressure to prevent alveolar atelectasis (matching the functional residual capacity preserved by native glottic grunting) without inspiratory pressure assistance.
- Clinical Role: Recommended by PALICC-2 as the standard trial modality for older infants and children to reveal occult respiratory muscle exhaustion.
- T-Piece Circuit:
- Physiological Mechanism: Completely unassisted breathing from an open blow-by gas reservoir.
- Limitation: Imposes severe resistive loads on small children and eliminates positive end-expiratory pressure, leading to dependent alveolar collapse. Largely obsolete in modern PICU practice.
Optimal Duration of Pediatric SBT
Historically, pediatric trials ranged from 60 to 120 minutes. Contemporary randomized clinical trials and multicenter prospective pediatric cohorts have demonstrated that a 30- to 60-minute SBT is non-inferior to a 120-minute trial in predicting successful extubation across general pediatric populations. Extending trials to 120 minutes is reserved for borderline candidates, children with severe underlying neuromuscular disease, or long-term ventilated patients recovering from complex cardiac surgery.
Objective Failure Criteria
During the SBT, bedside clinicians must monitor physiological indicators continuously. The trial must be aborted immediately if any of the following criteria are met:
graph TD
    subgraph FC["Multi-System Pediatric SBT Failure Criteria"]
        F1["Respiratory Rate Failure:<br/>RR > 2 SD above age-adjusted mean<br/>or Severe Bradypnea / Apnea"]
        F2["Increased Work of Breathing:<br/>Suprasternal / Subcostal Retractions,<br/>Nasal Flaring, Grunting, Paradox"]
        F3["Cardiovascular Decompensation:<br/>HR change > 20% from baseline,<br/>Hypotension, Mottling, Diaphoresis"]
        F4["Gas Exchange Failure:<br/>SpO2 < 90–92% on FiO2 ≤ 0.50,<br/>Acute Acidosis: ΔpH > 0.08, PaCO2 > 55–60 mmHg"]
    end
Age-Specific Respiratory Rate Failure Limits During SBT
| Age Group | Normal Resting Spontaneous RR (breaths/min) | SBT Tachypnea Failure Threshold ($> 2\text{ SD}$) | SBT Severe Bradypnea Limit |
|---|---|---|---|
| Neonate ($< 1\text{ month}$) | $30 - 50$ | $> 60 - 65$ | $< 25$ |
| Infant ($1 - 12\text{ months}$) | $25 - 45$ | $> 55 - 60$ | $< 20$ |
| Toddler ($1 - 3\text{ years}$) | $20 - 35$ | $> 45$ | $< 15$ |
| Preschool ($4 - 6\text{ years}$) | $18 - 25$ | $> 35$ | $< 12$ |
| School Age ($7 - 12\text{ years}$) | $14 - 22$ | $> 30$ | $< 10$ |
| Adolescent ($> 12\text{ years}$) | $12 - 18$ | $> 25$ | $< 8$ |
Paradoxical inward movement of the anterior chest wall during inspiration (see-saw breathing) during a pediatric SBT is a hallmark of imminent diaphragmatic fatigue or upper airway obstruction. In infants, high chest wall compliance ($C_{cw}$) allows negative pleural pressures generated by a fatigued diaphragm to collapse the cartilaginous rib cage inward, resulting in inefficient alveolar ventilation and rapid respiratory decompensation.
Objective Bedside Predictors of Extubation Success
While the clinical SBT remains the cornerstone of extubation decision-making, objective quantitative indices refine risk stratification and prevent premature liberation.
graph TD
    A["Bedside Extubation Indices"] --> B["Pediatric RSBI & C-RSBI"]
    A --> C["Diaphragmatic Ultrasound (POCUS)"]
    A --> D["Neuromuscular Drive: P0.1 & MIP"]

    B --> B1["RSBI = RR / (Vt/kg)<br/>Infants: < 6.0–8.0 breaths/min/(mL/kg)<br/>C-RSBI = RSBI / Cdyn"]
    C --> C1["Thickening Fraction: DTF > 25–35%<br/>Excursion: DE > 4–8 mm (infants), > 10–14 mm (older)"]
    D --> D1["Airway Occlusion: P0.1 = 1.0–3.5 cmH2O<br/>MIP / NIF ≤ -30 cmH2O"]
Pediatric Rapid Shallow Breathing Index (RSBI)
The adult Yang-Tobin index ($\text{RSBI} = \frac{RR}{V_T \text{ [L]}}$) uses absolute tidal volume, making it inaccurate across pediatric weight ranges spanning from a $3\text{ kg}$ neonate to a $70\text{ kg}$ adolescent. The weight-standardized Pediatric RSBI ($p\text{RSBI}$) normalizes tidal volume to body weight:
$$p\text{RSBI} = \frac{\text{Spontaneous Respiratory Rate (breaths/min)}}{\text{Tidal Volume (mL/kg)}} = \frac{RR}{V_T / \text{kg}}$$$$\text{Compliance-Adjusted RSBI (C-RSBI)} = \frac{p\text{RSBI}}{C_{\text{dyn}} \text{ (mL/cmH}_2\text{O/kg)}} = \frac{RR / (V_T/\text{kg})}{\Delta V / \Delta P}$$| Metric / Parameter | Age / Weight Stratification | Threshold for Extubation Success | Predictive Validity & Pitfalls |
|---|---|---|---|
| Standard Adult RSBI | Adolescents ($> 50\text{ kg}$) | $< 105\text{ breaths/min/L}$ | Reliable only in adult-sized adolescents. |
| Pediatric RSBI ($p\text{RSBI}$) | Infants ($< 1\text{ year}$) Children ($1 - 12\text{ years}$) | $< 8.0\text{ breaths/min/(mL/kg)}$ $< 6.0\text{ breaths/min/(mL/kg)}$ | High negative predictive value; values $> 10-11$ strongly indicate impending fatigue. |
| Compliance-Adjusted RSBI ($C\text{-RSBI}$) | General PICU cohort | $< 8.0 - 10.0$ | Integrates dynamic lung stiffness; superior accuracy in resolving restrictive lung injury. |
Airway Occlusion Pressure at 100 ms ($P_{0.1}$)
$P_{0.1}$ represents the negative airway pressure generated against an occluded airway during the first $100\text{ ms}$ of spontaneous inspiration:
- Physiological Normal: $1.0 - 3.5\text{ cmH}_2\text{O}$.
- Depressed Drive ($P_{0.1} < 1.0\text{ cmH}_2\text{O}$): Indicates central nervous system depression, excessive residual sedation, or blunted neuromuscular responsiveness.
- Excessive Drive ($P_{0.1} > 4.0 - 5.0\text{ cmH}_2\text{O}$): Reflects severe respiratory muscle overload, high metabolic demand, or occult resistive/elastic load, predicting post-extubation exhaustion.
Maximal Inspiratory Pressure (MIP / NIF)
Measured via unidirectional occlusion valve over $20-30\text{ seconds}$ of spontaneous effort:
$$\text{MIP} \le -30\text{ cmH}_2\text{O} \quad (\text{e.g., } -35\text{ to } -50\text{ cmH}_2\text{O})$$A value less negative than $-20\text{ to } -25\text{ cmH}_2\text{O}$ indicates severe diaphragmatic weakness, quadriplegia, or critical illness myopathy.
Point-of-Care Diaphragmatic Ultrasound (D-POCUS)
Point-of-care ultrasound directly visualizes diaphragmatic morphology and dynamic contractile function at the bedside without patient cooperation.
graph LR
    subgraph D_US["Point-of-Care Diaphragmatic Ultrasound"]
        direction TB
        M1["B-Mode / Zone of Apposition<br/>(8th–10th Intercostal Space)"] --> M2["Diaphragmatic Thickness (TDI & TDE)<br/>DTF = (TDI - TDE) / TDE × 100%"]
        M3["M-Mode / Subcostal Approach<br/>(Transhepatic / Transsplenic View)"] --> M4["Diaphragmatic Excursion (DE)<br/>Infants: > 4–8 mm<br/>Children: > 10–14 mm"]
    end
Diaphragmatic Thickening Fraction (DTF)
Assessed using a high-frequency linear vascular transducer ($10-15\text{ MHz}$) positioned at the zone of apposition between the anterior and mid-axillary lines in the 8th to 10th intercostal space:
$$\text{DTF } (\%) = \frac{\text{Thickness at End-Inspiration } (T_{\text{insp}}) - \text{Thickness at End-Expiration } (T_{\text{exp}})}{T_{\text{exp}}} \times 100$$- Normal Extubation Readiness Threshold: $\text{DTF} > 25\% - 35\%$.
- Diaphragm Dysfunction / Atrophy: $\text{DTF} < 17\% - 20\%$ or basal end-expiratory thickness $< 1.2 - 1.5\text{ mm}$ in infants indicates ventilator-induced diaphragmatic atrophy.
Diaphragmatic Excursion (DE)
Assessed using a low-to-medium frequency phased-array or microconvex transducer ($3.5-8\text{ MHz}$) positioned subcostally via the transhepatic (right) or transsplenic (left) acoustic window in M-mode:
- Infants and Young Children: $\text{DE} > 4.0 - 8.0\text{ mm}$.
- Older Children & Adolescents: $\text{DE} > 10.0 - 14.0\text{ mm}$.
- Paradoxical Motion ($\text{DE} < 0\text{ mm}$): Signifies phrenic nerve injury (frequent following congenital cardiac surgery or surgical chest dissection) and predicts immediate extubation failure unless supported by non-invasive positive pressure.
Clinical Architecture: The PUMP-LOAD Weaning Framework
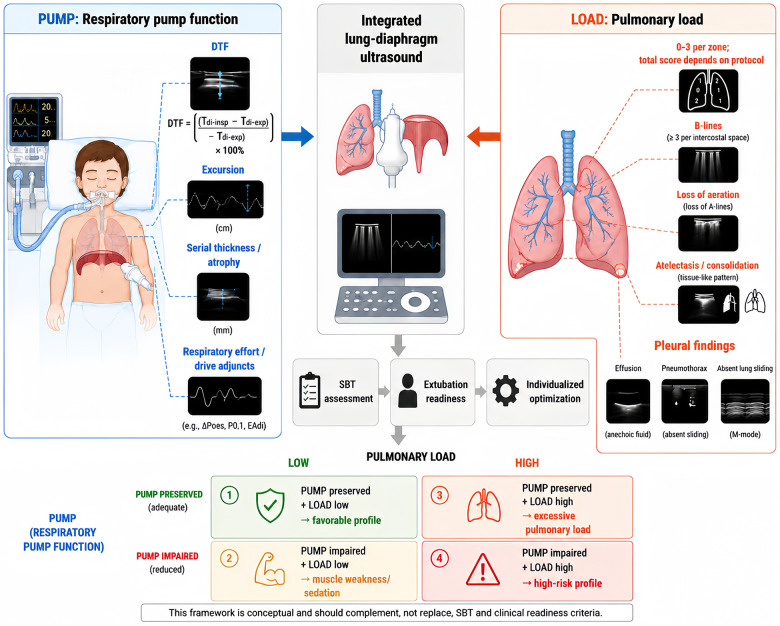 Figure 1: The integrative PUMP-LOAD pathophysiological framework for pediatric weaning and extubation readiness assessment. The PUMP axis integrates central neural drive, neuromuscular transmission, and diaphragmatic contractility (assessed bedside via diaphragm ultrasound: thickening fraction [DTF] and excursion [DE], rapid shallow breathing index [RSBI], airway occlusion pressure [P0.1], and maximum inspiratory pressure [MIP/NIF]). The LOAD axis evaluates resistive work of breathing (small endotracheal tube caliber, dynamic airway resistance, subglottic edema/cuff leak patency) and elastic work (lung compliance, alveolar aeration via lung ultrasound score [LUS], and chest wall elastance) alongside cardiovascular reserve (LV/RV filling pressures, post-extubation afterload shifts). Sourced from Tiseo D, et al. Front Pediatr 2026;14:1904927 under CC-BY 4.0.
flowchart TD
    subgraph PUMP_AXIS["PUMP Evaluation (Capacity)"]
        PA1["P0.1: 1.0–3.5 cmH2O (Drive)"]
        PA2["MIP ≤ -30 cmH2O (Strength)"]
        PA3["Diaphragm DTF > 25–35% (Contractility)"]
        PA4["Diaphragm DE > 5–10 mm (Displacement)"]
    end

    subgraph LOAD_AXIS["LOAD Evaluation (Demand)"]
        LA1["Resistive: Raw, Small ETT Caliber, Secretions"]
        LA2["Elastic: Lung Ultrasound Score (LUS), Dynamic Compliance"]
        LA3["Cardiovascular: Left Ventricular Diastolic Filling, Afterload Shift"]
        LA4["Upper Airway: Cuff Leak Volume > 10–15%"]
    end

    PUMP_AXIS --> INTEGRATION{"PUMP ≥ LOAD Equilibrium?"}
    LOAD_AXIS --> INTEGRATION

    INTEGRATION -- "Capacity > Demand" --> EXTUBATE["Safe Extubation to Native Airway"]
    INTEGRATION -- "Demand > Capacity" --> RESCUE["Prophylactic NIV / HFNC or Delayed Extubation"]
Upper Airway Patency and Post-Extubation Failure Prevention
Post-extubation stridor (PES) due to laryngeal and subglottic mucosal edema occurs in $5\% - 15\%$ of unselected pediatric extubations and accounts for over one-third of all extubation failures in the PICU.
graph TD
    A["Screening for Post-Extubation Airway Compromise"] --> B["Cuff Leak Test (CLT)"]

    B --> C{"Leak Assessment"}
    C -- "Qualitative: Audible leak at ≤ 20–25 cmH2O<br/>Quantitative: Leak volume > 10–15% of Vt" --> D["Low Stridor Risk<br/>Standard Post-Extubation Care"]
    C -- "No Leak / High Airway Pressure (> 25 cmH2O)<br/>or Leak Volume < 10%" --> E["High Stridor Risk Identified"]

    E --> F["Dexamethasone Prophylaxis Bundle:<br/>• Dose: 0.5 mg/kg IV (max 10 mg)<br/>• Schedule: Q6H for 4–6 doses<br/>• Duration: 12–24h prior to extubation"]

    F --> G["Re-evaluate Cuff Leak Prior to Extubation"]
    G --> H["Extubation Strategy:<br/>1. Extubate under Direct Vision / Full Resuscitation Equipment<br/>2. Prophylactic Post-Extubation HFNC (1.5–2.0 L/kg/min)<br/>3. Immediate Nebulized Racemic Epinephrine if Stridor Develops"]
Pediatric Cuff Leak Test (CLT)
The cuff leak test evaluates the mucosal clearance space between the outer circumference of the endotracheal tube and the non-distensible cricoid cartilage ring (the narrowest functional anatomical boundary of the pediatric upper airway).
flowchart LR
    A["Suction Oropharynx & Trachea Thoroughly"] --> B["Deflate ETT Cuff Completely"]
    B --> C["Qualitative Method:<br/>Auscultate Larynx while slowly increasing<br/>circuit pressure to 20–25 cmH2O"]
    B --> D["Quantitative Method:<br/>Measure Inspiratory Vt vs Expiratory Vt on<br/>ventilator: Leak Volume = (Vti - Vte) / Vti"]

    C --> E{"Audible Air Escapement<br/>at Ppeak ≤ 20–25 cmH2O?"}
    D --> F{"Leak Volume > 10–15%?"}

    E & F -- "Yes" --> G["Pass: Low Laryngeal Edema Risk"]
    E & F -- "No" --> H["Fail: Significant Subglottic Edema Detected"]
Diagnostic Thresholds
- Qualitative Cuff Leak:
- Deflate cuff completely.
- Occlude ETT connector or deliver volume breath; listen with a stethoscope over the thyroid/cricoid cartilage.
- Normal: Audible air leak around the tube at peak airway pressures $\le 20 - 25\text{ cmH}_2\text{O}$.
- Failed: No leak audible at pressures $> 25 - 30\text{ cmH}_2\text{O}$, indicating circumferential subglottic mucosal compression.
- Quantitative Cuff Leak Volume:
$$\text{Cuff Leak Fraction } (\%) = \frac{V_{T,\text{insp}} - V_{T,\text{exp}}}{V_{T,\text{insp}}} \times 100$$
- Target: $\text{Leak Volume} > 10\% - 15\%$ (or $> 0.5 - 1.0\text{ mL/kg}$).
- High Risk: Leak fraction $< 10\%$, correlating with a high probability of severe post-extubation stridor.
Corticosteroids reduce laryngeal edema through genomic suppression of microvascular permeability and inflammatory cytokines. This cellular process requires protein synthesis and gene transcription; therefore, a single dose administered minutes prior to extubation is ineffective. Corticosteroids must be initiated 12 to 24 hours (minimum 4 to 6 doses Q6H) prior to extubation to achieve clinical benefit.
Comprehensive Post-Extubation Stridor Prophylaxis & Management
graph TD
    subgraph Stratification["Risk Stratification for Post-Extubation Failure"]
        R1["High-Risk Features:<br/>• Intubation duration > 48–72 hours<br/>• Age < 2 years (small subglottic caliber)<br/>• Failed Cuff Leak Test<br/>• Repeated / Traumatic Intubations<br/>• Underlying upper airway anomalies (Trisomy 21, Pierre Robin)"]
    end

    Stratification --> Prevention["Prevention Bundle"]

    subgraph Prevention["Multimodal Prevention & Rescue Pathway"]
        P1["IV Dexamethasone (0.5 mg/kg Q6H × 4–6 doses, max 10 mg/dose)"]
        P2["Prophylactic High-Flow Nasal Cannula (HFNC 1.5–2.0 L/kg/min)<br/>or Non-Invasive Positive Pressure Ventilation (NIV / CPAP)"]
        P3["Post-Extubation Stridor Rescue:<br/>• Nebulized Racemic Epinephrine (2.25%, 0.5 mL in 3 mL NS)<br/>  or L-Epinephrine 1:1000 (0.5 mg/kg, max 5 mg)<br/>• Heliox (70:30 or 80:20 Helium-Oxygen mixture)"]
    end
| Intervention | Mechanism of Action | Pediatric Dosing & Delivery | Clinical Indications & Nuances |
|---|---|---|---|
| Systemic Dexamethasone | Downregulates inflammatory capillary leak and subglottic tissue edema | $0.5\text{ mg/kg/dose IV}$ (max $10\text{ mg}$) every 6 hours for $4 - 6\text{ doses}$ | High-risk airway, absent cuff leak, prolonged intubation ($> 48\text{ h}$). |
| Nebulized Epinephrine | $\alpha_1$-adrenergic vasoconstriction of mucosal arterioles shrinking edema | Racemic epinephrine 2.25%: $0.5\text{ mL}$ in $3\text{ mL}$ normal saline, or L-epinephrine $1:1000$: $0.5\text{ mg/kg}$ (max $5\text{ mg}$) | Acute post-extubation stridor at rest. Observe for rebound edema after $60-90\text{ minutes}$. |
| Heliox Therapy | Low-density gas mixture ($\text{He:O}_2\ 70:30\text{ or }80:20$) converts turbulent upper airway flow to laminar | Delivered via non-rebreather mask or heated high-flow circuit | Severe stridor with impending fatigue; ineffective if $\text{FiO}_2 > 0.40$ required. |
| Prophylactic HFNC / NIV | Delivers positive pharyngeal distending pressure, stenting upper airway and maintaining FRC | HFNC: $1.5 - 2.0\text{ L/kg/min}$ (max $50-60\text{ L/min}$) NIV/CPAP: $5 - 8\text{ cmH}_2\text{O}$ | Extubated infants $< 1\text{ year}$, cardiac surgery, neuromuscular disease, high pre-extubation $WOB$. |
While prophylactic non-invasive ventilation (NIV/CPAP/HFNC) successfully prevents extubation failure in high-risk children, using NIV as a "rescue" for a child in frank extubation failure with severe exhaustion, lethargy, or worsening respiratory acidosis carries high mortality. If acute post-extubation failure does not improve within $30 - 60\text{ minutes}$ of non-invasive support, prompt, controlled reintubation by an expert airway team is mandatory.
High-Yield Clinical Algorithm & Decision Matrix
graph TD
    A["Daily Liberation Rounds"] --> B{"Screening Checklist Passed?"}
    B -- "No" --> A
    B -- "Yes" --> C["Perform 30–60 min SBT (CPAP 5 or PS 5–8 / PEEP 5)"]

    C --> D{"SBT Failure Criteria?"}
    D -- "Tachypnea / Acidosis / Distress" --> E["Trial Failed: Return to AC/SIMV<br/>Evaluate Cause (Diaphragm POCUS, Secretions)"]
    D -- "Comfortable, Stable ABG & Vitals" --> F["SBT Passed: Assess Airway Patency"]

    F --> G{"Cuff Leak Test & Secretion Clearance"}
    G -- "Absent Leak / High Risk" --> H["Initiate Dexamethasone Bundle (12–24h)<br/>Schedule Planned Extubation to HFNC/NIV"]
    G -- "Present Leak & Intact Reflexes" --> I["Direct Extubation to Age-Appropriate O2/HFNC"]

    H & I --> J{"Post-Extubation Surveillance (First 48 Hours)"}
    J -- "Stable RR, Clear Breath Sounds, Warm Perfusion" --> K["Successful Liberation Achieved"]
    J -- "Stridor at Rest" --> L["Nebulized Racemic Epinephrine<br/>Escalate to Heliox / CPAP"]
    L --> M{"Rapid Resolution within 30–60 min?"}
    M -- "Yes" --> K
    M -- "No / Severe Distress" --> N["Controlled Urgent Reintubation with Video Laryngoscopy"]
Practical Clinical Pearls & Bedside Rules
- The 30-Minute Rule: In pediatric patients passing readiness criteria, a 30-minute SBT provides equal diagnostic accuracy to a 120-minute trial without fatiguing pediatric respiratory muscles.
- Small ETT Resistance Compensation: In infants with small ETTs ($ID \le 3.5\text{ mm}$), always provide modest pressure support ($PS 5-8\text{ cmH}_2\text{O}$) during the trial to neutralize the artificial $WOB_{imp}$.
- Post-Operative Cardiac Extubation: Children following open-heart surgery with cardiopulmonary bypass are at high risk for unilateral phrenic nerve palsy. Perform bedside diaphragm ultrasound to verify bilateral excursion before extubation.
- Steroid Timing Matters: Never rely on a single dose of IV dexamethasone given immediately before extubation. Effective prevention of post-extubation subglottic edema requires starting steroids $12-24\text{ hours}$ in advance.
- Reintubation Preparedness: Always keep a full assortment of emergency airway equipment, including an ETT one half-size smaller than the currently placed tube, a stylet, and video laryngoscopy immediately at the bedside during every pediatric extubation.
Key Takeaways & Summary
- Protocolized Daily Screening: Standardized daily assessment of respiratory mechanics ($P/F \ge 200-250$, $OI \le 4-5$, $\text{PEEP} \le 5-6\text{ cmH}_2\text{O}$), hemodynamic stability, and neurological responsiveness significantly shortens PICU duration of mechanical ventilation.
- SBT Rigor: A 30- to 60-minute SBT on low-level PS or CPAP represents the gold-standard bedside readiness challenge.
- POCUS Integration: Diaphragm ultrasound provides an objective physiological window into respiratory muscle pump function ($\text{DTF} > 25-35\%$, $\text{DE} > 4-8\text{ mm}$ in infants).
- Subglottic Patency Protection: Quantitative cuff leak evaluation identifying leak volumes $< 10-15\%$ flags children who benefit from a 12- to 24-hour course of intravenous dexamethasone.
- Proactive Support: High-risk pediatric cohorts (infants, cardiac surgery, neuromuscular disease) should transition seamlessly from the ETT to prophylactic non-invasive respiratory support (HFNC or NIV) to ensure sustained liberation success.