During refractory Pediatric Acute Respiratory Distress Syndrome (PARDS) and life-threatening hypoxemic or hypercapnic respiratory failure unresponsive to maximal conventional and advanced ventilatory strategies (including prone positioning, high-frequency oscillatory ventilation [HFOV], and neuromuscular blockade), Extracorporeal Membrane Oxygenation (ECMO) serves as an advanced mechanical rescue modality. Once extracorporeal life support is instituted, the primary therapeutic objective of invasive mechanical ventilation undergoes an essential paradigm shift: from serving as the primary gas exchanger to executing ultra-protective "lung rest" ventilation.
Rest ventilation completely dissociates systemic gas exchange from pulmonary mechanical strain, abolishing the cyclic mechanical power ($\text{MP}$), volutrauma, barotrauma, and atelectrauma that drive ventilator-induced lung injury (VILI), thereby permitting biological parenchymal repair and resolution of pulmonary vascular hypertension.
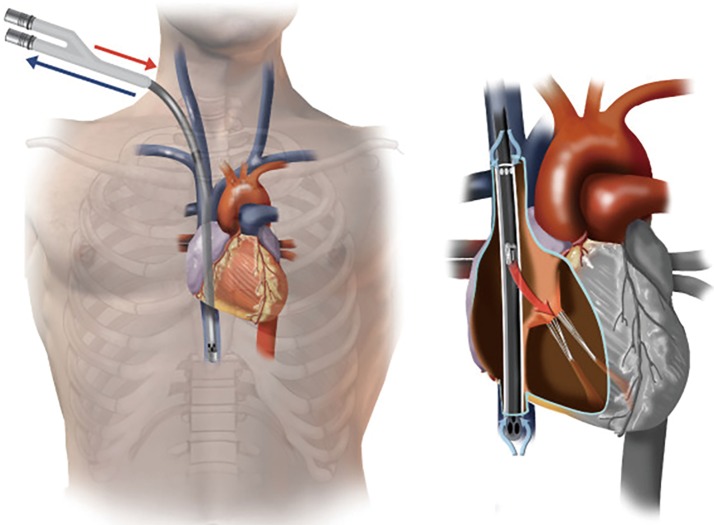 Figure 1: Anatomical and physiological configuration of veno-venous extracorporeal membrane oxygenation (VV-ECMO) utilizing a bicaval dual-lumen catheter (Avalon Elite) inserted via the right internal jugular vein. Blue arrows delineate systemic venous drainage from the superior vena cava (proximal drainage basket) and inferior vena cava (distal drainage basket). Red arrow demonstrates the central reinfusion jet within the mid-right atrium directed specifically toward the tricuspid valve orifice, maximizing forward delivery of oxygenated blood to the pulmonary circulation while eliminating recirculation. Source: Ngai CW, Ng PY, Sin WC. J Thorac Dis. 2018;10(Suppl 5):S624–S628. DOI:
10.21037/jtd.2018.02.70
. PMCID: PMC5911548.
Extracorporeal Life Support in Pediatric Respiratory Failure
ELSO Guidelines & PALICC-2 Indications for ECMO Initiation
The Pediatric Acute Lung Injury Consensus Conference (PALICC-2) and the Extracorporeal Life Support Organization (ELSO) establish strict physiological and prognostic criteria for identifying pediatric patients who will derive a survival benefit from ECMO before irreversible multi-organ dysfunction or terminal ventilator-induced parenchymal disruption ensues.
flowchart TD
    A["Severe PARDS on Optimized Conventional Ventilation\n(Invasive MV + PEEP Titration + Prone Positioning +/- NMB)"] --> B{"Evaluate Severity Metrics\n(OI, OSI, pH, PaCO2)"}

    B -->|"OI >= 40 for >= 4h\nor OI >= 25 for 12-24h"| C["Severe Refractory Hypoxemia"]
    B -->|"pH < 7.15 with PaCO2 > 80 mmHg\nPIP > 35 or Delta P > 15 cmH2O"| D["Severe Uncompensated Respiratory Acidosis"]
    B -->|"Intractable Bronchopleural Fistula\nor Massive Air Leak Syndrome"| E["Refractory Barotrauma / Air Leak"]

    C --> F{"Hemodynamic Assessment\n(Echocardiography & Inotrope Score)"}
    D --> F
    E --> F

    F -->|"Isolated Respiratory Failure\nPreserved Biventricular Function"| G["Veno-Venous (VV) ECMO\n(Dual-Lumen IJ or Two-Site Fem-IJ)"]
    F -->|"Concurrent Septic Shock, Cardiogenic Shock,\nor Severe Refractory RV Failure"| H["Veno-Arterial (VA) ECMO\n(Carotid-IJ or Femoral-Femoral)"]
The decision to cannulate is guided by indices of refractory gas exchange impairment and oxygenation kinetics:
- Severe Refractory Hypoxemia:
- Oxygenation Index ($\text{OI}$) $\ge 40$ sustained for $\ge 4\text{ hours}$, or $\text{OI} \ge 25-30$ sustained for $12-24\text{ hours}$ despite optimal rescue interventions (prone positioning, neuromuscular blockade, inhaled nitric oxide [iNO], or recruitment maneuvers).
- In non-invasive arterial monitoring contexts, Oxygen Saturation Index ($\text{OSI}$) $\ge 20-22$ for $\ge 4\text{ hours}$.
- Severe Uncompensated Hypercapnic Acidosis:
- Arterial $\text{pH} < 7.15$ with $\text{PaCO}_2 > 80-100\text{ mmHg}$ resulting from severe alveolar dead space fraction ($V_D/V_T > 0.65-0.75$), where ongoing attempts to normalize ventilation require dangerous driving pressures ($\Delta P > 15-18\text{ cmH}_2\text{O}$) or peak inspiratory pressures ($P_{\text{peak}} > 35-40\text{ cmH}_2\text{O}$).
- Refractory Air Leak Syndromes:
- Massive, uncontained bronchopleural fistulae, tension pneumomediastinum, or severe subcutaneous emphysema where high airway pressures perpetuate catastrophic air loss, loss of lung volume, and severe hypoventilation.
- Bridge to Lung Transplantation or Specific Mechanical Intervention:
- End-stage pulmonary fibrosis, irreversible alveolar capillary dysplasia (ACD), or surfactant protein deficiencies awaiting evaluation or donor organ availability.
Where $\bar{P}_{\text{aw}}$ is mean airway pressure ($\text{cmH}_2\text{O}$), $\text{FiO}_2$ is expressed as a fraction ($0.21 - 1.0$), and $\text{PaO}_2$ is in $\text{mmHg}$. In pediatric cohorts, an $\text{OI} \ge 40$ is historically associated with $> 80\%$ predicted mortality with medical management alone, establishing the definitive threshold for extracorporeal life support deployment.
Cannulation Configurations: Veno-Venous vs. Veno-Arterial ECMO
| Feature / Metric | Veno-Venous (VV) ECMO | Veno-Arterial (VA) ECMO |
|---|---|---|
| Primary Indication | Isolated severe respiratory failure (PARDS, viral pneumonia, status asthmaticus) with preserved myocardial performance | Combined severe respiratory failure and refractory septic shock, cardiogenic shock, cardiac arrest (E-CPR), or primary pulmonary hypertension with acute right ventricular failure |
| Cannulation Strategy | Single-site Bicaval Dual-Lumen Cannula (e.g., Avalon Elite 13–31 Fr) in right internal jugular vein, OR two-site cannulation (Right IJ drainage + Femoral vein return, or Femoral vein drainage + Right IJ return) | Right internal jugular vein (drainage) + Right common carotid artery (return) in neonates/infants; Femoral vein (drainage) + Femoral artery (return) in older children/adolescents |
| Hemodynamic Support | None directly (relies entirely on native cardiac output); decreases RV afterload secondarily via correction of hypoxic pulmonary vasoconstriction and hypercapnic acidosis | Complete systemic hemodynamic and circulatory support (replaces native left and right ventricular stroke work) |
| Pulmonary Perfusion | Native pulmonary blood flow receives fully oxygenated, decarboxylated extracorporeal blood; pulmonary artery carries high $\text{SaO}_2$ ($> 85-90\%$) | Pulmonary blood flow is significantly reduced due to systemic arterial bypass; potential risk of pulmonary vascular stasis and intracardiac thrombosis if LV ejection is absent |
| Coronary & Cerebral Oxygenation | Uniformly oxygenated blood throughout systemic arterial tree determined by membrane output and native shunt | Differential hypoxemia ("Harlequin syndrome" / North-South syndrome) risk if native cardiac output recovers while native lung gas exchange remains severely impaired |
| Vascular Morbidity | Sparing of arterial system; carotid artery ligation avoided | Requires arterial cannulation; risks include limb ischemia (requiring distal perfusion cannula in femoral access) and stroke/neurological injury |
"Rest" Lung Ventilation Mechanics & Ergotrauma Abolition
Physical Elimination of Dynamic Mechanical Power ($\text{MP}$) and Biotrauma
Mechanical ventilation delivers energy to the lung parenchyma during each inflation cycle. When this energy exceeds the tissue's physical dissipation capacity, mechanical power induces microstructural disruption of alveolar-capillary membranes, alveolar rupture, extracellular matrix degradation, and intense pro-inflammatory mediator release (biotrauma).
flowchart LR
    subgraph Damaging High-Power Conventional MV
        D1["High Driving Pressure (Delta P > 15)"] & D2["High Respiratory Rate (RR > 30)"] & D3["High Peak Pressure (PIP > 35)"] --> MP1["Massive Mechanical Power (> 25 J/min)\nCyclic Volutrauma + Atelectrauma"]
        MP1 --> BIO1["Cytokine Storm (IL-6, IL-8, TNF-a)\nMicrovascular Leak & Fibroproliferation"]
    end

    subgraph Ultra-Protective Rest Ventilation on ECMO
        R1["Low Driving Pressure (Delta P <= 10)"] & R2["Low Respiratory Rate (RR 6-10)"] & R3["Moderate PEEP (8-12 cmH2O)"] --> MP2["Minimal Mechanical Power (< 2-5 J/min)\nComplete Dynamic Stress Abolition"]
        MP2 --> BIO2["Parenchymal Quiescence\nEndothelial Re-endothelialization & Alveolar Healing"]
    end
The mechanical power ($\text{MP}$) transmitted to the pediatric lung during volume- or pressure-controlled ventilation is derived from the simplified Gattinoni equation:
$$\text{MP} = 0.098 \times \text{RR} \times V_T \times \left( P_{\text{peak}} - \frac{1}{2}\Delta P \right) \quad [\text{J/min}]$$Or expressed in terms of driving pressure ($\Delta P$) and dynamic elastance ($E_{\text{rs}}$):
$$\text{MP} = 0.098 \times \text{RR} \times \left( \frac{1}{2} E_{\text{rs}} \cdot V_T^2 + \text{PEEP} \cdot V_T + R_{\text{aw}} \cdot \dot{V}_{\text{insp}} \cdot V_T \right)$$Under ECMO rest conditions, by reducing the respiratory rate ($\text{RR}$) from $30-40\text{ bpm}$ to $6-10\text{ bpm}$, reducing $V_T$ from $6-8\text{ mL/kg}$ to $2-3\text{ mL/kg}$, and minimizing $\Delta P \le 10\text{ cmH}_2\text{O}$, total mechanical power is decreased by $> 85-90\%$, effectively eradicating physical ergotrauma.
Rest Ventilator Parameter Matrix
Following full establishment of ECMO blood flow and sweep gas delivery, the mechanical ventilator is transitioned immediately to ultra-protective rest parameters.
| Ventilator Setting | Rest Ventilation Target | Physiological Objective & Bedside Rationale |
|---|---|---|
| Ventilation Mode | Pressure-Controlled Continuous Mandatory Ventilation (PC-CMV) or APRV (with low $P_{\text{high}}$) | Decelerating flow profile minimizes peak alveolar shear stresses; guarantees fixed, unyielding pressure limits without volume overshooting. |
| Peak Inspiratory Pressure ($P_{\text{insp}}$ / PIP) | $20 - 25\text{ cmH}_2\text{O}$ | Absolute ceiling to eliminate barotrauma and prevent alveolar overdistension in heterogeneous "baby lung" regions. |
| Driving Pressure ($\Delta P = \text{PIP} - \text{PEEP}$) | $\le 10 - 12\text{ cmH}_2\text{O}$ | Minimizes cyclic parenchymal strain ($\epsilon = V_T / \text{FRC}$); abolishes dynamic tissue shear forces. |
| Positive End-Expiratory Pressure (PEEP) | $8 - 12\text{ cmH}_2\text{O}$ (up to $14\text{ cmH}_2\text{O}$ in severe obesity or stiff chest wall) | Critical anti-atelectasis stent: maintains Functional Residual Capacity (FRC) and prevents cyclic end-expiratory alveolar collapse and secondary consolidation. |
| Tidal Volume ($V_T$) | $2 - 4\text{ mL/kg}$ PBW (or near-zero in severe parenchymal destruction) | Complete abolition of volutrauma; alveolar gas movement is secondary, as extracorporeal circuit conducts total minute ventilation. |
| Respiratory Rate (RR) | $6 - 10\text{ breaths/min}$ | Minimizes cyclic frequency factor in mechanical power equation; extends expiratory duration preventing dynamic hyperinflation. |
| Inspiratory Time ($T_{\text{insp}}$) | $1.0 - 1.5\text{ seconds}$ (or $I:E$ ratio $1:1$ to $1:1.5$) | Promotes slow, homogenous alveolar recruitment across high time-constant lung units without elevating peak pressures. |
| Inspired Oxygen Fraction ($\text{FiO}_2$) | $0.30 - 0.40$ (rarely up to $0.50$) | Rapidly de-escalated to eliminate hyperoxic pulmonary vasoconstriction, absorption atelectasis, and reactive oxygen species (ROS) mediated alveolar cytotoxicity. |
Completely discontinuing PEEP ($\text{PEEP} = 0$) or disconnecting the airway during acute ECMO support precipitates immediate, irreversible compressive and absorption atelectasis, resulting in catastrophic "white out" of both lung fields, severe pulmonary vascular constriction, intra-alveolar fibrin deposition, and prolonged duration of extracorporeal support. PEEP must be rigorously maintained at $8-12\text{ cmH}_2\text{O}$ to preserve alveolar scaffolding.
Extracorporeal Mass Transfer: Sweep Gas vs. Blood Flow Physics
flowchart TD
    subgraph Extracorporeal Membrane Oxygenator
        BF["Extracorporeal Blood Flow (Q_ecmo)\n60-100 mL/kg/min (VV)\n30-80 mL/kg/min (VA)"] -->|Determines Oxygen Delivery| O2["Oxygenation (PaO2 / SaO2)\nControlled by: Q_ecmo + Membrane FiO2\n(Limited by Hemoglobin Binding & Henry's Law)"]

        SG["Sweep Gas Flow Rate (V_sweep)\n0.5 to 2.0 x Q_ecmo (L/min)"] -->|Determines CO2 Elimination| CO2["Decarboxylation (PaCO2)\nControlled by: Sweep Gas Velocity & Gradient\n(Highly Soluble Gas, Perfusion-Independent Diffusion)"]
    end
The membrane oxygenator functions as an artificial alveolar-capillary barrier consisting of polymethylpentene (PMP) hollow-fiber membranes. The transfer kinetics of oxygen and carbon dioxide are fundamentally decoupled:
1. Extracorporeal Oxygenation ($VO_2$)
Oxygen transfer across the membrane oxygenator is governed by the total extracorporeal blood flow rate ($Q_{\text{ecmo}}$) and the inlet-outlet oxyhemoglobin saturation differential:
$$VO_{2,\text{ecmo}} = Q_{\text{ecmo}} \times 1.34 \times [\text{Hb}] \times \left( S_{\text{post}}\text{O}_2 - S_{\text{pre}}\text{O}_2 \right) + Q_{\text{ecmo}} \times 0.0031 \times \left( P_{\text{post}}\text{O}_2 - P_{\text{pre}}\text{O}_2 \right)$$Because oxygen has low solubility in aqueous plasma ($0.0031\text{ mL O}_2/\text{dL}/\text{mmHg}$), transferring sufficient oxygen requires high blood flow rates ($60 - 100\text{ mL/kg/min}$ in pediatric VV-ECMO, up to $100-150\text{ mL/kg/min}$ in neonates) to satisfy total systemic metabolic oxygen consumption ($VO_2 \approx 4-6\text{ mL/kg/min}$). Membrane $\text{FiO}_2$ is maintained between $0.80 - 1.0$.
2. Extracorporeal Carbon Dioxide Removal ($VCO_2$)
Carbon dioxide is $> 20\text{ times}$ more soluble than oxygen in blood and tissue. Consequently, $\text{CO}_2$ transfer across the PMP membrane is diffusion-gradient limited rather than blood-flow limited:
$$VCO_{2,\text{ecmo}} \propto \dot{V}_{\text{sweep}} \times \left( \frac{P_{\text{pre}}\text{CO}_2 - P_{\text{sweep,in}}\text{CO}_2}{\text{Membrane Resistance}} \right)$$Adjusting the Sweep Gas Flow Rate ($\dot{V}_{\text{sweep}}$, measured in $\text{L/min}$) regulates the partial pressure gradient across the hollow fibers:
- Increasing sweep gas flow flushes $\text{CO}_2$ out of the gas compartment, maximizing the trans-membrane $\text{PCO}_2$ gradient and accelerating $\text{CO}_2$ clearance.
- Decreasing sweep gas flow permits $\text{CO}_2$ accumulation in the sweep lumen, narrowing the gradient and elevating systemic $\text{PaCO}_2$.
Rapid clearance of chronic or severe hypercapnia immediately post-cannulation drops $\text{PaCO}_2$ precipitously ($> 20-30\text{ mmHg/hour}$), inducing profound cerebral vasoconstriction, severe reductions in cerebral blood flow, and intracranial hemorrhage or ischemic stroke. Sweep gas must be titrated cautiously to decrease $\text{PaCO}_2$ by no more than $5-10\text{ mmHg/hour}$, maintaining post-membrane $\text{PaCO}_2 \ge 35-40\text{ mmHg}$.
Lung Recovery Assessment & Decannulation Weaning
Physiological Indices of Native Parenchymal Healing
Throughout the duration of rest ventilation, daily serial assessments of native pulmonary mechanics and gas exchange are conducted to detect parenchymal recovery:
- Static Respiratory System Compliance ($C_{\text{stat}}$): $$C_{\text{stat}} = \frac{V_T}{P_{\text{plat}} - \text{PEEP}}$$ During rest ventilation, compliance initially measures $< 0.3 - 0.5\text{ mL/cmH}_2\text{O/kg}$. As alveolar inflammation and edema resolve, tidal volume generation under identical rest pressures ($P_{\text{insp}} 22\text{ cmH}_2\text{O}$) progressively increases from $< 2\text{ mL/kg}$ to $> 5-6\text{ mL/kg}$ ($C_{\text{stat}} > 0.8 - 1.0\text{ mL/cmH}_2\text{O/kg}$).
- Radiographic and Ultrasonographic Clearing:
- Resolution of bilateral dependent consolidations and ground-glass opacities on chest radiography.
- Lung Ultrasound: Transition from confluent B-lines and subpleural consolidations (Lung Ultrasound Score $> 18-24$) to re-aeration patterns with distinct A-lines and normal pleural sliding (Score $< 6-8$).
- Reduction in Native Transpulmonary Shunt Fraction ($Q_s/Q_t$):
- Progressive elevation of native arterial $\text{PaO}_2$ and $\text{SaO}_2$ at stable or diminishing extracorporeal blood flows and membrane $\text{FiO}_2 \le 0.50$.
Stepwise Decannulation Protocol: The Sweep Gas Challenge
Weaning from VV-ECMO differs fundamentally from VA-ECMO. In VV-ECMO, pump blood flow remains high to prevent circuit thrombosis, while the membrane's gas exchange contribution is systematically eliminated by shutting off the sweep gas.
flowchart TD
    W1["Native Lung Recovery Criteria Met:\n- Cstat >= 0.8-1.0 mL/kg/cmH2O\n- Rest VT >= 5-6 mL/kg at Pinsp <= 25\n- CXR / LUS Significant Aeration\n- Hemodynamically Stable"] --> W2["Step 1: Optimize Native Ventilator to Moderate Lung-Protective Settings:\n- PC or VC Mode: VT 5-7 mL/kg\n- PEEP 8-10 cmH2O\n- Ventilator FiO2 <= 0.50\n- RR Age-appropriate (16-24 bpm)"]

    W2 --> W3["Step 2: Initiate Sweep Gas Weaning:\n- Titrate Sweep Gas Flow down to 0 L/min\n- Maintain Extracorporeal Blood Flow at 100% (prevent circuit stasis)\n- Set Membrane FiO2 to 0.21 (Room Air)"]

    W3 --> W4["Step 3: Sweep Gas Challenge (Observation for 4 to 24 Hours):\n- Serial ABG at 30 min, 2h, 4h, 12h\n- Continuous SpO2, EtCO2, and Hemodynamic Monitoring"]

    W4 --> W5{"Sweep Gas Challenge Validation:\n- pH >= 7.35\n- PaCO2 35-48 mmHg\n- PaO2 >= 70-80 mmHg (SpO2 >= 92%)\n- FiO2 <= 0.50, Delta P <= 14 cmH2O"}

    W5 -->|"Passed Trial"| W6["Proceed to Surgical / Percutaneous Decannulation\nMaintain Systemic Anticoagulation until Clamp"]
    W5 -->|"Failed Trial (Hypoxemia / Severe Acidosis)"| W7["Resume Extracorporeal Sweep Gas\nReturn Ventilator to Ultra-Protective Rest Settings\nReassess in 24-48 Hours"]
During the final weaning phase on VV-ECMO, do NOT decrease the blood pump flow rate below $30-50\text{ mL/kg/min}$ (or $< 1.0-1.5\text{ L/min}$ in adolescents), as low blood velocities across the oxygenator fiber bundle induce boundary-layer stasis and acute circuit thrombosis. Instead, keep pump flow at baseline ($100\%$) and disconnect or set sweep gas to $0\text{ L/min}$ with membrane $\text{FiO}_2 = 0.21$. In this state, the ECMO circuit acts merely as an extracorporeal arteriovenous/venovenous shunt with zero gas exchange, forcing native lungs to sustain $100\%$ of metabolic $VO_2$ and $VCO_2$.
Anticoagulation Management & Post-Decannulation Care
Anticoagulation Targets during Rest Ventilation and Decannulation
Extracorporeal circuit surfaces trigger the contact activation pathway (Factor XII) and platelet activation. Rigorous systemic anticoagulation is balanced against bleeding risks:
| Anticoagulant Agent | Mechanism of Action | Monitoring Assay | Target Range (Standard) | High Bleeding Risk Target |
|---|---|---|---|---|
| Unfractionated Heparin (UFH) | Potentiates Antithrombin III; inhibits Thrombin (IIa) and Factor Xa | Anti-Factor Xa (Gold standard) Activated Partial Thromboplastin Time (aPTT) Activated Clotting Time (ACT) | Anti-Xa: $0.3 - 0.7\text{ IU/mL}$ aPTT: $60 - 85\text{ seconds}$ ACT: $180 - 210\text{ seconds}$ | Anti-Xa: $0.2 - 0.4\text{ IU/mL}$ aPTT: $45 - 60\text{ seconds}$ ACT: $160 - 180\text{ seconds}$ |
| Bivalirudin | Direct Thrombin Inhibitor (DTI); unhindered by AT-III deficiency or Heparin-Induced Thrombocytopenia (HIT) | aPTT Dilute Thrombin Time (dTT) Ecarin Clotting Time (ECT) | aPTT: $60 - 85\text{ seconds}$ dTT: $60 - 90\text{ seconds}$ | aPTT: $50 - 65\text{ seconds}$ |
- Fasting & Gastric Decompression: Confirm enteral nutrition held for $\ge 4-6\text{ hours}$; aspirate nasogastric/orogastric tube.
- Neuromuscular Blockade & Sedation: Administer short-acting neuromuscular blockade (e.g., rocuronium $0.6-1.0\text{ mg/kg}$) during cannula withdrawal to prevent spontaneous inspiratory efforts generating catastrophic negative intrathoracic venous pressure and venous air embolism.
- Heparin Discontinuation: Discontinue systemic heparin infusion $2-4\text{ hours}$ prior to open surgical vascular decannulation (or immediately prior to percutaneous decannulation with purse-string vessel closure).
- Post-Decannulation Vascular Surveillance: Execute Doppler ultrasound within $24\text{ hours}$ to screen for internal jugular or femoral venous occlusive thrombosis.
Post-ECMO Mechanical Ventilation Strategy
Following decannulation, lungs remain vulnerable to secondary VILI. Patients must not be exposed to excessive mechanical power:
- Maintain Lung-Protective Ventilation:
- Transition to Volume-Controlled or Pressure-Controlled ventilation targeting physiological tidal volumes: $V_T = 5 - 7\text{ mL/kg}$ PBW.
- Restrict plateau pressure $P_{\text{plat}} \le 28\text{ cmH}_2\text{O}$ and driving pressure $\Delta P \le 12 - 14\text{ cmH}_2\text{O}$.
- Maintain moderate PEEP ($6 - 10\text{ cmH}_2\text{O}$) matched to regional closing pressures.
- Early Spontaneous Breathing and Sedation Lightening:
- Rapidly taper continuous neuromuscular infusions.
- Transition to assisted modes (Pressure Support Ventilation [PSV] or Neurally Adjusted Ventilatory Assist [NAVA]) as soon as respiratory drive stabilizes, promoting diaphragmatic conditioning and preventing critical illness myopathy.
- Aggressive Pulmonary Toilet & Secretion Clearance:
- Institution of in-line suctioning, chest physiotherapy, therapeutic bronchoscopy (if lobar atelectasis persists from retained mucopurulent plugs), and early mobilization protocols.
Clinical Summary & Bedside Action Plan
flowchart LR
    subgraph 1. Initiation
        I1["Refractory PARDS\nOI >= 40 or pH < 7.15"] --> I2["Cannulate VV (or VA)\nEstablish Full ECLS Flow"]
    end

    subgraph 2. Rest Ventilation
        I2 --> R1["Drop PIP to 20-25 cmH2O\nPEEP 8-12 cmH2O\nRR 6-10 bpm, FiO2 0.3-0.4\nSweep Gas titrates PaCO2"]
    end

    subgraph 3. Healing & Weaning
        R1 --> W1["Serial Compliance Check\nCstat > 0.8-1.0 mL/kg/cmH2O\nSweep Gas Challenge (0 L/min)"]
    end

    subgraph 4. Decannulation
        W1 --> D1["Validate ABG on Mild Settings\nParalyze during Pull\nPost-ECMO Protective MV"]
    end
- ECMO is a Mechanical Bridge, Not a Cure: Extracorporeal support provides immediate hemodynamic and gas exchange stabilization, creating the physiological window necessary for parenchymal recovery.
- Rest Ventilation Eliminates Ergotrauma: Lowering driving pressure ($\Delta P \le 10-12\text{ cmH}_2\text{O}$), tidal volume ($V_T 2-4\text{ mL/kg}$), and respiratory rate ($6-10\text{ bpm}$) abolishes the mechanical power driving progressive ventilator-induced lung injury.
- Decoupled Physiology: Adjust extracorporeal blood flow ($Q_{\text{ecmo}}$) for oxygen delivery; adjust sweep gas flow rate ($\dot{V}_{\text{sweep}}$) for carbon dioxide clearance.
- Decannulation Readiness via Sweep Challenge: Confirm parenchymal independence by reducing sweep gas to zero while validating normal arterial blood gas parameters on moderate, lung-protective ventilator settings.