Pediatric critical care mechanical ventilation demands instant bedside pattern recognition, rigorous biomechanical computation, and rapid algorithmic decision-making. Unlike adult ventilation, pediatric respiratory failure spans a spectrum from neonatal lung immaturity and reactive small airways to congenital heart disease physiology and complex neuromuscular weakness.
This monograph provides six exhaustive, graduate-level clinical case vignettes and emergency board spotters simulating acute clinical deterioration, scalar waveform aberrations, and life-saving rescue protocols.
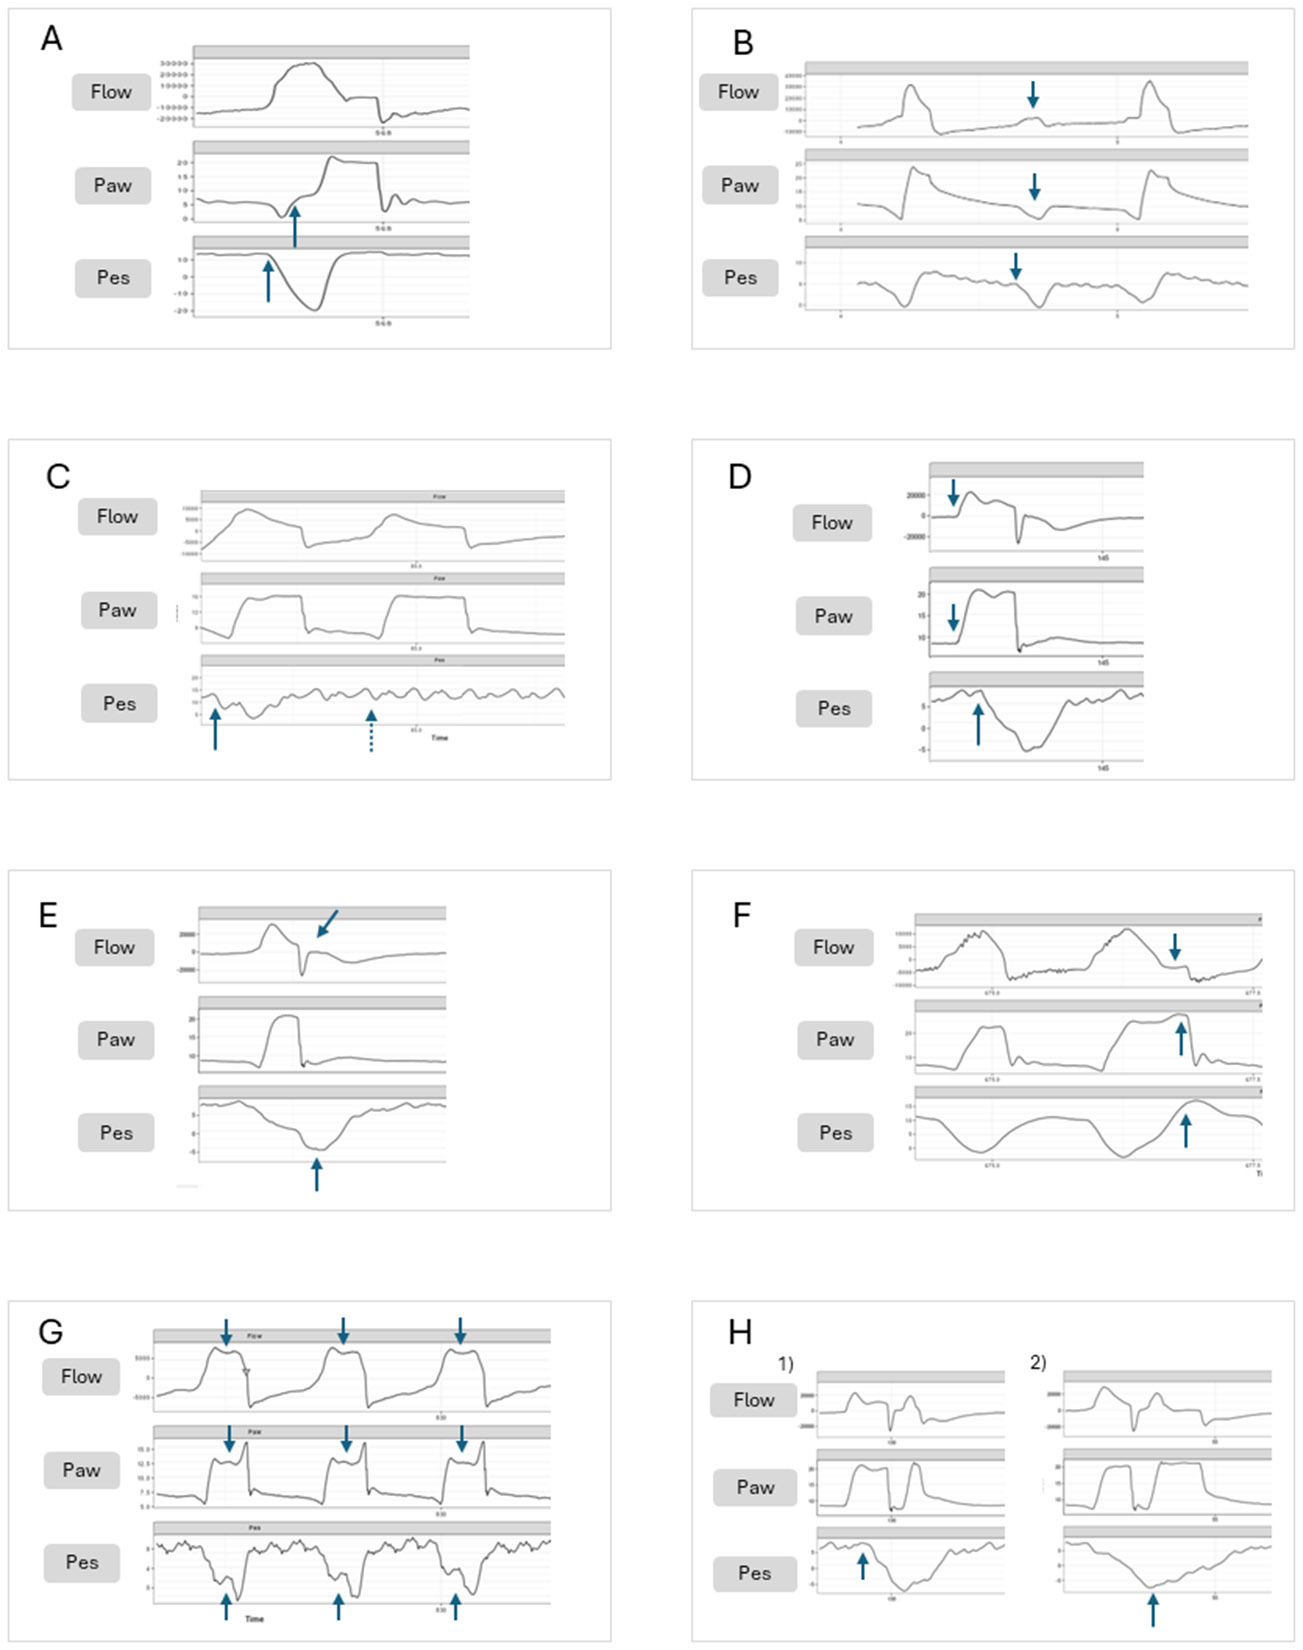 Figure 1: High-resolution scalar analysis of patient-ventilator asynchrony (PVA) and mechanical spotters in pediatric pressure-controlled ventilation. In all panels, the top scalar represents Flow ($\text{L/min}$), the middle scalar represents Airway Pressure ($P_{aw}$, $\text{cmH}_2\text{O}$), and the bottom scalar represents Esophageal Pressure ($P_{es}$, $\text{cmH}_2\text{O}$). Panel A demonstrates Delayed Triggering with an esophageal pressure drop preceding pressurization. Panel B highlights Ineffective Triggering where diaphragmatic effort fails to cycle the valve. Panel C shows Auto-Triggering from circuit leak/cardiac oscillations. Panel D illustrates Reverse Triggering with ventilator-induced diaphragmatic entrainment. Panel E reveals Premature Termination with flow drop and bounce. Panel F illustrates Delayed Termination where patient neural exhalation meets ongoing machine inspiration. Panel G captures severe Flow Undershoot (Flow Starvation) with classical concavity in $P_{aw}$ and a $W$-shaped $P_{es}$ swing. Panel H delineates Double Cycling / Breath Stacking induced by neural overdrive. (Source: Yoon et al., Expert Rev Respir Med, 2025; DOI:
10.1080/17476348.2025.2487165
, PMCID:
PMC12109136
).
Case 1: Severe Viral Bronchiolitis Decompensation
Clinical Presentation & Baseline Mechanics
A 3-month-old infant ($4.2\text{ kg}$) with confirmed Respiratory Syncytial Virus (RSV) and human Metapneumovirus (hMPV) co-infection is admitted to the PICU with severe subcostal retractions, grunting, nasal flaring, and recurrent central apneas. Initial arterial blood gas (ABG) on high-flow nasal cannula ($2\text{ L/kg/min}$, $\text{FiO}_2\ 0.60$) reveals severe respiratory acidosis: $\text{pH } 7.12$, $\text{PaCO}_2\ 78\text{ mmHg}$, $\text{PaO}_2\ 54\text{ mmHg}$, $\text{HCO}_3^-\ 25\text{ mEq/L}$, and base excess $+1\text{ mEq/L}$.
The infant is intubated with a $3.5\text{ mm}$ internal diameter (ID) cuffed endotracheal tube (ETT) and placed on Pressure-Controlled Synchronized Intermittent Mandatory Ventilation (PC-SIMV) with Pressure Support.
flowchart TD
    A["3-Month-Old Infant with RSV/hMPV"] --> B["Severe Small Airway Edema + Mucus Plugs"]
    B --> C["Marked Spatial Heterogeneity of Time Constants (τ = Raw × Crs)"]
    C --> D1["Fast-Filling Units (Low Compliance) -> Cyclic Collapse"]
    C --> D2["Slow-Emptying Units (High Raw) -> Dynamic Hyperinflation & Gas Trapping"]
    D1 --> E["Pneumatic Stenting via PEEP Titration (8-10 cmH2O)"]
    D2 --> F["Extended Expiratory Time (I:E = 1:3) to Clear τ_exp"]
    E & F --> G["Resolution of Flow-Volume Scooping + Stable Alveolar Ventilation"]
Pathophysiological Breakdown
Viral bronchiolitis produces widespread necrosis of bronchiolar ciliated epithelium, peribronchiolar lymphocytic infiltration, and luminal plugging by fibrin and mucus. This generates marked respiratory time-constant heterogeneity:
$$\tau = R_{aw} \times C_{rs}$$Where:
- Units with dense mucus plugging exhibit high airway resistance ($R_{aw}$) and prolonged expiratory time constants ($\tau_{slow} = 0.6\text{--}1.0\text{ s}$), predisposing to dynamic gas trapping and intrinsic PEEP ($\text{PEEP}_i$).
- Surrounding consolidated or micro-atelectatic alveolar regions exhibit reduced compliance ($C_{rs}$) and short time constants ($\tau_{fast} < 0.15\text{ s}$), collapsing during passive expiration.
- Expiratory flow-volume loops reveal characteristic expiratory scooping (coving), where flow plummets immediately post-peak due to dynamic compression of floppy, non-cartilaginous infant small airways.
Setting an inadequate PEEP ($< 5\text{ cmH}_2\text{O}$) worsens peripheral small-airway collapse during expiration. Titrating extrinsic PEEP to $7\text{--}10\text{ cmH}_2\text{O}$ provides a pneumatic stent across downstream bronchioles, matching or slightly exceeding regional closing pressures. This paradoxical maneuver reduces expiratory airway resistance, homogenizes $\tau$, accelerates lung emptying, and decreases trapped gas volume.
Ventilator Intervention & Mechanics Tracking
| Parameter | Pre-Intervention Settings | Post-Titration Rescue Settings | Physiological Rationale |
|---|---|---|---|
| Ventilator Mode | PC-SIMV + PS | PC-CMV (Time-Cycled) | Eliminates high-frequency triggering fatigue during acute phase |
| Inspiratory Pressure ($\Delta P_{insp}$) | $16\text{ cmH}_2\text{O}$ (Peak $21$) | $14\text{ cmH}_2\text{O}$ (Peak $23$) | Maintains tidal volume $6\text{--}7\text{ mL/kg}$ ($26\text{ mL}$) |
| Extrinsic PEEP | $5\text{ cmH}_2\text{O}$ | $9\text{ cmH}_2\text{O}$ | Pneumatic stenting of dynamic bronchiolar collapse |
| Respiratory Rate ($RR$) | $36\text{ breaths/min}$ | $24\text{ breaths/min}$ | Prolongs total cycle time ($T_{tot} = 2.5\text{ s}$) |
| Inspiratory Time ($T_I$) | $0.60\text{ s}$ | $0.50\text{ s}$ | Ensures full inspiratory delivery without stealing from expiration |
| Expiratory Time ($T_E$) | $1.06\text{ s}$ | $2.00\text{ s}$ ($I:E = 1:4$) | Provides $> 3\text{--}4\ \tau_{slow}$ for complete alveolar emptying |
| Auto-PEEP ($\text{PEEP}_i$) | $7.8\text{ cmH}_2\text{O}$ | $1.2\text{ cmH}_2\text{O}$ | Complete release of trapped alveolar gas |
| Follow-up ABG | $\text{pH } 7.14 / \text{PaCO}_2\ 76$ | $\text{pH } 7.34 / \text{PaCO}_2\ 48$ | Normalization of systemic acid-base balance |
Case 2: Acute Pulmonary Hypertensive Crisis Post-VSD Repair
Clinical Presentation & Cardiopulmonary Deterioration
A 6-month-old infant ($6.0\text{ kg}$) with Trisomy 21 undergoes patch closure of a large perimembranous ventricular septal defect (VSD) with severe preoperative hyperkinetic pulmonary arterial hypertension. Four hours postoperatively in the Cardiac PICU, following endotracheal suctioning, the infant develops acute cardiovascular collapse:
- Invasive arterial blood pressure crashes from $82/48\text{ mmHg}$ to $38/20\text{ mmHg}$ (mean $26\text{ mmHg}$).
- Central venous pressure (CVP) surges from $7\text{ mmHg}$ to $22\text{ mmHg}$.
- Pulmonary artery catheter reveals pulmonary artery pressure ($PAP$) equal to systemic arterial pressure ($PAP = 42/24\text{ mmHg}$, systemic $BP = 38/20\text{ mmHg}$).
- ECG monitor demonstrates Junctional Ectopic Tachycardia (JET) at $210\text{ bpm}$.
- Pulse oximetry drops precipitously from $99\%$ to $68\%$.
flowchart TD
    A["Noxious Stimulus (Endotracheal Suctioning)"] --> B["Surge in Sympathetic Tone + Endothelin-1 Release"]
    B --> C["Acute Pulmonary Vasoconstriction -> PVR Surge"]
    C --> D["PAP Exceeds Systemic MAP -> RV Pressure Overload"]
    D --> E["Acute RV Dilation & Ischemia"]
    E --> F["Interventricular Septal Leftward Shift (Reversed Bernheim Effect)"]
    F --> G["Severe LV Cavity Compression -> Precipitous Fall in LV Preload & Cardiac Output"]
    G --> H["Cardiovascular Collapse & Refractory Shock"]
Emergency Pulmonary Vasodilation Resuscitation Ladder
- Abort All Manipulations: Instantly halt suctioning and secure airway.
- Alveolar Hyperoxia: Administer $\text{FiO}_2\ 1.00$ immediately (oxygen is a potent direct precapillary pulmonary vasodilator).
- Induce Mild Respiratory Alkalosis: Hand-ventilate or increase minute ventilation to target $\text{pH } 7.50\text{--}7.55$ and $\text{PaCO}_2\ 30\text{--}35\text{ mmHg}$. Alkalosis directly relaxes pulmonary vascular smooth muscle.
- Selective Pulmonary Vasodilator: Initiate Inhaled Nitric Oxide (iNO) at $20\text{ ppm}$ via ventilator inspiratory limb.
- Analgo-Sedation & Neuromuscular Blockade: Administer IV Fentanyl ($2\ \mu\text{g/kg}$) and Vecuronium ($0.1\text{ mg/kg}$) to abolish endogenous catecholamine surges.
- Inotropic & Lusitropic Support: Maintain RV perfusion pressure with systemic vasopressor (Norepinephrine / Epinephrine) and RV lusitropy with Milrinone ($0.5\ \mu\text{g/kg/min}$).
graph TD
    Step1["1. Oxygenation: 100% FiO2"] --> Step2["2. Targeted Alkalosis: pH 7.50-7.55 / PaCO2 30-35 mmHg"]
    Step2 --> Step3["3. Selective Inhaled Vasodilation: iNO 20 ppm"]
    Step3 --> Step4["4. Deep Neuromuscular Blockade + Opioids"]
    Step4 --> Step5["5. RV Inotropy & Systemic Perfusion: Epinephrine + Milrinone"]
    Step5 --> Step6["6. Refractory: VA-ECMO Cannulation"]
Hemodynamic & Ventilatory Parameter Matrix
| Variable | Baseline PICU Admission | Acute PHT Crisis Peak | Post-Resuscitation (iNO + Alkalosis) |
|---|---|---|---|
| Systemic Arterial BP (MAP) | $58\text{ mmHg}$ | $26\text{ mmHg}$ | $62\text{ mmHg}$ |
| Mean Pulmonary Artery Pressure ($\text{mPAP}$) | $18\text{ mmHg}$ | $34\text{ mmHg}$ | $16\text{ mmHg}$ |
| $\text{mPAP} / \text{MAP}$ Ratio | $0.31$ (Favorable) | $1.31$ (Suprasystemic Crisis) | $0.26$ (Subsystemic) |
| Central Venous Pressure (CVP) | $6\text{ mmHg}$ | $22\text{ mmHg}$ | $8\text{ mmHg}$ |
| Inhaled Nitric Oxide | $0\text{ ppm}$ | $0\text{ ppm}$ | $20\text{ ppm}$ |
| Ventilator Rate / $\text{FiO}_2$ | $26\text{ bpm} / 0.35$ | $26\text{ bpm} / 0.35$ | $34\text{ bpm} / 1.00 \to 0.50$ |
| Arterial Blood Gas | $\text{pH } 7.38 / \text{PaCO}_2\ 39$ | $\text{pH } 7.21 / \text{PaCO}_2\ 56$ | $\text{pH } 7.52 / \text{PaCO}_2\ 32$ |
| Echocardiographic Septal Motion | Normal circular LV cavity | Severe LV D-shaping, flat septum | Restoration of round LV cavity |
Case 3: Severe Refractory PARDS with High Driving Pressure
Clinical Presentation & PALICC-2 Stratification
A 4-year-old child ($16\text{ kg}$) with severe pneumococcal sepsis presents with refractory Pediatric Acute Respiratory Distress Syndrome (PARDS). On Volume-Controlled Ventilation with $V_T = 6\text{ mL/kg}$ ($96\text{ mL}$), $\text{PEEP} = 12\text{ cmH}_2\text{O}$, and $\text{FiO}_2 = 0.90$, arterial blood gas shows:
- $\text{pH } 7.22$, $\text{PaCO}_2\ 58\text{ mmHg}$, $\text{PaO}_2\ 52\text{ mmHg}$, $\text{HCO}_3^-\ 23\text{ mEq/L}$.
- Mean Airway Pressure ($\bar{P}_{aw}$) is $20\text{ cmH}_2\text{O}$.
- Peak Inspiratory Pressure ($PIP$) is $38\text{ cmH}_2\text{O}$; Plateau Pressure ($P_{plat}$) is $34\text{ cmH}_2\text{O}$.
Oxygenation Index & Biomechanical Computation
$$\text{Oxygenation Index (OI)} = \frac{\bar{P}_{aw} \times \text{FiO}_2 \times 100}{\text{PaO}_2} = \frac{20 \times 0.90 \times 100}{52} = 34.6$$$$\text{Driving Pressure (}\Delta P) = P_{plat} - \text{PEEP} = 34 - 12 = 22\text{ cmH}_2\text{O}$$$$\text{Static Respiratory System Compliance (}C_{stat}) = \frac{V_T}{P_{plat} - \text{PEEP}} = \frac{96}{22} = 4.36\text{ mL/cmH}_2\text{O}\ (0.27\text{ mL/cmH}_2\text{O/kg})$$flowchart LR
A["OI = 34.6 (Severe PARDS by PALICC-2)"] --> B["Driving Pressure ΔP = 22 cmH2O (High VILI Risk)"]
B --> C["Step 1: Early Prone Positioning (≥ 16 h/day)"]
C --> D["Step 2: Transpulmonary Pressure (P_L) Titration"]
D --> E{"P_L,exp >= 0 and ΔP <= 15 cmH2O Achieved?"}
E -- Yes --> F["Maintain Ultra-Protective Conventional Ventilation"]
E -- No --> G["Step 3: Rescue High-Frequency Oscillatory Ventilation (HFOV)"]
G --> H{"Refractory Hypoxemia (OI > 40 or pH < 7.15)?"}
H -- Yes --> I["Step 4: Prompt Veno-Venous (VV) ECMO Cannulation"]
Under the PALICC-2 guidelines, severe PARDS on invasive mechanical ventilation is defined by an $OI \ge 16$ or an Oxygen Saturation Index ($OSI$) $\ge 12.3$. An $OI$ of $34.6$ places this patient at extreme risk of mortality, mandating aggressive tier-2 interventions.
Management Steps & Escalation Pathway
- Neuromuscular Blockade: Continuous Cisatracurium infusion ($2\ \mu\text{g/kg/min}$) to eliminate patient-ventilator dyssynchrony, abolish transpulmonary pressure spikes, and reduce metabolic oxygen consumption.
- Early Prone Positioning: Instituted for $\ge 16\text{ hours/day}$. Prone positioning homogenizes the vertical dorsal-to-ventral pleural pressure gradient ($\Delta P_{pl}$), relieves cardiac compressive atelectasis on the left lower lobe, and recruits dependent dorsal lung regions without increasing airway pressures.
- Transpulmonary Pressure Optimization via Esophageal Balloon:
- Measured end-expiratory esophageal pressure ($P_{es,exp}$) is $14\text{ cmH}_2\text{O}$.
- End-expiratory transpulmonary pressure: $$P_{L,exp} = \text{PEEP} - P_{es,exp} = 12 - 14 = -2\text{ cmH}_2\text{O} \quad \text{(Negative = Cyclic Alveolar Collapse)}$$
- PEEP is increased from $12$ to $16\text{ cmH}_2\text{O}$, bringing $P_{L,exp} = +2\text{ cmH}_2\text{O}$, stabilizing functional residual capacity (FRC).
- Transition Criteria to HFOV / VV-ECMO:
- If driving pressure remains $> 15\text{ cmH}_2\text{O}$ or $P_{plat} > 30\text{ cmH}_2\text{O}$ despite prone positioning, immediately transition to High-Frequency Oscillatory Ventilation (HFOV) (CD-HFOV: mean airway pressure $3\text{--}5\text{ cmH}_2\text{O}$ above conventional $\bar{P}_{aw}$, frequency $8\text{--}10\text{ Hz}$).
- If $OI > 40$ persists for $> 4\text{ hours}$ or refractory hypercapnia with $\text{pH } < 7.15$ ensues, execute emergent Veno-Venous (VV) ECMO cannulation via bicaval dual-lumen cannula.
Case 4: Dynamic Hyperinflation & Arrest in Status Asthmaticus
Clinical Presentation & Post-Intubation Arrest
A 10-year-old child ($30\text{ kg}$) with acute near-fatal asthma refractory to continuous nebulized albuterol, IV magnesium sulfate, and IV terbutaline is intubated in the ED due to respiratory arrest and lethargy. A $6.0\text{ mm}$ cuffed ETT is secured. Immediately following connection to the transport ventilator ($V_T = 300\text{ mL}$, $RR = 28\text{ bpm}$, $I:E = 1:2$, $\text{PEEP} = 5\text{ cmH}_2\text{O}$), the child develops profound bradycardia and loses central pulses: Pulseless Electrical Activity (PEA) Cardiac Arrest.
flowchart TD
    A["Rapid Set Rate (28 bpm) + Short Expiratory Time (1.4 s) in Severe Bronchospasm"] --> B["Gross Expiratory Time Inadequacy (Req τ_exp > 1.2 s, needing > 4 s)"]
    B --> C["Progressive End-Expiratory Breath Stacking (Dynamic Hyperinflation)"]
    C --> D["Intrinsic PEEP (Auto-PEEP) Climbs to > 25 cmH2O"]
    D --> E["Intrathoracic Pressure Equalizes with CVP/MSFP"]
    E --> F["Venous Return (ΔP_VR = MSFP - RAP) Drops to Zero"]
    F --> G["Severe RV Preload Starvation -> Zero Cardiac Output -> PEA Arrest"]
Pathophysiological Mechanism of Arrest
In severe bronchospasm, airway resistance ($R_{aw}$) rises to $> 30\text{--}50\text{ cmH}_2\text{O/L/s}$. With a respiratory system compliance ($C_{rs}$) of $0.03\text{ L/cmH}_2\text{O}$, the expiratory time constant is:
$$\tau_{exp} = R_{aw} \times C_{rs} = 40 \times 0.03 = 1.2\text{ seconds}$$Complete passive expiration requires at least $4\text{ to }5\times \tau_{exp} = 4.8\text{ to }6.0\text{ seconds}$. At a set rate of $28\text{ bpm}$ ($T_{tot} = 2.14\text{ s}$, $T_E = 1.43\text{ s}$), each cycle truncates exhalation by $> 3.5\text{ seconds}$, stacking $> 100\text{ mL}$ of trapped gas per breath.
The resulting intrathoracic pressure of $> 25\text{ cmH}_2\text{O}$ collapses the inferior and superior vena cavae, completely abolishing systemic venous return:
$$\dot{Q}_{VR} = \frac{MSFP - RAP}{R_{VR}} \to 0$$DO NOT ADMINISTER EPINEPHRINE FIRST!
- Disconnect the ETT from the ventilator circuit immediately.
- Manually compress the bilateral chest wall to facilitate exhalation of trapped volume. A prolonged, audible rush of air will escape the ETT.
- Within 10–20 seconds of releasing dynamic hyperinflation, intrathoracic pressure drops, venous return floods the right ventricle, and spontaneous pulse/blood pressure return instantaneously.
graph TD
    A1["Post-Intubation PEA Arrest in Asthmatic"] --> B1["IMMEDIATE Ventilator Disconnection"]
    B1 --> C1["Manual Bimanual Chest Compression (Gas Decompression)"]
    C1 --> D1["Audible Gas Decompression Rush -> RAP Falls"]
    D1 --> E1["Immediate Restoration of Pulses & Circulation"]
    E1 --> F1["Re-initiate Ultra-Low-Rate Permissive Hypercapnia Ventilation"]
Controlled Post-Resuscitation Mechanical Strategy
| Ventilator Setting | Initial Fatal Setting | Corrected Lung-Protective Strategy | Pathophysiological Objective |
|---|---|---|---|
| Mode | VC-CMV | PC-CMV or VC-CMV with square wave | Decelerating flow or constant flow with long $T_E$ |
| Tidal Volume ($V_T$) | $300\text{ mL}$ ($10\text{ mL/kg}$) | $180\text{--}210\text{ mL}$ ($6\text{--}7\text{ mL/kg}$) | Prevents volumetric alveolar overdistension |
| Respiratory Rate | $28\text{ bpm}$ | $8\text{--}10\text{ bpm}$ | Crucial: Expands $T_{tot}$ to $6.0\text{--}7.5\text{ s}$ |
| Inspiratory Time ($T_I$) | $0.71\text{ s}$ | $0.80\text{--}1.00\text{ s}$ | Ensures sufficient time for gas delivery |
| Expiratory Time ($T_E$) | $1.43\text{ s}$ ($I:E = 1:2$) | $5.00\text{--}6.50\text{ s}$ ($I:E = 1:5\text{--}1:6$) | Provides $> 4\text{--}5\ \tau_{exp}$ for complete emptying |
| Extrinsic PEEP | $5\text{ cmH}_2\text{O}$ | $0\text{--}4\text{ cmH}_2\text{O}$ (Low / ZEEP) | Minimizes baseline expiratory resistance threshold |
| Target Plateau Pressure | $> 40\text{ cmH}_2\text{O}$ | $\le 30\text{ cmH}_2\text{O}$ | Strict protection against barotrauma/pneumothorax |
| Target Acid-Base | Normalization attempted | Permissive Hypercapnia ($\text{pH } \ge 7.15$, $\text{PaCO}_2\ 60\text{--}90$) | Avoids lethal air trapping to chase normal $\text{PaCO}_2$ |
Case 5: Tracheostomy False Passage in Home Ventilated Child
Clinical Presentation & Emergency Airway Trap
A 5-year-old child ($18\text{ kg}$) with Spinal Muscular Atrophy (SMA) Type 1 on home mechanical ventilation via a $4.5\text{ mm}$ cuffed Bivona tracheostomy tube presents to the emergency department following an accidental decannulation during physical therapy. The home nurse attempted immediate blind recannulation using a spare $4.5\text{ mm}$ tube.
Upon reconnection to the portable ventilator:
- High peak inspiratory pressure alarm sounds continuously ($> 50\text{ cmH}_2\text{O}$).
- Delivered tidal volume drops from $140\text{ mL}$ to $< 15\text{ mL}$.
- The child becomes severely cyanotic ($\text{SpO}_2\ 52\%$, heart rate $48\text{ bpm}$).
- Palpation of the neck and upper anterior chest reveals rapid, extensive crepitus and subcutaneous emphysema tracking up to the mandible.
flowchart TD
    A["Accidental Tracheostomy Decannulation in SMA-1 Child"] --> B["Blind Forcible Reinsertion of Tracheostomy Tube"]
    B --> C["Tube Dissects Pretracheal Fascial Plane (False Passage)"]
    C --> D["Positive Pressure Breaths Pump Gas into Mediastinum & Subcutaneous Tissues"]
    D --> E["Total Airway Occlusion + High Peak Pressure + Massive Subcutaneous Emphysema"]
    E --> F["Immediate Step: Deflate Cuff & Remove Misplaced Tracheostomy Tube"]
    F --> G["Occlude Stoma with Gauze & Perform Bag-Mask Ventilation from Above"]
    G --> H["Definitive Track Navigation: Tracheal Tube Introducer / Fiberoptic Scope"]
Algorithmic DOPE Troubleshooting & Emergency Management
- D - Dislodgement / Displacement: False tract creation into the pretracheal space is the single most common cause of fatal airway obstruction following recannulation.
- O - Obstruction: Mucus plug or crust in the cannula lumen.
- P - Pneumothorax / Tension Gas: Secondary to pretracheal dissection tracking into pleural cavities.
- E - Equipment Failure: Circuit disconnect, exhalation valve failure.
Step-by-Step False Passage Rescue Sequence
- Immediate Decompression & Removal: Instantly deflate the tracheostomy cuff and remove the misplaced tube. Continuing positive pressure through a false passage forces gas into the deep cervical fascia and anterior mediastinum, precipitating tension pneumomediastinum.
- Upper Airway Oxygenation: Cover the stoma with a sterile gloved finger or occlusive gauze pad. Apply standard pediatric Bag-Valve-Mask (BVM) ventilation with $100\%\ \text{O}_2$ from above (oral/nasal) using an appropriately fitted mask and jaw-thrust maneuver.
- Controlled Stomal Recannulation:
- Lubricate a pediatric Tracheal Tube Introducer (gum elastic bougie) or a soft pediatric suction catheter.
- Gently navigate the true tracheal lumen under direct visualization using a pediatric flexible bronchoscope or fiberoptic stylet.
- Rail-road an uncuffed $3.5\text{ mm}$ or $4.0\text{ mm}$ ETT (downsized by $0.5\text{--}1.0\text{ mm}$) over the bougie into the true trachea.
- Verification of Tracheal Position: Confirm bilateral symmetrical breath sounds, continuous 6-phase square wave capnography ($\text{EtCO}_2 > 30\text{ mmHg}$), and flexible endoscopic visualization of tracheal rings and distal carina.
Case 6: Post-Extubation Laryngeal Stridor and Impending Failure
Clinical Presentation & Airway Dynamics
An 18-month-old toddler ($11\text{ kg}$) is extubated in the PICU following 7 days of invasive mechanical ventilation for septic shock and secondary ARDS. The child was intubated with an uncuffed $4.5\text{ mm}$ ETT. Prior to extubation, a cuff leak test was performed by deflating the cuff / occluding the ETT: zero audible leak was detected at airway pressures up to $30\text{ cmH}_2\text{O}$ (Negative Cuff Leak).
Within 20 minutes post-extubation:
- The toddler develops loud biphasic stridor, hoarse cry, severe suprasternal and subcostal retractions, and agitation.
- Respiratory rate is $54\text{ breaths/min}$; heart rate is $175\text{ bpm}$.
- Pulse oximetry on room air declines from $98\%$ to $87\%$.
flowchart TD
    A["7 Days Intubation with Tight Uncuffed ETT"] --> B["Ischemic Pressure Necrosis at Cricoid Ring"]
    B --> C["Post-Extubation Mucosal Hyperemia & Subglottic Edema"]
    C --> D["Airway Radius Halved: 4 mm -> 2 mm (1 mm Circumferential Edema)"]
    D --> E["Airway Resistance Surges 16-Fold (Poiseuille Law: R ∝ 1/r^4)"]
    E --> F["Severe Inspiratory Negative Pressure Swings & Work of Breathing"]
    F --> G["Tiered Intervention: Nebulized Racemic Epinephrine + IV Dexamethasone + HFNC/CPAP"]
Physical Derivation: The Poiseuille Law of Pediatric Airway Resistance
The infant subglottic airway at the non-distensible cricoid ring is the narrowest anatomical point of the upper airway. Laminar gas flow resistance is governed by Poiseuille's equation:
$$R_{airway} = \frac{8 \eta l}{\pi r^4}$$Where $\eta$ is gas viscosity, $l$ is airway length, and $r$ is airway radius.
If the normal infant subglottic radius is $r_1 = 2.0\text{ mm}$ (diameter $4.0\text{ mm}$), and post-extubation inflammatory edema deposits just $0.5\text{ mm}$ of circumferential mucosal swelling ($r_2 = 1.5\text{ mm}$):
$$\frac{R_2}{R_1} = \left( \frac{r_1}{r_2} \right)^4 = \left( \frac{2.0}{1.5} \right)^4 = (1.333)^4 = 3.16 \quad (316\%\text{ increase in resistance})$$If edema increases to $1.0\text{ mm}$ ($r_3 = 1.0\text{ mm}$):
$$\frac{R_3}{R_1} = \left( \frac{2.0}{1.0} \right)^4 = (2.0)^4 = 16.0 \quad (1600\%\text{ surge in resistance!})$$This dramatic, exponential rise in resistance causes massive inspiratory transpulmonary pressure swings, rapid diaphragmatic fatigue, and impending catastrophic upper airway closure.
Tiered Rescue & Escalation Protocol
graph TD
    A["Post-Extubation Stridor & Retractions"] --> B["Step 1: Inhaled Racemic Epinephrine (0.05 mL/kg 2.25% in 3 mL Saline)"]
    B --> C["Step 2: IV Dexamethasone (0.5 mg/kg, Max 10-16 mg)"]
    C --> D["Step 3: High-Flow Nasal Cannula (HFNC 2 L/kg/min) or CPAP (6-8 cmH2O)"]
    D --> E{"Reassessment at 30-60 Minutes: Stridor & Retractions Resolved?"}
    E -- Yes --> F["Maintain Humidified Support + Monitor Rebound Effect at 2-3 Hours"]
    E -- No --> G["Impending Exhaustion / Desaturation / Lethargy"]
    G --> H["Immediate Reintubation with Downsized ETT (0.5-1.0 mm smaller) with Video Laryngoscopy"]
Medical & Non-Invasive Intervention Summary
| Modality | Formulation / Dosing | Mechanism of Action | Monitoring & Clinical Pitfalls |
|---|---|---|---|
| Nebulized Racemic Epinephrine | $0.05\text{ mL/kg}$ of $2.25\%$ solution (max $0.5\text{ mL}$) diluted in $3\text{ mL}\ 0.9\%\ \text{NaCl}$ | $\alpha_1$-adrenergic precapillary vasoconstriction shrinking subglottic mucosal edema | Peak effect $15\text{--}30\text{ min}$; Rebound hyperemia occurs at $2\text{--}3\text{ hours}$; mandates continuous PICU monitoring |
| Systemic Corticosteroids | Dexamethasone $0.5\text{ mg/kg}$ IV (max $10\text{--}16\text{ mg}$) or Methylprednisolone $1\text{ mg/kg}$ | Inhibits capillary leak, decreases inflammatory transcription factors | Onset requires $4\text{--}6\text{ hours}$; ideally initiated $12\text{--}24\text{ hours}$ prior to planned high-risk extubation |
| Non-Invasive CPAP / HFNC | HFNC at $2.0\text{ L/kg/min}$ or CPAP $6\text{--}8\text{ cmH}_2\text{O}$ | Delivers continuous positive distending pressure, stenting subglottic collapse | Reduces work of breathing; warm humidification prevents mucosal crusting |
| Heliox ($70/30$ or $80/20$) | Helium-Oxygen mixture ($70\%\ \text{He} / 30\%\ \text{O}_2$) | Decreases gas density, converting turbulent flow in narrowed subglottis to laminar flow | Ineffective if $\text{FiO}_2 > 0.40$ required; requires specialized calibrated flowmeter |
Master Diagnostic & Mechanical Board Spotter Checklist
Waveform Spotter Archetypes & Scalar Diagnostics
flowchart LR
    A["Ventilator Scalar Waveform Spotter"] --> B["Flow-Time Scalar Anomalies"]
    A --> C["Pressure-Time Scalar Anomalies"]
    A --> D["Pressure-Volume & Flow-Volume Loops"]

    B --> B1["Auto-PEEP: Flow does not reach zero baseline before next breath"]
    B --> B2["Secretion Flutter: High-frequency irregular oscillations on expiratory limb"]

    C --> C1["Flow Starvation: Dished/concave pressure rise + W-shaped Pes drop"]
    C --> C2["Double Triggering: Two mechanical cycles separated by < 50% T_I"]

    D --> D1["Beaking / Overdistension: Bird-beak deflection at high lung volumes"]
    D --> D2["Expiratory Scooping: Deep concave bite in flow-volume loop"]
Emergency Spotter Decision Matrix
| Waveform / Clinical Spotter Sign | Definitive Pathophysiologic Diagnosis | Immediate Bedside Action & Corrective Setting |
|---|---|---|
| Non-zero expiratory flow baseline + acute hypotension | Dynamic Hyperinflation & Severe Auto-PEEP | Disconnect circuit immediately; compress chest manually; lower $RR$ ($8\text{--}12\text{ bpm}$); extend $T_E$ ($I:E = 1:4$). |
| "Dished" concave inspiratory pressure curve + excessive patient work | Flow Starvation / Flow Undershoot | Switch to decelerating flow; increase flow rate / pressure rise time; increase pressure support level. |
| Two consecutive ventilator cycles delivered within $< 50\%\ T_I$ | Double Triggering / Breath Stacking | Increase set $V_T$ or $T_I$; increase sedation; optimize trigger sensitivity. |
| Sawtooth ragged oscillations on flow-time scalar | Airway Secretions / Circuit Condensate | Perform inline endotracheal suctioning; drain condensate from water traps. |
| High Peak Pressure + Normal Plateau Pressure ($PIP - P_{plat} > 15$) | Increased Resistive Work (ETT Kinking, Mucus Plug, Bronchospasm) | Suction ETT; pass catheter to rule out tube kink; administer inhaled bronchodilator. |
| High Peak Pressure + High Plateau Pressure ($P_{plat} > 30$, $\Delta P > 15$) | Decreased Respiratory System Compliance (Pneumothorax, ARDS, Atelectasis) | Perform emergency chest auscultation/POCUS to rule out tension pneumothorax; titrate PEEP; prone position. |
| Sudden loss of delivered $V_T$ in PC mode + absent unilateral breath sounds | Right Mainstem Endobronchial Intubation | Deflate cuff; withdraw ETT by $1\text{--}2\text{ cm}$; verify bilateral breath sounds and symmetric chest rise. |
| Persistent expiratory flow baseline deficit on volume scalar | Large Circuit / Endotracheal Tube Cuff Leak | Check pilot balloon; inflate ETT cuff to $20\text{--}25\text{ cmH}_2\text{O}$; inspect circuit connections. |